RE-EXAMINING PROSTATE FINE NEEDLE ASPIRATION BIOPSY IN THE 21ST CENTURY: CANCER CYTOLOGY PATTERNS AS SEEN WITH ISUP GRADING OF PROSTATIC CARCINOMA
Published in Annals of Urology
John Maksem ✉
John MaksemCorresponding author More articles by this author →
Published
1 Foreward#
In this presentation, we have built upon and extended a data set that we originally assembled to analyze and translate Gleason histology grading into patterns useful for grading prostate cytology preparations as obtained from fine needle aspirations of the prostate gland[1]. This expanded data set, again of matched biopsy/cytology pairs was finalized in early 1988, but outside of its passing mention in the “Urologic Clinics of North America”[2], our findings were never officially published. The latter study involved a collaborative effort involving myself (now retired), the acclaimed urologic pathologist—Dr. Myron Tannenbaum (now deceased), and the originator of Gleason grading—Dr. Donald Gleason (now deceased). The study encompassed biopsy-to-cytology correlations (obtained from the same cores of prostate sextant biopsies that were collected into a polyfunctional fixative and processed, simultaneously, as hematoxylin and eosin histology slides and cytocentrifuge cytology slides). It comprised prostate cancer cases from 302 men. Because of recent changes in prostate histology pattern assignment and grading generally accepted by the International Society of Urological Pathology (ISUP; born of a consensus meeting for grading of prostatic carcinoma held in September 2019, in Nice, France), I have retrofitted our otherwise unpublished observations into patterns proposed by the ISUP grading system[3] with the purpose of representing ISUP prostate tissue patterns as they would appear in matched cytological preparations if they were collected today. It is our goal to show how prostate cytology can still have relevancy to today’s practice of urological cytopathology. What follows, rather than a strictly scientific study, is a historical vignette regarding past successes with fine needle aspiration biopsy of the prostate that is accompanied by a “picture book” or “mini atlas” of cytology images meant to show today’s cytopathologists just how much can be seen with a simple, readily available and cost-effective technique. It is also my hope to encourage the continued exposure of pathology residents and cytopathology fellows to FNA prostate cytology and not to banish a practice that once dominated prostate cancer diagnosis to “a dustbin of now-ignored methodologies”.
2 The Comings and Goings of Fine Needle Aspiraton Biopsy of the Prostate#
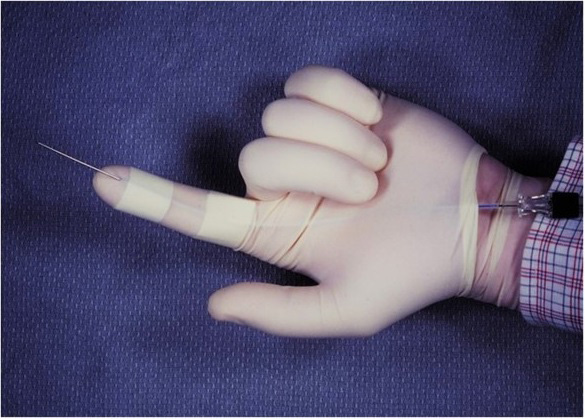
Prostate fine needle aspiration (FNA) biopsy was born out of necessity. Before the 1960s, prostate biopsy required a transperineal approach, with open perineal prostate biopsy of the anesthetized patient used as the gold standard for prostate cancer diagnosis. Beginning in the 1920s, the perineal approach was considered obligatory because of the very real concern for fecal contamination and systemic infection that was associated with a transrectal approach, especially in a pre-antibiotic era. Since the 1980s, transrectal sextant biopsy with cutting needles became the preferred method for prostate diagnosis due to the development and popularization of transrectal ultrasound, the relative ease and convenience of the transrectal approach to tissue acquisition, and the ability of biopsied tissue to offer the pathologist a universally familiar histological sample[4]. However, there was a time, beginning in the 1960s, that a method introduced by Franzen, Giertz, and Zajicek became popular, beginning in Europe, and came to dominate the field of prostate diagnosis for about 30 years—fine needle aspiration (FNA) biopsy.[5]
In 1966, Esposti reviewed his experience with the cytologic diagnosis of prostate tumors using transrectal aspiration. He reported on 1,110 cases and found that FNA biopsy was successful for diagnosing prostate tumors and benign prostate conditions,[6] and 11 years later, with an eye towards investigating possible complications (because this was a transrectal biopsy) Esposti, Elman, and Norlen examined their problems with FNA prostate biopsy.[7]. Among their patients, they found 4 cases of coliform-sepsis, one with a fatal outcome, but these were discovered only after more than 14,000 transrectal FNA biopsies were performed with Franzen’s apparatus. A few cases of transient febrile reaction and urinary contamination were also recognized, and the authors noted that one of their patients with sepsis and two with febrile reactions belonged to a relatively small group of men that were referred from the Department of Rheumatology, leading the authors to conclude that individuals with rheumatic diseases run a higher risk of procedural complications.
In 1975, Sonnenschein examined the effectiveness of transrectal FNA cytology to diagnose prostate cancer.[8] His publication addressed 403 patients suspected of having prostate cancer based on rectal examination and he found a 93.35% accuracy rate for cytology. In 2.39% of the men, cancer was not detected by FNA, whereas in 3.72%, a cytological, but not a histological diagnosis was made. Sonnenschein emphasized the value of FNA biopsy and remarked that FNA could be carried out at any time, without preparation, anesthesia, or danger to the patient. Similar findings were echoed the following year by Kelsey, Kohler, MacKinney, and Kline;[9] and in the same year that the Kelsey paper appeared, Bandhauer, Spieler, and Egle likewise concluded that FNA “…is an ideal method of early recognition of prostatic carcinoma, and its reliability is equal to the more elaborate transrectal or transperineal needle biopsy.”[10]
In 1977, Ackermann and Muller reported a retrospective analysis of 645 simultaneous perineal punch biopsies and transrectal FNAs for prostatic cancer diagnosis to see whether carcinoma could be detected with FNA biopsy as frequently and as reliably as with perineal punch biopsy.[11] They found prostate cancer in 39.1% of men using both techniques. Cancer was diagnosed more often by perineal punch than by FNA biopsy (36.1% vs 27.7%), largely due to technical issues (with doubtful results and unsatisfactory preparations observed more frequently with FNA). On the upside, false positive cytological outcomes did not occur, and the authors concluded that “…cytological evaluation of aspirated prostatic cells appears reliable. A definite morphological diagnosis can be expected with this technique.” In that same year, Moller reported on 761 FNA biopsy specimens in which 83% of 303 cancers were diagnosed by this method.[12] Again, this lower yield pointed to the possibility that either lack of standardization, lack of experience, or technical problems plagued specimen collection or preparation (or both).
After 20 years of experience, Esposti and Franzén collaborated in re-evaluating prostate FNA diagnosis of carcinoma.[13] They advised that by repeating aspiration biopsies in clinically suspected cases, the danger of a false negative report could be minimized, and good correlation existed between cytologic and histologic findings, so much so that among 350 men with prostate cancer, disease was detected cytologically in 96% by FNA. Furthermore, they reiterated that, “…a false positive diagnosis is not to be feared when the diagnostic work is performed by a trained staff.” One year later, Willems and Lowhagen echoed this confidence when they published their greater than 20 years’ experience with the method at the Karolinska.[14] At that time, the cytologic criteria for diagnosing prostate cancer in May Grunwald Giemsa-stained aspirates were institutionally defined, and the authors determined that while the accuracy of the cytological diagnosis of prostate cancer was like that of the histopathologic diagnosis, even at that time, they recognized FNA prostate as less traumatic and more cost effective than histologic biopsy. They reiterated that its accuracy depended very much upon “…the skill of the examiner taking the cell samples and on the alertness of the cytopathologist for possible diagnostic pitfalls.” They further stated that cytologic grading of prostatic carcinoma into well, moderately, and poorly differentiated types (although not precisely equivalent to the either the Gleason or ISUP grading methods of today) could be significantly correlated to histopathologic grading, clinical stage, response to therapy and survival, and to the degree of tumor differentiation (as determined by DNA ploidy).
Soon thereafter, Zattoni, Pagano, Rebuffi and Costantin published their four years’ experience with the method.[15] As with others before them, they agreed that FNA prostate was quick, safe, and reliable. They advised that case findings could be improved when several FNA biopsies were performed at a single setting (wherein complications remained rare). In their study, a cytologic diagnosis was obtained in 511 consecutive patients and 195 cytologic diagnoses were compared with histologic findings obtained from the same patients. There was 96.42% correlation of “benign” vs “malignant” outcomes. The findings in 127 histologically graded prostatic cancers were then compared with the cytologic differentiation observed in aspiration smears of the same patients and cytological grading corresponded favorably to histologic grading in 85.8%. As FNA prostate crossed the English Channel from mainland Europe, Anandan, Rowell, MacKenzie, Johnson, and Gingell published a retrospective study of all Franzen FNAs undertaken at the Southmead Hospital in Bristol, UK, between January 1978 and December 1981. A total of 1,043 FNA cytologies were examined from 753 patients, and the diagnosis of prostate cancer was missed in only 2 men.[16] Remarkably, in 21 men with histologically benign prostate biopsies, carcinoma was detected with the FNA technique. Furthermore, of 91 men who had carcinoma in their prostatectomy specimens, in 65 (72%) the cytological and histological grading were identical.
One of the early United States’ reports regarding FNA prostate was that of Chodak, Steinberg, Bibbo, Wied, Straus, Vogelzang, and Schoenberg.[17] This comprised an experiential review conducted over an 18-months period. FNA biopsy was the only technique used in 75 men and cancer was diagnosed in 19. Two patients were not treated because a core biopsy performed elsewhere was negative, whereas aspiration and transperineal core biopsies were performed in 62 others. The sensitivity of FNA to diagnose prostate cancer was 98% (45 of 46 biopsies) while, at the same time, only 81% (37 of 46) of core biopsies detected cancer. Authors encouraged the widespread use of this technique in the United States. That same year, Ljung, Cherrie, and Kaufman reported on 103 cases with histological follow-up.[18] Similar results followed. The sensitivity for FNA was 95%, specificity 97%, and efficiency 87%. The matched core needle biopsy had a sensitivity of 76%, specificity 100% and efficiency 71%. The following year, Layfield, Mukamel, Hilborne, Hannah, Glasgow, Ljung, and deKernion compared FNA cytology to the Gleason grading system.[19] Cytological grade determined by prostate FNA was compared to histological grade in the radical prostatectomy of 30 men. The degree of cytological pleomorphism determined by a consensus-grade of 3 observers correctly predicted the Gleason grade sum range in 80%, and this corresponded to the accuracy of predicting the Gleason grade of the radical prostatectomy specimen by histological examination of cutting needle biopsies and transurethral resection specimens that was reported in the literature.
As a reality check on sustained procedural sensitivity, Graham, Ignatoff, Holland, and Christ of Northwestern University Medical School, offered the results of transrectal FNA biopsies from 133 men but they focused on the outcomes of longitudinal patient follow up[20] They found an initial test specificity of 94%, however, with repeated rectal examinations and biopsies over an 11-years period, additional false negatives appeared. Their data suggested that FNA biopsy had a specificity and sensitivity akin to core biopsy but that “…it is important to re-test patients who have a palpable abnormality and an initially benign biopsy”, further noting that FNA biopsy had the “…simplicity [that] allows for a low threshold of suspicion of subtle abnormalities and for repeating biopsies after negative findings.”
Our entry into prostate FNA came in the early-1980’s at the encouragement of the then president of the American Urological Association, Dr. Martin Resnick (while we were both at Case Western Reserve University in Cleveland, OH). Our first publication, released in 1988 along with our long-time collaborator, Dr Paul W. Johenning, a urologist, was entitled, “Is cytology capable of adequately grading prostate carcinoma? Matched series of 50 cases comparing cytologic and histologic pattern diagnoses”.[1] This study was unique in that it employed a polyfunctional cytological and histological fixative, meaning that cytology was not just collected at the same time as histology, but it was collected from the washings that accumulated in the fixative solution that held the same sextant core tissue biopsies. [see: Cytological and histological fixative formulation and methods for using same. Patent number: 4857300. Filed: July 27, 1987. Date of Patent: August 15, 1989. Inventor: John A. Maksem] In this study, we compared patterns of cellular arrangement among 50 cases of prostate cancer that were studied in these truly simultaneously obtained histological and cytological specimens. Cell patterns were independently scored in a semiquantitative fashion using both histological and cytological material, and “predicted Gleason scores” that were observed in tissue micro-fragment that were assigned to the cytological specimens based on their “pattern” in cytocentrifuge preparations. There was 84% exact agreement between histology and cytology scores and 100% agreement if the score was assigned a range of “+1” or “-1”—this was especially true when assigning Gleason scores of 3+4=7 vs 4+3=7, since there was no reliable method to quantitate the proportionate patterns in cytology preparations. We concluded, with the above proviso, that it was possible to predict corresponding prostate cancer tissue patterns with cytology preparations and to estimate Gleason scores in FNA material. One year later, Jacobs, Vago, and Weiss attempted to use Gleason scoring on prostate FNAs by examining 31 prostate aspirates that had concomitant surgical pathology tissue for correlation.[21] As with our study, they determined that Gleason scoring was possible on FNAs when the aspirated tissue micro-fragments were evaluated. They also noted that, as with the grading approach to prostate cancer advocated by Dr. Donald Gleason[22] (as opposed to prostate cancer grading as contemporaneously promoted by Dr. Fathollah K. Mostofi[23]), qualitative nucleolar appearance was not helpful in tumor grading.
On the other hand, Swedish investigators, Hostetter, Pedersen, Gustafsson, Manson, and Boeryd addressed the diagnosis and localization of prostate carcinoma by FNA and correlated it with histologic whole-organ sections after radical prostatectomy.[24] At the time of biopsy, diagrams of the palpated organ were drawn, depicting the location of the lesion and the site of each biopsy. Then, without the examiners’ knowledge of cytologic data, extirpated prostate glands were examined with whole organ histologic sections, and carcinomas were assigned a Gleason score. The location and extent of all atypical and malignant foci were mapped and the results of preoperative cytologic examination were compared with postoperative histopathologic findings. Not unexpectedly, as with any biopsy method (that is capable of only giving a “best possible scenario” answer when compared to whole-organ examination), this exercise showed a tendency toward underestimation of both the extent and degree of differentiation of the carcinomas using cytologic examination alone. However, in no case were these parameters overestimated by FNA cytology—that is, there were no false positives and no false upgrades of tumor.
In the year following our 1988 position statement on cytological prostate cancer grading and the same year of the confirmatory Jacobs et al assessment of cytological prostate cancer grading, Narayan, Jajodia, Stein, and Tanagho published a study entitled, “A comparison of fine needle aspiration and core biopsy in diagnosis and preoperative grading of prostate cancer.”[25] Their study had 3 objectives: (1) determine whether performing core biopsies and fine needle aspiration in each patient with a prostate nodule increases the detection rate of prostate cancer—it did; (2) assess the accuracy of preoperative grading by fine needle aspiration in predicting the final pathological grade in radical prostatectomy specimens—in their hands, it did not; and (3) examine the usefulness of fine needle aspiration in screening for unsuspected stage A prostate cancer—it was not useful. Of 203 consecutive men undergoing prostate examination, prostate core and fine needle aspiration biopsies were performed in 121 men, and an additional 58 men underwent prostate biopsies just before transurethral resection of the prostate with 24 undergoing radical prostatectomy. As with prior studies, the diagnostic accuracy of FNA was superior to that of core biopsy and performance of both biopsies yielded a higher percentage of positive diagnoses than either biopsy alone; however, in the hands of these investigators, except in poorly differentiated cancers, FNA appeared to be a poor predictor of the final pathological grade.
The following year, Klotz, Shaw, and Srigley from the Sunnybrook Medical Centre, University of Toronto, reported on the accuracy of FNA and core biopsy of the prostate from 88 men with prostatic nodules.[26] All men with positive findings on aspiration also had positive findings on core biopsy, for a positive predictive value for FNA of 100%—this was the favorable result. However, five negative and six “insufficient” results were obtained by FNA, for a negative predictive value for FNA of 88%--this was the detrimental result. Again, this dichotomy of successful collections between cytology and histology raised, in my mind, the likelihood of technical issues with FNA specimen collection and/or fixation. Nonetheless, these authors encouraged the use of FNA as a diagnostic maneuver in the initial assessment of prostatic nodules.
In a 2005 paper presented as part of a tribute to Torsten Lowhagen (a noted teacher and overall giant in the field of cytopathology) at the Lillehammer Lifelong Learning Conference, Pérez-Guillermo, Acosta-Ortega, and Garcia-Solano advocated for the continuing use of prostate FNA in this century.[27] In their paper, they offered a brief historical review of prostate FNA and presented their 20 years’ experience with the method. They opined that despite the worldwide acceptance of the thin-needle core approach, the use of transrectal FNA of palpable prostate abnormalities was cheaper, faster, and easier to perform, and had a lower morbidity than any other technique so far developed. In a 2007 paper that was also presented as part of the tribute to Dr. Lowhagen, we agreed that with the worldwide acceptance of mechanically assisted, ultrasound guided thin needle biopsy of the prostate gland, prostate FNA has fallen out of favor with both urologists and cytopathologists. Nonetheless, we contended that given the cost to submit from 12 to 18 core biopsies per patient, prostate FNA remained more cost effective, expedient, and economical than any other sampling method so far developed for prostate cancer diagnosis. We also concluded that prostate FNA should not be dismissed, outright, as an anachronism from the diagnostic armamentarium of either the urologist or the pathologist,[28] especially in an era of budding immunohistochemical and molecular testing.
Furthermore, even marked by the waning use of prostate FNA as a primary biopsy tool, prostate cytology was shown to have a role in the assessment of core biopsies obtained with thin needle transrectal ultrasound guided tissue biopsy. For example, in a paper entitled, “Does imprint cytology improve the accuracy of transrectal prostate needle biopsy?”, Sayar, Bulut, Bahar, Bahar, Seringec, Resim, and Cıralık evaluated 1,262 transrectal prostate cutting-needle biopsy specimens taken from 100 patients.[29] They reported malignant imprint cytology in 236 specimens (18.7%), 197 (15.6%) of which were confirmed by histologic examination, giving an initial 3.1% (n = 39) discrepancy rate. However, with deeper sectioning of discrepant cores, 14 (1.1% of the original specimens) were then diagnosed as malignant, 3 (0.2%) as atypical small acinar proliferation (ASAP), and 5 (0.4%) as high-grade prostatic intraepithelial neoplasia (HGPIN). 7 of 964 (0.6% of 76.4%) cytologically negative imprint cytologies were histologically malignant. Nonmalignant but abnormal findings were seen in 62 imprint cytology specimens (4.9%) and these were all determined to be due to benign processes. Authors reported that the accuracy, sensitivity, specificity, positive predictive value, negative predictive value, false-positive rate, and false-negative rate of imprint preparations were 98.1%, 96.9%, 98.4%, 92.8%, 99.3%, 1.6%, and 3.1%, respectively. They concluded that even in the absence of FNA collection: “Imprint cytology is a valuable tool for evaluating TRUS-guided core needle biopsy specimens from the prostate. Use of imprint cytology in combination with histopathology increases diagnostic accuracy when compared with histopathologic assessment alone.”
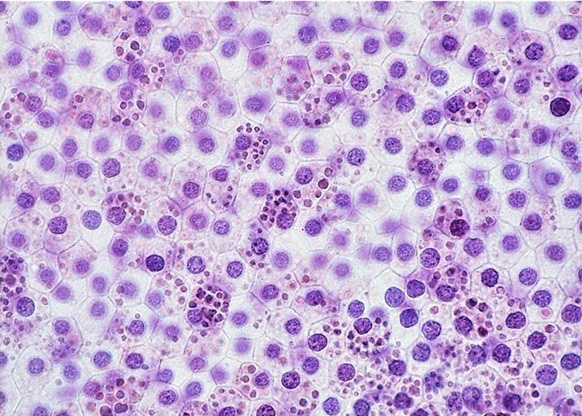
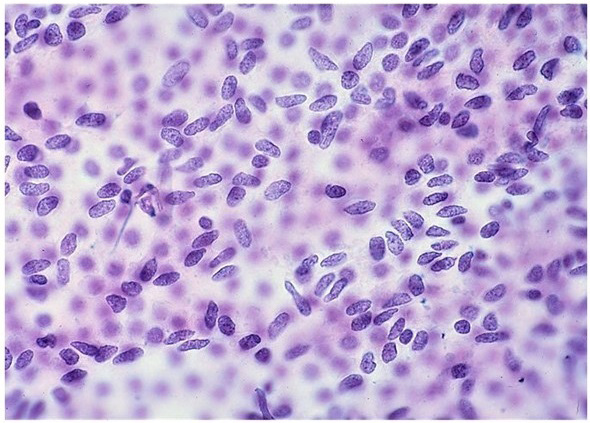
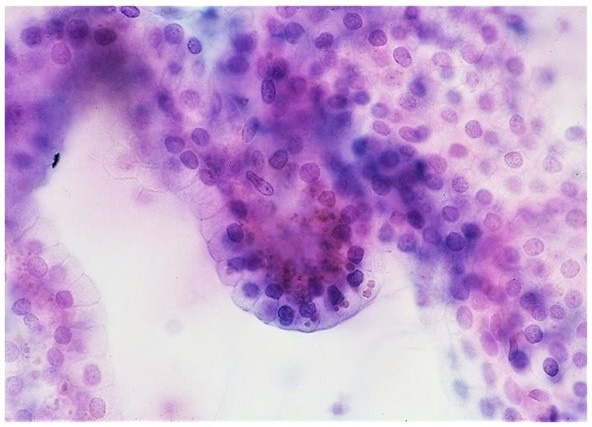
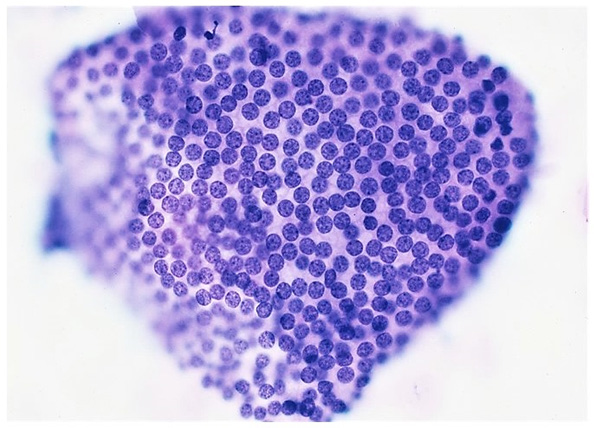
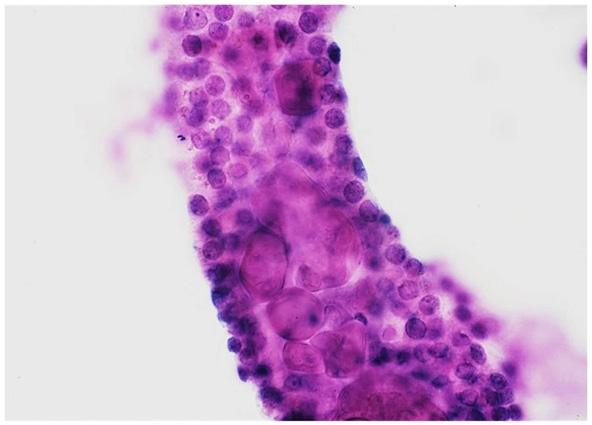
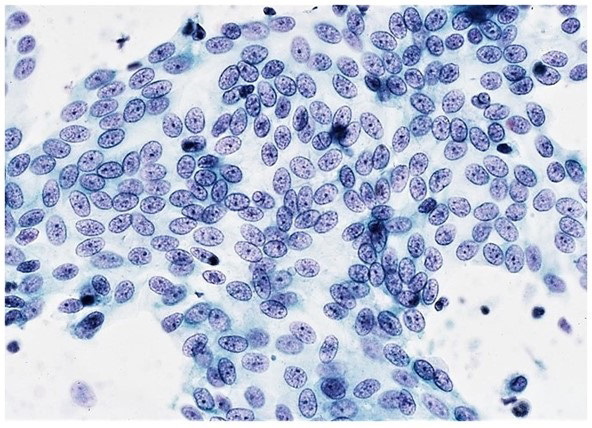
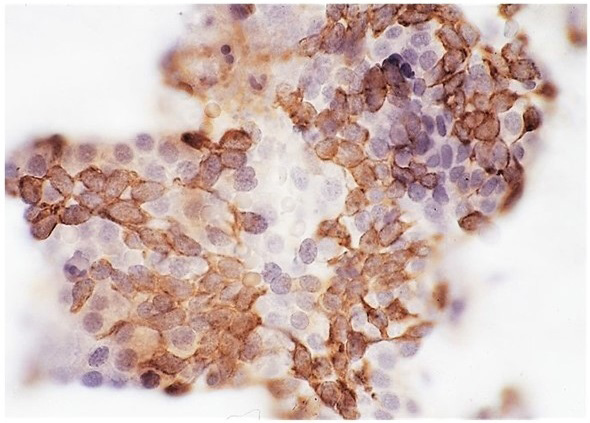
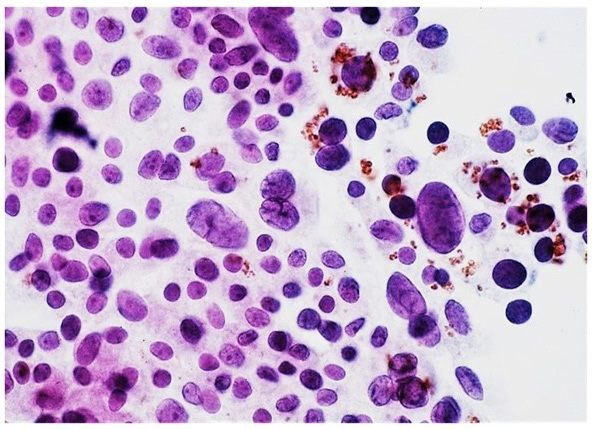
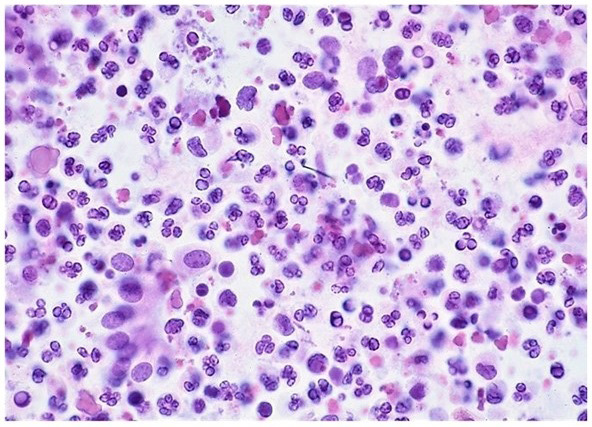
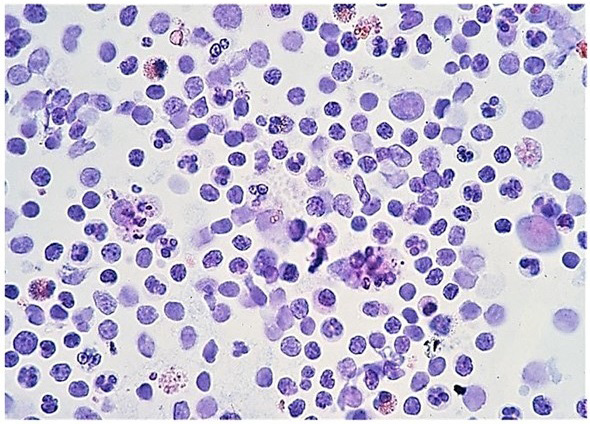
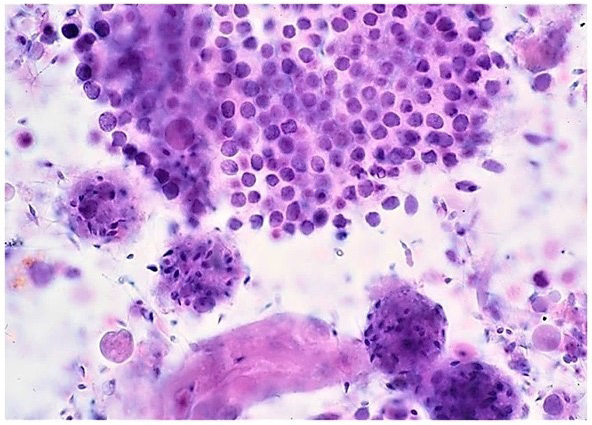
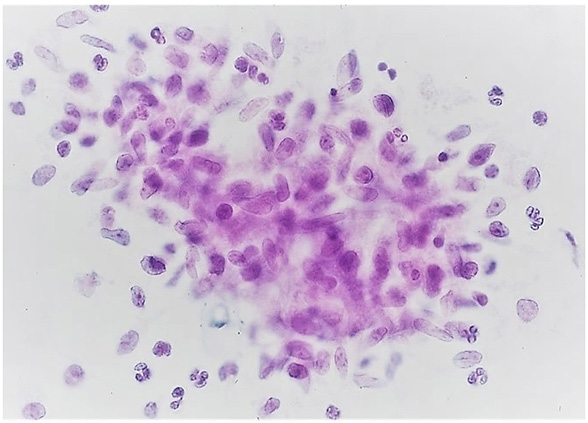
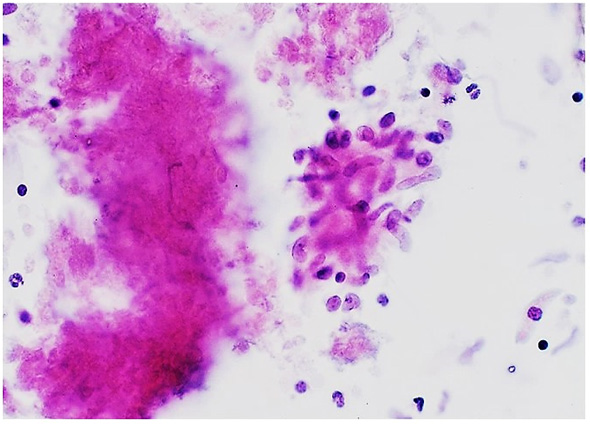
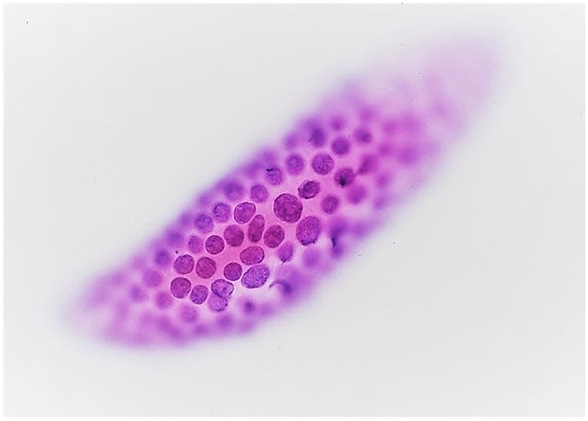
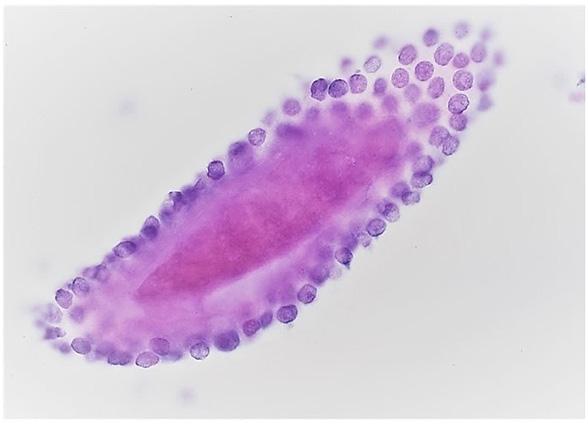
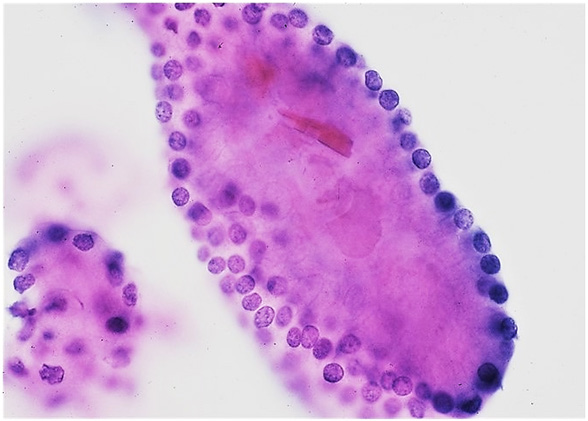
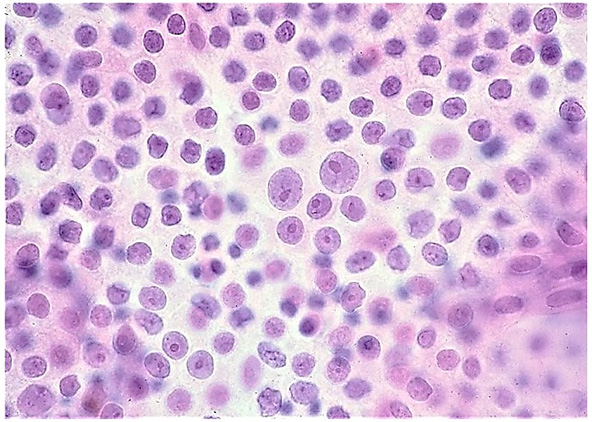
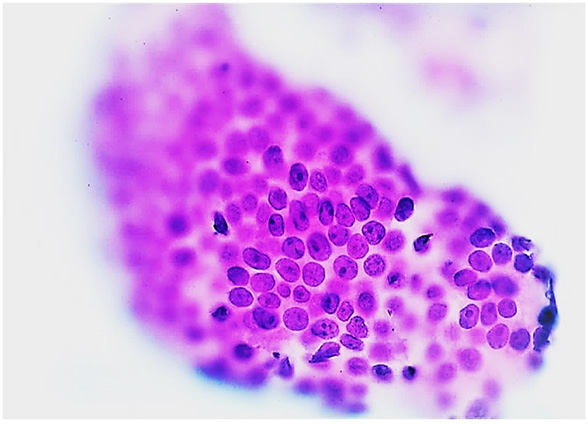
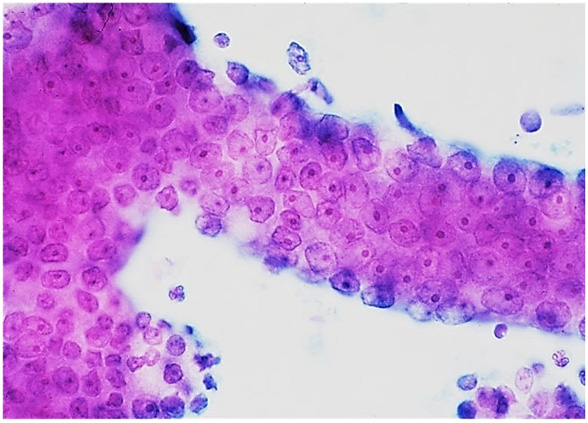
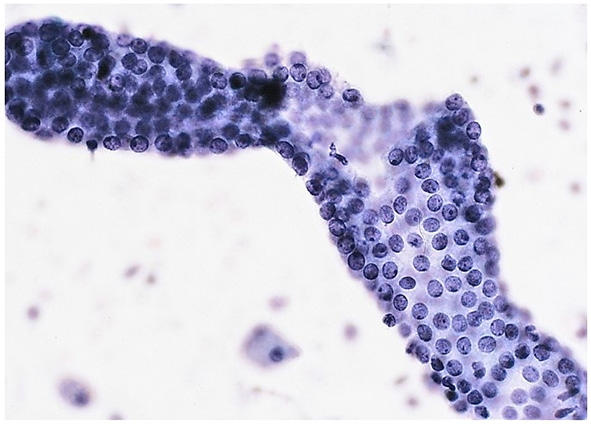
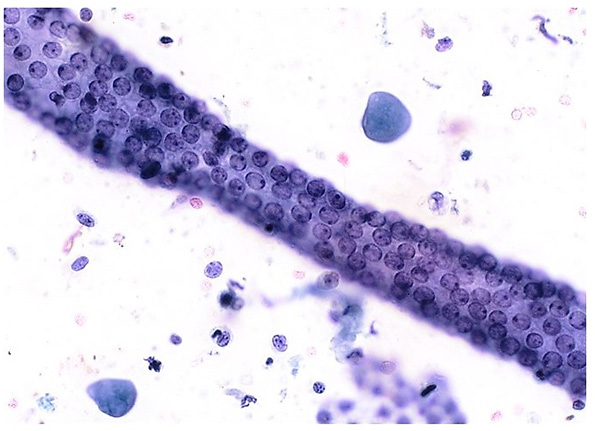
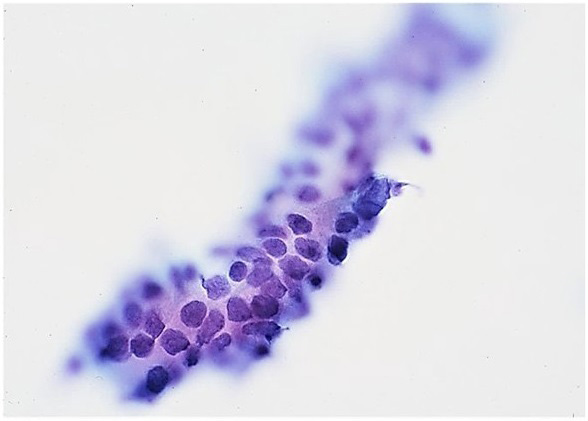
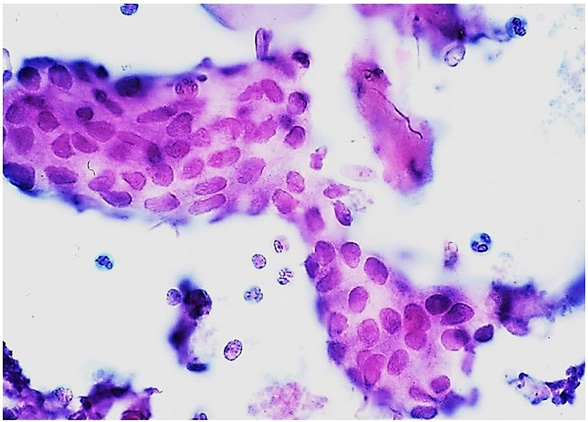
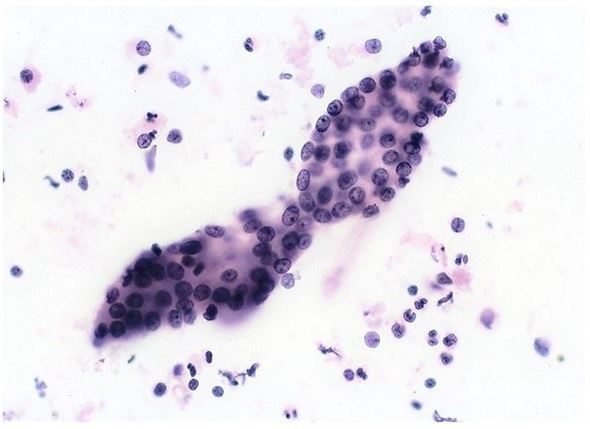
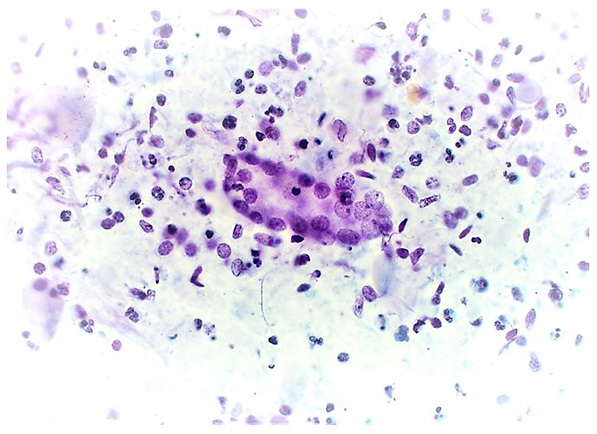
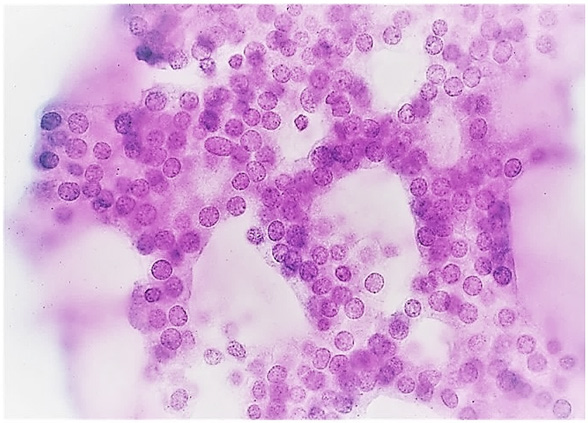
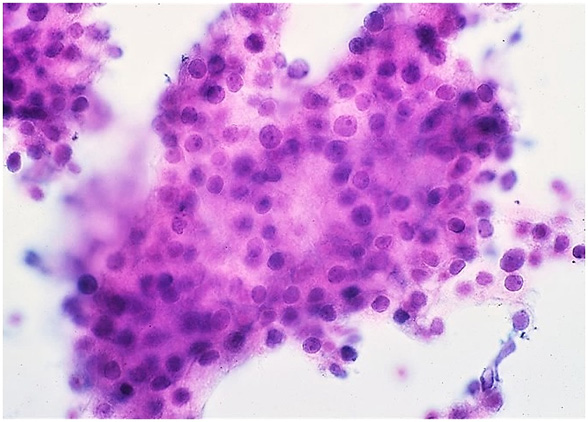
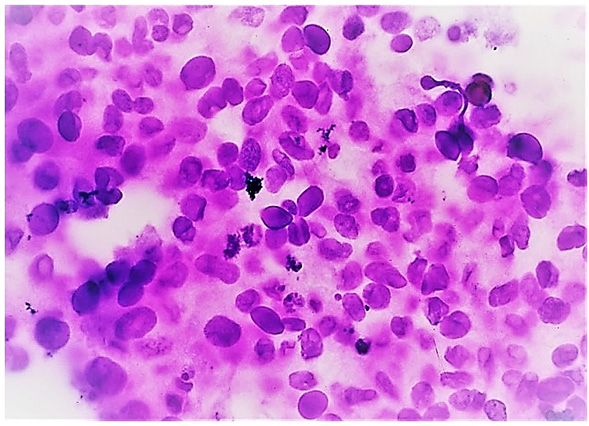
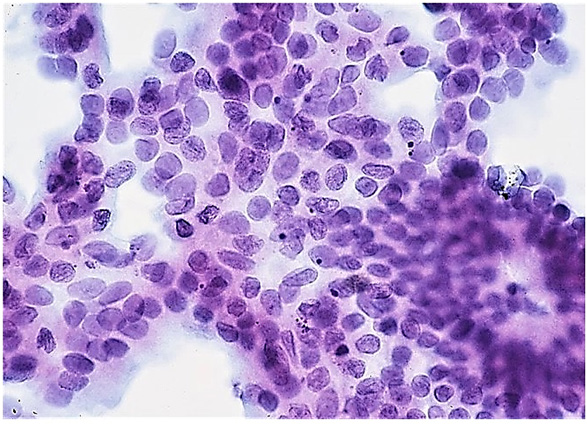
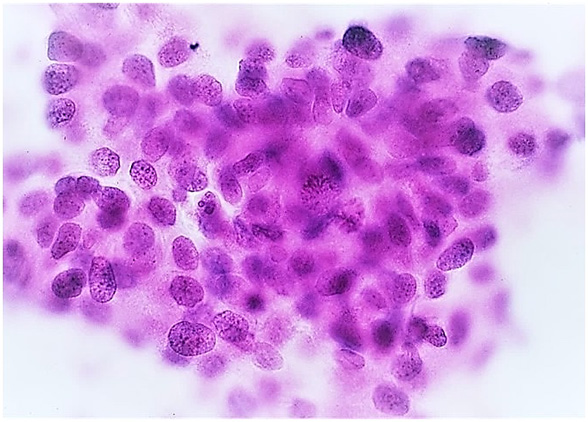
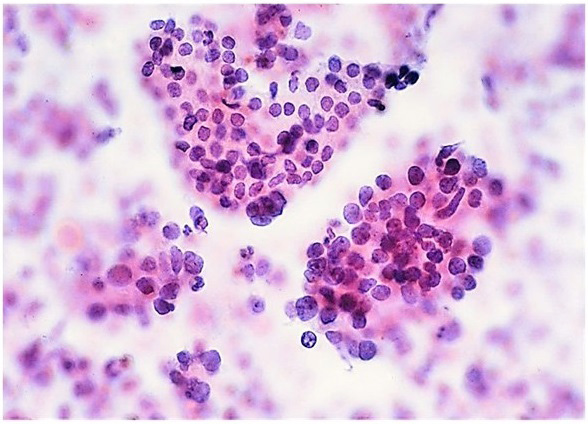
Herein, I have taken it upon myself to re-open the case for prostate cytology, by “retrofitting” our 1988 observations into the ISUP grading system.[3] What follows, rather than a strictly scientific study, is a picture book of cytology images that are meant to show physicians what can be seen with this simple technique and to hopefully advocate for the continued exposure of pathology residents and cytopathology fellows learning FNA prostate cytology.
Table 1 Distribution of cancer grade-groups that were re-evaluated from our 1988 data set and reassigned an ISUP pattern-based grade grouping. *Note, since the quantitation of patterns is not consistently reproducible on cytology slides, grade groups 2 and 3 should realistically be combined into a single category. It is our opinion that ancillary testing such as PTEN, cMYC, and p63 may have future use in stratifying the risk of these patterns.
| GRADE GROUP | 1 | 2 or 3* | 4 or 5 |
|---|---|---|---|
| PATTERN SCORE | 3+3 | 3+4 or 4+3 | 8 through 10 |
| NUMBER OF CASES | 100 | 133 | 69 |
| PERCENT OF CASES | 33% | 44% | 23% |
Table 2 Cancer cytopathology findings by pattern as they corresponded to descriptions of ISUP patterns. Of note, nuclear morphology does not serve in assigning prostate cancers into their pattern groupings.
| PATTERNS SEEN WITH CYTOLOGY | 3 | 4 | 5 |
|---|---|---|---|
| GLANDS | DISCRETE | ||
| OUTER GLANDD CONTOUR | REGULAR | RAGGED | |
| GLAND LUMEN CONFIGURATION | OPEN | SLIT-LIKE | |
| GLAND LUMEN COMPLEXITY | ABSENT | PRESENT | |
| CRIBRIFORM STRUCTURES | REGULAR | RAGGED | |
| COMEDONECROSIS | ABSENT | PRESENT | |
| SOLID TUMOR GROWTH | PRESENT | ||
| INDIVIDUAL DYSHESIVE CELLS | PRESENT |

Article information
- Published
This article is published open access under the CC BY 4.0 licence. CC BY 4.0 · Corrections policy
References 31#
- 1
Maksem JA, Johenning PW. Is cytology capable of adequately grading prostate carcinoma? Matched series of 50 cases comparing cytologic and histologic pattern diagnoses. Urology. 1988 May;31(5):437-44. doi: 10.1016/0090-4295(88)90745-5. PMID: 3284154.
- 2
Maksem JA, Park CH, Johenning PW, Galang CF, Tannenbaum M. Aspiration biopsy of the prostate gland. Urol Clin North Am. 1988 Nov;15(4):555-75. PMID: 2460986.
- 3
van Leenders GJLH, van der Kwast TH, Grignon DJ, Evans AJ, Kristiansen G, Kweldam CF, Litjens G, McKenney JK, Melamed J, Mottet N, Paner GP, Samaratunga H, Schoots IG, Simko JP, Tsuzuki T, Varma M, Warren AY, Wheeler TM, Williamson SR, Iczkowski KA; ISUP Grading Workshop Panel Members. The 2019 International Society of Urological Pathology (ISUP) Consensus Conference on Grading of Prostatic Carcinoma. Am J Surg Pathol. 2020 Aug;44(8):e87-e99. doi: 10.1097/PAS.0000000000001497. PMID: 32459716; PMCID: PMC7382533.
- 4
Schmeusser B, Levin B, Lama D, Sidana A. Hundred years of transperineal prostate biopsy. Ther Adv Urol. 2022 May 21;14:17562872221100590. doi: 10.1177/17562872221100590. PMID: 35620643; PMCID: PMC9128053.
- 5
FRANZEN S, GIERTZ G, ZAJICEK J. Cytological diagnosis of prostatic tumours by transrectal aspiration biopsy: a preliminary report. Br J Urol. 1960 Jun;32:193-6. doi: 10.1111/j.1464-410x.1960.tb03763.x. PMID: 13824614.
- 6
Esposti PL. Cytologic diagnosis of prostatic tumors with the aid of transrectal aspiration biopsy. A critical review of 1,110 cases and a report of morphologic and cytochemical studies. Acta Cytol. 1966 May-Jun;10(3):182-6. PMID: 5227368.
- 7
Esposti PL, Elman A, Norlén H. Complications of transrectal aspiration biopsy of the prostate. Scand J Urol Nephrol. 1975;9(3):208-13. doi: 10.3109/00365597509134213. PMID: 1108177.
- 8
Sonnenschein R. The effectiveness of transrectal aspiration cytology in the diagnosis of prostatic cancer. Eur Urol. 1975;1(4):189-92. PMID: 1233185.
- 9
Kelsey DM, Kohler FP, MacKinney CC, Kline TS. Outpatient needle aspiration biopsy of the prostate. J Urol. 1976 Sep;116(3):327-8. doi: 10.1016/s0022-5347(17)58803-5. PMID: 957500.
- 10
Bandhauer K, Spieler P, Egle N. Evaluation of prostatic cytology in primary diagnosis and clinical course of prostatic carcinoma. Prog Clin Biol Res. 1976;6:329-45. PMID: 1023215.
- 11
Ackermann R, Müller HA. Retrospective analysis of 645 simultaneous perineal punch biopsies and transrectal aspiration biopsies for diagnosis of prostatic carcinoma. Eur Urol. 1977;3(1):29-34. doi: 10.1159/000472050. PMID: 837951.
- 12
Møller JT. Transrectal cytological aspiration biopsy in prostatic disease. Int Urol Nephrol. 1977;9(3):235-40. doi: 10.1007/BF02082169. PMID: 75865.
- 13
Esposti PL, Franzén S. Transrectal aspiration biopsy of the prostate. A re-evaluation of the method in the diagnosis of prostatic carcinoma. Scand J Urol Nephrol Suppl. 1980;55:49-52. PMID: 6938035.
- 14
Willems JS, Löwhagen T. Transrectal fine-needle aspiration biopsy for cytologic diagnosis and grading of prostatic carcinoma. Prostate. 1981;2(4):381-95. doi: 10.1002/pros.2990020406. PMID: 6173871.
- 15
Zattoni F, Pagano F, Rebuffi A, Costantin G. Transrectal thin-needle aspiration biopsy of prostate: four years’ experience. Urology. 1983 Jul;22(1):69-72. doi: 10.1016/0090-4295(83)90354-0. PMID: 6191423.
- 16
Anandan N, Rowell MJ, MacKenzie E, Johnson DH, Gingell JC. Role of Franzen needle aspiration biopsy in carcinoma of the prostate. J R Soc Med. 1983 Oct;76(10):828-30. doi: 10.1177/014107688307601005. PMID: 6631858; PMCID: PMC1439605.
- 17
Chodak GW, Steinberg GD, Bibbo M, Wied G, Straus FS 2nd, Vogelzang NJ, Schoenberg HW. The role of transrectal aspiration biopsy in the diagnosis of prostatic cancer. J Urol. 1986 Feb;135(2):299-302. doi: 10.1016/s0022-5347(17)45619-9. PMID: 3944865.
- 18
Ljung BM, Cherrie R, Kaufman JJ. Fine needle aspiration biopsy of the prostate gland: a study of 103 cases with histological followup. J Urol. 1986 May;135(5):955-8. doi: 10.1016/s0022-5347(17)45936-2. PMID: 3959248.
- 19
Layfield LJ, Mukamel E, Hilborne LH, Hannah JB, Glasgow BJ, Ljung BM, deKernion JB. Cytological grading of prostatic aspiration biopsy: a comparison with the Gleason grading system. J Urol. 1987 Oct;138(4):798-800. doi: 10.1016/s0022-5347(17)43378-7. PMID: 3656536.
- 20
Graham JB, Ignatoff JM, Holland JM, Christ ML. Prostatic aspiration biopsy: an assessment of accuracy based on long-term observations. J Urol. 1988 May;139(5):971-4. doi: 10.1016/s0022-5347(17)42734-0. Erratum in: J Urol 1988 Dec;140(6):1558. PMID: 3283386.
- 21
Jacobs DM, Vago JF, Weiss MA. Gleason grading of prostatic adenocarcinoma on fine-needle aspiration. Diagn Cytopathol. 1989;5(2):126-33. doi: 10.1002/dc.2840050204. PMID: 2776596.
- 22
Gleason DF. Histologic grading of prostate cancer: a perspective. Hum Pathol. 1992 Mar;23(3):273-9. doi: 10.1016/0046-8177(92)90108-f. PMID: 1555838.
- 23
Mostofi FK, Davis CJ Jr, Sesterhenn IA. Pathology of carcinoma of the prostate. Cancer. 1992 Jul 1;70(1 Suppl):235-53. doi: 10.1002/1097-0142(19920701)70:1+<235::aid-cncr2820701311>3.0.co;2-g. PMID: 1376194.
- 24
Hostetter AL, Pedersen KV, Gustafsson BL, Månson JC, Boeryd BR. Diagnosis and localization of prostate carcinoma by fine-needle aspiration cytology and correlation with histologic whole-organ sections after radical prostatectomy. Am J Clin Pathol. 1990 Dec;94(6):693-7. doi: 10.1093/ajcp/94.6.693. PMID: 2244591.
- 25
Narayan P, Jajodia P, Stein R, Tanagho EA. A comparison of fine needle aspiration and core biopsy in diagnosis and preoperative grading of prostate cancer. J Urol. 1989 Mar;141(3):560-3. doi: 10.1016/s0022-5347(17)40894-9. PMID: 2918592.
- 26
Klotz LH, Shaw PA, Srigley JR. Transrectal fine-needle aspiration and truecut needle biopsy of the prostate: a blinded comparison of accuracy. Can J Surg. 1989 Jul;32(4):287-9. PMID: 2660974.
- 27
Pérez-Guillermo M, Acosta-Ortega J, Garcia-Solano J. The continuing role of fine-needle aspiration of the prostate gland into the 21st century: a tribute to Torsten Löwhagen. Diagn Cytopathol. 2005 May;32(5):315-20. doi: 10.1002/dc.20241. PMID: 15830367.
- 28
Maksem JA, Berner A, Bedrossian C. Fine needle aspiration biopsy of the prostate gland. Diagn Cytopathol. 2007 Dec;35(12):778-85. doi: 10.1002/dc.20764. PMID: 18008341.
- 29
Sayar H, Bulut BB, Bahar AY, Bahar MR, Seringec N, Resim S, Çıralık H. Does imprint cytology improve the accuracy of transrectal prostate needle biopsy? Diagn Cytopathol. 2015 Feb;43(2):91-7. doi: 10.1002/dc.23187. Epub 2014 Jun 26. PMID: 24964902.
- 30
Guerra A, Flor-de-Lima B, Freire G, Lopes A, Cassis J. Radiologic-pathologic correlation of prostatic cancer extracapsular extension (ECE). Insights Imaging. 2023 May 16;14(1):88. doi: 10.1186/s13244-023-01428-3. PMID: 37191739; PMCID: PMC10188796.
- 31
Svatek RS, Karam JA, Rogers TE, Shulman MJ, Margulis V, Benaim EA. Intraluminal crystalloids are highly associated with prostatic adenocarcinoma on concurrent biopsy specimens. Prostate Cancer Prostatic Dis. 2007;10(3):279-82. doi: 10.1038/sj.pcan.4500954. Epub 2007 Feb 27. PMID: 17325718.