Dosimetry and dose metric considerations on in vitro inhalation toxicity testing of nano- aerosols
Ji Hyun Lee1
Ji Hyun Lee- 1 HCT Seattle, USA
Mi Seong Jo2
Mi Seong Jo- 2 HCT, Icheon, Korea
Hoi Pin Kim3
Hoi Pin Kim- 3 H&H Bio, Asan, Korea
Youngshang Han4
Youngshang Han- 4 Department of Mechanical Engineering, University of Washington, Seattle, USA
Yong Taek Kwon5
Yong Taek Kwon- 5 H&H Bio, Asan, Korea;’
Kangho Ahn6
Kangho Ahn- 6 Art Plus, Seoul, Korea, Hanyang University, Ansan, Korea
Il Je Yu7 ✉
Il Je YuCorresponding author- 7 HCT Seattle, USA; Department of Environmental and Occupational Health Sciences, University of Washington, Seattle, USA
Show affiliations (7)
- 1HCT Seattle, USA
- 2HCT, Icheon, Korea
- 3H&H Bio, Asan, Korea
- 4Department of Mechanical Engineering, University of Washington, Seattle, USA
- 5H&H Bio, Asan, Korea;’
- 6Art Plus, Seoul, Korea, Hanyang University, Ansan, Korea
- 7HCT Seattle, USA; Department of Environmental and Occupational Health Sciences, University of Washington, Seattle, USA
Published
Abstract
Recently, new approach methods (NAM) have been utilized to reduce animal experimentation and housing and care costs. The use of NAM to assess safety is paramount, underscoring the need for the method to be established for validity and reliability. NAM for inhalation toxicity is now developing to replace traditional animal inhalation toxicity tests. To align with animal inhalation toxicity studies, dosimetry and dose metrics for in vitro inhalation must be consistent with those of animal studies. In this study, we present a novel approach to address key elements of dosimetry and dose metric characterization for in vitro inhalation toxicity testing using an air-liquid interface (ALI) system. By generating nanosized NaCl aerosols and exposing a 6-transwell ALI system for two hours, we quantitatively determined deposited doses for each transwell. Our study further identifies critical dose metrics for in vitro inhalation studies, including particle size, number concentration, concentration stability, and deposition variability during exposure. Importantly, when comparing the deposition outcomes of in vitro and in vivo systems, our results demonstrate that the in vitro deposition variability closely mirrors that observed in vivo lung deposition. This finding underscores the potential of our in vitro methodology to align with regulatory inhalation guidelines, offering a robust framework for transitioning from animal-based inhalation studies to NAM-based approaches. Our work contributes to the growing body of evidence supporting the scientific and regulatory feasibility of NAMs in inhalation toxicology, highlighting their capability to deliver accurate and reproducible results.
1 Introduction#
New approach methodologies (NAMs) have been defined as any in vitro, in-chemical, or computational (in silico) method that, when used alone or in concert with others, enables improved chemical, drug, and pesticide safety assessment through more protective and/or relevant models and as a result, contributes to the replacement of animals. Traditionally, inhalation toxicity tests expose animals to acute, subacute, subchronic, or chronic in the inhalation chambers with defined concentrations. The duration of exposure to animals lasts 4 hours, once for acute tests and 6 hours/day for subacute, subchronic, and chronic periods. Generally accepted regulatory inhalation test guidelines OECD test guideline (TG) 403 (acute)[1], 412 (subacute)[2], 413 (subchronic)[3], and guidance document 39[4] to assist the regulated community and regulators in selecting the most appropriate inhalation TG so that particular data requirements can be met while reducing animal usage and suffering. These guidelines prescribe sex and number of animals to expose, exposure method (whole-body or nose-only), duration of exposure, concentration levels (one control and three concentrations), exposure conditions, chamber airflow, test article concentration monitoring, particle size measurement, and animal husbandry. These inhalation tests are very expensive and require special equipment and dedicated space. However, with the potential of in vitro inhalation studies to mimic in vivo conditions, there is hope for a more cost-effective and animal-friendly future in inhalation toxicology.
Flow-through exposure mode used in animal inhalation tests has been applied to in vitro inhalation tests. In flow-through ALI exposure systems, a minimal sample flow is introduced to the apical surface of the biological test system. The slower aerosol movement, caused by stagnation in the flow, results in deposition primarily through diffusion[5-7]. Several in vitro aerosol exposure devices to in vitro cell cultures at the air-liquid interphase (ALI) have been developed to mimic pulmonary exposure situations, including a nano aerosol chamber for in vitro toxicity (NACIVT)[8], multi-culture exposure chamber (MEC)[9], PreciseInhale®/XposeALI®[10], and commercially marked VITROCELL® and CULTEX® . Flow-through ALI systems employ alternative deposition techniques, such as thermophoresis and electrostatic deposition, and feature varying configurations, such as parallel sample flow to the apical side. These systems can also be adjusted with different parameters, including flow rates and the use of constant or pulsed electrophoresis[8, 11-12]. These systems have been used to test cigarette smoke, fumes, nanoparticles and indoor pollutants. A one-day workshop on ALI in vitro models for respiratory toxicology held in Paris in March 2016 reached a consensus conclusion that validation of in vitro inhalation is a key issue to challenge[8]. Along with validation, the reliability of in vitro inhalation toxicity measurements using ALI is a key issue[13].
In order for in vitro results to be comparable to in vivo results, it is important that the dosimetry and dose metrics are comparable. Dosimetry refers to the amount of a particle dose, either inhaled, deposited, or retained, whereas Dose metrics (i.e., the measure of the dose) can be expressed as particle number, surface area, mass, surface reactivity, specific surface reactivity, and others like ROS-inducing capacity[14]. Table 1 compares exposure dose metrics in vivo with in vitro inhalation study. In contrast, using rats or mice in animal inhalation studies, in vitro study frequently uses human primary pneumocytes or cell lines derived from human carcinoma cells cultured in air-liquid interphase (ALI) mode. In ALI culture, a key characteristic is that the cells’ basal surface interacts with the liquid culture medium while the apical surface is exposed to air. Typically, cells are seeded onto the permeable membrane of a cell culture insert, initially providing a culture medium to both apical and basal compartments. Once the cells reach confluence, they are subjected to an “air-lift” process, where the medium is provided solely to the basal chamber. This arrangement mimics the environment of the human airway, encouraging the development of a mucociliary phenotype. The dose metrics of animal inhalation tests require that the exposure atmosphere should be held as constant as practicable, and individual chamber concentration samples should deviate from the mean chamber concentration by no more than ±10% for gases and vapors and by no more than ±20% for liquid or solid aerosols (Table 1). In vitro studies must maintain the same concentration over the exposure period as in vivo studies. However, animal studies require O2 of at least 19% CO2, less than 1% in an inhalation chamber, and in vitro studies are usually conducted in a 5% CO2 environment. More than ten times of air change per hour is required for the in vivo inhalation study, but dynamic airflow is recommended for in vitro study, considering human ventilation 10 m3 /day and alveolar surface area 634,620 cm2[15], 0.017 ml/cm2 /min is the desired flow rate. When considering a surface area of 4.2 cm2 for one well of 6-transwell, a flow of 0.07 ml/min/transwell is desired but hardly achievable. Thus, when considering the primary deposition mode to the alveolar region is diffusion, the flow rate to the ALI transwell should be held as low as possible not to damage alveolar cells and to make diffusion-dominant deposition mode observed in the alveolar region. A higher flow rate could lead to drying of the cell surface, which could lead to cell death. Gas and vapor mainly deposit to the lung by diffusion, while particle deposition is size-dependent. For air concentration monitoring in an animal study, at least 2 samples for 4 hr exposure (acute) and 3 samplings for 6 hr exposure (subacute to chronic), or at least once if not feasible due to limited airflow rates or low concentrations, are required. For in vitro studies, sampling may not be possible due to the large flow rate required for sampling. Thus, real-time monitoring with low-flow rate sampling would be desired. Although an animal inhalation study is needed to measure mass median aerodynamic diameter (MMAD), an in vitro study may not be feasible due to the large volume required for an impactor. In the animal inhalation study, at least two different methods of determining quantitative particle exposure (i.e., particle counts, size distribution, or particle mass) should be used with real-time monitors such as scanning mobility particle sizers, differential mobility analyzers, optical particle counters or aerodynamic particle sizers. In vitro inhalation studies must also identify the particle number, size distribution, or particle mass with appropriate instruments. The mass concentration of exposed air should be determined by the appropriate filter or tube (e.g., Charcoal or silica) in both studies. Recent revisions of OECD inhalation TGs for subacute and subchronic require the determination of lung burden during post-exposure observation periods. Also, lung deposition at the end of the first exposure day would help to figure out daily lung deposition. Likewise, an in vitro study also needs to determine the deposition of particles or absorption of gas or vapor using a filter, quartz crystal microbalance, and other possible methods. In addition, before the in vitro inhalation experiment, it is desired to determine whether individual transwell concentration samples should deviate from the mean chamber concentration by no more than ±10% for gases and vapors and by no more than ±20% for liquid or solid aerosols.
This report presents our results on the particle deposition study for in vitro inhalation using a 6-transwell with nano-sized particles. We tested whether the exposure to nano aerosol to ALI is in accordance with the dosimetry and dose metrics we suggested. Further, homogeneous deposition of nano aerosols to the 6-transwell with the maintenance of air concentration was studied and compared with in vivo lung deposition data previously published. In addition, real-time monitoring of particle size and the number of in vitro studies was conducted.
Table 1 Exposure dose metrics for In vivo vs in vitro inhalation
| In vivoa | In vitro using ALI | |
|---|---|---|
| Maintenance of concentration | < ±10% for gas & vapor; | Desired as in vivo |
| < ±20% for liquid or solid aerosols. | ||
| O2 and CO2 | O2 at least 19%; CO2 less than 1% | O2 at least 19%; CO2 5% |
| Dynamic air flow | At least 10 air change/hr | < 10 air change/hr; low flow rate desired not to dry cell |
| Mode of deposition | Impaction, sedimentation, diffusion | Impaction, sedimentation, diffusion |
| Concentration monitoring | Real-time desired, sample 1-3 times/day | Real-time desired |
| Aerosol particle size distribution | MMAD < 2µm with GSD 1-3 | Not able to measure MMAD due to high flow to impactor |
| Real-time particle monitoring | Desired | Desired |
| Quantitative monitoring | Filters, impingers/bubblers | Filters, impingers/bubblers |
| Lung deposition determination | Lung burden measurement during post-exposure observation | Filter, Quartz crystal microbalance, etc, after exposure |
a, described in OECD TG, 412, 413 and 39 [1-4]. MMAD, Mass median aerodynamic diameter; GSD. Geometric standard deviation
2 Materials and Methods#
2.1 Nano-sized particle generation and exposure to transwell#
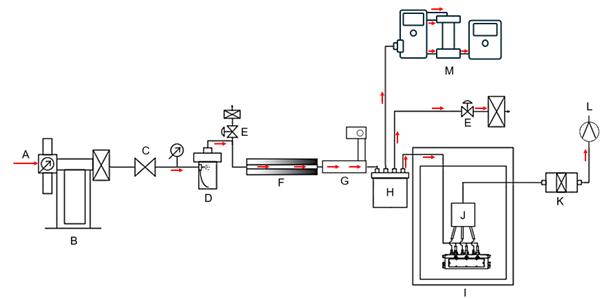
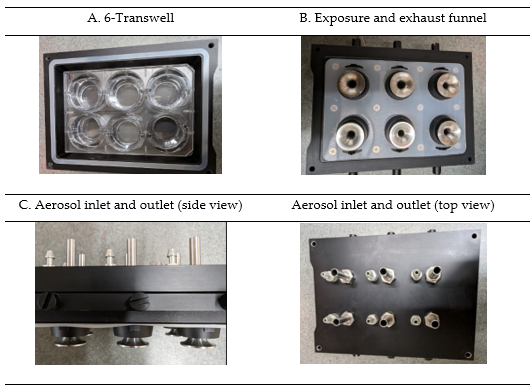
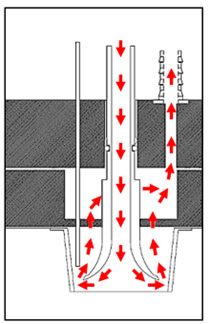
The generation of NaCl nanoparticles was a spray-dry method, as described by Chen and Chein[16]. NaCl particles were selected to test our in vitro inhalation because NaCl aerosols can be generated with high reproducibility, ensuring consistent particle size and concentration, and stable over time, meaning they do not easily evaporate or change their physical state and are non-toxic[17-19]. Also, NaCl aerosols, such as particle sizers and samplers, are commonly used to calibrate and test aerosol instrumentation[20]. The NaCl nanoparticles (0.5% of NaCl, Cat No. 7647-14-5, VWR) were generated using an atomizer (AG-01, HCT, Icheon, Korea), and purified air was used as the carrier gas. A mass flow controller (MFC, AERA, FC-7810CD4 V, Tokyo, Japan) generated nanoparticles with an airflow of 3 liter/min (Figure 1). The generated NaCl nanoparticles were passed through a diffusion dryer, and a soft X-ray neutralized the particles. The NaCl aerosol particles were diluted in a diluter and introduced to an HIVIS system (HCT In Vitro Inhalation System). The system accommodated a commercial 6-transwell plate (Falcon cat 353046) with inserts (0.4 µm transparent PET membrane, cat 353090), and each transwell was covered with an axial flow inlet funnel and outlet for exhausted air (Figure 2). Figure 3 shows the direction of the flow of HIVIS. The exhausted air was passed through a sampling cassette to measure the air concentration, and the flow rate to the exhausted sampling cassette was 12 ml/min or 30 ml/min, assuming 2 ml/min and 5 ml/min to each transwell using a low flow sampling pump (Gilian LFS-113, Sensidyne, St. Petersburg, FL), which was previously calibrated by a Bios calibrator (Dry Cal DC Lite, Butler, NJ). A scanning mobility particle sizer (SMPS, size range 9-294 nm, ART Plus., Icheon, Korea) monitored the particle diameter and number during the 2-hrs of the exposure periods. A 6-transwell plate containing cell culture inserts (transparent PET membrane 0.4 µm pore size, REF 353090, Falcon, NY) containing 2 ml of water below the transwell inserts was exposed to NaCl particles for 2-hr.
2.2 Monitoring of In vitro inhalation and analysis of nanoparticles#
The distribution of the NaCl nanoparticles concerning size and number was measured directly using an SMPS. The air samples were collected on a 37 mm MCE filter (0.45 µm, SKC) from the outlet port of HIVIS using a Gilian flow sampler pump at a 12 and 30 ml flow rate, respectively.
2.3 Determination of deposit concentration#
After 2-hr exposures to the transwell, 3 ml of water was added to each transwell to make a total volume of 5 ml. NaCl concentration was measured by a conductivity meter (EC60 Conductivity tester, Apera Instruments, Columbus, OH). It was determined by a standard curve obtained from serial dilution of NaCl from 5x10⁻³ , 1x10⁻³ , 5x10⁻⁴ , 1x10⁻⁴ to 5x10⁻⁵ %.
2.4 Comparing in vitro deposition with in silico deposition#
The estimated disposition (100% deposition = average air concentration (mg/m3 ) x flow rate x exposure duration (2-hr)) was compared with the actual deposition obtained from experiments. In addition, the actual deposition was compared with the estimated deposition from the MPPD (2016, version 3.04, AL, USA)[21]
2.5 Statistical Analysis#
The statistical analysis was performed using Sigmaplot version 10 (Systat, San Jose, CA). The data were presented as mean ± standard deviation (SD). The coefficient of variation (CV) and 95% confidence interval were also calculated. The result evaluations were all performed using a T-test. The level of statistical significance was set at p < 0.05 and p < 0.01.
3 Results#
3.1 Maintenance of concentration of particles to 6-transwell during 2-hr exposure#
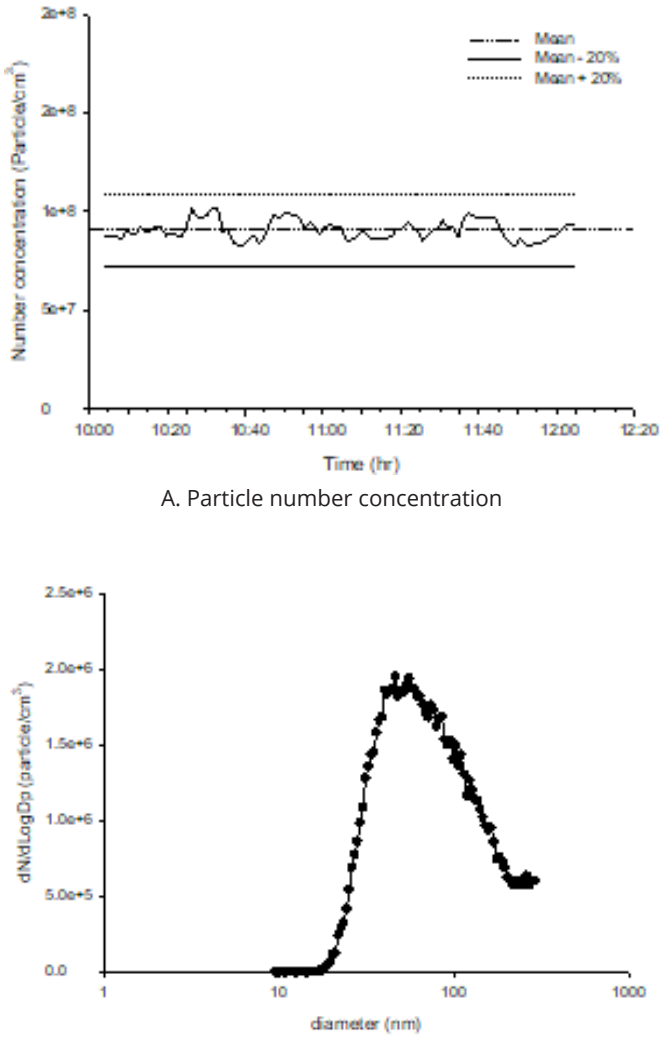
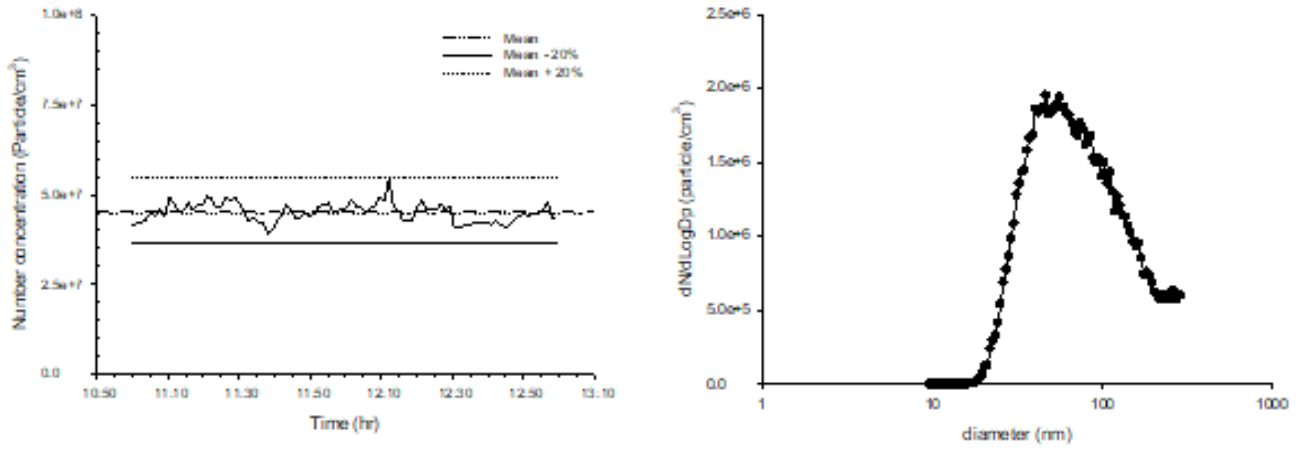
The generated NaCl nanoparticles were delivered to the HIVIS system to deposit 6-transwell. During the 2-hr exposure period, particle number concentration was maintained stably within ±20% with a 30 ml/min pump and 12 ml/min pump flow rate, respectively (Figure 4A & Figure 5A), as in vivo OECD inhalation test guidelines suggested.
A. Particle number concentration
B. Particle diameter distribution
3.2 Particle distribution#
During the 2-hr exposure period, particle size and distributions are described in Table 4. Particle distributions are also described in Figure 4B and Figure 5 B. The median diameters for flow rates 30 ml/min and 12 ml/min are 65.89 and 62.20 nm, respectively (Table 2)
Table 2 Particle size and mass concentration of NaCl particles.
| Flow rate (ml/min) | Median (nm) | GM (nm) | GSD | #Concentration (106 /cm3 ) | Mass Concentration (mg/m3 ) |
|---|---|---|---|---|---|
| 30 | 65.89 | 71.30 | 1.87 | 1.40 | 2.64 |
| 12 | 62.20 | 68.39 | 1.87 | 1.38 | 2.19 |
GM, geometric mean diameter, GSD, geometric standard deviation
B. Particle diameter distribution
A. Particle number concentration
3.3 Deposition of the particles to 6-transwell#
Tables 3 and 4 describe the results of 10 repeats of NaCl particle deposition to 6-transwell during 2-hr of exposure. Ten repeats of deposition experiments were conducted with two flow rates, 12 and 30 ml/min. The average concentrations of deposit to each 6-transwell were 4.55 µg and 4.03 µg, respectively, for 30 ml/min and 12 ml/min flow rates, and standard deviations were below 20% from the mean, as seen in Tables 3 and 4. Flow rate 30 ml/min showed significantly higher (P<0.05) deposited concentration compared with flow rate 12 ml/min. and also flow rate 30 ml showed significantly higher (P<0.01) air concentration compared with flow rate 12 ml/min (Table 3 and 4).
Table 3 Deposition of NaCl particles to transwell with low-flow pump 30 ml/min.
| Flow rate 30 ml/min | ||||||
|---|---|---|---|---|---|---|
| 6-transwell | % of SD from mean | Sampling filter | ||||
| Experiment number | Conductivitya (µs/cm) | Concentrationb (µg) | Conductivity (µs/cm) | Concentration (µg) | Air concentration (mg/m3 ) | |
| 1 | 2.62 ± 0.11 | 4.73 ± 0.19 | 4.08 | 10.8 | 19.54 | 5.32 |
| 2 | 3.47 ± 0.15 | 6.27 ± 0.27 | 4.30 | 10.0 | 18.09 | 5.03 |
| 3 | 2.52 ± 0.13 | 4.51 ± 0.24 | 5.34 | 10.9 | 19.52 | 5.42 |
| 4 | 2.23 ± 0.07 | 3.90 ± 0.13 | 3.34 | 12.4 | 21.10 | 5.86 |
| 5 | 2.10 ± 0.13 | 3.60 ± 0.22 | 6.15 | 12.2 | 20.76 | 5.77 |
| 6 | 2.54 ± 0.30 | 4.36 ± 0.51 | 11.77 | 11.9 | 20.25 | 5.63 |
| 7 | 2.68 ± 0.18 | 4.55 ± 0.30 | 6.60 | 13.6 | 23.05 | 6.40 |
| 8 | 2.67 ± 0.21 | 4.53 ±0.36 | 8.00 | 10.6 | 17.96 | 4.99 |
| 9 | 2.68 ± 0.24 | 4.52 ± 0.41 | 8.98 | 10.1 | 17.12 | 4.76 |
| 10 | 3.05 ± 0.10 | 5.06 ± 0.20 | 3.91 | 13.3 | 22.54 | 6.26 |
| Mean±SD | 4.55 ± 0.74* | 6.25 | 20.00 ± 1.95 | 5.54±0.54** | ||
a, average conductivity of 6 transwell; b, average concentration of deposited NaCl;*, P<0.05 30 ml vs 12 ml; **, P<0.01 30 ml vs 12 ml. 95% Confidence interval 4.36-4.74, CV =0.16
Table 4 Deposition of NaCl particles to transwell with low-flow pump 12 ml/min.
| Flow rate 12 ml/min | ||||||
|---|---|---|---|---|---|---|
| 6-transwell | % of SD from mean | Sampling filter | ||||
| Experiment number | Conductivitya (µs/cm) | Concentrationb (µg) | Conductivity (µs/cm) | Concentration (µg) | Air concentration (mg/m3 ) | |
| 1 | 2.08 ± 0.15 | 3.65 ± 0.26 | 7.02 | 18.56 | 10.6 | 2.94 |
| 2 | 2.50 ± 0.22 | 4.37 ± 0.38 | 8.64 | 18.91 | 10.8 | 3.00 |
| 3 | 2.63 ± 0.24 | 4.50 ± 0.40 | 8.95 | 20.14 | 11.5 | 3.19 |
| 4 | 2.12 ± 0.07 | 3.61 ± 0.12 | 3.25 | 18.23 | 10.7 | 2.97 |
| 5 | 2.18 ± 0.11 | 3.70 ± 0.18 | 4.89 | 17.89 | 10.5 | 2.92 |
| 6 | 2.63 ± 0.24 | 4.46 ± 0.25 | 5.66 | 19.59 | 11.5 | 3.19 |
| 7 | 2.32 ± 0.11 | 3.63 ± 0.17 | 4.61 | 17.56 | 11.2 | 3.11 |
| 8 | 2.55 ± 0.25 | 3.94 ± 0.39 | 9.80 | 17.25 | 11.0 | 3.06 |
| 9 | 2.87 ± 0.27 | 4.41 ± 0.43 | 9.78 | 17.25 | 11.0 | 3.06 |
| 10 | 2.32 ± 0.15 | 3.56 ± 0.23 | 6.51 | 18.50 | 11.8 | 3.27 |
| Mean±SD | 4.03 ±0.40* | 6.95 | 11.06 ± 0.43 | 3.07±0.12** | ||
a, average conductivity of 6 transwell; b, average concentration of deposited NaCl’ *, P<0.05 30 ml vs 12 ml; **, P<0.01 30 ml vs 12 ml. 95% Confidence interval 3.93-4.13, CV 0.10.
3.4 Comparing in vitro deposition with in silico deposition#
The Multiple-Path Particle Dosimetry (MPPD) model is a computational tool used to predict the deposition of inhaled particles in the human respiratory system[16]. It’s particularly useful in toxicology, exposure science, and risk assessment, especially for aerosols and nanoparticles. It also accounts for factors like airflow, breathing patterns, and particle properties (size, shape, density) to calculate how much of the inhaled material reaches each region of the lung. We compared MPPD deposition with experimental ALI deposition to estimate particle deposition in silico vs in vitro. The estimated disposition was compared with the actual deposition obtained from experiments and MPPD modeling (Table 5). Although MPPD estimated a total of 0.250 deposition to the head, tracheobronchial, and pulmonary regions of the human lung with both flow rates, the actual deposition was 0.23 and 0.91 of the estimated deposition, indicating sufficient deposition to ALI transwell (Table 5). Our previous comparison between 6-hr animal exposure to AgNP for 6-hr with MPPD modeling also shows the discrepancy between in vivo and in silico. MPPD (version 3.04) estimated 27% of pulmonary deposition after 6-h (1-day) exposure, while the actual deposition fraction measured by silver mass weight analysis was 13.4%[30].
A. Model parameter
Table 5 Parameters used in multiple-path particle dosimetry (MPPD) and exposure model and regional deposition.
| Model parameter | Human | |
|---|---|---|
| Airway morphometry | Model | Yeh/Schum 5-lobe |
| Functional residual capacity | 3300 ml | |
| Upper respiratory tract | 50 ml | |
| Particle properties | Density | 2.16g/cm3 |
| Geometric mean diameter | 71.30 nm (30 ml/min) 68.39 nm (12 ml/min) | |
| Geometric standard deviation | 1.87 | |
| Exposure condition | Aerosol concentration | 5.54 mg/m3 (30 ml/min) 3.07 mg/m3 (12 ml/min) |
| Breathing frequency | 12 times/min | |
| Tidal volume | 625 ml | |
| Breathing | Oronasal mouth breathing |
B. Regional deposition
| Flow rate | Head | Tracheobronchial | Pulmonary | Total* |
|---|---|---|---|---|
| 30 ml/ min | 0.041 | 0.079 | 0.124 | 0.250 |
| 12 ml/min | 0.062 | 0.080 | 0.124 | 0.266 |
*Deposition is expressed as a fraction.
3.5 Comparing in vitro deposition with in vivo deposition#
The results of ten in vivo lung deposition studies we conducted previously were compared with current in vitro studies to determine the deviation of deposition homogeneity. Silver nanoparticles (AgNP) ranged from 11-20 nm, gold nanoparticles (AuNP, 11-105 nm), and multiwalled carbon nanotubes (MWCNT, 1015) were exposed to 4-6 rats for 6-hr in a nose-only inhalation chamber. After 6-hr exposure, rats were sacrificed and lungs were removed to measure deposited mass concentration. The average percent of deviation from the mean was 12.31%, ranging from 6.1 to 21.7% (Table 6). Comparing in vivo deposition to lung with in vitro deposition to ALI, our in vitro deposition showed a similar percent of deviation from the mean. A previous out study conducted for AgNP in vitro inhalation [24, Appendix 2] showed less than 5.4% deviation from the mean could be comparable with AgNP in vivo deposition studies.
Table 6 In vivo short-term particle deposition to the lung after short-term inhalation nose-only exposure.
| Exp No | Particle | Size (nm) | Particle # (#/cm3 ) | Exposure (µg/m3 ) | Exposure (hr) | Deposition (µg/lung) | Animal No. | Deviation from mean (%) | Analytical. Method | Ref |
|---|---|---|---|---|---|---|---|---|---|---|
| 1 | AgNP | 20 | 1.31 × 10⁷ | 964.67 | 6 | 10.72 ± 0.53 | 5 | 6.1 | ICP-MS | 30 |
| 2 | AgNP | 18-19 | 1.98 × 10⁶ | 31.22 | 6 | 0.25 ± 0.02 | 4 | 8.0 | AA | 31 |
| 3 | AgNP | 18-19 | 4.06 × 10⁶ | 81.79 | 6 | 0.65 ± 0.08 | 4 | 12.3 | AA | 31 |
| 4 | AgNP | 18-19 | 7.23 × 10⁶ | 115.60 | 6 | 0.98 ± 0.16 | 4 | 16.3 | AA | 31 |
| 5 | AgNP | 11 | 1.44 × 10⁶ | 17.38 | 6 | 0.05 ± 0.005 | 4 | 10.6 | ICP-MS | 32 |
| 6 | AuNP | 13 | 1.97 × 10⁶ | 12.80 | 6 | 0.51 ± 0.088 | 4 | 17.3 | AA | 33 |
| 7 | AuNP | 105 | 1.06 × 10⁶ | 13.70 | 6 | 0.43 ± 0.040 | 4 | 9.3 | AA | 33 |
| 8 | AuNP | 11 | 1.67 × 10⁶ | 34.80 | 6 | 2.94 ± 0.64 | 5 | 21.7 | ICP-MS | 32 |
| 9 | AuNP | 11 | 1.38 × 10⁶ | 19.34 | 6 | 3.24 ± 0.78 | 4 | 7.4 | ICP-MS | 34 |
| 10 | MWCNT | 1015 | 1.66 × 10⁶ | 4253 | 6 | 6.61 ± 0.93 | 6 | 14.1 | EC | 35 |
| 12.31 (6.1-21.7) |
AgNP, silver nanoparticles; AuNP, gold nanoparticles; MWCNT, multiwalled carbon nanotubes; ICP-MS, inductively coupled plasma mass spectrometer; AA, atomic absorption spectrometer; EC, elemental carbon analyzer.
4 Discussion#
Our dose metric study indicated that in vitro inhalation studies can be compatible with in vivo studies if the dosimetry and dose metrics are well characterized. Our in vitro inhalation study showed that well-maintained exposure concentration during a 2-hr exposure period, as prescribed by the OECD test guidelines and guidance documents, was within less than 20% deviation from the mean. Further, we characterized particle number and size distribution during the in vitro exposure period, corresponding to real-time monitoring of particle number and size suggested by the guidelines and guidance document. In addition, we monitored exposed air concentration during the exposure period and deposited concentration after exposure. Our results suggested that an in vitro study can be compatible with an in vivo inhalation study if the dosimetry and dose metrics are well characterized.
The flow rate not to damage respiratory epithelial cells cultured on ALI was suggested by 5 ml/transwell[22-23], and also our previous study indicated that 10 ml/min did not damage cells for 2-hr exposure[24]. Therefore, the flow rates we used, 12 and 30 ml, do not damage epithelial cells during a 2-hr exposure period. It is challenging to characterize the lung deposit concentration during in vivo study; the only way to determine the lung deposit concentration (called lung burden measurement) is to sacrifice the animal right after exposure. The deposit mass dose quantification for particle inhalation test is one of the difficult tasks in an in vitro inhalation toxicity test. There are several methods available depending on the materials, such as using filter paper laid on the transwell for further chemical analysis, such as the ICP-MS (Inductive coupled plasma mass spectroscopy or AA (atomic absorption) for metals or UV-VIS (Ultraviolet-Visible spectroscopy) method or a placing quartz crystal microbalance (QCM). Although QCM is a susceptible device used to measure minute mass changes on a surface by detecting variations in the resonance frequency of a quartz crystal[25-26], QCM is highly sensitive to surface changes, which can be a disadvantage if the measurements are affected by unwanted surface contaminants or if surface preparation is inconsistent, and measurements can be influenced by temperature, pressure, and humidity changes, requiring careful control and calibration to ensure accuracy[27-28]. Also, it works best with thin, rigid, and evenly distributed films. Soft, highly viscous, or unevenly distributed films can complicate the interpretation of results[29]. The accuracy and sensitivity of the measurements depend heavily on the quality and stability of the quartz crystal used in the device[25].
Deposit dose determination in an in vitro inhalation study using multiple ALI transwells causes a significant complication. Because only one transwell or a few transwells are determined for mass dose, there are doubts about whether multiple transwells receive the same dose. Our HIVIS system clearly shows a similar dose within ±20% throughout the 6-transwell. In this system, two different flow rates, 12 ml/min and 30 ml/ min were used to expose a 6-transwell, assuming flow rates of 2 ml/min and 5 ml/min, respectively, are delivered to each transwell. Previous studies using MFC with a flow rate of 60 ml/min to 6-transwell (10 ml/min per transwell) indicated that a 10 ml/min flow rate per well for 2-hr exposure did not damage A549 lung cells[24]. When we generated silver nanoparticles (AgNP, 50 nm) to expose ALI transwells, AgNP deposited with spatial uniformity (Appendix 1). In this current experiment, we used a flow sampler instead of MFC to deliver extremely low-flow air (2 to 5 ml/min per well) so as not to damage cells.
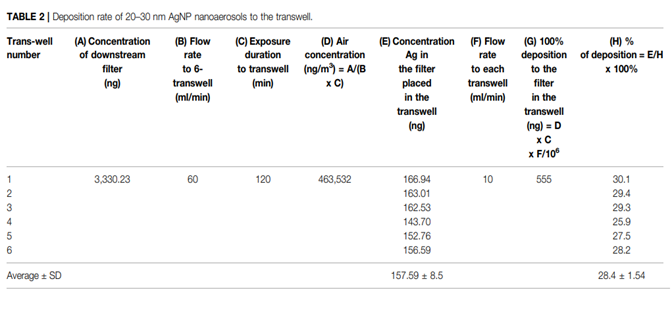
Inhaled particles are typically deposited to the human respiratory tract, typically three main regions: upper airways (nasal passages, mouth, larynx, and trachea), conducting airways (trachea, bronchi, and bronchioles), and pulmonary or alveolar region (bronchioles, alveolar ducts, and alveoli). Smaller particles (<1 µm), such as nanoparticles or ultrafine particles, tend to reach this region and deposit by diffusion (Brownian motion). The deposition of nanoaerosol observed in our system to ALI transwell could be dominantly diffusion mode, as in respiratory alveolar cells. Although the higher flow rate (30 ml/min) resulted in more air and deposit concentration to the ALI transwell, the lower flow rate (12 ml/min) showed more deposition fraction. The deposit dose of approximately 0.48-0.54 µg/cm2 transwell surface area/hr to the ALI transwell is not small. Although not directly comparable, a rat silver nanoparticle (AgNP, 20 nm) in vivo inhalation study of 0.96 mg/m3 for 6-hr exposure showed a 10.72 µg/lung retained dose[30]. When rat alveolar surface area is assumed 4,000 cm2[36], 2.68 ng of AgNP/cm2 /6-hr (0.45 ng/cm2 /hr) were deposited. Our in vitro exposure study showed nearly 1,000 times higher levels of deposition when compared with AgNP in vivo exposure. The amount of deposition can be adjusted by aerosol generation by controlling MFC flow and dilution of air. Therefore, users of in vitro inhalation should always determine aerosol concentration ranges to the desired deposition to test cell systems.
To ensure the accuracy and reliability of our results, we analyzed errors from experimental and instrumental sources and assessed the comparability of in vitro and in vivo data. Variability in aerosol deposition across transwells was quantified using mean, standard deviation, and coefficient of variation (CV), with confidence intervals calculated to indicate reproducibility. Instrumental errors, including those from the aerosol generator and particle size analyzer, were minimized through calibration according to manufacturer guidelines, and measurement uncertainties were included in the error estimates. To compare in vitro and in vivo deposition, we calculated metrics such as percent deviation and root mean square error (RMSE) to quantify agreement and variability. These methods collectively ensure the reliability and reproducibility of the study.
The degree of deposition of particles to in vitro ALI transwell, as well as in vivo animal lungs, can vary depending on the type of particle. When we compared in vivo lung deposition with in vitro ALI deposition, in vitro NaCl aerosol deposition showed a lower percentage of deviation from the mean than in vivo lung deposition. NaCl particles showed consistent deposition throughout the 6-transwell with less variation due to the ready formation of salt crystal particles after the spray-drying procedure. Our previous limited study on AgNP also showed less variation throughout the 6-transwell[18]. However, some particles generated by the atomizer did not show consistent deposition throughout the 6-transwell with high variation. Before conducting an in vitro inhalation study, test particle generation, maintenance of exposure concentration with real-time monitoring, deposit dose determination method, and deposition variation among ALI should be studied thoroughly.
In this experimental setting, we did not provide 5% CO2, humidity, and appropriate temperature for the cell culture system because this paper aimed to highlight the importance of dosimetry and dose metrics. HIVIS has a water circulation system to provide proper temperature for ALI cell culture, and CO2 and humidity can be provided by simple engineering.
5 Conclusion#
A New Approach Methodology (NAM) for inhalation toxicity is being developed to re place traditional animal-based inhalation tests. To ensure that in vitro results are comparable to in vivo outcomes, dosimetry and dose metrics must align between both systems. This study assessed key elements of dosimetry and dose metrics for in vitro inhalation toxicity using an air-liquid interface (ALI) system, where NaCl nanosized aerosols were generated and exposed to a 6-transwell ALI setup. We carefully monitored particle size, particle number, and concentration stability during the two-hour exposure period. The geometric mean particle sizes were 68 nm (GSD 1.87) and 71 nm (GSD 1.87) for flow rates of 12 mL/min and 30 mL/min, respectively. Aerosol number and mass concentrations were maintained at 1.38×10⁶ particles/cm3 (2.64 mg/m3) for 71 nm particles and 1.40×10⁶ particles/cm3 (2.19 mg/m3) for 68 nm particles throughout the exposure. Deposition efficiency across the transwells showed coefficients of variation of 0.16 and 0.1, with 95% confidence intervals of 4.36−4.74, and 3.92-4.13, respectively. Comparing in vivo and in vitro short-term deposition, the deposition deviation from 10 short-term animal studies averaged 12.3%, while our in vitro deposition deviation was less than 7%. These results demonstrate that the in vitro dose metrics align closely with in vivo metrics, meeting regulatory inhalation guidelines and reinforcing the reliability of this ALI-based NAM for inhalation toxicity testing.

Declarations
€Funding
✎Author contributions
◎Competing interests
▤Data availability
♥Acknowledgements
Article information
- Published
Copyright © 2025 Il Je Yu. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 36#
- 1
OECD (Organization Economic Cooperation and Development). 2024. OECD guideline for the testing of chemicals 403, Acute inhalation toxicity. Paris: OECD.
- 2
OECD (Organization Economic Cooperation and Development). 2018. OECD guideline for the testing of chemicals 412, 28-day (subacute) inhalation toxicity study. Paris: OECD.
- 3
OECD (Organization Economic Cooperation and Development). 2018. OECD guideline for the testing of chemicals 413, 90-day (subchronic) inhalation toxicity study. Paris: OECD.
- 4
OECD (Organization Economic Cooperation and Development) 2018. Guidance document on inhalation toxicity studies, Series on testing and assessment No. 39. 2nd ed. Paris: OECD.
- 5
Lucci, F., Castro, N. D., Rostami, A. A., Oldham, M. J., Hoeng, J., Pithawalla, Y. B., and Kuczaj, A. K. (2018) Characterization and modeling of aerosol deposition in Vitrocell® exposure systems - exposure well chamber deposition efficiency. J. Aerosol Sci. 123, 141− 160.
- 6
Steiner, S., Majeed, S., Kratzer, G., Vuillaume, G., Hoeng, J., and Frentzel, S. (2017) Characterization of the Vitrocell® 24/48 aerosol exposure system for its use in exposures to liquid aerosols. Toxicol. In Vitro 42, 263−272
- 7
Lacroix G, Koch W, Ritter D, Gutleb AC, Larsen ST, Loret T, Zanetti F, Constant S, Chortarea S, Rothen-Rutishauser B, Hiemstra PS, Frejafon E, Hubert P, Gribaldo L, Kearns P, Aublant JM, Diabaté S, Weiss C, de Groot A, Kooter I. Air-Liquid Interface In Vitro Models for Respiratory Toxicology Research: Consensus Workshop and Recommendations. Appl In Vitro Toxicol. 2018 Jun 1;4(2):91-106. doi: 10.1089/aivt.2017.0034. PMID: 32953944; PMCID: PMC7500038.
- 8
Jeannet N, Fierz M, Kalberer M, Burtscher H, Geiser M. Nano aerosol chamber for in-vitro toxicity (NACIVT) studies. Nanotoxicology. 2015 Feb;9(1):34-42. doi: 10.3109/17435390.2014.886739. Epub 2014 Feb 20. PMID: 24552156
- 9
Asimakopoulou A, Daskalos E, Lewinski N , Riediker M , Papaioannou E1 , Konstandopoulos AG. 2013. Development of a dose-controlled multiculture cell exposure chamber for efficient delivery of airborne and engineered nanoparticles. J. Phys.: Conf. Ser. 429 012023
- 10
Ji, J., Hedelin, A., Malmlof, ¨ M., Kessler, V., Seisenbaeva, G., Gerde, P., Palmberg, L., 2017. Development of combining of human bronchial mucosa models with XposeALI® for exposure of air pollution nanoparticles. PLoS One 12, e0170428.
- 11
Zavala, J., Lichtveld, K., Ebersviller, S., Carson, J. L., Walters, G. W., Jaspers, I., Jeffries, H. E., Sexton, K. G., and Vizuete, W. (2014) The Gillings Sampler–an electrostatic air sampler as an alternative method for aerosol in vitro exposure studies. Chem.-Biol. Interact. 220, 158−68.
- 12
Frijns, E., Verstraelen, S., Stoehr, L. C., Van Laer, J., Jacobs, A., Peters, J., Tirez, K., Boyles, M. S. P., Geppert, M., Madl, P., Nelissen, I., Duschl, A., and Himly, M. (2017) A Novel Exposure System Termed NAVETTA for In Vitro Laminar Flow Electrodeposition of Nanoaerosol and Evaluation of Immune Effects in Human Lung Reporter Cells. Environ. Sci. Technol. 51 (9), 5259−5269.9.
- 13
Petersen EJ, Sharma M, Clippinger AJ, Gordon J, Katz A, Laux P, Leibrock LB, Luch A, Matheson J, Stucki AO, Tentschert J, Bierkandt FS. Use of Cause-and-Effect Analysis to Optimize the Reliability of In Vitro Inhalation Toxicity Measurements Using an Air-Liquid Interface. Chem Res Toxicol. 2021 Jun 21;34(6):1370-1385. doi: 10.1021/acs.chemrestox.1c00080. Epub 2021 Jun 7. PMID: 34097823.
- 14
Kuempel ED, Sweeney LM, Morris JB, Jarabek AM. Advances in Inhalation Dosimetry Models and Methods for Occupational Risk Assessment and Exposure Limit Derivation. J Occup Environ Hyg. 2015;12 Suppl 1(sup1):S18-40. doi: 10.1080/15459624.2015.1060328. Erratum in: J Occup Environ Hyg. 2018 Apr;15(4):D31. doi: 10.1080/15459624.2018.1430971. PMID: 26551218; PMCID: PMC4685615.
- 15
NIOSH (National Institute for Occupational Safety and Health). 2013. Occupational Exposure to Carbon Nanotubes and Nanofibers. Current Intelligence Bulletin 65. Cincinnati, OH: NIOSH.
- 16
Chen TM, Chein HM. 2006. Generation and Evaluation of Monodisperse Sodium Chloride and Oleic Acid Nanoparticles. Aerosol and Air Quality Research, 6(3): 305-321.
- 17
Hinds WC. 1999. Aerosol Technology: Properties, Behavior, and Measurement of Airborne Particles. Wiley-Interscience.
- 18
Liu BYH, Lee, KW. 1975. An Aerosol Generator of High Stability. American Industrial Hygiene Association Journal, 36(12), 861-865
- 19
Seinfeld JH, Pandis SN. 2016. Atmospheric Chemistry and Physics: From Air Pollution to Climate Change. John Wiley & Sons
- 20
Chen BT, Fletcher RA, Chen YS, 2011. Calibration of Aerosol Instruments, Aerosol Measurement: Principles, Techniques, and Applications, 3rd Edition, Editors :Pramod Kulkarni P, Baron PA, Willeke P. https://doi.org/10.1002/9781118001684.ch21, Wiley
- 21
MPPD (version 3.04), Applied Research Associates Inc., Raleigh, NC, 2016.
- 22
Kim JS, Peters TM, O’Shaughnessy PT, Adamcakova-Dodd A, Thorne PS. Validation of an in vitro exposure system for toxicity assessment of air-delivered nanomaterials. Toxicol In Vitro. 2013 Feb;27(1):164-73. doi: 10.1016/j.tiv.2012.08.030. Epub 2012 Sep 5. PMID: 22981796; PMCID: PMC3950355.
- 23
Leibrock, L., Jungnickel, H., Tentschert, J., Katz, A., Toman, B., Petersen, E. J., Bierkandt, F. S., Singh, A. V., Laux, P., and Luch, A. (2020) Parametric optimization of an air-liquid interface system for flow-through inhalation exposure to nanoparticles: assessing dosimetry and intracellular uptake of CeO2 nanoparticles. Nanomaterials 10, 2369.
- 24
Kim B, Shin JH, Kim HP, Jo MS, Kim HS, Lee JS, Lee HK, Kwon HC, Han SG, Kang N, Gulumian M, Bello D, Yu IJ. 2022. On-Site Deployment of an Air-Liquid-Interphase Device to Assess Health Hazard Potency of Airborne Workplace Contaminants: The Case of 3-D Printers. Front. Toxicol. 4:818942. doi: 10.3389/ftox.2022.818942
- 25
Janshoff A, Galla HJ, Steinem C. 2000. Piezoelectric mass-sensing devices as biosensors:An alternative to otical biosensors? Angewandte Chemie International Edition, 39(22): 4004-4032.
- 26
Zhou H, Zheng, H. 2006. Applications of the quartz crystal microbalance in biomedicine. Journal of Biomedical Science and Engineering, 2(3): 184-188.
- 27
Marx KA. 2003. Quartz crystal microbalance: A useful tool for studying thin polymer films and complex biomolecular systems at the solution−surface interface. Biomacromolecules, 4(5): 1099-1120.
- 28
Ward MD, Buttry DA. 1990. In situ interfacial mass detection with piezoelectric transducers. Science, 249(4972), 1000-1007.
- 29
Rodahl M, HööK F, Krozer A., Brzezinski P, Kasemo, B. (1995). Quartz crystal microbalance setup for frequency and Q-factor measurements in gaseous and liquid environments. Review of Scientific Instruments, 66(7):3924-3930.
- 30
Park JD, Kim JK, Jo MS, Kim YH, Jeon KS, Lee JH, Faustman EM, Lee HK, Ahn K, Gulumian M, Oberdörster G, Yu IJ. 2019. Lobar Evenness of Deposition/Retention in Rat Lungs of Inhaled Silver Nanoparticles: An Approach for Reducing Animal Use While Maximizing Endpoints, Particle and Fibre Toxicology, 16:2.
- 31
Jo MS, Kim JK, Kim Y, Kim HP, Kim HS, Ahn K, Lee JH, Faustman EM, Gulumian M Kelman B, Yu IJ. 2019. Mode of silver clearance following 28-day inhalation exposure to silver nanoparticles determined from lung burden assessment including post-exposure observation periods, Archive of Toxicology, 94(3) 773-784.
- 32
Kim JK, Kim HP, Park JD, Ahn K, Kim WY, Gulumian M, Oberdörster G, Yu IJ. 2021 Lung retention and particokinetics of silver and gold nanoparticles in rats following subacute inhalation co-exposure, Particle and Fibre Toxicology, 18:5
- 33
Han SG, Lee JS, Ahn K, Kim YS, Kim JK, Lee JH, Shin JH, Jeon KS, Cho WS, Song NW, Gulumian M, Shin BS, Yu IJ. 2015. Size-dependent clearance of gold nanoparticles from lungs of Sprague-Dawley rats after short-term inhalation exposure, Archives of Toxicology, 89(7): 1083-94.
- 34
Kim HP, Kim JK, Jo MS. Park JD, Ahn K, Gulumian M, Oberdorster G, Yu IJ. Even lobar deposition of poorly soluble gold nanoparticles (AuNPs) is similar to that of soluble silver nanoparticles (AgNPs). 2020. Particle and Fibre Toxicology, 17:54
- 35
Kim JK, Jo MS, Kin Y, Kim TG, Shin JH, Kim BW, Kim HP, Lee HK, Ahn K, Oh SM, Cho WS, Yu IJ. 2020. A 28-day inhalation toxicity study with evaluation of lung deposition and retention of tangled multi-walled carbon nanotubes, Nanotoxicology, 14 (2), 250-262
- 36
Stone KC, Mercer RR, Freeman BA, Chang LY, Crapo JD. 1992. Distribution of lung cell numbers and volumes between alveolar and nonalveolar tissue. Am Rev Respir Dis 146(2):454–456.
Cited by 3#
- In vitro delivery and transwell uptake of volatile and semi-volatile organic compounds in an air–liquid interface exposure systemJ. Lee, H. Lee, K. Ahn et al.Frontiers in Toxicology · 2026 · doi.org/10.3389/ftox.2026.1783871
- Quantitative Evaluation of Protein Nanoparticle Aerosol Deposition in an Air–Liquid Interface (ALI) System and Comparison with In Silico Lung Deposition ModelingJ. Lee, H. Lee, M. Jo et al.Aerosol and Air Quality Research · 2026 · doi.org/10.1007/s44408-026-00129-y
- Protein aerosol deposition to air-liquid interface (ALI)J. Lee, H. Lee, M. Jo et al. · 2025 · doi.org/10.21203/rs.3.rs-6839038/v1
Each citation is confirmed in the citing article's own reference list (Crossref).