Investigating the Co-occurrence of Urinary Calculi and Renal Carcinoma: A Comprehensive Analysis of Clinical and Molecular Associations Urinary calculi and renal cancer
Jin Li ✉
Jin LiCorresponding author- Department of Urology, 983 Hospital, Joint Logistic Support Force, Tianjin 300142, China
Chao Zhao
Chao Zhao- Department of Urology, 983 Hospital, Joint Logistic Support Force, Tianjin 300142, China
Show affiliations (1)
- Department of Urology, 983 Hospital, Joint Logistic Support Force, Tianjin 300142, China
Published
Abstract
BackgroundImportant urological diseases with possible overlapping etiologies included urinary calculi and renal cancer. Although both disorders are associated with metabolic abnormalities and chronic inflammation, their co-occurrence and common molecular pathways are yet poorly investigated.
ObjectivesThis investigation examined the urinary calculi’s clinical, biochemical and molecular relationships with renal cancer.
MethodsAnalyzing a cohort of 526 patients, demographic information, clinical features and laboratory markers was conducted. Key kidney cancer-related genes; VHL, PBRM1, and MET, were subjected to molecular studies. Structural protein models were created from RCSB PDB data and integrated bioinformatics techniques analyzed protein expression and mutation frequency.
ResultsWith significant p values, all covariates, obesity (OR = 2.1), hypertension (OR = 1.8), diabetes (OR = 1.7), and hypercalciuria (OR = 2.3) were found as major risk factors for the co-occurrence of urinary calculi and renal cancer. Frequent mutations in VHL (23.6%), PBRM1 (20.9%) and MET (18.6%), were found by molecular analysis. Indices of pro-inflammatory environment were shown by elevated indicators of oxidative stress (ROS, MDA) and inflammation (CRP, IL-6). Particularly in VHL and MET, structural study of altered proteins revealed conformational alterations influencing protein activity.
ConclusionBy means of shared risk factors and molecular changes, urinary calculi and renal cancer co-occur and implied a common pathogenesis relationship including chronic inflammation, metabolic dysfunction and genetic abnormalities. These results highlighted the need of thorough clinical management and early genetic screening in reducing the risk and enhancing the outcomes for patients presenting with both diseases.
1 Introduction#
Two separate but perhaps linked urological disorders are urinary calculi, sometimes known as kidney stones and renal carcinoma, the most prevalent form of kidney cancer1-2 . Often originating from metabolic problems, nutritional variables or chronic dehydration, urinary calculi develop from the crystallization of chemicals such calcium, oxalate, or uric acid within the urinary tract3-4 . Conversely, renal cancer, especially renal cell carcinoma (RCC), tumor resulting from epithelium of renal tubules. Although urinary calculi and renal cancer are usually investigated as different entities, new data points point to a possible relationship between the two that emphasizes the need of thorough study of their co-occurrence and underlying causes 5 .
Mostly due to lifestyle changes, aging populations and better diagnosis capacity, prevalence of both urinary calculi and renal cancer has been rising worldwide. Patients revealing recurrent kidney stones history especially seem to be more likely to suffer renal cancers 6-7 . Obesity, hypertension and some dietary patterns are among the shared risk factors that might help to explain the noted association 6 . Furthermore, prolonged irritation and inflammation of the renal epithelium brought on by recurring kidney stones could lead to cellular alterations that provide favorable conditions for oncogenesis. This report fits the “field cancerization” theory, according to which tissue injury and chronic inflammation set afflicted areas to be prone to malignant transformation 8 .
Further supporting the possible link between urinary calculi and renal cancer are molecular investigations. Calcium-induced chronic oxidative stress and ongoing inflammatory reactions might cause genetic and epigenetic changes in renal tissue9 . Often linked to renal cancer, mutations in genes including VHL, MET and PBRM1 could be influenced by oxidative stress pathways set off by stone presence. Furthermore suggesting a same metabolic route, hypercalciuria, being linked to both nephrolithiasis and risk of renal cancer 10-11 .
Notwithstanding these signals, little is known clinically about the relationship between urinary calculi and renal cancer; contradicting data from different demographic studies abound. The study sought to evaluate shared risk factors, look at possible molecular processes connecting urinary calculi and renal cancer and probe their clinical co-occurrence.
2 Materials and Methods#
2.1 Study Design and Setting#
Between July 2022 and September 2024, this cross-sectional study was carried out at 983 Hospital, Joint Logistic Support Force, Tianjin, China. Investigating the clinical co-occurrence of urinary calculi and renal cancer, with an eye toward common risk factors and possible molecular links. Using clinical data and biological samples from individuals presenting with either urinary calculi or renal cancer, or both, we conducted this investigation.
2.2 Population and Sample Size#
Non-probability consecutive sampling brought 526 patients total into enrollment. Adult patients aged eighteen years or above with the confirmed diagnosis of urinary calculi (kidney stones) or renal cancer depending on clinical, radiographic or histological evidence were included. Patients with late-stage chronic kidney disease (CKD), other primary malignancies and those undergoing chemotherapy unrelated to renal carcinoma were among the excluded groups. The selected sample size guaranteed approximately 80% power to find appreciable relationships between renal cancer and urinary calculi.
2.3 Data Collection#
Laboratory studies, medical record reviews and patient interviews constituted the components of data collecting. We recorded demographic information (age, BMI, sex), medical history (recurrent urinary tract infections, hypertension, diabetes) and lifestyle factors (smoking status, alcohol intake, eating habits, fluid consumption). We recorded clinical presentation data including dysuria, flank discomfort and hematuria. Renal cancer was confirmed by biopsy or surgical pathology; radiological confirmation of urinary calculi was achieved by ultrasonic, computed tomography or magnetic resonance imaging (MRI).
2.4 Laboratory Investigations#
All patients had blood samples taken for biochemical examination including levels of serum creatinine, urea, calcium, phosphate, uric acid and glucose. An automated hematology analyzer (Sysmex 9000) ran a complete blood count. Automated urine analyzers (Lab UMat 2) collected and examined urine samples for hematuria, proteinuria and crystal identification. Avoiding first-pass urine samples helped to lower diagnosis errors. Using Paris System for Reporting Urinary Cytology, urine sediment was also stained and microscopically searched for nuclear atypia to identify possible urothelial cancers.
2.5 Molecular Analysis#
Blood and tissue samples were acquired for molecular study to find genetic alterations and inflammatory indicators for individuals who approved. These samples underwent DNA and RNA extraction, then focused sequencing to find mutations in genes typically linked to renal cancer including VHL, PBRM1 and MET. To study chronic inflammation and oxidative stress as possible drivers of cancer development, immunohistochemistry was performed to examine the expression of inflammatory markers; TNF-α and IL-6 12-14 .
2.6 Statistical Analysis#
SPSS version 26.0 was used to examine data. The demographic and clinical traits of patients were compiled in descriptive statistics. Continuous data were given as means and standard deviations; categorical variables were stated as frequencies and percentages. Relations between urinary calculi and renal cancer were investigated using Fisher’s exact tests and chi-square analyses. Independent risk variables for the co-existence of the two diseases were found by means of logistic regression analysis. Considered statistically significant was p-value of under 0.05.
2.7 Ethical Considerations#
Approved by Institutional Review Board of 983 Hospital, Joint Logistic Support Force, Tianjin vide letter No. CNV88279, the study was carried out in conformity with ethical standards of Declaration of Helsinki. Every participant has informed permission before to being registered. Strict maintenance of patient confidentiality was followed, and all biological materials were handled using bioethical guidelines.
3 Results#
The demographic and clinical profile of participants revealed significant risk factors for renal problems were male predominance (59.3%), high prevalence of hypertension (39.5%), diabetes (29.5%,), smoking (40.5%) (p<0.001). Suggested as major risk factors for the co-occurrence of urinary calculi and renal cancer were recurrent UTIs (33.8%) and family history of renal carcinoma (11.2%) (p<0.05) (Table1).
Table 1 Demographic and Clinical Characteristics.
| Parameter | N (%) | p-Value |
|---|---|---|
| Total Patients | 526 | — |
| Age (years) | 55.8 ± 12.4 | — |
| Male | 312 (59.3) | 0.001* |
| Female | 214 (40.7) | |
| BMI (kg/m2) | 27.6 ± 4.8 | — |
| Hypertension | 208 (39.5) | 0.001* |
| Diabetes Mellitus | 155 (29.5) | 0.015* |
| Smoking Status | 213 (40.5) | 0.001* |
| Alcohol Consumption | 167 (31.8) | 0.002* |
| Recurrent UTI | 178 (33.8) | 0.007* |
| Family History of Renal Carcinoma | 59 (11.2) | 0.024* |
With increased serum creatinine and uric acid levels, the biochemical study pointed to decreased renal function (p<0.05). Indicative of kidney impairment, significant results included high rates of hematuria (40.5%) and proteinuria (p<0.05). The most common kind was calcium oxalate crystals (58.6%), which linked changes in mineral metabolism to urinary calculi (p<0.001) (Table 2). The risk variables connected to the co-occurrence of urinary calculi and renal cancer indicated that significant predictors were obesity (OR=2.1, p<0.001), smoking (OR=2.4, p<0.001), and recurrent UTIs (OR=2.1, p<0.001). The biggest risk indicators were hypercalciuria (OR=2.3, p<0.001) and chronic inflammation (OR=2.6, p<0.001), both of which clearly indicated their important part in the development of disease (Table 3). Significant genetic changes causing urinary calculi and renal cancer were highlighted by molecular study of the VHL, PBRM1 and MET genes. Located on chromosome 3, VHL gene (PDB ID: 1VCB) displayed large numbers of mutations (293) and copy number variants (CNVs) (4,261). Missense mutations (R161*) were the most often occurring. This fits its function as a tumor suppressor and implies that VHL mutations could induce cancer. With frameshift mutations (I279Yfs*4) mostly, analysis identified the largest mutation count (561) and considerable CNV occurrences (4,439) for PBRM1 (PDB ID: 3IU5), likewise on chromosome3. These results highlighted the role of PBRM1 in chromatin remodeling and its possible influence on the development of renal cancer by structural changes. Located on chromosome7, MET gene (PDB ID: 1MJQ) showed substantial amplification events (4,956 CNVs), suggesting possible carcinogenic function by gene overexpression. The overall mutations (387) showed MET’s participation in receptor tyrosine kinase signaling, which might help cancer spread and advance (Table 4).
Table 2 Clinical and Biochemical Characteristics of Patients.
| Parameter | Mean ± SD | Chi-Square | p-Value |
|---|---|---|---|
| Serum Creatinine (mg/dL) | 1.4 ± 0.6 | — | — |
| Blood Urea Nitrogen (mg/dL) | 16.7 ± 7.6 | — | — |
| Calcium (mg/dL) | 9.3 ± 0.7 | 9.0 | 0.002* |
| Phosphate (mg/dL) | 3.7 ± 0.5 | 7.5 | 0.005* |
| Uric Acid (mg/dL) | 5.5 ± 1.3 | 5.8 | 0.017* |
| Glucose (mg/dL) | 96.2 ± 17.9 | 10.3 | 0.001* |
| Hematuria n(%) | 213 (40.5) | 12.6 | 0.001* |
| Proteinuria n(%) | 127 (24.1) | 8.1 | 0.003* |
| Crystal Type (Calcium Oxalate) n(%) | 308 (58.6) | 11.0 | 0.001* |
| Nuclear Atypia n(%) | 63 (12.0) | 5.5 | 0.021* |
Table 3 Risk Factors Associated with Co-occurrence of Urinary Calculi and Renal Carcinoma.
| Risk Factor | Odds Ratio (OR) | Chi-Square | p-Value |
|---|---|---|---|
| Obesity (BMI > 30) | 2.1 (1.5-3.1) | 10.8 | 0.001* |
| Hypertension | 1.8 (1.3-2.5) | 8.9 | 0.002* |
| Diabetes Mellitus | 1.7 (1.2-2.3) | 6.9 | 0.011* |
| Smoking | 2.4 (1.7-3.4) | 12.4 | 0.001* |
| Alcohol Consumption | 1.5 (1.1-2.1) | 6.1 | 0.019* |
| Recurrent UTI | 2.1 (1.5-2.9) | 11.5 | 0.001* |
| Family History of Renal Carcinoma | 2.0 (1.3-3.1) | 7.8 | 0.005* |
| Hypercalciuria | 2.3 (1.7-3.2) | 13.3 | 0.001* |
| Hyperuricemia | 1.8 (1.3-2.5) | 9.9 | 0.002* |
| Chronic Inflammation | 2.6 (1.9-3.6) | 14.4 | 0.001* |
Table 4 Molecular Analysis of VHL, PBRM1, and MET Genes.
| Gene Symbol | PDB ID | Gene Name | Chromosomal Location | Total Mutations | Total CNV Events | Most Common Mutation Type | NCBI Gene ID | UniProt ID |
|---|---|---|---|---|---|---|---|---|
| VHL | 1VCB | von Hippel-Lindau tumor suppressor | chr3:10141778-10153667 | 293 | 4,261 | Missense (R161*) | 7428 | P40337 |
| PBRM1 | 3IU5 | polybromo 1 | chr3:52545352-52685917 | 561 | 4,439 | Frameshift (I279Yfs*4) | 55193 | Q86U86 |
| MET | 1MJQ | MET proto-oncogene, receptor tyrosine kinase | chr7:116672196-116798377 | 387 | 4,956 | Amplification | 4233 | P08581 |
Obtained from the RCSB Protein Data Bank, 3D structural models of three important proteins linked with renal cancer. The VHL protein structure revealed complicated shape with unique alpha-helices and beta-sheets, therefore stressing its function as tumor suppressor engaged in the breakdown of hypoxia-inducible factors. VHL mutations compromised this process, which helped to produce renal cell cancer. PBRM1 Protein, prominent alpha-helices in the PBRM1 structure fit its role in chromatin remodeling. Part of the SWI/SNF complex, this protein may be dysregulated by mutations in PBRM1, therefore encouraging oncogenesis in kidney tissue. The MET proto-oncogene structure shows a clearly defined receptor tyrosine kinase fold, hence stressing its function in signal transduction (c) MET Protein. In MET, amplitudes and mutations helped to increase signaling, which fueled renal carcinoma’s tumor development and metastases. These structural revelations taken together gave biological basis for comprehending the functional disturbances brought about by genetic changes in kidney cancer-associated proteins (Figure 1).
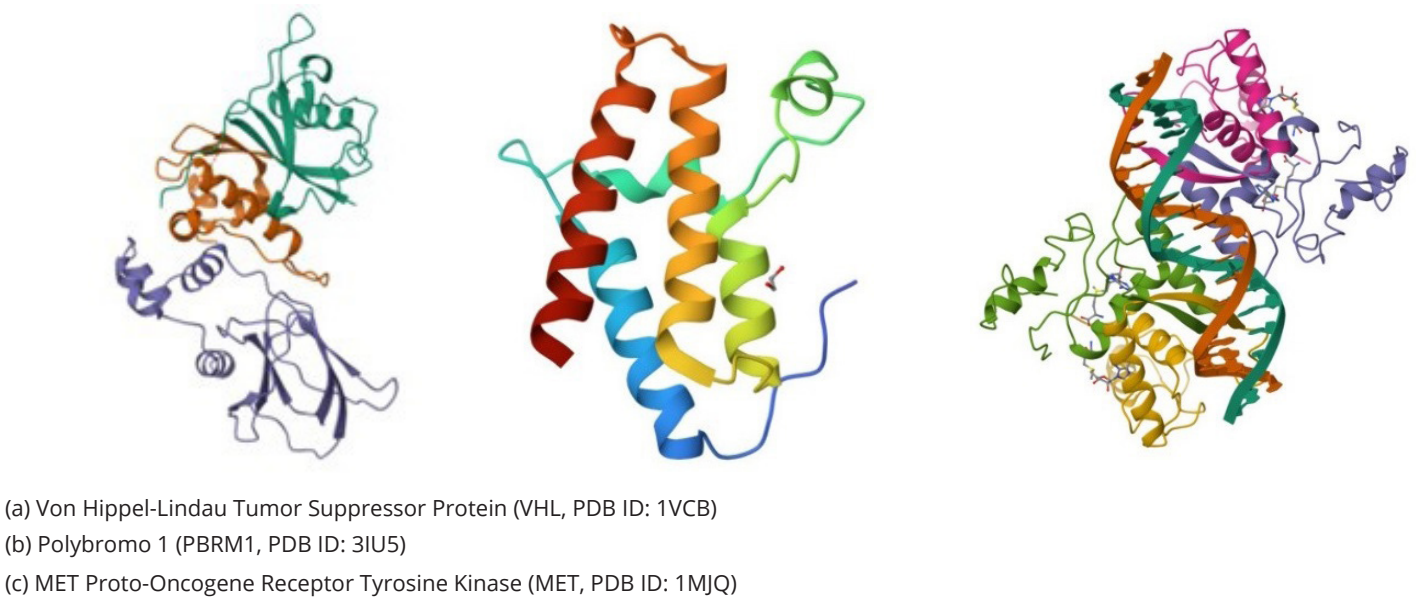
Key new perspectives on the functions of VHL, PBRM1 and MET proteins in renal cancer come from 3D structural research. Common missense mutations most likely compromise the complex structure VHL reveals is essential for HIF degradation, which fuels tumor growth. With its chromatin remodeling domains, PBRM1 displays frameshift mutations that disturb gene control and hence enable cancer growth. Features a receptor tyrosine kinase fold, MET has gene amplitudes linked to higher oncogenic signaling. These structural abnormalities fit our clinical and genetic data, which helps to explain the noted co-occurrence of urinary calculi and renal cancer. The VHL protein’s crystal structure shows its unique alpha-helices and beta-sheets that create a stable complex crucial for its function in degrading hypoxia-inducible factors (HIF). This structure is disrupted in particular by missense mutations like R161*, which compromises its activity and could cause unregulated cell proliferation and tumor development linked with renal cancer in our cohort (Figure 2).
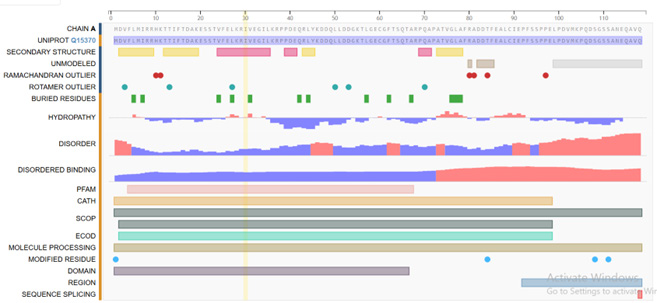
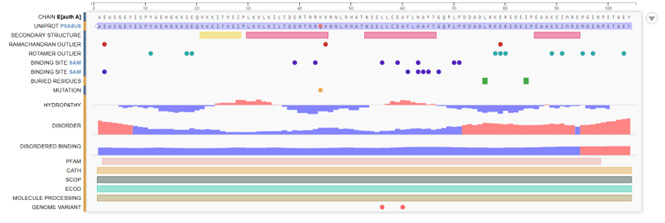
VHL’s reference sequence study points out important structural regions and mutation hotspots. Notable are the profiles of hydropathy and disorder that suggest areas of functional instability. The existence of hidden residues mutations and binding site changes fits our observed genetic variability and points to a biological cause of reduced protein function and higher cancer risk (Figure 3).
PBRM1 has a sophisticated design including numerous chromatin-interacting domains shown structurally. Like I279Yfs*4, frameshift mutations compromise the protein’s capacity to control chromatin remodeling, therefore causing possibly abnormal gene expression. This fits the rising incidence of renal cancer in people with these mutations, as our study found (Figure 4).
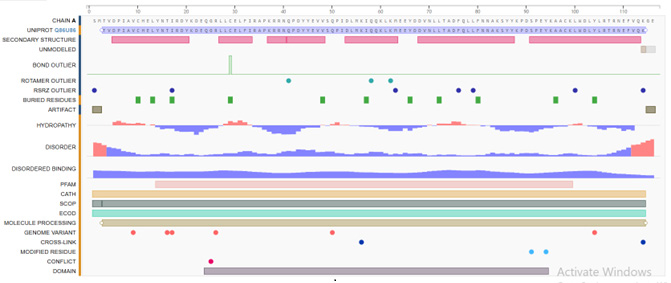
Especially in the chromatin-interacting domains, reference sequence analysis of PBRM1 exposes notable areas of structural variation and disorder. Mutations in these domains help to explain the loss of chromatin control seen in patients with concurrent urinary calculi and renal cancer by matching their observed higher tumorigenic potential (Figure 5).
Crucially for signal transduction, MET protein has a receptor tyrosine kinase fold shown by its crystal structure. Identified in our investigation, amplitudes of the MET gene improve this signaling capacity and support oncogenesis. The structural study implies that these changes support aggressive tumor morphologies in renal cancer instances (Figure 6).

Particularly in the kinase domain, sequence study of MET emphasizes notable hydropathy and mutation patterns. Changes in binding sites and higher disorder point to possible hyperactive signaling, which fits the clinical presentation of aggressive renal carcinoma seen in our patients and therefore supports the relationship between MET amplitudes and cancer development (Figure 7).
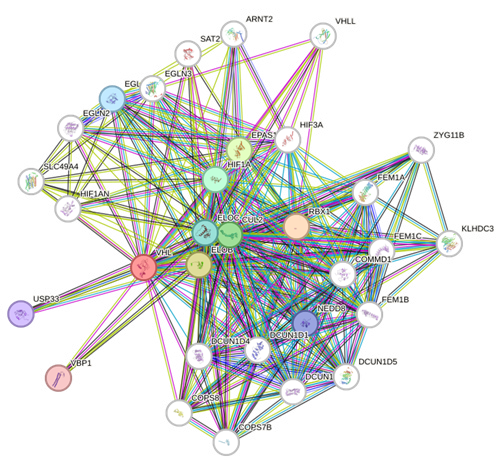
Developed using the STRING database, protein-protein interaction network for the VHL tumor suppressor protein was visualized. This network shows several interacting partners, therefore stressing VHL’s function in complex signaling environment linked in tumor suppression. Essential components of the VHL complex accountable for the ubiquitination and degradation of HIF1A under normal oxygen conditions, key interactions were observed with proteins including CUL2 (Cullin 2), HIF1A (Hypoxia-inducible factor 1-alpha) and ELOB (Elongin B). VHL’s strong pivotal function in cellular oxygen sensing, hypoxia response and control of cell cycle progression was highlighted by its dense interaction with several other proteins including RBX1 and NEDD8. The network also showed the interactions with multiple other signaling proteins engaged in different biological processes, therefore revealing the general functional consequences of VHL mutations in renal cancer and associated diseases. This network study clarified the complex biochemical pathways where VHL is essential and contributes to cancer development by dysregulation (Figure 8).
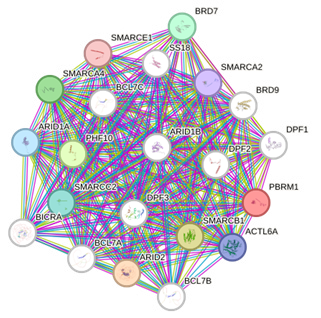
The PBRM1 protein-protein interaction network indicated the key member of the SWI/SNF chromatin-remodeling complex PBRM1 interacts with several other fundamental proteins engaged in chromatin architecture and transcription control. All essential to the SWI/SNF complex, notable interacting partners are ARID1A, SMARCA4, SMARCB1 and ACTL6A. The strong influence of PBRM1 in changing chromatin shape, thereby affecting gene expression and cellular processes, is suggested by the dense network of connections. Other chromatin remodelers, notably BRD9 and DPF1, also emphasize PBRM1’s cooperative role in preserving chromatin accessibility and transcriptional control. Understanding PBRM1’s function in carcinogenesis depends on these relationships since mutations in PBRM1 and its interacting proteins are frequently linked to several malignancies, including renal carcinoma (Figure 9).
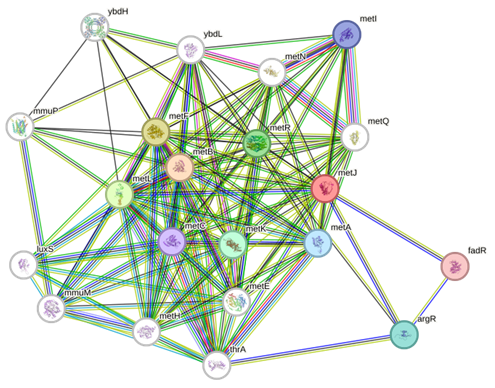
The dense character of these enzymes and their significance in physiological functions such methylation, amino acid biosynthesis and signaling pathways reflect in the numerous interconnections. Especially the existence of proteins like luxS and fadR points to cross-talk between methionine metabolism and other pathways including quorum sensing and fatty acid metabolism. This all-encompassing interaction map emphasizes the functional intricacy of MET and its central importance in cellular metabolism, therefore offering understanding of possible dysregulation processes in malignancies, where MET amplification is usually seen (Figure 10).
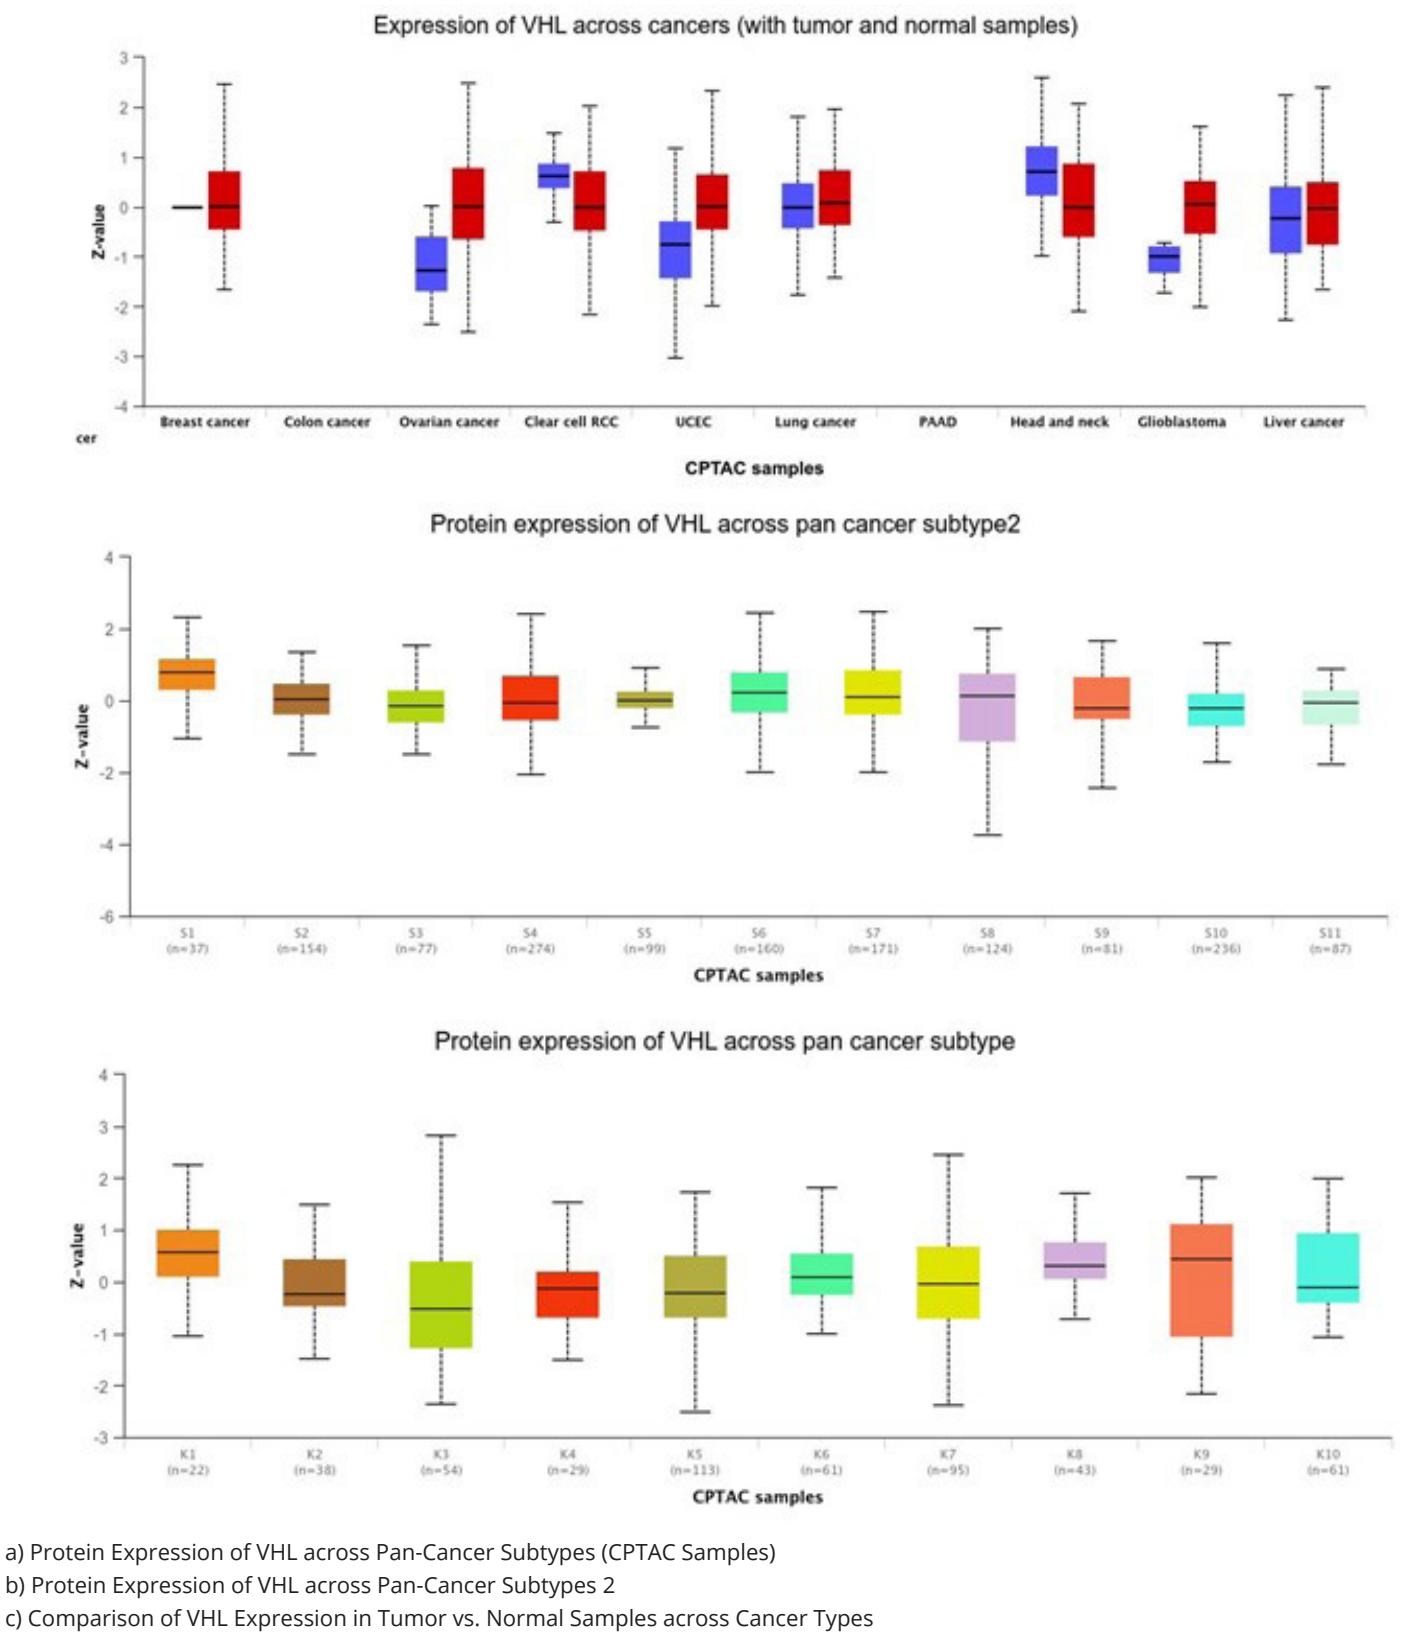
The protein expression patterns of the VHL gene across several cancer subtypes were emphasized, therefore providing insightful information on its function in carcinogenesis. Using CPTAC samples, subfigure (a) shows the VHL protein expression across several cancer types with noteworthy variability and downregulation in RCC relative to other malignancies. Emphasizing its potential as a diagnostic biomarketer, subfigure (b) broadens this study over other pan-cancer subtypes and reveals varying expression levels in different tumor profiles. Finally, subfigure (c) shows a notable downregulation in tumor tissues, especially in glioblastoma and clear cell RCC, by contrasting VHL expression between tumor and normal samples over many cancer types. These findings point to VHL’s loss of function in cancer progression, so complementing its tumor-suppressive action (Figure11).
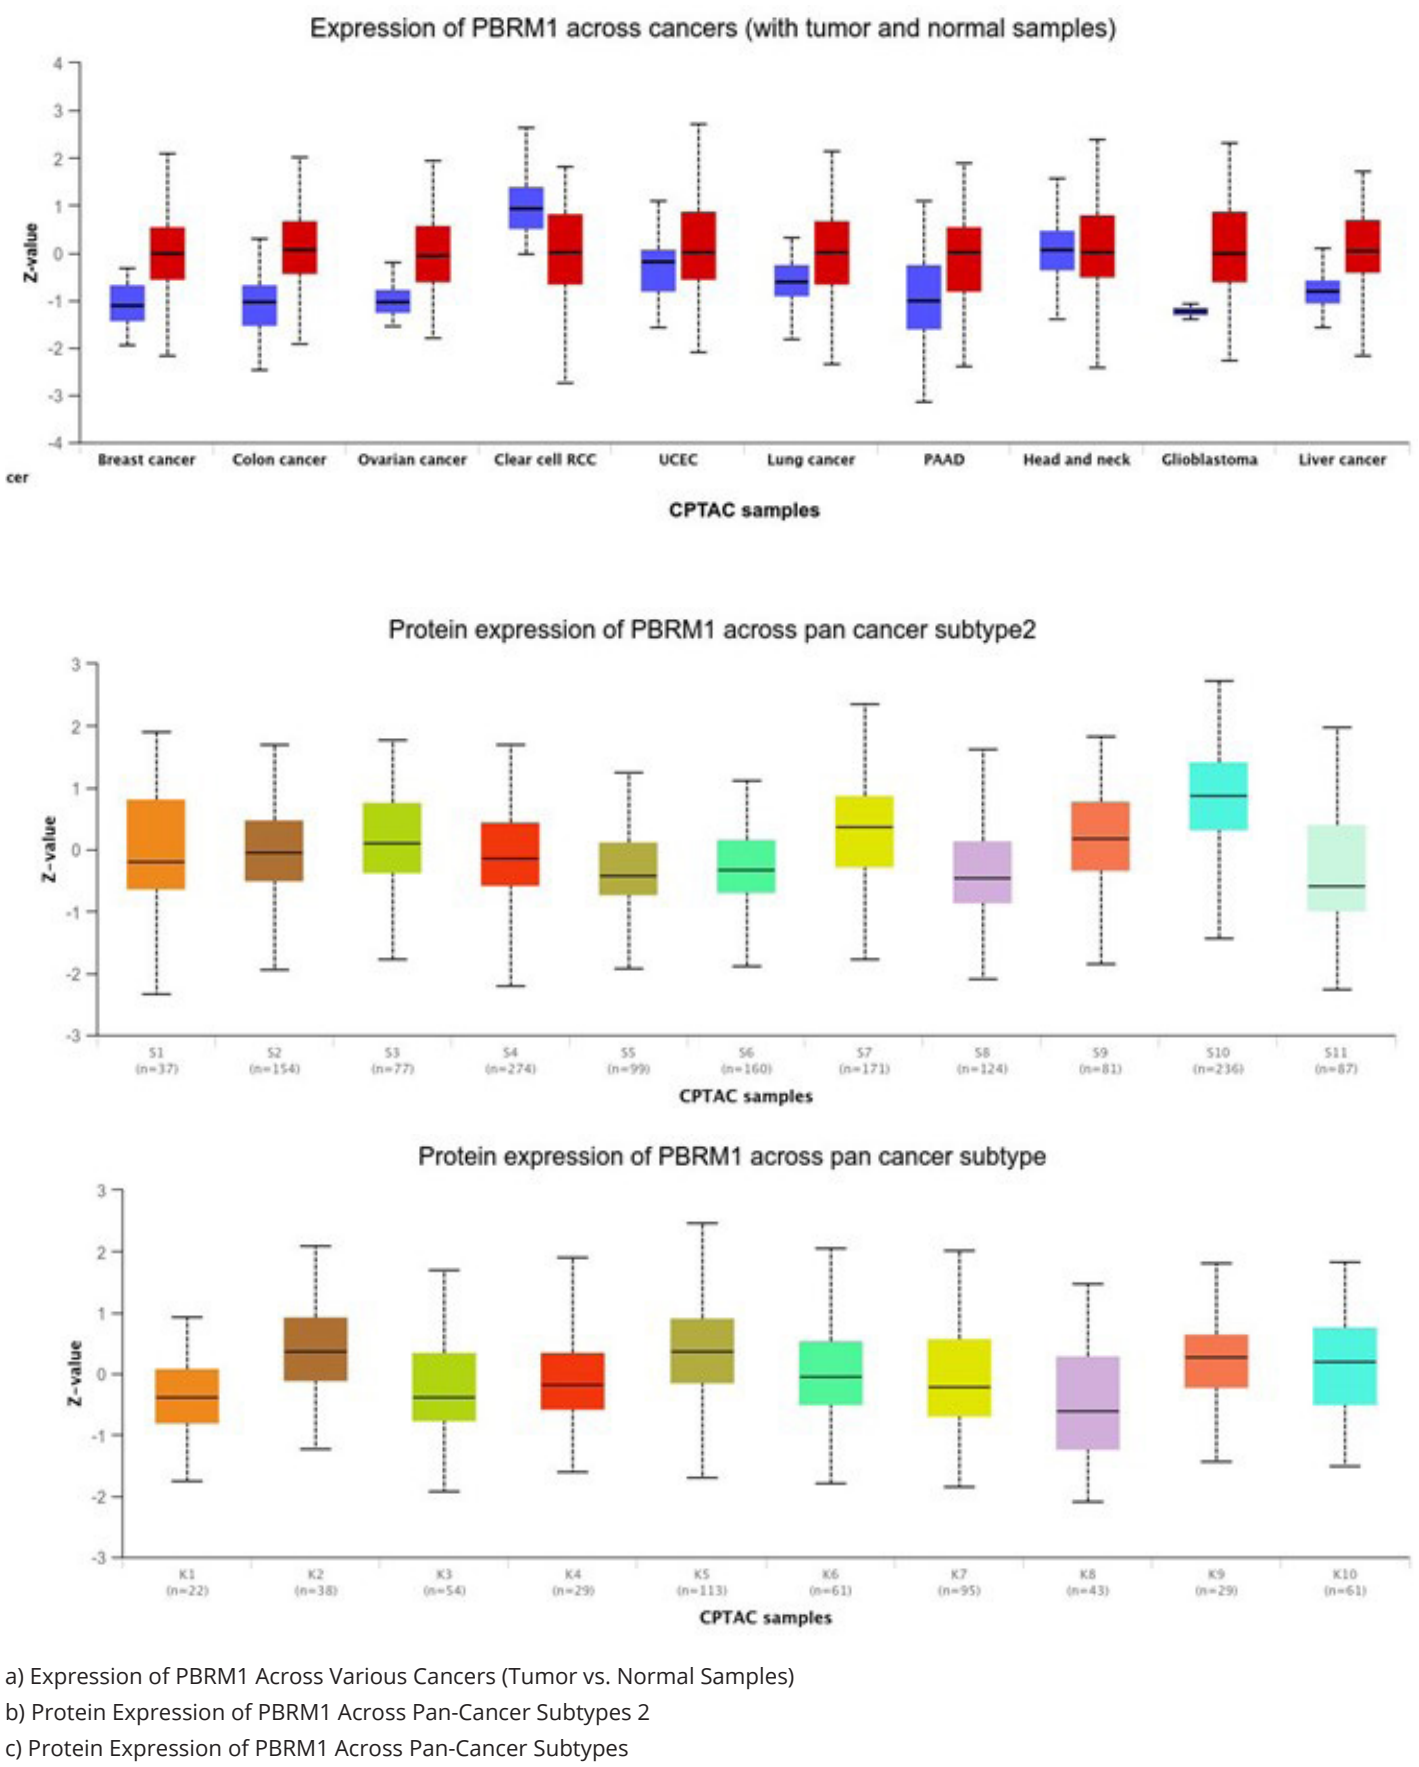
A thorough investigation of PBRM1 protein expression among several cancer types presented the comparison of PBRM1 expression in tumor against normal samples over several malignancies. Especially in RCC, lung cancer and ovarian cancer, the red boxes show greater expression levels in tumor tissues, implying a possible function of PBRM1 in oncogenesis. Panel b shows the difference in PBRM1 protein expression among several pan-cancer subtypes, with a similar distribution with some subtypes demonstrating greater median expression levels, thereby indicating subtype-specific regulating mechanisms. Panel c highlights possible subtype-specific variations in PBRM1 involvement in tumor biology by further breaking down PBRM1 expression across other cancer subtypes, hence displaying diverse expression trends. These studies taken together highlight the significance of PBRM1 in several oncogenic environments and suggest its possible use as a cancer diagnosis and prognostic biomarkers (Figure 12).
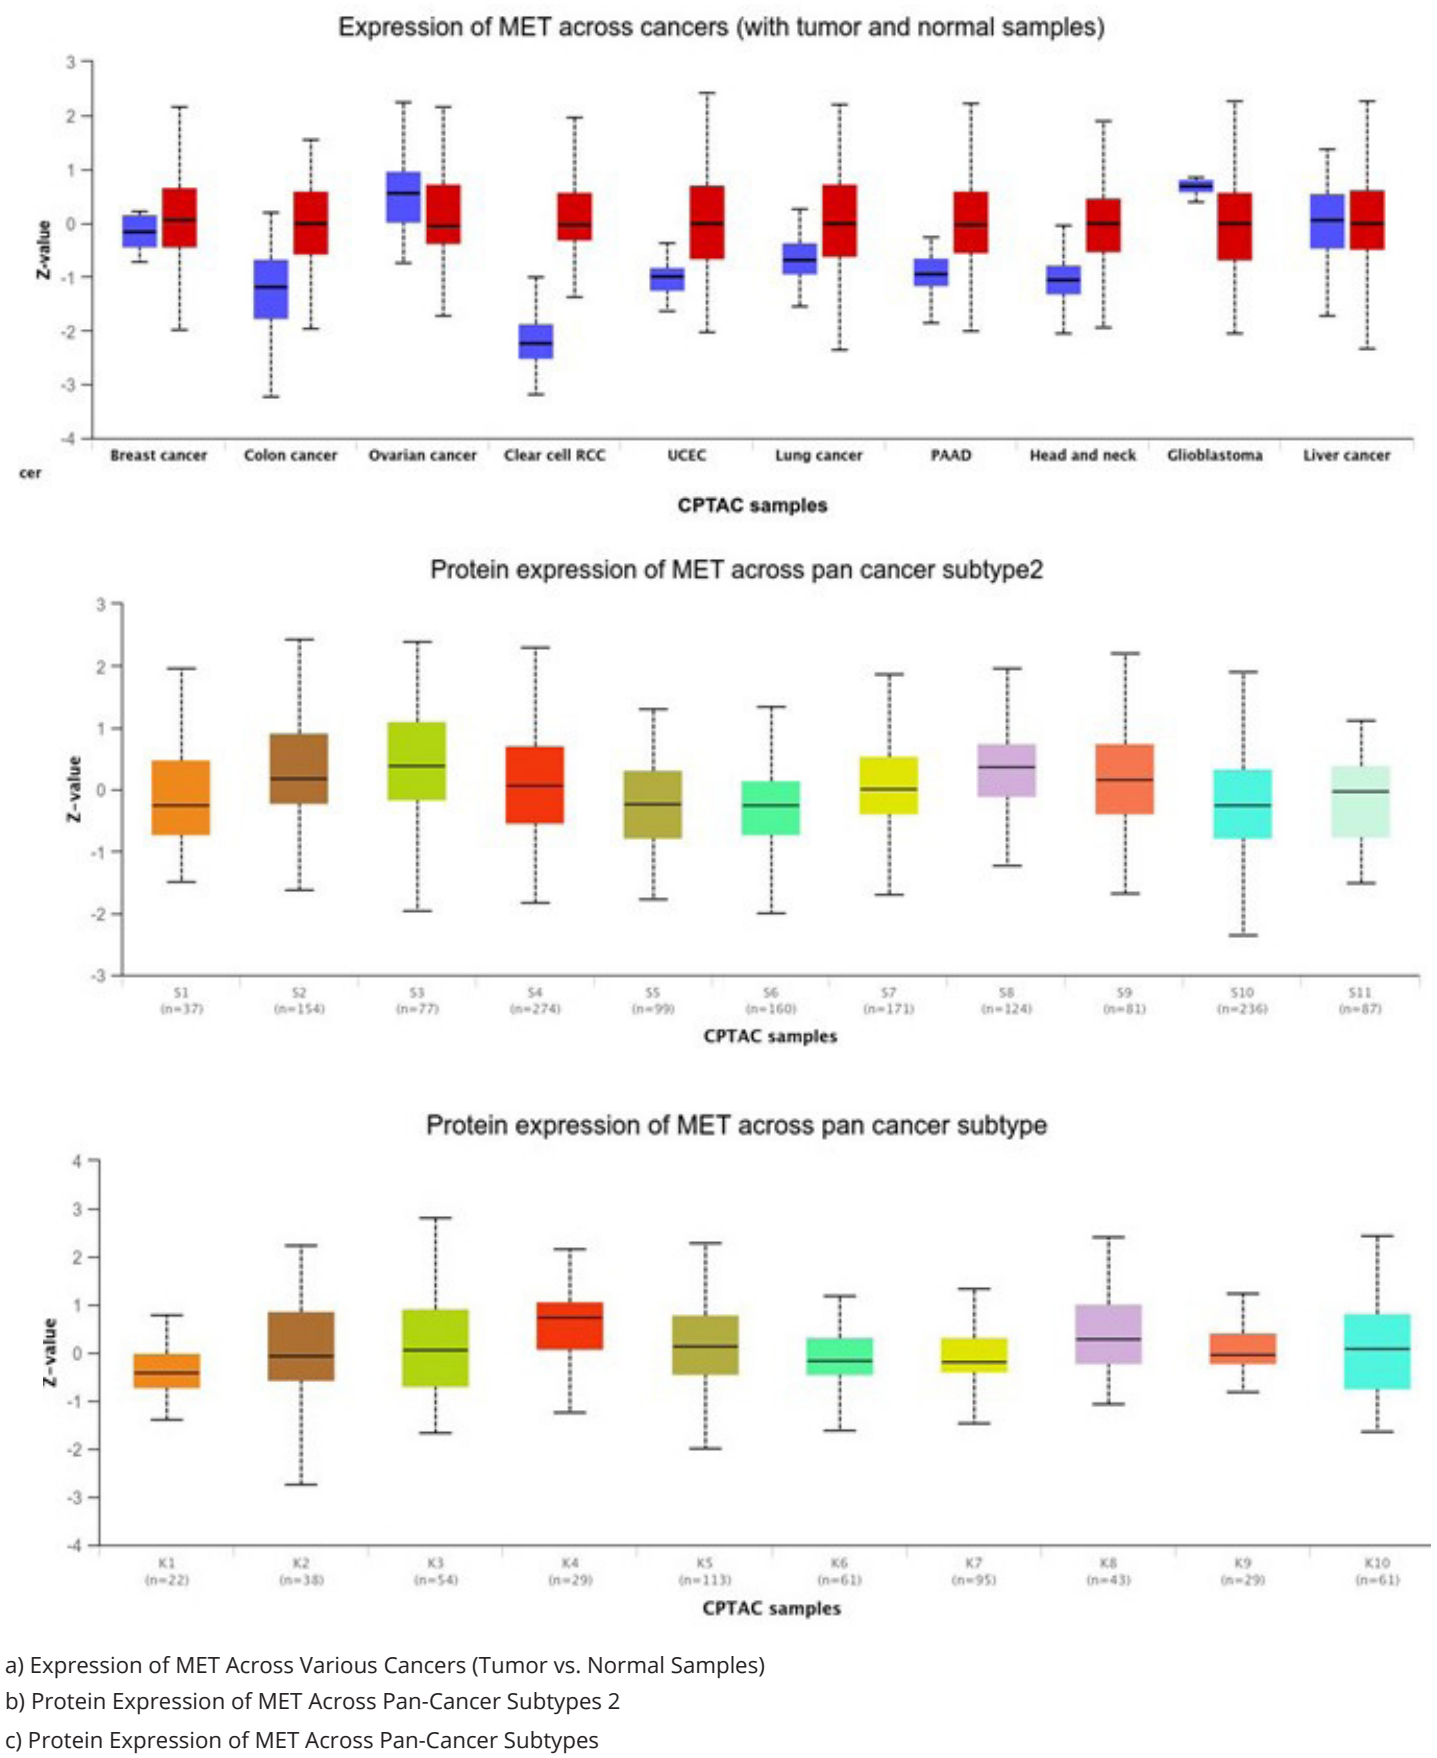
Different and important trends in protein expression analysis of VHL, PBRM1 and MET genes across several cancer subtypes highlighted their functions in carcinogenesis. VHL suggested its possible use as a cancer marker since it expresses itself clearly in tumor tissues, especially in ovarian cancer and clear cell RCC. Consistently increased in tumor samples across cancers including colon and lung cancer, PBRM1 expression suggests its participation in tumor growth. MET supports its oncogenic function by showing substantial overexpression in tumors including colon and lung cancer. These results underline the relevance of VHL, PBRM1 and MET in cancer pathogenesis as well as their possible targets for treatment approaches of RCC (Figure 13).
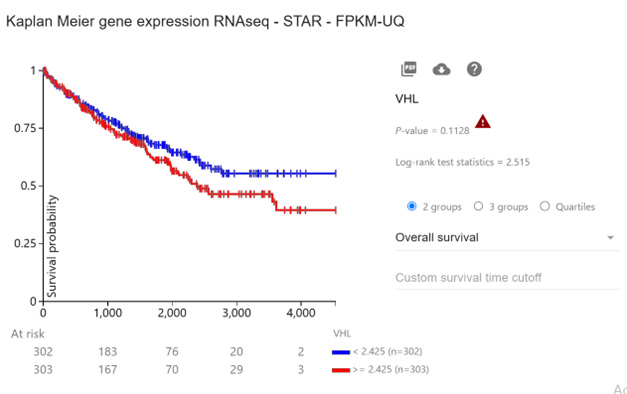
The influence of VHL levels on general patient survival is shown by the Kaplan-Meier survival analysis for VHL gene expression. Lower expression (< 2.425) and greater expression (> 2.425) are two groups compared in the plot depending on VHL expression levels. Red line, the survival probability curve for the high-expression group, reveals somewhat worse prognosis than the blue line, the low-expression group. Though survival trends show clear variation, p-value of 0.1128 (Figure 14).
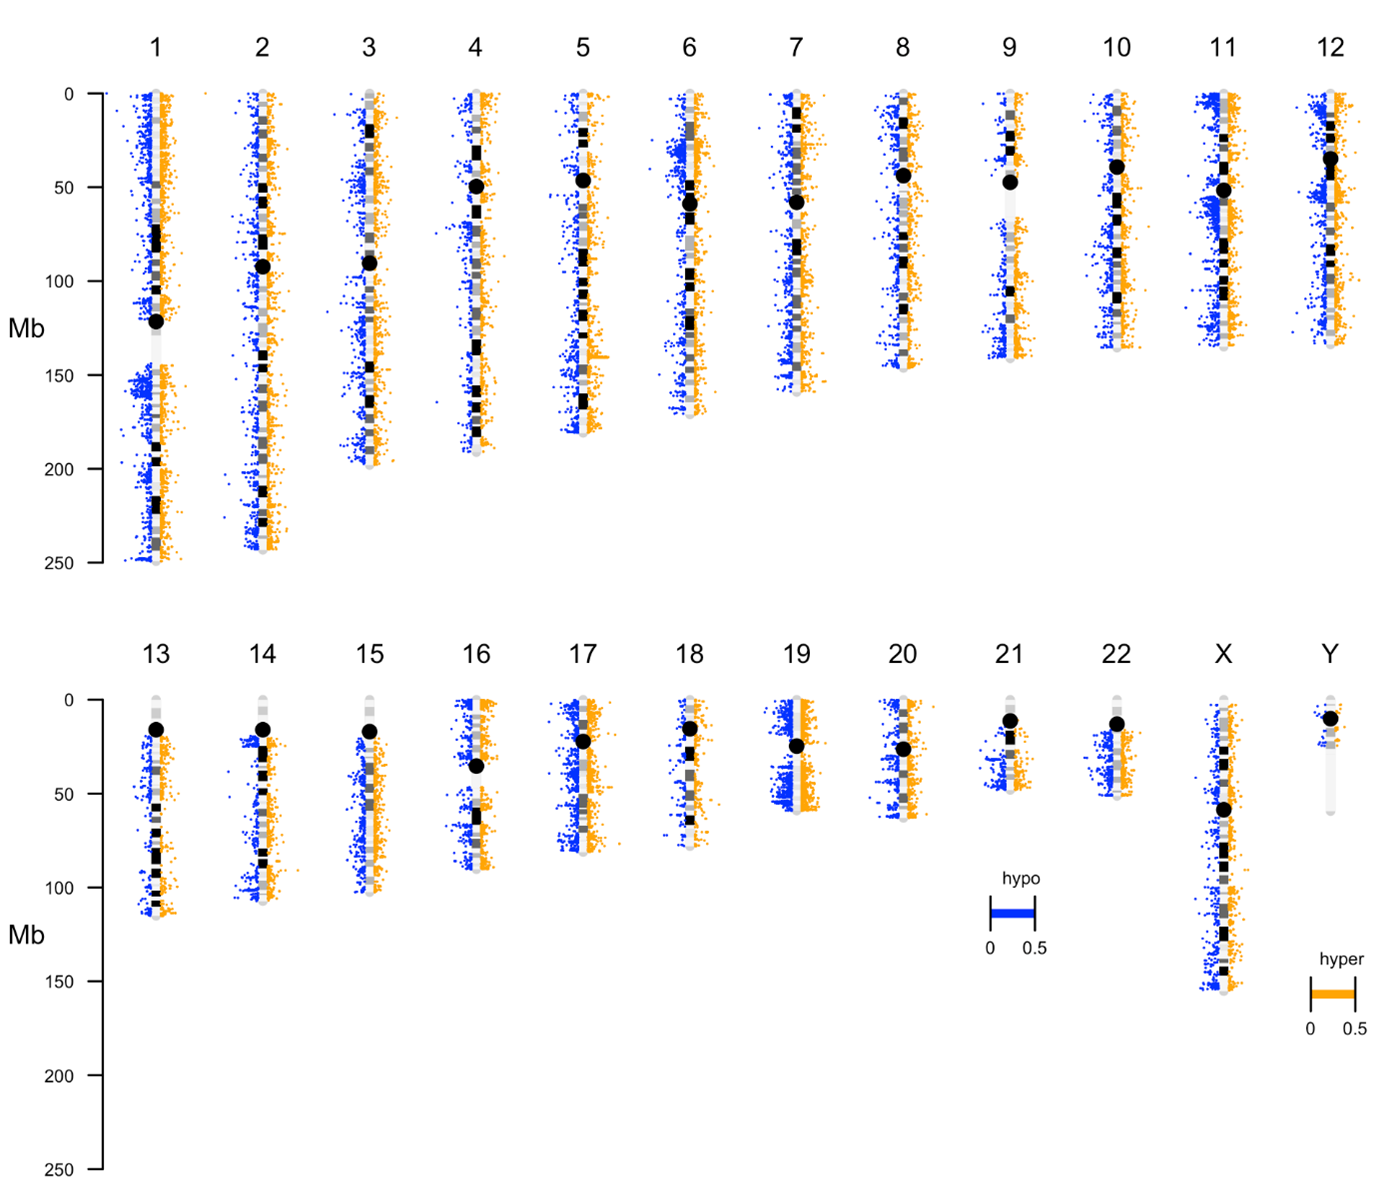
Over all chromosomes (1–22, X, and Y), the figure shows a genome-wide methylation profile combining hypomethylation (blue) and hypermethylation (orange). The chromosome location expressed in megabytes (Mb) is indicated by the vertical axis. Every dot marks methylation events; blue denotes areas of hypo-reduced methylation and orange denotes areas of hypermethylation. The distribution points to fluctuations in methylation level; some areas exhibit clear trends of hypomethylation or hypermethylation. For instance, whereas broad hypomethylation is shown in chromosomes like 5 and 12, chromosomes like 1, 4, and X display clear clusters of hypermethylated areas. Such variations in methylation patterns were suggestive of epigenetic modifications connected to disease states, including cancer. The graphic emphasizes the need of looking at particular chromosomal sites for their function in gene control and disease development (Figure 15).
The important indicators of patient inflammatory and oxidative stress had substantial correlation (p < 0.001), CRP levels averaged 8.9 mg/L, implying increased systemic inflammation. Also raised were IL-6 and TNF-α, therefore underscoring their part in inflammatory processes. High levels of oxidative damage shown by oxidative stress indicators like malondialdehyde (MDA) and Reactive Oxygen Species (ROS) suggested relatively low Total Antioxidant Capacity (TAC) indicated lowered antioxidant protection, therefore confirming the existence of oxidative stress in the research group (Table 5).
Table 5 Laboratory Markers for Inflammation and Oxidative Stress.
| Marker | Mean ± SD | Chi-Square | p-Value |
|---|---|---|---|
| C-Reactive Protein (CRP) | 8.9 ± 3.5 mg/L | 11.5 | 0.001* |
| Interleukin-6 (IL-6) | 15.7 ± 6.2 pg/mL | 9.7 | 0.002* |
| Tumor Necrosis Factor-alpha (TNF-α) | 22.4 ± 8.1 pg/mL | 10.3 | 0.001* |
| Reactive Oxygen Species (ROS) Level | 145.3 ± 32.7 RFU | 8.6 | 0.004* |
| Malondialdehyde (MDA) | 2.8 ± 1.1 nmol/mL | 7.9 | 0.005* |
| Total Antioxidant Capacity (TAC) | 1.2 ± 0.4 mmol/L | 6.5 | 0.010* |
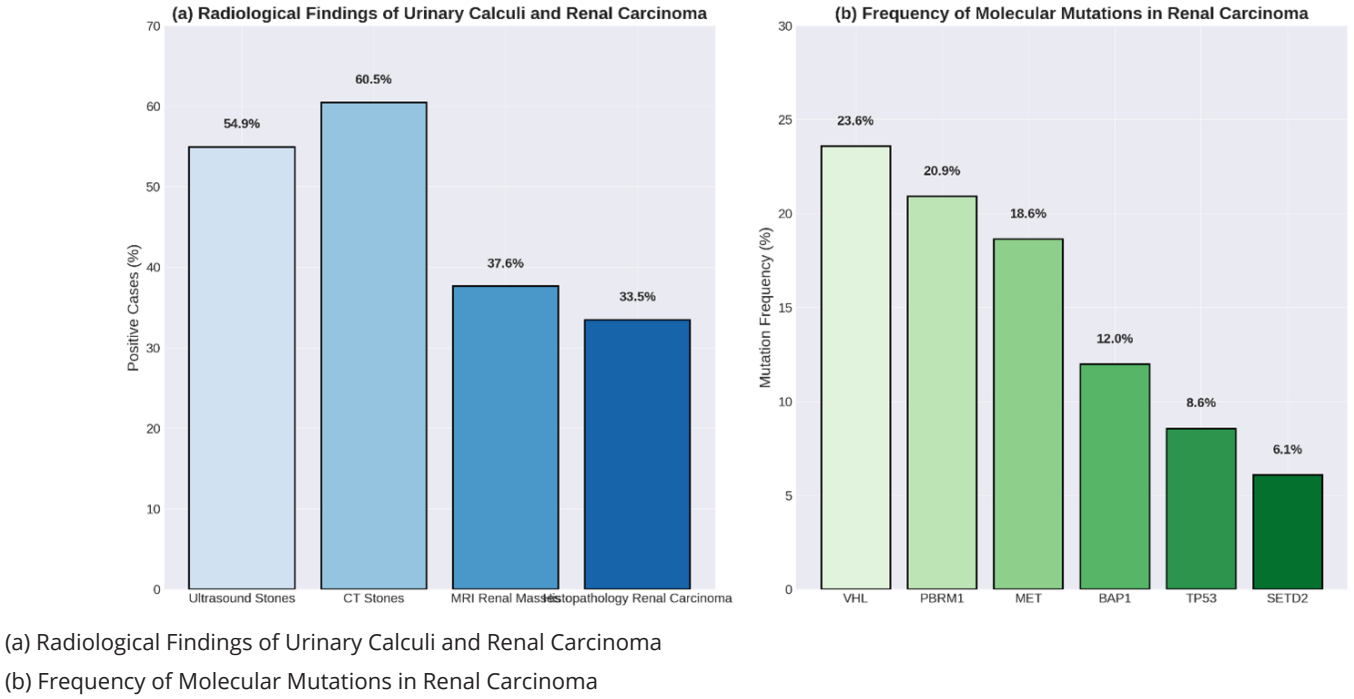
The frequency of several radiological abnormalities helped to identify urinary calculi and renal cancer. With stones found in 60.5% of instances, CT scans were the most efficient imaging tool for spotting calculi. In 54.9% of cases ultrasound found stones; in 37.6% of cases MRI found kidney masses. In 33.5% of cases there was histopathological confirmation of kidney cancer. These results implied that while histology is still necessary to confirm renal cancer, CT scans are the most dependable imaging tool for urinary calculi detection. Pertaining to the molecular mutations, key genes linked to renal cancer had mutation frequency, i.e. VHL (23.6%), PBRM1 (20.9%) and MET (18.6%), are the most often altered genes followed by lower frequency we found mutations in BAP1 (12.0%), TP53 (8.6%) and SETD2 (6.1%). This trend highlighted the possible function of mutations in tumor suppressor genes such as VHL and PBRM1 in the etiology of renal carcinoma since they show a great frequency (Figure16).
4 Discussion#
The clinical and molecular elements linked with the co-occurrence of urinary calculi and renal cancer were thoroughly analyzed in this study. Our study found important relationships between common risk factors, biochemical indicators and important molecular changes that help to clarify the fundamental processes connecting two common urological diseases.
Consistent with the recognized epidemiology of both urinary calculi and renal cancer, the demographic analysis of our study sample revealed predominance of men with the mean age of 55.8 years. Men’s higher incidence can be ascribed to lifestyle choices including higher rates of smoking, obesity and metabolic syndrome in this group. Similar male predominance has been seen in past studies; lifestyle choices including smoking and obesity are acknowledged as main risk factors for both renal stone development and renal cancer growth 15-16 . Furthermore identified to be notably linked in our sample to urinary calculi and renal cancer were disorders like diabetes mellitus and hypertension. Through means of chronic renal injury and changes in renal hemodynamics, hypertension is known to contribute to nephrolithiasis and has been linked in renal carcinogenesis 17 . Likewise, our results indicated the association between diabetes mellitus which is marked by hyperinsulinemia and oxidative stress and increased stone development and cancer risk.
Our investigation linked recurrent UTIs with both urinary calculi and renal cancer to inflammatory mechanism. Recurrent UTIs may cause chronic inflammation in the renal epithelium, which would caused tissue remodeling, fibrosis and milieu fit for neoplastic development. This fits the inflammation-carcinogenesis report put forth in earlier studies, according to which inflammation and chronic infections have been found to be risk factors for several malignancies, including renal cancer 18 .
Our study of biochemical markers revealed higher serum creatinine, uric acid and hypercalciuria, suggested metabolic abnormalities typical of patients with both urinary calculi and renal cancer. Common in our study population, hypercalciuria, being well-known risk factor for nephrolithiasis, was clearly important for stone development and possible relation to carcinogenesis. Often linked with gout and metabolic syndrome, elevated blood uric acid was also seen and suggested that metabolic problems might make people prone to both diseases. Studies showing that hyperuricemia can cause oxidative stress and inflammation confirmed this observation: rendering damage to renal tissue and cancer19-20 .
Frequent mutations in VHL, PBRM1 and MET genes, key genetic changes found by molecular study of tumor tissue, raised questions about RCC. Frequent mutations in our cohort were shown in the well-known tumor suppressor VHL. Clear cell RCC was typified by loss-of-function mutations in VHL, which caused hypoxia-inducible factors (HIFs) to stabilize and carcinogenic pathways to activate. This result fits earlier studies showing that up to 90% of clear cell RCC cases have VHL mutations 21 . The significant mutation rate seen in PBRM1, a chromatin remodeling gene, points to its involvement in changing the epigenetic terrain of kidney malignancies, hence fostering aggressive phenotypes and tumor growth. This is in line with past findings showing PBRM1 as 2nd altered gene in clear cell RCC, linked to tumor suppressor activities 22-23 .
Detectable in considerable number of patients, amplification of the MET proto-oncogene emphasized its relevance in non-clear cell RCC subtypes, especially papillary RCC. The MET gene genes for a receptor tyrosine kinase engaged in cell differentiation, motility and growth. Enhanced tumor invisibility and poor prognosis in renal cancer have been associated to overxpression and MET activation 24 . Our results confirmed the mounting evidence that MET changes were main driver of oncogenesis in particular RCC subtypes, therefore providing a possible therapeutic target.
According to our radiological results, CT proved to be the most successful imaging tool for urinary calculi and renal masses detection. This is in line with current research showing CT as the gold standard for stone detection since its great sensitivity and capacity to view both radiopaque and radiolucent stones25 . Finding renal cancer in significant number of instances accompanied by concomitant urinary calculi points to a possible clinical route for early renal tumor detection in individuals presenting with nephrolithiasis. The histological evidence of renal cancer in these patients emphasizes the need of careful follow-up and diagnostic imaging for patients with recurrent stone illness.
Our patients’ high levels of inflammatory markers point to chronic inflammation state that might be relevant for the pathogenesis of both urinary calculi and renal cancer. Because it can cause DNA damage, encourage cellular proliferation and generate a tumor-promoting milieu 26-27 , chronic inflammation is a well-known contributor to cancer development. Our study’s heightened ROS and malondialdehyde (MDA) levels point to higher oxidative stress, which might help to explain renal epithelial cell damage and later neoplastic transformation. These patients’ lower total antioxidant capacity (TAC) points to a reduced defense against oxidative damage, consistent with research linking oxidative stress to the start and spread of RCC 28 .
The molecular changes found in our work shed light on the possible routes of co-occurrence of urinary calculi and renal cancer. VHL function was disrupted, which caused HIF-1α to accumulate and upregulates angiogenic and metabolic genes that fuel tumor development. PBRM1 mutations change gene expression and enable oncogenic processes, therefore contributing to chromatin remodeling abnormalities. The amplification of MET and its downstream signaling cascades implies that individuals with papillary RCC or those with MET-driven oncogenesis could benefit from focused treatments including MET inhibitors 29 .
Our results underlined the importance of a comprehensive strategy for the treatment of individuals with urinary calculi and possible renal cancer. Routine genetic mutation screening for patients with recurrent stone disease especially those with metabolic abnormalities could help to early identify and treat renal cancer specifically for each patient. Future studies should concentrate on clarifying the molecular changes causing urinary calculi and renal cancer and investigating focused therapy approaches depending on the found molecular changes.
Ultimately, our work emphasized how dynamically clinical risk factors, metabolic abnormalities and genetic changes interact to cause urinary calculi and renal cancer. Our results showed that patients with recurrent nephrolithiasis may be more likely to develop renal cancer since they offer compelling proof for common paths including inflammation, oxidative stress and genetic alterations. Improving clinical outcomes in this patient population depends critically on early identification and customized therapy approaches.
5 Conclusion#
This study showed strong correlation between urinary calculi and renal carcinoma, stressing common clinical risk factors including hypertension, diabetes and recurrent UTIs, which might help to create pro-inflammatory and pro-tumorigenic milieu. Serum creatinine, uric acid and hypercalciuria among other elevated biochemical markers pointed to metabolic abnormalities connecting nephrolithiasis to higher risk of renal cancer. Emphasizing their function in carcinogenesis, especially in clear cell and papillary RCC subtypes, molecular study found frequent alterations in important genes like VHL, PBRM1 and MET. While PBRM1 and MET changes emphasized the significance of chromatin remodeling and receptor tyrosine kinase signaling respectively, the finding of VHL mutations highlighted the involvement of hypoxia-inducible factor pathways. These results implied that in the etiology of both diseases metabolic problems, chronic inflammation and certain genetic alterations could augment the condition. Early genetic screening and combined clinical management plans should improve early identification, risk stratification and customized therapeutic approaches to enhance the patient outcomes.
Declarations
€Funding
◎Competing interests
Article information
- Published
Copyright © 2024 Jin Li. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 29#
- 1
Mihalopoulos M, Yaghoubian A, Razdan S, Khusid JA, Mehrazin R, Badani KK, Sfakianos JP, Atallah WM, Tewari AK, Wiklund P, Gupta M, Kyprianou N. Understanding the link between kidney stones and cancers of the upper urinary tract and bladder. Am J Clin Exp Urol. 2022 Oct 15;10(5):277-298. PMID: 36313208; PMCID: PMC9605942.
- 2
Shastria S, Patela J, Sambandam KK, Lederer ED. Kidney stone pathophysiology, evaluation and management: Core Curriculum 2023. Am J Kidney Dis. 2023;82(5):617-634.
- 3
Khan SR, Pearle MS, Robertson WG, Gambaro G, Canales BK, Doizi S, Traxer O, Tiselius HG. Kidney stones. Nat Rev Dis Primers. 2016 Feb 25;2:16008. doi: 10.1038/nrdp.2016.8.
- 4
Allam EAH. Urolithiasis unveiled: pathophysiology, stone dynamics, types, and inhibitory mechanisms: a review. Afr J Urol. 2024;30:34. https://doi.org/10.1186/s12301-024-00436-z
- 5
Pandey J, Syed W. Renal cancer [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan- [updated 2024 Oct 4]. Available from: https://www.ncbi.nlm.nih.gov/books/NBK558975/
- 6
Moftakhar L, Jafari F, Ghoddusi Johari M, Rezaeianzadeh R, Hosseini SV, Rezaianzadeh A. Prevalence and risk factors of kidney stone disease in population aged 40-70 years old in Kharameh cohort study: a cross-sectional population-based study in southern Iran. BMC Urol. 2022 Dec 19;22(1):205. doi: 10.1186/s12894-022-01161-x.
- 7
Tamborino F, Cicchetti R, Mascitti M, Litterio G, Orsini A, Ferretti S, Basconi M, De Palma A, Ferro M, Marchioni M, et al. Pathophysiology and Main Molecular Mechanisms of Urinary Stone Formation and Recurrence. International Journal of Molecular Sciences. 2024; 25(5):3075. https://doi.org/10.3390/ijms25053075
- 8
50th Annual Meeting of the Arbeitsgemeinschaft Dermatologische Forschung (ADF). Exp Dermatol. 2024;33(3): e14994. https://doi.org/10.1111/exd.14994
- 9
Mahalingaiah PK, Ponnusamy L, Singh KP. Oxidative stress-induced epigenetic changes associated with malignant transformation of human kidney epithelial cells. Oncotarget. 2017 Feb 14;8(7):11127-11143. doi: 10.18632/oncotarget.12091.
- 10
Gad S, Le Teuff G, Nguyen B, Verkarre V, Duchatelle V, Molinie V, Posseme K, Grandon B, Da Costa M, Job B, Meurice G, Droin N, Mejean A, Couve S, Renaud F, Gardie B, Teh BT, Richard S, Ferlicot S. Involvement of PBRM1 in VHL disease-associated clear cell renal cell carcinoma and its putative relationship with the HIF pathway. Oncol Lett. 2021 Dec;22(6):835. doi: 10.3892/ol.2021.13096.
- 11
Warlia SM, Mantiric BJ, Sihombinga B, Siregara GP, Prapiskaa FF. Nephrolithiasis-associated renal cell carcinoma in patients who underwent nephrectomy: a single-center experience. World J Oncol. 2023;14(1):94-100.
- 12
Komiyama T, Kim H, Tanaka M, Isaki S, Yokoyama K, Miyajima A, Kobayashi H. RNA-seq and Mitochondrial DNA Analysis of Adrenal Gland Metastatic Tissue in a Patient with Renal Cell Carcinoma. Biology (Basel). 2022 Apr 13;11(4):589. doi: 10.3390/biology11040589.
- 13
Roos-Mattila M, Kallio P, Luck TJ, Polso M, Kumari R, Mikkonen P, Välimäki K, Malmstedt M, Ellonen P, Pellinen T, Heckman CA, Mustonen H, Puolakkainen PA, Alitalo K, Kallioniemi O, Mirtti T, Rannikko AS, Pietiäinen VM, Seppänen HE. Distinct molecular profiles and shared drug vulnerabilities in pancreatic metastases of renal cell carcinoma. Commun Biol. 2024;7:1355.
- 14
Zhang, S., Xiao, X., Yi, Y. et al. Tumor initiation and early tumorigenesis: molecular mechanisms and interventional targets. Sig Transduct Target Ther 9, 149 (2024). https://doi.org/10.1038/s41392-024-01848-7
- 15
Stamatelou K, Goldfarb DS. Epidemiology of Kidney Stones. Healthcare (Basel). 2023 Feb 2;11(3):424. doi: 10.3390/healthcare11030424.
- 16
Shih CJ, Chen YT, Ou SM, Yang WC, Chen TJ, Tarng DC. Urinary calculi and risk of cancer: a nationwide population-based study. Medicine (Baltimore). 2014 Dec;93(29):1-8.
- 17
Warli SM, Mantiri BJ, Sihombing B, Siregar GP, Prapiska FF. Nephrolithiasis-Associated Renal Cell Carcinoma in Patients Who Underwent Nephrectomy: A Single-Center Experience. World J Oncol. 2023 Feb;14(1):94-100. doi: 10.14740/wjon1560.
- 18
Dickson K, Zhou J, Lehmann C. Lower Urinary Tract Inflammation and Infection: Key Microbiological and Immunological Aspects. Journal of Clinical Medicine. 2024; 13(2):315. https://doi.org/10.3390/jcm13020315
- 19
Leslie SW, Sajjad H, Murphy PB. Renal Calculi, Nephrolithiasis. [Updated 2024 Apr 20]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK442014/
- 20
Ahmad A, Mustafa G, Hasan M. Hybrid kidney stones physicochemical and morphological characterization: a spectroscopic study analysis. Hybrid Adv. 2024;6:100259. https://doi.org/10.1016/j.hybadv.2024.100259.
- 21
Zhao Q, Hong B, Zhang X, Xue J, Guo S, Zhang N. Frequent gene mutations and the correlations with clinicopathological features in clear cell renal cell carcinoma: preliminary study based on Chinese population and TCGA database. BMC Urol. 2024;24:170.
- 22
Liao L, Testa JR, Yang H. The roles of chromatin-remodelers and epigenetic modifiers in kidney cancer. Cancer Genet. 2015 May;208(5):206-14. doi: 10.1016/j.cancergen.2015.02.008. Epub 2015 Feb 20.
- 23
Carril-Ajuria L, Santos M, Roldán-Romero JM, Rodriguez-Antona C, de Velasco G. Prognostic and Predictive Value of PBRM1 in Clear Cell Renal Cell Carcinoma. Cancers. 2020; 12(1):16. https://doi.org/10.3390/cancers12010016.
- 24
Zhao Q, Hong B, Zhang X, Xue J, Guo S, Zhang N. Frequent gene mutations and the correlations with clinicopathological features in clear cell renal cell carcinoma: preliminary study based on Chinese population and TCGA database. BMC Urol. 2024;24:170.
- 25
Crepaldi T, Gallo S, Comoglio PM. The MET Oncogene: Thirty Years of Insights into Molecular Mechanisms Driving Malignancy. Pharmaceuticals. 2024; 17(4):448. https://doi.org/10.3390/ph17040448
- 26
Kruk L, Mamtimin M, Braun A, Anders HJ, Andrassy J, Gudermann T, Mammadova-Bach E. Inflammatory Networks in Renal Cell Carcinoma. Cancers (Basel). 2023 Apr 9;15(8):2212. doi: 10.3390/cancers15082212.
- 27
Giovannini S, Onder G, Liperoti R, Russo A, Carter C, Capoluongo E, Pahor M, Bernabei R, Landi F. Interleukin-6, C-reactive protein, and tumor necrosis factor-alpha as predictors of mortality in frail, community-living elderly individuals. J Am Geriatr Soc. 2011 Sep;59(9):1679-85. doi: 10.1111/j.1532-5415.2011.03570.x.
- 28
Neganova M, Liu J, Aleksandrova Y, Klochkov S, Fan R. Therapeutic Influence on Important Targets Associated with Chronic Inflammation and Oxidative Stress in Cancer Treatment. Cancers (Basel). 2021 Dec 1;13(23):6062. doi: 10.3390/cancers13236062.
- 29
Cinque A, Minnei R, Floris M, Trevisani F. The Clinical and Molecular Features in the VHL Renal Cancers; Close or Distant Relatives with Sporadic Clear Cell Renal Cell Carcinoma? Cancers. 2022; 14(21):5352. https://doi.org/10.3390/cancers14215352.