Blastocystis sp.: frequency and typing among Irritable Bowel Syndrome (IBS) patients
Published in The Journal of Clinical Medicine
Buthaina Darwish
Buthaina Darwish- Department of Animal Biology, Faculty of Science, Damascus University, Damascus, Syria
Ghalia Aboualchamat
Ghalia Aboualchamat- Department of Animal Biology, Faculty of Science, Damascus University, Damascus, Syria
Samar Al Nahhas iD ✉
Samar Al NahhasCorresponding author- Department of Animal Biology, Faculty of Science, Damascus University, Damascus, Syria
Show affiliations (1)
- Department of Animal Biology, Faculty of Science, Damascus University, Damascus, Syria
Published
Abstract
Blastocystis is an intestinal protozoan that has been evaluated for its possible pathogenicity role in IBS disease. In Syria, no previous studies have focused on the presence of Blastocystis among IBS patients; therefore, this study aims to specify the frequency of Blastocystis parasite and its subtypes (STs) among IBS patients. Fecal samples were obtained from 70 patients; 35 IBS and 35 non-IBS patients. Samples were subjected to direct microscopic examination, and then studied by conventional PCR. Genotyping using seven specific primers targeting the SSU rRNA gene was employed. No significant correlation between gender was found (Chi- Square; P= 0.212); however, significant difference was found in ages among both groups (Mann-Whitney Test; P= 0.011). Blastocystis was detected in 71.4% (25/35) of IBS patients and in 77.1% (27/35) of non-IBS patients; nonetheless, the difference between the two groups was not statistically significant (P=0.299). Interestingly, a high proportion of single Blastocystis infection (88%; 22/25) was found among IBS patients’ samples compared to those of the non-IBS. Three different subtypes were identified, where ST1 subtype was the dominant in IBS patients and ST3 was found only in the non-IBS participants. In addition, the patients suffering from IBS had approximately a six-time increase risk of having flatulence symptoms compared to the non-IBS patients (OR:5.712; P= 0.001), and it was the main clinical symptoms found among IBS patients with ST1 subtype. In conclusion this study is the first in Syria to highlight the prevalence of Blastocystis sp. among IBS patients. Further studies are needed to investigate Blastocystis pathogenic role causing IBS syndrome.
1 Introduction#
Blastocystis sp. is the most common unicellular parasite living in the lower intestinal tract of humans and a wide range of vertebrates[1, 2]. Different routes of transmission were observed, namely zoonotic, anthroponotic and waterborne transmission[3, 4]. Genetic diversity is common among Blastocystis sp. with more than 41 subtypes being identified so far[5]. The pathogenic role of Blastocystis is controversial; recent studies have indicated its association with gastrointestinal disorders as inflammation bowel diseases (IBD) and irritable bowel syndrome (IBS),[6, 7].
IBS is a common healthcare problem with worldwide distribution[8]. The prevalence of IBS varies between developed and developing countries ranging between 5-24% and 35-43% respectively[9, 10]. Blastocystis has never been examined in IBS patients in any previous study in Syria; therefore, this study aimed to identify the frequency of Blastocystis and its subtypes (STs) among Syrian IBS patients.
2 Materials and Methods#
2.1 Ethical approval#
This study was approved and funded by Damascus University (approved No. 4031; funder No. 501100020595). Patients and their families were informed about the study and they signed a written informed consent.
2.2 Selection criteria and sample characterization#
IBS along with non-IBS patients were recruited in this study. All patients were attending the Al-Mouwasat University Hospital and the Syrian Specialty Hospital for diagnosis and therapy. Patients and their families were informed about the study, and a written consent was signed. A form about the clinical and epidemiological data was filled for each patient containing information about gender, age and presence of gastrointestinal symptoms. The study was conducted from November 2021 to February 2022.
2.3 Stool collection and examination#
Fecal specimens were obtained from both IBS and non-IBS individuals and collected in labeled and sterile containers. Stool smears were done as described by Manser et al.[11] and examined directly using light microscope (×40 magnifications). The diagnostic criterion adopted in determining the positivity of Blastocystis sp. infection was the detection of 2 to 5 vacuolar forms[12].
2.4 Molecular detection and genotyping#
Approximately, a fecal sample of 250–300 mg from each patient was used for genomic DNA extraction using QIAamp DNA stool mini kit (QIAamp DNA Stool Mini Kit, QIAGEN) as described by Rebih et al.[13]. Molecular detection of Blastocystis sp. was applied using the small subunit ribosomal RNA (SSU-rRNA) gene by a pair of diagnostic primers (b11400 FORC and b11710. REVC), as mentioned by Stensvold et al.[14]. Samples were further subjected to typing using seven subtype-specific sequence-tagged-site (STS) primers[15]. The PCR cycling conditions were as described by Darwish et al.[16]. A negative control (4 μl of nuclease-free water) was used for contamination detection in all PCR experiments. PCR reactions were carried out using Eppendorf Master Cycler. The PCR products were electrophoresed in 1.5–2% agarose gel stained with ethidium bromide (Sigma Aldrich, USA) along with a 100 bp DNA ladder (GeneDirex Inc, Taiwan ROC) as a standard size.
2.5 Statistical analysis#
The data were processed using the Statistical Package for Social Sciences (SPSS) version 23. Descriptive analyses were conducted for variables and were presented as frequencies and percentages. Pearson chi-square test and Fisher’s exact tests were used to study the association between IBS and qualitative variables, namely gender and clinical symptoms. In addition, the Mann-Whitney U test was used to assess whether there is a statistically significant difference between the age of IBS and non-IBS patients. A P-value ≤ 0.05 was considered statistically significant.
3 Results#
The study included of 35 untreated IBS and 35 non-IBS patients. The participants’ ages ranged from 3 to 83; the mean age of IBS patients was higher than that of the non-IBS individuals (43.3±18.8) and (31.3±20.9) respectively. Significant difference was found between the two groups (P =0.011). Furthermore, IBS was highly detected among female patients (25/35; 71.4%), whereas the ratio between male and female among non-IBS group was closely similar (15/35, 43%; 20/32, 57% respectively). No significant association was found between gender of both groups (OR: 1.87, 95% CI=0.69–3.06, P=0.212).
When comparing clinical symptoms between IBS and non-IBS patients, our data revealed that patients suffering from IBS had approximately a six-time increase risk of having flatulence symptoms compared with the non-IBS patients, (OR: 5.7, 95% CI=2.008-16.244, P= 0.001). In addition, significant differences were found between the two groups of patients regarding anorexia/weight loss and nausea/vomiting symptoms respectively (OR: 0.337, 95% CI= 0.125-0.907, P= 0.029; OR: 0.367, 95% CI= 0.134-1.003, P=0.050) (Table 1).
Table 1 Evaluation of clinical symptoms between IBS and non-IBS patients
| Symptoms | Non-IBS | IBS | OR (95% Cl) | P-value* | |||
|---|---|---|---|---|---|---|---|
| N | % | n | % | ||||
| Diarrhea | No | 17 | 48.6% | 17 | 48.6% | 1.01 (0.392 - 2.553) | 0.998 |
| Yes | 18 | 51.4% | 18 | 51.4% | |||
| Constipation | No | 31 | 88.6% | 27 | 77.1% | 2.296(0.622 - 8.480) | 0.205 |
| Yes | 4 | 11.4% | 8 | 22.9% | |||
| Constipation/Diarrhea | No | 28 | 80.0% | 27 | 77.1% | 1.185(0.378 - 3.720) | 0.771 |
| Yes | 7 | 20.0% | 8 | 22.9% | |||
| Abdominal pain | No | 13 | 37.1% | 9 | 25.7% | 1.707(0.614 -4.744) | 0.303 |
| Yes | 22 | 62.9% | 26 | 74.3% | |||
| Abdominal spasm | No | 17 | 48.6% | 23 | 65.9% | 0.493(0.188 -1.290) | 0.147 |
| Yes | 18 | 51.4% | 12 | 34.3% | |||
| Flatulence | No | 22 | 62.9% | 8 | 22.9% | 5.712 (2.008- 16.244) | 0.001* |
| Yes | 13 | 37.1% | 27 | 77.1% | |||
| Anorexia/Weight loss | No | 16 | 45.7% | 25 | 71.4% | 0.337 (0.125- 0.907) | 0.029* |
| Yes | 19 | 54.3% | 10 | 28.6% | |||
| Nausea/Vomiting | No | 18 | 51.4% | 26 | 74.3% | 0.367 (0.134 - 1.003) | 0.050* |
| Yes | 17 | 48.6% | 9 | 25.7% | |||
*Chi-Square Test; *P-value ≤ 0.05
The microscopic study results showed the presence of Blastocystis sp. in 71.4% (25/35) of IBS patients’ samples and in 77.1% (27/35) of those of the non-IBS group. No significant difference was found between the two groups (P= 0.299). In addition, co-infection was found in eleven samples of the two groups (3 in IBS and 8 in non-IBS samples). Interestingly, high proportion of single Blastocystis infection (88%; 22/25) was found among IBS patients’ samples compared to those of the non-IBS (Table 2).
Table 2 The frequency of Blastocystis with/without other intestinal parasites
| IBS | Non-IBS | |
|---|---|---|
| Single infection (Blastocystis sp) | 22 (88%) | 19 (70.4%) |
| Protozoa Co-infection | 3 (12%) | 8 (29.6%) |
| Co-infection | ||
| Blastocystis sp + Ent. histolytica complex* | 2 | 3 |
| Blastocystis sp + Ent. coli | 0 | 2 |
| Blastocystis sp + Ent. histo.complex* + Ent.coli | 0 | 2 |
| Blastocystis sp + Ent. histo.complex*+ Giardia | 0 | 1 |
| Blastocystis sp + Ent. coli + Chilomastex | 1 | 0 |
*Entamoeba histolyticacomplex = Ent. histolytica/Ent. dispar/Ent. moshkovskii
Molecular detection and genotyping was pursued for all positive samples (Figure 1: A, B). Three different subtypes were identified (ST1, ST2, and ST3); however, six samples remained undefined (Table 3). Our results detected higher proportion of ST1 subtype among IBS samples compared to the non-IBS (72.7% vs 26.3%). Mixed STs (ST1 and ST2) was found in two samples from IBS patients. ST3 was only detected in non-IBS samples (Table 3).
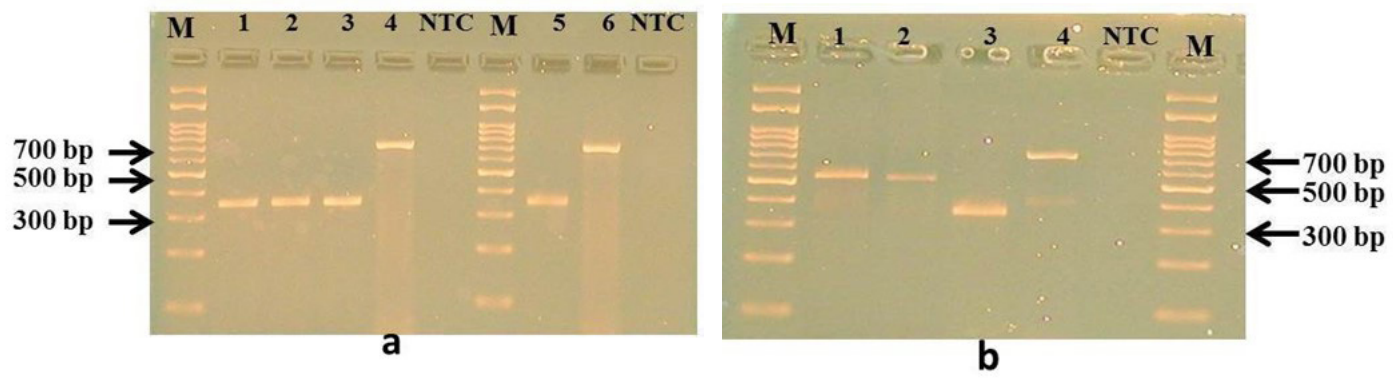
a- M (100 bp DNA ladder marker). Single infection: lanes 1-3: ST1 (351 bp); lane 4: ST2 (704 bp). Mix-infection ST1+ST2: lanes5, 6. NTC: negative control for contamination detection.
b- M (100 bp DNA ladder marker). Lanes 1, 2: ST3 (526 bp); lane 3: ST1 (351 bp); lane 4: ST2 (702 bp). NTC: negative control for contamination detection.
Table 3 The prevalence of Blastocystis subtypes in IBS and Non-IBS patients
| IBS | Different subtypes | ||||
|---|---|---|---|---|---|
| ST1 | ST2 | ST3 | ST1+ST2 | STs? | |
| N=25 (%) | 17 68% | 2 8% | - | 2 8% | 4 16% |
| Non-IBS | |||||
| N=27 (%) | 9 33.3% | 3 11.1% | 12 44.4% | 1 3.7% | 2 7.4% |
STs?: unknown subtypes
Furthermore, the IBS clinical symptoms associated with Blastocystis ST1 subtype (single infection) were analyzed. Although no significant correlation was found, our results showed that flatulence and abdominal pains were the most frequent symptoms detected (81.3%, 68.8%; OR: 2.167 and 1.10 respectively) followed by nausea/vomiting (43.8%; OR: 1.556) (Table 4).
Table 4 The clinical symptoms related to the IBS patients with Blastocystis ST1
| Symptoms | ST1 | OR (95% Cl) | P value* | ||||
|---|---|---|---|---|---|---|---|
| No | Yes | ||||||
| N | % | N | % | ||||
| Diarrhea | No | 4 | 66.7% | 10 | 62.5% | 1.200 (0.166 - 8.659 ) | 0.998 |
| Yes | 2 | 33.3% | 6 | 37.5% | |||
| Constipation | No | 4 | 66.7% | 13 | 81.3% | 0.462 (0.056 - 3.811) | 0.585 |
| Yes | 2 | 33.3% | 3 | 18.8% | |||
| Constipation/ Diarrhea | No | 5 | 83.3% | 11 | 68.8% | 2.273 (0.208 - 24.882) | 0.634 |
| Yes | 1 | 16.7% | 5 | 31.3% | |||
| Abdominal pain | No | 2 | 33.3% | 5 | 31.3% | 1.10 (0.149 - 8.125) | 0.988 |
| Yes | 4 | 66.7% | 11 | 68.8% | |||
| Abdominal Spasm | No | 5 | 83.3% | 12 | 75.0% | 1.667 (0.147 - 18.874) | 0.997 |
| Yes | 1 | 16.7% | 4 | 25.0% | |||
| Flatulence | No | 2 | 33.3% | 3 | 18.8% | 2.167 (0.262 - 17.892) | 0.585 |
| Yes | 4 | 66.7% | 13 | 81.3% | |||
| Anorexia/weight loss | No | 6 | 100.0% | 11 | 68.8% | - | 0.266 |
| Yes | 0 | 0.0% | 5 | 31.3% | |||
| Nausea/Vomiting | No | 2 | 33.3% | 9 | 56.3% | 1.556 (0.218 - 11.086) | 0.998 |
| Yes | 4 | 66.7% | 7 | 43.8% | |||
*Fisher’s exact test
4 Discussion#
Irritable Bowel Syndrome (IBS) is a disorder where the development and the appearance of clinical symptoms can be attributed to multiple factors[10, 17]. Recently, it was found that Blastocystis sp. can promote a mild inflammatory environment within the intestinal mucosa that consequently can be positively associated with IBS clinical symptoms[18]. In Syria, to the best of our knowledge, no study highlighting the relation between IBS and enteric parasites has been conducted. Thus, the present study focused on the presence of Blastocystis as an intestinal parasite among IBS patients.
Our findings revealed that single Blastocystis sp. infection was more prevalent among IBS patients compared to those of the non-IBS patients. This result is consistent with some previous studies from Europe and the Middle East which found that approximately 30-40% of IBS patients were Blastocystis carriers[19-21].
The pathogenicity of Blastocystis is still doubtful due to its existence in both asymptomatic and symptomatic patients[22, 23]. In humans, the pathogenic potential of Blastocystis sp. has focused on subtyping[10, 24]. Still, subtype prevalence seems to vary from country to country and even among communities within the same country[25]. However, subtypes ST1-ST4 and ST7 are common in the Middle East and Europe; they constitute 90% of all human cases[10, 26]. Some studies suggested a potential association between IBS disease and particular Blastocystis subtypes including ST1, ST3, ST4 and ST7[9, 27-29], while other studies have not shown any correlation between the two[18, 23, 30]. Based on our molecular results, the ST1 genotype was predominant among IBS patients, whereas ST3 was only found in the non-IBS individuals. This finding is consistent with previous studies conducted in Pakistan[31, 32].
Furthermore, in this study, the risk of flatulence symptoms was about 6 times higher in IBS than in the non-IBS patients; additionally, flatulence and abdominal pains were the most common symptoms found in IBS patients with Blastocystis ST1. These findings may lead us to suggest that Blastocystis ST1 is likely to associate with these clinical manifestations. Moreover, our result revealed a high infection rate among IBS females than males (2.5:1). This finding is in agreement with previous studies, which reported that females are twice likely to suffer from IBS than males[33-35]. In addition, females are frequently reported as a risk factor for developing post-infected IBS (PI-IBS)[10, 29].
Furthermore, our results indicated that adults and the elderly are highly likely to be at risk of IBS more than the other age groups. This finding is consistent with the results of previous studies[33, 36, 37]. This study is the first in Syria to highlight the high prevalence of Blastocystis sp. among IBS patients. Among the three identified subtypes, ST1 was the predominant. However, the pathogenic potential of this subtype could not be elucidated in the study.
5 Conclusion#
The identification of Blastocystis subtypes may help in understanding their possible role in IBS disease. Further studies are needed to clarify the influence of other pathogens and host factors in IBS patients, since the interaction between them might lead to phenotypic changes and different levels of virulence.
Declarations
⚖Ethics statement
✓Patient consent
€Funding
✎Author contributions
◎Competing interests
▤Data availability
♥Acknowledgements
Article information
- Published
This article is published open access under the CC BY 4.0 licence. CC BY 4.0 · Corrections policy
References 37#
- 1
Stensvold, C.R.; van der Giezen, M. Associations between gut microbiota and common luminal intestinal parasites. Trends Parasitol 2018; 34, 369–377. https://doi.org/ 10.1016/j.pt.2018.02.004.
- 2
Valenca-Barbosa, C.; do Bomfim, T.C.B.; Teixeira, B.R.; Gentile, R.; Neto, S.F.d.C.; Magalhães, B.S.N.; et al. Molecular epidemiology of Blastocystis isolated from animals in the state of Rio de Janeiro, Brazil. PLoS ONE 2019; 14(1): e0210740. https://doi.org/10.1371/journal.pone.0210740.
- 3
Maloney, J.G.; Molokin, A.; Santin, M. Next generation amplicon sequencing improves detection of Blastocystis mixed subtype infections. Infect Genet Evol 2019; 73(March):119–125.
- 4
Pérez, M.R.; Yáñez, C.M.; Hernández, A.M.; Sustaita, J.J.D.; Jiménez, E.G.; Andrade, M.R.; et al. Blastocystis infection frequency and subtype distribution in university students. Heliyon 2020; 6(12):e05729. doi: 10.1016/j.heliyon.2020.e05729. PMID: 33385079; PMCID: PMC7770537.
- 5
Santin, M.; Figueiredo, A.; Molokin, A.; George, N.S.; Köster, P.C.; Dashti, A.; et al. Division of Blastocystis ST10 into three new subtypes: ST42–ST44. J Eukaryot Microbiol 2023; e12998. https://doi.org/10.1111/jeu.12998.
- 6
Mohemmi, N.; Moradi, M.; Khalilian, A.; Maghsood, A.H.; Fallah, M. The relationship between Blastocystis hominis infection and Irritable Bowel Syndrome (IBS) and comparing direct wet mount, stool culture, Formalin-Ether and trichrome staining procedures for identifying organisms. Hormozgan Med J 2021; 19(2):77-84.
- 7
Abedi, S.H.; Fazlzadeh, A.; Mollalo, A.; Sartip, B.; Mahjour, S.; Bahadory, S.; et al. The neglected role of Blastocystis sp. and Giardia lamblia in development of irritable bowel syndrome: A systematic review and meta-analysis. Microbl Pathogenesis 2022; 162:105215
- 8
Longstreth, G.F.; Thompson, W.G.; Chey, W.D.; Houghton, L.A.; Mearin, F.; Spiller, R.C. Functional bowel disorders. Gastroenterology 2006; 130:1480-91.
- 9
Poirier, P.; Wawrzyniak, I.; Vivares, C.P.; Delbac, F.; El Alaoui, H. New insights into Blastocystis spp.: a potential link with irritable bowel syndrome. PLoS Pathog 2012; 8:e1002545.
- 10
Lepczyńska, M.; Dzika, E.; Kubiak, K.; Korycińska, J. The role of Blastocystis sp. as an etiology of irritable bowel syndrome. Pol Ann Med 2016; 23(1):57.
- 11
Manser, M.M.; Saez, A.C.; Chiodini, P.L. Fecal parasitology: concentration methodology needs to be better standardized. PloS negl trop dis 2016; 10(4): e0004579. https://doi.org/10.1371/ journal.pntd.0004579 PMID: 27073836
- 12
Speich, B.; Marti, H.; Ame, S.M.; Ali, S.M.; Bogoch, I.I.; Utzinger, J.; et al. Prevalence of intestinal protozoa infection among school-aged children on Pemba Island, Tanzania, and effect of single-dose albendazole, nitazoxanide and albendazole-nitazoxanide. Parasites & Vectors 2013; 6(1):1–8. https://doi.org/10.1186/1756-3305-6-3 PMID: 23289920.
- 13
Rebih, N.; Boutaiba, S.; Aboualchamat, G.; Souttou, K.; Hakem, A.; Al Nahhas, S. Molecular and epidemiological characterization of Giardia intestinalis assemblages detected in Djelfa, Algeria. J Parasit Dis 2020; 44(2):281. doi: 10.1007/s12639-020-01206-8.
- 14
Stensvold, R.; Brillowska-Dabrowska, A.; Nielsen, H.V.; Arendrup, M.C. Detection of Blastocystis hominis in unpreserved stool specimens by using polymerase chain reaction. J Parasitol 2006; 92(5):1081–7. https://doi.org/10.1645/GE-840R.1 PMID: 17152954.
- 15
Yoshikawa, H.; Wu, Z.; Nagano, I.; Takahashi, Y. Molecular comparative studies among Blastocystis isolates obtained from humans and animals. J Parasitol 2003; 89(3):585–94. https://doi.org/10.1645/00223395(2003)089[0585:MCSABI]2.0.CO;2.
- 16
Darwish, B.; Aboualchamat, G.; Al Nahhas, S. Molecular characterization of Blastocystis subtypes in symptomatic patients from the southern region of Syria. PLoS ONE 2023; 18(3): e0283291. https://doi.org/10.1371/journal. pone.0283291.
- 17
Ohman, L.; Simren, M. Intestinal microbiota and its role in irritable bowel syndrome (IBS). Curr Gastroenterol Rep 2013; 15(5):323.
- 18
Norouzi, M.; Pirestani, M.; Arefian, E.; Dalimi, A.; Sadraei, J.; Mirjalali, H.; et al. Frequency, Associated Factors, Clinical Symptoms, and Subtypes of Blastocystis sp. in Patients with Irritable Bowel Syndrome and Healthy Individuals: A Case-Control Study. Int J Enteric Pathog 2023; 11(1): 8-13. Doi 10.34172/ijep.5562.
- 19
Boorom, K.F.; Smith, H.; Nimri, L.; Viscogliosi, E.; Spanakos, G.; Parkar, U.; et al. Oh my aching gut: irritable bowel syndrome, Blastocystis and asymptomatic infection. Parasit Vectors 2008; 1: 40.
- 20
Ramirez-Miranda, M.E.; Hernandez-Castellanos, R.; Lopez-Escamilla, E.; Moncad D.; Rodriguez-Magallan, A.; Pagasa-Melero, C.; et al. Parasites in Mexican patients with irritable bowel syndrome: a case-control study. Parasit Vectors 2010; 3:96. doi: 10.1186/1756-3305-3-96 PMID: 20942938.
- 21
Das, R.; Khalil, S.; Mirdha, B.R.; Makharia, G.K.; Dattagupta, S.; Chaudhry, R.; Molecular Characterization and Subtyping of Blastocystis Species in Irritable Bowel Syndrome Patients from North India. PLoS ONE 2016; 11(1): e0147055. doi:10.1371/journal.pone.0147055.
- 22
Cifre, S.; Gozalbo, M.; Ortiz, V.; Sorianod, J.M.; Merinoe, J.F.; Trelisa, M. Blastocystis subtypes and their association with Irritable Bowel Syndrome. Med Hypotheses 2018; 116: 4–9.
- 23
Delshad, A.; Saraei, M.; Alizadeh, S.A.; Niaraki, S.R.; Alipour, M.; Hosseinbigi, B.; et al. Distribution and molecular analysis of Blastocystis subtypes from gastrointestinal symptomatic and asymptomatic patients in Iran. Afri Health Sci. 2020; 20 (3): 1179-1189. https://dx.doi.org/10.4314/ahs.v20i3.21.
- 24
Fouad, S.A.; Basyoni, M.M.A.; Fahmy R.A.; Kobaisi, M.H. The pathogenic role of different Blastocystis hominis genotypes isolated from patients with irritable bowel syndrome. Arab J Gastroenterol 2011; 12: 194-200.
- 25
Alfellani, M.A.; Stensvold, C.R.; Vidal-Lapiedra, A.; Onuoha, E.S.; Fagbenro-Beyioku, A.F.; Clark, C.G. Variable geographic distribution of Blastocystis subtypes and its potential implications. Acta Tropica 2013; 1;126(1):11-8.
- 26
Coco, V.F.; Molina, N.B.; Basualdo, J.A.; Cordoba, M.A. Blastocystis spp.: Advances, controversies and future challenges. Rev Argent Microbial 2017; 49 (1):110-118. http://dx.doi.org/10.1016/j.ram.2016.08.004.
- 27
Hussein, E.M.; Hussein, A.M.; Eida, M.M.; Atwa, M.M. Pathophysiological variability of different genotypes of human Blastocystis hominis Egyptian isolates in experimentally infected rats. Parasitol Res 2008; 102(5):853–60.
- 28
El Safadi, D.; Meloni, D.; Poirier, Ph.; Osman, M.; Cian, A.; Gaayeb, L.; et al. Short Report: Molecular Epidemiology of Blastocystis in Lebanon and Correlation between Subtype 1 and Gastrointestinal Symptoms. Am J Trop Med Hyg 2013; 88(6):1203–1206. doi:10.4269/ajtmh.12-0777.
- 29
Kesuma, Y.; Firmansyah, A.; Bardosono, S.; Sari, I.P.; Kurniawan, A. Blastocystis ST-1 is associated with Irritable Bowel Syndrome diarrhea (IBS-D) in Indonesian adolescences. Parasite Epidemiol Control 2019; 6; e00112.
- 30
Krogsgaard, L.R.; Engsbro, A.L.; Stensvold, C.R.; Nielsen, H.V.; Bytzer, P. The prevalence of intestinal parasites is not greater among individuals with irritable bowel syndrome: a population-based case-control study. Clin Gastroenterol Hepatol 2015 ; 13(3):507–13.
- 31
Yakoob, J.; Jafri, W.; Jafri, N.; Khan, R.; Islam, M.; BEG, M.A.; ZAMAN, V. Irritable bowel syndrome: in search of an etiology: role of Blastocystis hominis. Am J Trop Med Hyg 2004; 70 (4), 383-385
- 32
Yakoob. J.; Jafri, W.; Beg, M.A.; Abbas, Z.; Naz, S.; Islan, M.; et al. Irritable bowel syndrome: is it associated with genotypes of Blastocystis hominis. Parasitol Res 2010; 106(5): 1033–8. doi: 10.1007/s00436-010-1761-x PMID: 20177906
- 33
Park, D.W.; Lee, O.Y.; Shim, S.G.; Jun, D.W.; Lee, K.N.; Kim, H.Y.; et al. The Differences in prevalence and sociodemographic characteristics of irritable bowel syndrome according to Rome II and Rome III. J Neurogastroenterol Motil 2010; 16:186-93
- 34
Lovell, R.M.; and Ford, A.C. Effect of gender on prevalence of irritable bowel syndrome in the community: systematic review and meta-analysis. Am J Gastroenterol 2012; 107: 991–1000. Doi:10.1038/ajg.2012.131.
- 35
Azizian, M.; Basati, G.; Abanga,h G.; Mahmoudi, M.R.; Mirzaei, A. Contribution of Blastocystis hominis subtypes and associated inflammatory factors in development of irritable bowel syndrome. Parasitol Res 2016; 115 (5): 2003-2009. doi:10.1007/s00436-016-4942-4
- 36
Hanlon, P.; Nicholl, B.I.; Jani, B.D.; Lee, D.; McQueenie, R.; Mair, F.S. Frailty and pre-frailty in middle-aged and older adults and its association with multi-morbidity and mortality: a prospective analysis of 493737 UK Biobank participants. Lancet Public Health 2018; 3(7):e323–e332
- 37
Wu, S.; Yang, Z.; Liu, S.; Zhang, Q.; Zhang, S.; Zhu, S. Frailty status and risk of irritable bowel syndrome in middle-aged and older adults: A large-scale prospective cohort study. E Clin Med 2022; 56:101807. doi: 10.1016/j.eclinm.2022.101807. PMID: 36593792; PMCID: PMC9803645.
Cited by 3#
- Blastocystis ST1: Protein Profile and Specific Serum Immunoglobulin in Irritable Bowel Syndrome (IBS) PatientsB. Darwish, G. Aboualchamat, S. Al NahhasActa Parasitologica · 2025 · doi.org/10.1007/s11686-024-00946-4
- The Role of Blastocystis spp. in the Etiology of Gastrointestinal and Autoimmune DiseasesO. Pawelec-Pęciak, N. Łanocha-Arendarczyk, K. Grzeszczak et al.Pathogens · 2025 · doi.org/10.3390/pathogens14040313
- Updated report of Blastocystis spp. in a teaching hospital of Brazil: A 6-year retrospective experienceG. de Melo, M. Ferreira, V. Castilho et al.Clinics · 2025 · doi.org/10.1016/j.clinsp.2024.100543
Each citation is confirmed in the citing article's own reference list (Crossref).