Mandibular asymmetries in brazilian adolescents: prevalence and associated factors
Published in The Journal of Clinical Medicine
Ann Arbor ✉
Ann ArborCorresponding author More articles by this author →Belo Horizonte
Belo Horizonte More articles by this author →Minas Gerais
Minas Gerais More articles by this author →
Published
Abstract
ObjectivesEstimate the prevalence of mandibular asymmetries in Brazilian adolescents and investigate the demographic and skeletal factors associated to the asymmetries.
MethodsCone beam computed tomography (CBCT) images from 376 individuals aged from 10 to 19 were analysed to investigate mandibular asymmetry categorized as relative mandibular symmetry, moderate asymmetry, and severe asymmetry. Exposure variables included sex, age, side of mandibular deviation, sagittal and vertical skeletal pattern of the individuals, and cranial base angulation. The chi-square test was used to evaluate the association among asymmetry and the exposure variables. Gross prevalence rations were estimated and adjusted by Poisson regression with robust variance. Significance level was established at 5%.
ResultsPrevalence values were of 78.2% for relative mandibular symmetry, 14.4% for moderate asymmetry, and 7.4% for severe asymmetry. Bivariate analysis revealed that mandibular asymmetry was associated to age, sex, and side of the mandibular deviation (p=0.021, p=0.038 e p=0.000, respectively).
ConclusionsThe prevalence of mandibular asymmetry in Brazilian adolescents was of 21.8%, being more associated to patients of the male sex aged between 17-19 years who present mandibular deviation to the left side.
1 Introduction#
Although an individual may present good facial aesthetics, the front view of the face is not completely symmetric, being absolute bilateral symmetry unusual in nature[1-3].
In general the facial asymmetry is a consequence of a disorganized growing pattern of the cranial structures which may be triggered by genetic factors, congenital malformations, environmental factors, habits and/or traumas, and functional deviations that may compromise maxillary and mandibular growth[2], or due to pathological factors, such as hyperplasia, osteosarcoma, paralysis, and others[4-6].
Facial asymmetry may also happen during the growth, being defined as idiopathic and non-syndromic, and occurring in the general population. This asymmetry is not observed at birth or during the childhood, and it gradually manifests itself over the growth[1,2,7] being capable of negatively influencing the psychosocial characteristics of the individuals and their quality of life[8-10].
When determining facial asymmetry, mandibular deviation is usually the main characteristic influencing the disharmony, being the displacement of the chin in relation to the median sagittal plane of the face the most striking one[4,11-13]. It is also common for the individual to present a subclinical mild degree of facial asymmetry. Such characteristic may be related to skeletal disharmony, hidden by the soft tissue that covers it, and, although there are discrepancies between the right and left sides, it is considered normal[1,2,14].
Asymmetries may also pose a challenge to orthodontic treatments[15-18], mainly in adults. The most of the studies and data presented in the literature are related to this age group and have showed a prevalence from 11% to 37%[13,19,22]. However, when the diagnostic method is more accurate, the asymmetry prevalence may be higher than 50%[2,4,23,24], which indicates that a precise diagnosis is paramount to locate the asymmetry and determine the best strategy for the treatment[15-18].
On the prevalence of asymmetries in adolescents, there are few studies in the literature. In one of the few not so recent study, Ramirez-Yañez et al[2] found that about 25% of the patients evaluated presented craniofacial asymmetry.
Therefore, considering the absence of studies with young individuals from Brazil mainly using cone beam computed tomography (CBCT), the objective of this cross-sectional retrospective study was to estimate the prevalence of mandibular asymmetry among Brazilian adolescents, and its association with demographic and skeletal factors.
2 Materials and Methods#
2.1 Sample#
Institutional ethical committee approval from Lutheran University of Brazil (Canoas - RS) was obtained prior to conducting the study (reference number: 4.310.478).
The sample was comprised by cone beam computed tomography (CBCT) of 376 individuals extracted from the database of a dental diagnosis and planning center (Compass3D®, Belo Horizonte, MG, Brazil). Images were randomly chosen in relation to sex and race of the individuals.
StatCalc from Epi Info version 7 was used to sample calculation. The calculation was based on a cross-sectional study with an expected prevalence of 25% of individuals ranging from moderate to severe asymmetry, confidence interval of 95% and power of 80%. The proportion of exposed and no-exposed ones was of 1:1, and the minimum sample should be comprised by 288 individuals.
The inclusion criteria were: tomographic images should have been asked either with clinical justification, or if it was impossible to answer to the clinical needs using conventional radiographic techniques (guidelines from Sedentexct project) 25, individuals should be between 10 and 19 years old, images should have been generated in tomographic devices of the same brand (i-CAT®, Imaging Sciences International, Hatfield, Pa). Exclusion criteria: individuals who had undergone trauma and/or surgeries on the face, craniofacial syndromes and anomalies.
2.2 Tomography#
The same equipment (i-CAT - Imaging Sciences International, Hatfield, Pa), adjusted for 120KvP, 3-8mA and exposition time of 20 seconds, was used.
Patients were instructed to seat, occlude in maximum habitual intercuspation, and leave lips at rest. The head was positioned keeping the Frankfurt plane parallel to the ground and the median sagittal plane perpendicular to the ground.
2.3 Data collecting#
DICOM files were imported to SimPlant Ortho Pro 2.0® (Materialise Dental, Lueven, Belgium), which provides the exact values of the measurements chosen. Aiming at a higher precision of the measurements, the location of the anatomic points were done by multi-planar reconstruction cuts, measurement scale of 0.01mm and 0.01°.
Table 1 presents the used points and planes of reference, and Table 2 shows the measures evaluated (Fig 1).
Table 1 Description of the anatomical points and reference planes used in this study.
| Point/Plane | Abbreviation | Definition |
|---|---|---|
| Anatomical porion | Po | The highest point of the external auditory meatus |
| Orbital | Or | The lowest point of the infra-orbital margin |
| Basion | Ba | Midpoint on the anterior margin of the occipital foramen |
| Sella | S | Central point of the sella turcica |
| Nasion | N | The most anterior and medium point of the nasofrontal suture |
| Subspinal | A | The deepest anterior point in the concavity of the anterior maxilla |
| Supramandibular | B | Point located in the deepest concavity of the anterior portion of the mandibular symphisis |
| Gnathion | Gn | The lowest point of the anterior margin of the lower jaw |
| Pterygoid | Pt | The highest and posterior point of the superior margin of the pterygomaxillary fissure |
| Gonion | Go | The lowest and most posterior point of the gonia angle outline |
| Frankfurt plane | Frankfurt | The plane passes through the right and left anatomical porion and the left orbital point (PoR, PoL – OrL) |
| Median Sagittal Plane | MSP | It refers to the intersection of Nasion and Basion points, perpendicular to the Frankfurt Plane. Used to evaluate transverse changes |
Table 2 Tomographic measure.
| Measurement | Definition | Variable |
|---|---|---|
| Gn-MSP | Distance between gnathion and the median sagittal plane | Mandibular Asymmetry |
| ANB angle | Angle formed by the intersection of the lines N-A and N-B | Sagittal skeletal pattern |
| N-Ba.PtE-Gn | Angle of the intersection of the lines N-Ba.PtE-Gn | Vertical skeletal pattern |
| S-N.S-Ba | Angle of the intersection of the lines S-N.S-Ba | Angle of the cranial base |
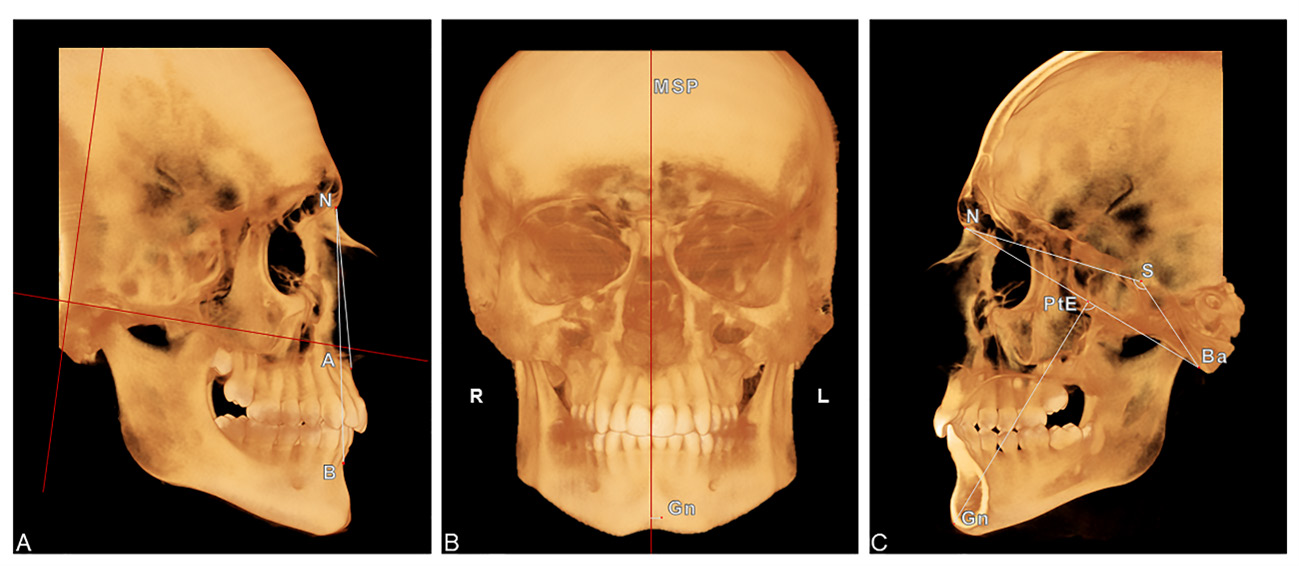
The primary outcome was the presence of mandibular asymmetry among Brazilian adolescents. Such asymmetry was determined by the displacement of the gnathion in relation to the median sagittal plane of the patient, because the chin has been responsible for having the greatest influence on the perception of facial symmetry[4,12,13]. Patients presenting up to 2mm gnathion deviation in relation to the median sagittal plane were considered as having relative symmetry[2,4,26-28]. The ones within more than 2mm up to 4mm gnathion deviation were classified as having moderate asymmetry, and the ones with a gnathion deviation greater than 4mm were classified as having severe asymmetry[4,12,29,30].
The exposure variables and the way they were analysed are described as follow:
Demographic variables: sex (male and female); Age (from 10 to 19), divided into three groups of age (10-13/14-16/17-19).
Skeletal variables: Side of the mandibular deviation (right or left), determined by the distance of the gnathion in relation to the median sagittal plane. Positive values indicate mandibular asymmetry to the left side and negative values to the right side. Sagittal skeletal pattern was determined by ANB angle, being considered Class I (between 0° and 4.5°), II (>4.5°), and III (<0°)[31,32]. Vertical skeletal pattern determined by N-Ba.PtE-Gn angle, it was considered as balanced (between 87° and 93°), vertical (<87°), and horizontal (93°)[33]. Cranial base angulation was determined by N-S-Ba angle, being considered normal (between 127° and 136°), acute (<127°) and obtuse (>136°)[34].
2.4 Error of the method#
Three dental professionals performed the tomographic measurements, being the error determined by the intraclass correlation coefficient (ICC), intraobserver and interobserver. The three professionals evaluated 10% of the tomographic measurements in two different moments, with an interval of two weeks between evaluations. ICC, intraobserver and interobserver, was of > 0.90 for both measurements, showing that the method was highly reliable.
2.5 Statistical Analysis#
SPSS® version 20.0 (IBM, Chicago, IL, USA) was used to the Statistical Analysis. Bivariate analysis, the qui-square (X2 ) test, was used to evaluate the association among asymmetry and the exposure variables, significance level of p<0.05. Crude prevalence rations were estimated and adjusted for the individuals with asymmetry, in the exposure variables, by the Poisson regression (p<0.20).
3 Results#
Table 3 shows the characteristics of the sample, with absolute and relative frequencies of the dependent (outcome) and independent variables.
Table 3 Characteristics of sample individuals (n=376).
| Variables/Category | N (%) |
|---|---|
| Sex | |
| Male | 160 (42.6) |
| Female | 216 (57.4) |
| Age | |
| 10-13 | 190 (50.5) |
| 14-16 | 116 (30.9) |
| 17-19 | 70 (18.6) |
| Mandibular Asymmetry | |
| Relative symmetry | 294 (78.2) |
| Moderate asymmetry | 54 (14.4) |
| Severe asymmetry | 28 (7.4) |
| Side of mandibular deviation | |
| Left | 250 (66.5) |
| Right | 126 (33.5) |
| Sagittal skeletal pattern | |
| Class I | 193 (51.3) |
| Class II | 113 (30.1) |
| Class III | 70 (18.6) |
| Vertical skeletal pattern | |
| Vertical | 99 (26.3) |
| Balanced | 232 (61.7) |
| Horizontal | 45 (12.0) |
| Cranial base angulation | |
| Acute | 2 (0.5) |
| Balanced | 370 (98.4) |
| Obtuse | 4 (1.1) |
The average age of the patients was of 13.7 years, and there was a prevalence of 21.8%, being 14.4% (54/356) of moderate asymmetry, and 7.4% (28/376) of severe asymmetry. The frequency of mandibular deviation to the left side (66.5%) was almost twice higher than to the right side (33.5%), and it was associated both with moderate and severe asymmetry.
Results about the prevalence of sagittal skeletal pattern showed that Class I was 51.3%, while Classes II and III represented 20.1% and 18.6% respectively. Regarding the vertical skeletal pattern, the balanced type (61.7%) was the most observed, followed by the vertical (26.3%) and horizontal (12%).
Data from cranial base angulation showed that the normal pattern (98.4%) was the most frequent, being followed by the obtuse angle (1.1%) and acute angle (0.5%).
Table 4 shows the results of the association tests between mandibular asymmetries and exposure variables. There was a significant association with the demographic variables of sex and age. Moderate asymmetry was associated to male adolescents, and to the older ones (17-19 years old).
Regarding the skeletal exposure variables, only the side of the mandibular deviation showed association with the principal outcome. It was observed that the deviation to the left side was associated with the presence of both moderate and severe asymmetries.
During the statistical analyses, it was observed that there was no need to use Poisson regression, as the only association with a p<0.02 was the variable regarding the side of the deviation, which showed a frequency of 100%, both for moderate and severe mandibular asymmetries.
Table 4 Bivariate analysis of the association between mandibular asymmetries and the exposure variables (n=376).
| Mandibular Asymmetry | ||||||||
|---|---|---|---|---|---|---|---|---|
| Relative Symmetry | Moderate | Severe | p | |||||
| Variable | Answer | n | % | n | % | n | % | |
| Sex | Female Male | 179 115 | 60.9% 39.1% | 22 32 | 40.7% 59.3% | 15 13 | 53.6% 46.4% | 0.021* |
| Age | 10-13 14-16 17-19 | 155 92 47 | 52.7% 31.3% 16.0% | 26 12 16 | 48.1% 22.2% 29.6% | 9 12 7 | 32.1% 42.9% 25.0% | 0.038* |
| Side of mandibular deviation | Left Right | 168 126 | 57.1% 42.9% | 54 - | 100.0% - | 28 - | 100.0% - | 0.000* |
| Sagittal skeletal pattern | Class I Class II Class III | 149 93 52 | 50.7% 31.6% 17.7% | 24 16 14 | 44.4% 29.6% 25.9% | 20 4 4 | 71.4% 14.3% 14.3% | 0.122NS |
| Vertical skeletal pattern | Vertical Balanced Horizon-tal | 77 183 34 | 26.2% 62.2% 11.6% | 14 34 6 | 25.9% 63.0% 11.1% | 8 15 5 | 28.6% 53.6% 17.9% | 0.872NS |
| Cranial base angulation | Acute Balanced Obtuse | 1 291 2 | 0.3% 99.0% 0.7% | 1 53 - | 1.9% 98.1% - | - 26 2 | - 92.9% 7.1% | 0.094NS |
Chi-Square test (X2 ).
NS: not-significant; *significant p≤0.05; **significant p≤0.01
4 Discussion#
One of the causes of mandibular asymmetry is the disorderly growth of facial structures. Departing from the diagnosis, professionals define the clinical approach considering both the age of the patient and the degree of asymmetry, which shows how relevant it is an early diagnosis. Therefore, this study evaluated a representative sample of CBCT from adolescents, three age groups, which allowed the estimate of the prevalence of different degrees of mandibular asymmetry and its association with demographic and skeletal factors. The prevalence was of 21.8% of mandibular asymmetry, being 14.4% moderate and 7.4% severe. The mandibular asymmetry was associated with age, sex, and side of the mandibular deviation.
Although some authors agree that to be considered an asymmetry the skeletal deviation should be of at least 4mm[4], others suggest that the asymmetry depends on the thickness of the soft tissue in the area, agreeing that in some cases present the asymmetry is present when the skeletal deviation is greater than 2mm[2]. As there has been no agreement on how to define asymmetry, in this study asymmetry was divided into categories[35], measuring the distance between the gnathion and the median sagittal plane, being individuals classified as presenting relative symmetry and moderate or severe mandibular asymmetry.
The prevalence of mandibular asymmetry was of 21.8% but the scarce number of studies in the literature regarding this age group makes the discussion more difficult. Among the few studies found, Ramirez-Yañez et al[2] found a prevalence of 25%, a bit superior to the one found in this study, and such difference may be related to the methodology used to evaluate the asymmetry.
Regarding the variable age, the literature is controversial. Although some studies show a significant association between mandibular asymmetry and age, as found in this study[2,36-38], others say otherwise[39-42]. A possibility to explain why only the patients between 17-19 years old presented a significant correlation with mandibular asymmetry would be that these individuals experience alternating periods of growth, suggesting that asymmetry might be an adaptive response to the functional needs of the jaw and the temporomandibular joint. However, this sample did not present an association with sagittal or vertical skeletal patterns of the patients.
Mandibular asymmetry was also associated to sex in this study, and male adolescents to moderate asymmetry. Liukkonen et al[38] and Melnik[43] have also found such correlation, but most studies do not identified such significant association[2,4,22,23,41,42,44,45].
There was a statistically significant association between the left side and moderate and severe asymmetries. Such findings are also controversial, as some studies reported the same results[2,13,23,44,46], while others said the correlation was higher with the right side of the face[1,23,36,37,47].
However, there has been two possible explanations to justify the high frequency of gnathion deviation to the left side. One of them says it may be explained by the dominant growing of the right side when the dimensions of the skull and brain are evaluated[4,48].
The other possibility would be the development of an asymmetric muscle habit, unilateral chewing, which transmits the masticatory force of the teeth to the bones of the face[49]. Kim et al[27] observed a higher volume of the cranial base on the contralateral side of the mandibular deviation in adults, while Kwon et al[50] did not find morphological differences. In this study, there was no association between this variable and mandibular asymmetry.
The discussion above, the low number of studies and the limitations imposed by a cross-sectional study show the relevance of future studies regarding mandibular asymmetry in adolescents, focusing on mandibular functional changes to understand the postural component and their impact on the facial growth as a whole.
5 Conclusion#
The prevalence of mandibular asymmetry in adolescents was of 21.8%, being 14.4% classified as moderate and 7.4% as severe.
Mandibular asymmetry was associated to sex and the side of the mandibular deviation, being more prevalent in male adolescents between 17 and 19 years old who presented the deviation to the left side of the face.
Declarations
◎Competing interests
♥Acknowledgements
Article information
- Published
This article is published open access under the CC BY 4.0 licence. CC BY 4.0 · Corrections policy
References 50#
- 1
Peck, S.; Peck, L.; Kataja, M. Skeletal asymmetry in esthetically pleasing faces. Angle Orthod. 1991, 61, 43-48. https://doi.org/10.1043/0003-3219(1991)061<0043:SAI EPF>2.0.CO;2.
- 2
Ramirez-Yañez, G.O.; Stewart, A.; Franken, E.; Campos, K. Prevalence of mandibular asymmetries in growing patients. Eur J Orthod. 2011, 33, 236-242. https://doi.org/10.1093/ejo/cjq057.
- 3
Van Elslande, D.C.; Russett, S.J.; Major, P.W.; Flores-Mir, C. Mandibular asymmetry diagnosis with panoramic imaging. Am J Orthod Dentofacial Orthop. 2008, 134, 183-192. https://doi.org/10.1016/j.ajodo.2007.07.021.
- 4
Haraguchi, S.; Takada, K.; Yasuda, Y. Facial asymmetry in subjects with skeletal Class III deformity. Angle Orthod. 2002, 72, 28-35. https://doi.org/10.1043/0003-3219(2002)072<0028:FAISWS>2.0.CO;2
- 5
Ortakoglu, K.; Akcam, T.; Sencimen, M.; Karakoc, O.; Ozyigit, H.A.; Bengi, O. Osteochondroma of the mandible causing severe facial asymmetry: a case report. Oral surgery, oral medicine, oral pathology, oral radiology, and endodontics. 2007, 103, 21-28. https://doi.org/10.1016/j.tripleo.2006.11.035.
- 6
González-Otero, S.; Navarro-Cuéllar, C.; Escrig-de Teigeiro, M.; Fernández-Alba-Luengo, J.; Navarro-Vila, C. Osteochondroma of the mandibular condyle: Resection and reconstruction using vertical sliding osteotomy of the mandibular ramus. Medicina oral, patologia oral y cirugia bucal. 2009, 14, 194-197.
- 7
Cheong, Y.W.; Lo, L.J. Facial asymmetry: etiology, evaluation, and management. Chang Gung medical journal. 2011, 34, 341-351.
- 8
Rhodes, G. The evolutionary psychology of facial beauty. Annual review of psychology. 2006, 57, 199-226. https://doi.org/10.1146/annurev.psych.57.102904.190208.
- 9
Ryan, F.S.; Barnard, M. Cunningham SJ. Impact of dentofacial deformity and motivation for treatment: a qualitative study. Am J Orthod Dentofacial Orthop. 2012, 141, 734-742. https://doi.org/10.1016/j.ajodo.2011.12.026.
- 10
Soh, C.L.; Narayanan, V. Quality of life assessment in patients with dentofacial deformity undergoing orthognathic surgery--a systematic review. Int J Oral Maxillofac Surg. 2013, 42, 974-980. https://doi.org/10.1016/j.ijom.2013.03.023.
- 11
Lee, M.S.; Chung, D.H.; Lee, J.W.; Cha, K.S. Assessing soft-tissue characteristics of facial asymmetry with photographs. Am J Orthod Dentofacial Orthop. 2010, 138, 23-31. https://doi.org/10.1016/j.ajodo.2008.08.029.
- 12
Masuoka, N.; Muramatsu, A.; Ariji, Y.; Nawa, H.; Goto, S.; Ariji, E. Discriminative thresholds of cephalometric indexes in the subjective evaluation of facial asymmetry. Am J Orthod Dentofacial Orthop. 2007, 131, 609-613. https://doi.org/10.1016/j.ajodo.2005.07.020.
- 13
Severt, T.R.; Proffit, W.R. The prevalence of facial asymmetry in the dentofacial deformities population at the University of North Carolina. The International journal of adult orthodontics and orthognathic surgery. 1997, 12, 171-176. https://doi.org/10.1016/S0889-5406(98)70097-6.
- 14
Masuoka, N.; Momoi, Y.; Ariji, Y.; Nawa, H.; Muramatsu, A.; Goto, S.; et al. Can cephalometric indices and subjective evaluation be consistent for facial asymmetry? Angle Orthod. 2005, 75, 651-655. https://doi.org/10.1043/0003-3219(2005)75[651:CCIASE]2.0.CO;2.
- 15
Bishara, S.E.; Burkey, P.S.; Kharouf, J.G. Dental and facial asymmetries: a review. Angle Orthod. 1994, 64, 89-98. https://doi.org/10.1043/0003-3219(1994)064<0089:DAF AAR>2.0.CO;2.
- 16
O’Grady, K.F.; Antonyshyn, O.M. Facial asymmetry: three-dimensional analysis using laser surface scanning. Plastic and reconstructive surgery. 1999, 104, 928-937. https://doi.org/10.1093/ejo/cjr091.
- 17
Pirttiniemi, P. Normal and increased functional asymmetries in the craniofacial area. Acta Odontol Scand. 1998, 56, 342-345. https://doi.org/10.1080/000163598428284.
- 18
Proffit, W.R.; White, R.P.; Sarver, D.M. Contemporary treatment of dentofacial deformity. 4rd ed.; Mosby: Maryland Heights, Missouri, USA, 2003; pp. 541-680.
- 19
Bailey, L.J.; Haltiwanger, L.H.; Blakey, G.H.; Proffit, W.R. Who seeks surgical-orthodontic treatment: a current review. The International journal of adult orthodontics and orthognathic surgery. 2001, 16, 280-292. https://doi.org/10.1067/mod.2002.125960.
- 20
Chew, M.T. Spectrum and management of dentofacial deformities in a multiethnic Asian population. Angle Orthod. 2006, 76, 806-809. https://doi.org/10.1043/0003-3219(2006)076[0806:SAMODD]2.0.CO;2.
- 21
Piao, Y.; Kim, S.J.; Yu, H.S.; Cha, J.Y.; Baik, H.S. Five-year investigation of a large orthodontic patient population at a dental hospital in South Korea. Korean journal of orthodontics. 2016, 46, 137-145. https://doi.org/10.4041/kjod.2016.46.3.137.
- 22
Sheats, R.D.; McGorray, S.P.; Musmar, Q.; Wheeler, T.T.; King GJ. Prevalence of orthodontic asymmetries. Semin Orthod. 1998, 4, 138-145. https://doi.org/10.1016/S1073-8746(98)80015-7.
- 23
Haraguchi, S.; Iguchi, Y.; Takada, K. Asymmetry of the face in orthodontic patients. Angle Orthod. 2008, 78, 421-426. https://doi.org/10.2319/022107-85.1.
- 24
Thiesen, G.; Gribel, B.F.; Kim, K.B.; Pereira, K.C.R.; Freitas, M.P.M. Prevalence and Associated Factors of Mandibular Asymmetry in an Adult Population. The Journal of craniofacial surgery. 2017, 28, e199-e203. https://doi.org/10.1097/SCS.0000000000003371.
- 25
Basic Principles for Use of Dental Cone Beam CT. Avaible ontline: http://www.sedentexct.eu/content/basic-principles-use-dental-cone-beam-ct.: Accessed on 13 August 2014.
- 26
Kim, E.J.; Palomo, J.M.; Kim, S.S.; Lim, H.J.; Lee, K.M.; Hwang, H.S. Maxillofacial characteristics affecting chin deviation between mandibular retrusion and prognathism patients. Angle Orthod. 2011, 81, 988-993. https://doi.org/10.2319/112210-681.1.
- 27
Kim, S.; Lee, K.; Lee, S.; Baik, H. Morphologic relationship between the cranial base and the mandible in patients with facial asymmetry and mandibular prognathism. Am J Orthod Dentofacial Orthop. 2013, 144, 330-340. https://doi.org/10.1016/j.ajodo.2013.03.024.
- 28
Kusayama, M.; Motohashi, N.; Kuroda, T. Relationship between transverse dental anomalies and skeletal asymmetry. Am J Orthod Dentofacial Orthop. 2003, 123, 329-337. https://doi.org/10.1067/mod.2003.41.
- 29
Baek, S.H.; Cho, I.S.; Chang, Y.I.; Kim, M.J. Skeletodental factors affecting chin point deviation in female patients with class III malocclusion and facial asymmetry: a three-dimensional analysis using computed tomography. Oral surgery, oral medicine, oral pathology, oral radiology, and endodontics. 2007, 104, 628-639. https://doi.org/10.1016/j.tripleo.2007.03.002.
- 30
Lee, J.K.; Jung, P.K.; Moon, C.H. Three-dimensional cone beam computed tomographic image reorientation using soft tissues as reference for facial asymmetry diagnosis. Angle Orthod. 2014, 84, 38-47. https://doi.org/10.2319/112112-890.1.
- 31
Tweed, C.H. The Frankfort-Mandibular Incisor Angle (FMIA) In Orthodontic Diagnosis, Treatment Planning and Prognosis. The Angle Orthodontist. 1954, 24, 121-169. https://doi.org/10.1043/0003-3219(1954)024<0121:TFIA FI>2.0.CO;2.
- 32
Tweed, C.H. Was the development of the diagnostic facial triangle as an accurate analysis based on fact or fancy? Am J Orthod. 1962, 48, 823-840. https://doi.org/10.1016/0002-9416(62)90002-7.
- 33
Ricketts, R. A foundation for cephalometric communication. American Journal of Orthodontics. 1960, 46, 330-357. https://doi.org/10.1016/0002-9416(60)90047-6.
- 34
Björk, A. Cranial base development: A follow-up x-ray study of the individual variation in growth occurring between the ages of 12 and 20 years and its relation to brain case and face development. American Journal of Orthodontics. 1955, 41, 198-225. https://doi.org/10.1016/0002-9416(55)90005-1.
- 35
Damstra, J.; Fourie, Z.;De Wit, M.; Ren, Y. A three-dimensional comparison of a morphometric and conventional cephalometric midsagittal planes for craniofacial asymmetry. Clinical oral investigations. 2012, 16, 285-294. https://doi.org/10.1007/s00784-011-0512-4.
- 36
de Moraes, M.E.; Hollender, L.G.; Chen, C.S.; Moraes, L.C.; Balducci, I. Evaluating craniofacial asymmetry with digital cephalometric images and cone-beam computed tomography. Am J Orthod Dentofacial Orthop. 2011, 139, e523-531. https://doi.org/10.1016/j.ajodo.2010.10.020.
- 37
Kula, K.; Esmailnejad, A.; Hass, A. Dental arch asymmetry in children with large overjets. Angle Orthod. 1998, 68, 45-52. https://doi.org/10.1043/0003-3219(1998)068<0045:DAAICW>2.3.CO;2.
- 38
Liukkonen, M.; Sillanmäki, L.; Peltomäki, T. Mandibular asymmetry in healthy children. Acta Odontol Scand. 2005, 63, 168-172. https://doi.org/10.1080/00016350510019928.
- 39
Azevedo, A.R.; Janson, G.; Henriques, J.F.; Freitas, M.R. Evaluation of asymmetries between subjects with Class II subdivision and apparent facial asymmetry and those with normal occlusion. Am J Orthod Dentofacial Orthop. 2006, 129, 376-383. https://doi.org/10.1016/j.ajodo.2005.12.002.
- 40
Ferrario, V.F.; Sforza, C.; Ciusa, V.; Dellavia, C.; Tartaglia, G.M. The effect of sex and age on facial asymmetry in healthy subjects: a cross-sectional study from adolescence to mid-adulthood. Journal of oral and maxillofacial surgery : official journal of the American Association of Oral and Maxillofacial Surgeons. 2001, 59, 382-388. https://doi.org/10.1053/joms.2001.21872.
- 41
Cho, M.J.; Hallac, R.R.; Ramesh, J.; Seaward, J.R.; Hermann, N.V.; Darvann, T.A.; et al. Quantifying Normal Craniofacial Form and Baseline Craniofacial Asymmetry in the Pediatric Population. Plastic and reconstructive surgery. 2018, 141380-7. https://doi.org/10.1097/PRS.0000000000004114.
- 42
Hsu, C.K.; Hallac, R.R.; Denadai, R.; Wang, S.W.; Kane, A.A.; Lo, L.J.; et al. Quantifying normal head form and craniofacial asymmetry of elementary school students in Taiwan. Journal of plastic, reconstructive & aesthetic surgery : JPRAS. 2019, 72, 2033-2040. https://doi.org/10.1016/j.bjps.2019.09.005.
- 43
Melnik, A.K. A cephalometric study of mandibular asymmetry in a longitudinally followed sample of growing children. Am J Orthod Dentofacial Orthop. 1992, 101, 355-366. https://doi.org/10.1016/S0889-5406(05)80329-4.
- 44
Thiesen, G.; Gribel, B.F.; Freitas, M.P.M.; Oliver, D.R.; Kim, K.B. Mandibular asymmetries and associated factors in orthodontic and orthognathic surgery patients. Angle Orthod. 2018, 88, 545-551. https://doi.org/10.2319/111517-785.1.
- 45
Djordjevic, J.; Pirttiniemi, P.; Harila, V.; Heikkinen, T.; Toma, A.M.; Zhurov, A.I.; et al. Three-dimensional longitudinal assessment of facial symmetry in adolescents. Eur J Orthod. 2013, 35, 143-151. https://doi.org/10.1093/ejo/cjr006.
- 46
Ercan, I.; Ozdemir, S.T.; Etoz, A.; Sigirli, D.; Tubbs, R.S.; Loukas, M.; et al. Facial asymmetry in young healthy subjects evaluated by statistical shape analysis. Journal of anatomy. 2008, 213, 663-669. https://doi.org/10.1111/j.1469-7580.2008.01002.x.
- 47
Skvarilová, B. Facial asymmetry: type, extent and range of normal values. Acta chirurgiae plasticae. 1993, 35, 173-180.
- 48
Cohen, M.M., Jr. Asymmetry: molecular, biologic, embryopathic, and clinical perspectives. American journal of medical genetics. 2001, 101, 292-314. https://doi.org/10.1002/ajmg.1217.
- 49
Woo, T.L. On the asymmetry of the human skull. Biometrika. 1931, 22, 324-352. https://doi.org/10.1093/biomet/22.3-4.324.
- 50
Kwon, T.G.; Park, H.S.; Ryoo, H.M.; Lee, S.H. A comparison of craniofacial morphology in patients with and without facial asymmetry--a three-dimensional analysis with computed tomography. Int J Oral Maxillofac Surg. 2006, 35, 43-48. https://doi.org/10.1016/j.ijom.2005.04.006
Cited by 1#
- The mandibular lingula (spine of Spix) in contemporary research: A comprehensive critical review of global morphological variations and clinical implicationsM. Rusu, A. Stănescu, A. Stancu et al.Annals of Anatomy - Anatomischer Anzeiger · 2026 · doi.org/10.1016/j.aanat.2026.152844
Each citation is confirmed in the citing article's own reference list (Crossref).