Goldenhar syndrome: a case report
Andrade Sobrinho
Andrade Sobrinho More articles by this author →Larissa Batista Pegorin
Larissa Batista Pegorin More articles by this author →Giovanna Soares Nutels
Giovanna Soares Nutels More articles by this author →Catherine Pancini Rezende
Catherine Pancini Rezende More articles by this author →Marina Marques Denobi ✉
Marina Marques DenobiCorresponding author More articles by this author →
Published
Abstract
Goldenhar syndrome was first described by Maurice Goldenhar in 1952 as an oculoauricular dysplasia. Later, in 1963, Gorlin et al included some vertebral anomalies to the syndrome. Oculo-auriculo vertebral spectrum (OAVS) is a rare and congenital disorder that results from the abnormal development of the first and second branchial arches, but the etiology is unknown, comprising multifactorial mechanisms. The objective of the present study is to facilitate its recognition and assist in the management of future cases. This is a case report of a 9-year-old child who was referred to the PUC Campinas Hospital due to a corneoscleral lesion in the right eye. Ophthalmological and general clinical evaluation showed signs of Oculoauriculovertebral dysplasia or Goldenhar syndrome. After complementary exams, limbal dermoid excision surgery with lamellar keratoplasty was performed. In this case, after the resection of the limbal dermoid, the patient showed an improvement in visual acuity, although partial. Therefore, we emphasize the importance of early diagnosis to prevent amblyopia.
1 Introduction#
Maurice Goldenhar, a Swiss ophthalmologist, first described oculoauricular dysplasia in 1952. Later, in 1963, Gorlin et al. included vertebral anomalies as signs of the syndrome.1,2 Goldenhar syndrome is characterized by impaired development of the eyes, ears, lip, tongue, palate, mandible, maxilla, and dental structures. Abnormalities can also be found in some internal organs (such as the heart and kidneys), the central nervous system, and the skeleton. It is also classified as 1st and 2nd branchial arch syndrome because of its origin.2
Choristoma is a tissue derived from germ layers foreign to that body site; thus, it is a displaced embryonic tissue that was destined to become skin3 . Limbal dermoids are classified as choristomas.
This benign tumor usually containing hair, adipose tissue, and squamous epithelium and it can be isolated or associated with systemic diseases such as Goldenhar syndrome, a rare congenital condition characterized by oculoauriculovertebral anomalies4 . Although some lesions do not affect vision, others can induce astigmatism or obstruct the visual axis, leading to amblyopia in children5 . The aim of this study was to present a rare case of a patient with Goldenhar syndrome and to highlight the importance of its recognition and early approach to prevent permanent ophthalmologic sequelae.
2 Case Report#
Patient female, 9 years old, was referred to the PUC Campinas Hospital because of a limbal lesion in the right eye. According to the mother, the nodule was present since birth and had grown since then. They denied personal, family, obstetric and gynecological antecedents, and reported that the child had lost ophthalmological follow-up after her first year of life.
On ophthalmological examination, the VA without correction was counting fingers 2 meters in the right eye (OD) and 20/25 in the left eye (OS).
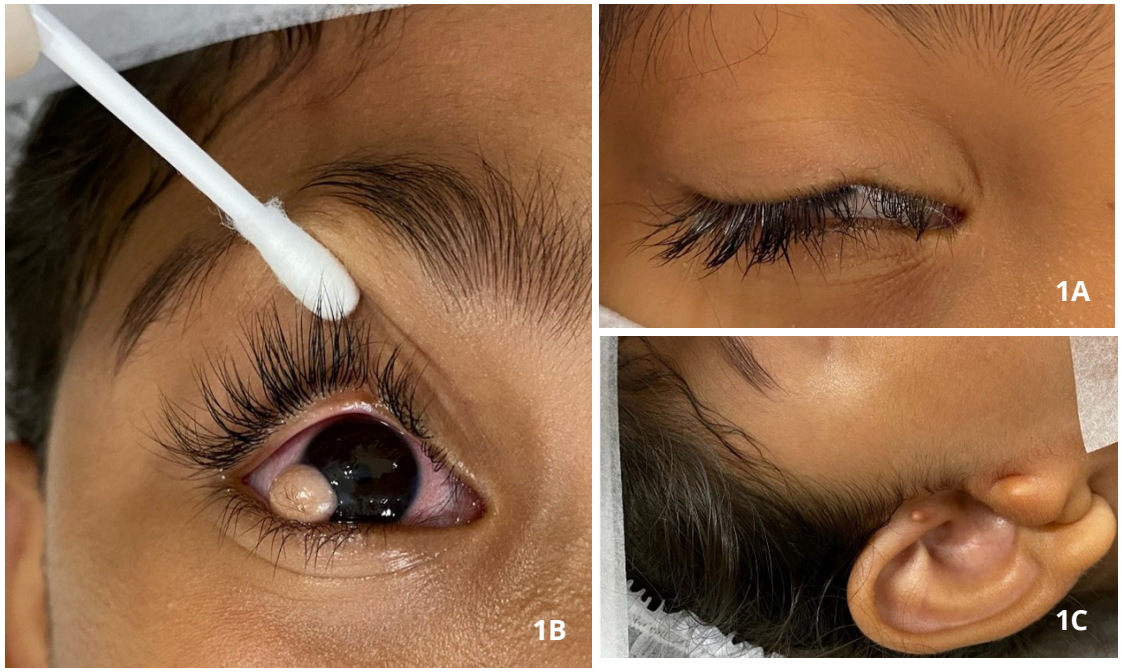
The ectoscopy showed coloboma of the upper eyelid (Figure 1A), an inferotemporal corneoscleral solid nodule in OD (Figure 1B), with hair follicles, and paracentral corneal opacity, OS without abnormalities. The intraocular pressure and ophthalmoscopic examination were normal. On general examination there were systemic alterations such as facial malformations and accessory auricular appendages ipsilateral to the corneal lesion (Figure 1C). The diagnostic hypothesis of a limbal dermoid associated with the oculo-auriculo-vertebral spectrum (OAVS) known as Goldenhar syndrome was raised, and clinical and complementary examinations were requested for investigation.
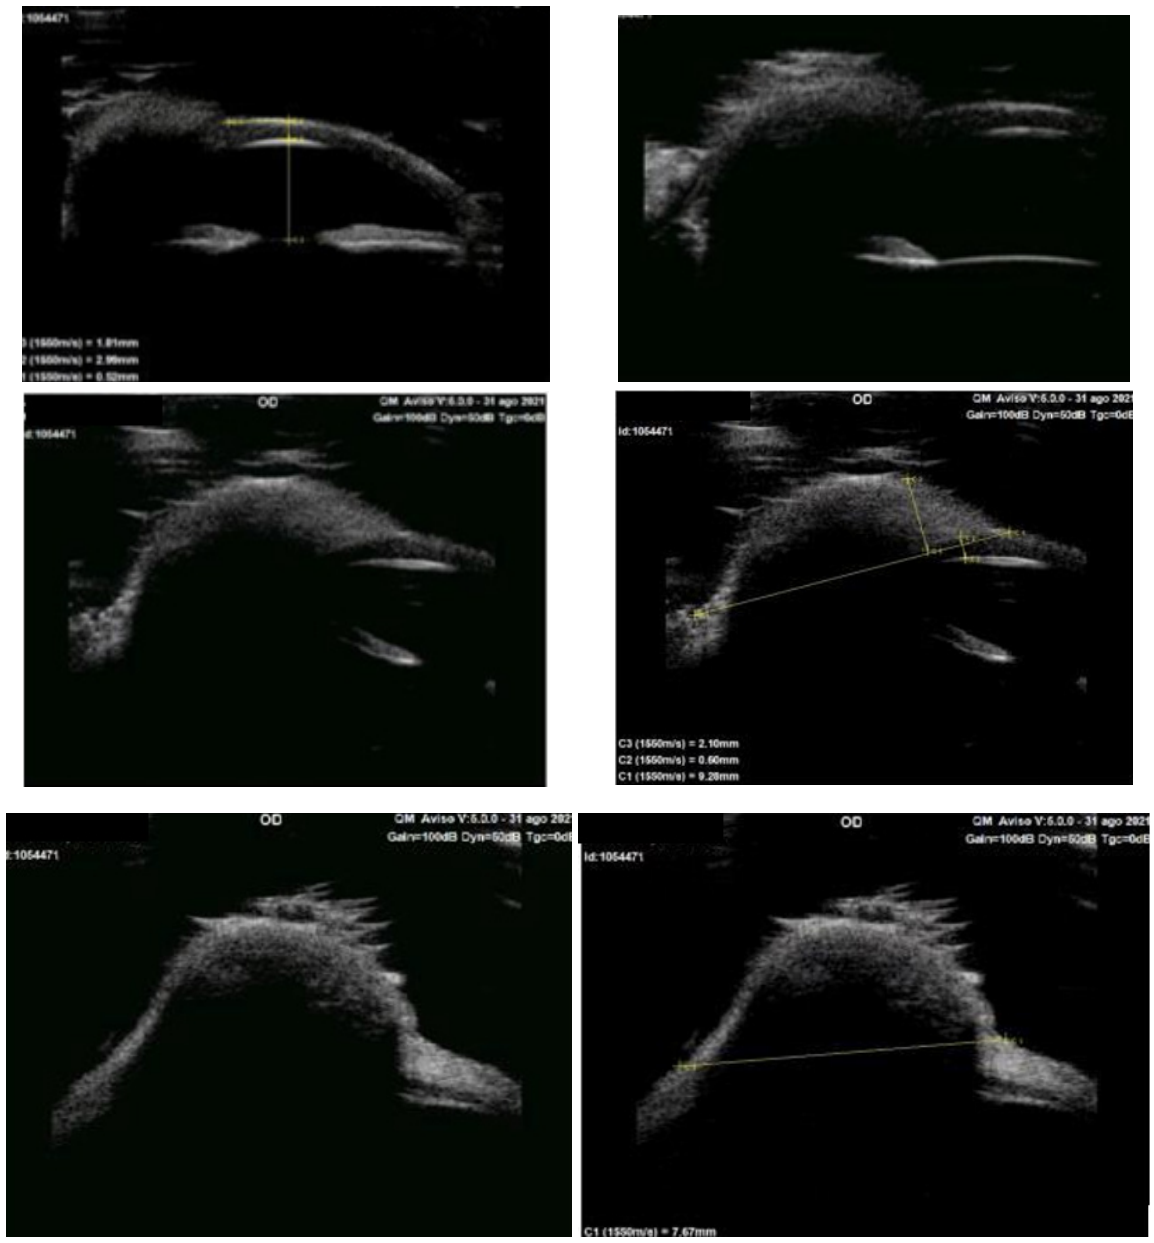
Right eye ultrasound biomicroscopy (UBM) (Figure 2) was performed to delineate the extent of the dermoid, which revealed an elevated lesion from 7 o'clock to 9 o'clock in the bulbar conjunctiva, with a cupuliform topography, a radial extension of 9.28 mm, and a dense, heterogeneous internal area that caused a posterior acoustic shadow artifact. Following this, ophthalmologic surgery was scheduled for lesion excision. As the posterior limit of the lesion could not be identified by the examination, a corneal graft was requested for the surgery
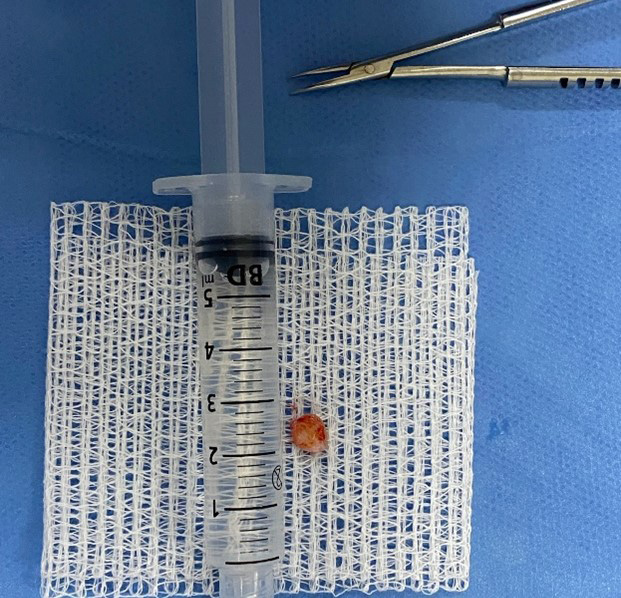
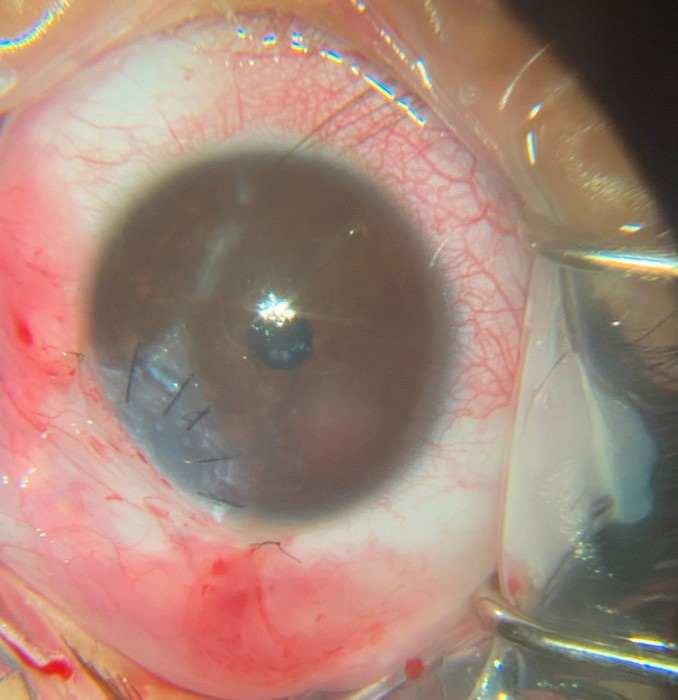
The limbal dermoid was excised. The lesion was approximately 1 cm (figure 3) and an area of corneoscleral thinning remained, so the surgeon chose to perform a lamellar transplant. The graft was prepared with an artificial chamber, diamond scalpel, iris spatula, and 7.0 mm punch. The lamellar graft was fixed with 10-0 nylon to the receptor area with subsequent conjunctival coverage of the sclera. The surgery was successfully performed (Figure 4).
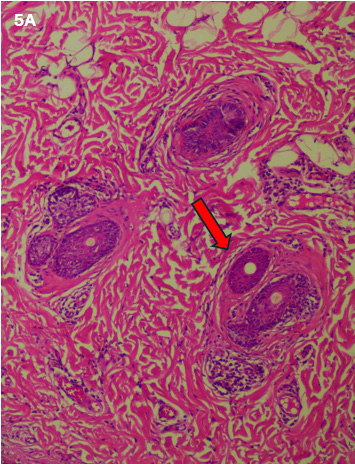
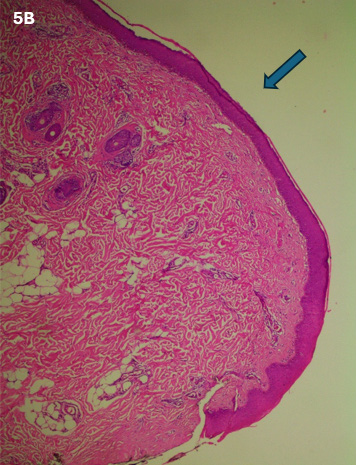
After excision, the lesion was sent for anatomopathology. The histological examination (Figure 5A and 5B) was compatible with a choristoma that showed stratified squamous epithelium, stroma consisting of intertwined and thickened collagen fibers with epidermal appendages - hair follicles, sebaceous, and sweat glands. The diagnosis of solid epipulbar dermoid associated with Goldenhar syndrome was then made.
The patient was evaluated on the first, seventh and thirtieth postoperative days. There was good evolution of the operative wound, and the sutures were removed without complications.
After the surgery, the visual acuity without correction was 20/400 in the right eye and 20/20P in the left eye. The refraction was: +2.00 -2.00 X 180º (VA 20/400) in the right eye and +1.00 -1.00 X 90º (VA 20/20) in the left eye. A contact lens fitting test was performed on the right eye with a spherical lens from Solotica (BC: 44D), resulting in a visual acuity of 20/200. The patient likely has amblyopia of refractive origin (astigmatism caused by the lesion). Glasses with polycarbonate lenses were prescribed. The patient is undergoing multidisciplinary follow-up, aiming at functional, aesthetic, and psychosocial rehabilitation, with reintegration into society.
3 Discussion#
OAVS is a rare and congenital disorder with an estimated prevalence of 1:3,500 - 1:5,600 births. The disease is a type of craniofacial microsomia (CFM) diagnosed based on clinical criteria and must be distinguished from other entities included in the CFM group, such as CHARGE Syndrome, Parry Romberg Syndrome, or Treacher Collins Syndrome5,6 . The origin of OAVS results from the abnormal development of the first and second branchial arches, but the etiology is unknown, comprising multifactorial mechanisms, including epigenetic and environmental factors7,8 .
Familial cases have been reported over multiple generations, frequently involving a history of consanguineous marriages, suggesting a potential inherited pattern. However, this hereditary link is not consistently observed across all cases.8 Sharma et al. propose that maternal exposure to substances like thalidomide, retinoic acid, tamoxifen, and cocaine may be associated with the development of the disease. Furthermore, maternal diabetes has been suggested as another potential etiological factor.9
Goldenhar syndrome is primarily characterized by sporadic genetic inheritance, with only a few documented cases of autosomal dominant and recessive patterns. The etiopathogenesis may involve multifactorial inheritance, various genetic interactions (such as 5q deletion, trisomy 18, and 7q duplication), and possibly environmental influences. This multifactorial nature results in a variable systemic phenotypic presentation, though the ophthalmic features tend to remain consistent.1,8
The spectrum of phenotypic features in Goldenhar syndrome is widely variable, involving eye defects, ear anomalies, mandibular hypoplasia, and vertebral malformations8,9,10 . In relation to ocular and adnexal anomalies, epibulbar dermoids, lipodermoids, eyelid coloboma, microphthalmia, anophthalmia, and lacrimal caruncle malformation have been described11 . In addition, retinal and optic nerve findings such as tilted optic disc, optic nerve hypoplasia, tortuous retinal vessels, and macular hypoplasia have also been reported12 .
Epibulbar dermoids can be located either on the cornea, limbus, and conjunctiva13 . Limbal dermoids are the most common choristomas, often located inferotemporally. This lesion usually compromises visual function and causes ocular deformity, astigmatism, invasion of the visual axis, blindness, inhibition of eye movement, and infiltration of fatty components into the cornea4,14 .
Limbal dermoid may present as an isolated malformation or in combination with other congenital anomalies such as craniofacial microsomia or OAVS, as reported in our case. Thus, in view of the diagnosis of this ocular lesion, other systemic anomalies should be investigated. This explains the importance of multidisciplinary follow-up15 .
The treatment of epibulbar dermoid is individualized and consists of surgical removal of the tumor due to functional and aesthetic impairment. The surgical technique performed depends on the size and location of the lesion. The techniques reported are simple excision, lamellar keratoplasty, penetrating keratoplasty, autologous mucosal graft, oral mucosal graft reconstruction, keratolimbic allograft, and cultured mucosal epithelial cell transplantation16 .
4 Conclusion#
Our case report presents a rare case of limbal dermoid associated with OAVS in a young pediatric patient. The treatment of choice was excision plus lamellar keratoplasty. At follow-up, there was an improvement in visual acuity, although visual development was already impaired. The diagnosis of the disease was suspected based on the classic clinical features and reveals the importance of early ophthalmologic management to ensure the development of visual function and prevent amblyopia.
1A
1C
1B
Article information
- Published
Copyright © 2024 Marina Marques Denobi. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 16#
- 1
Singh, M., Kaur, M., Grewal, A.M. et al. Ophthalmic features and management outcomes of 30 children having Goldenhar syndrome. Int Ophthalmol 40, 667–675 (2020). https://doi.org/10.1007/s10792-019-01227-0
- 2
Gorlin, R. J., Jue, K. L., Jacobsen, U., & Goldschmidt, E. (1963). Oculoauriculovertebral dysplasia. The Journal of Pediatrics, 63(5), 991–999. doi:10.1016/s0022-3476(63)80233-4
- 3
American Academy of Ophthalmology. External Disease and Cornea, Chapter 8. Basic and Clinical Science Course, Section 04. 2020-2021
- 4
Zhong J, Deng Y, Zhang P, Li S, Huang H, Wang B, Zhang H, Peng L, Yang R, Xu J, Yuan J. New Grading System for Limbal Dermoid: A Retrospective Analysis of 261 Cases Over a 10-Year Period. Cornea. 2018 Jan;37(1):66-71
- 5
Schmitzer S, Burcel M, Dăscălescu D, Popteanu IC. Goldenhar Syndrome - ophthalmologist's perspective. Rom J Ophthalmol. 2018 Apr-Jun;62(2):96-104
- 6
Barisic I, Odak L, Loane M, Garne E, Wellesley D, Calzolari E, et al. Prevalence, prenatal diagnosis and clinical features of oculo-auriculo-vertebral spectrum: a registry-based study in Europe. Eur J Hum Genet. 2014;22(8):1026-1033
- 7
Guida V, Calzari L, Fadda MT, Piceci-Sparascio F, Digil-io MC, Bernardini L, et al. Genome-Wide DNA Methylation Analysis of a Cohort of 41 Patients Affected by Oculo-Auriculo-Vertebral Spectrum (OAVS). Int J Mol Sci. 2021;22(3):1190
- 8
Tingaud-Sequeira A, Trimouille A, Sagardoy T, Lacombe D, Rooryck C. Oculo-auriculo-vertebral spectrum: new genes and literature review on a complex disease. J Med Genet. 2022;59(5):417-427
- 9
Rooijers W, Caron CJJM, Loudon SE, Padwa BL, Dunaway DJ, Forrest CR, et al. Ocular and adnexal anomalies in craniofacial microsomia: a systematic review. Int J Oral Maxillofac Surg. 2020;49(9):1107-1114
- 10
Cordero Alvarez DC. Goldenhar syndrome. Salud, Ciencia y Tecnología - Serie de Conferencias. 2024; 3:807. https://doi. org/10.56294/sctconf2024807.
- 11
Sharma JK, Pippal SK, Raghuvanshi SK, Shitij A. Síndrome de Goldenhar-Gorlin: relato de caso. Indian J Otolaringgol Head Neck Surg. 2006 Jan; 58(1):97-101. DOI: 10.1007/BF02907757. PMID: 23120253; PMCID: PMC3450607.
- 12
Margolis S, Aleksic S, Charles N, McCarthy J, Greco A, Budzilovich G. Retinal and optic nerve findings in Goldenhar-Gorlin syndrome. Ophthalmology. 1984;91(11):1327-1333
- 13
Kaouani A, Kerdoud O, Aloua R, Khalifi MC, Kettani AEL, Slimani F. Management of a giant ocular epibulbar dermoid. JPS Case Reports. 2021;71:101944
- 14
Umfress AC, Mawn LA, Joos KM, Donahue SP, Schmitt AD, Shieh C. Surgical management of large bilateral epibulbar dermoids with autologous oral mucous membrane transplantation. Am J Ophthalmol Case Rep. 2020;20:100982
- 15
Kokavec R. Goldenhar syndrome with various clinical manifestations. Cleft Palate Craniofac J. 2006 Sep;43(5):628-34. doi: 10.1597/05-094. PMID: 16986988.
- 16
Bogusiak K, Puch A, Arkuszewski P. Goldenhar syndrome: current perspectives. World J Pediatr. 2017 Oct;13(5):405-415. doi: 10.1007/s12519-017-0048-z. Epub 2017 Jun 15. PMID: 28623555.