Is the stent-assisted coiling still valid today?: longterm occlusion rate of the jailing technique
Melvin Francisco Ulerio Paniagua1,2
Melvin Francisco Ulerio Paniagua- 1 Department of Neurosurgery, Universidad Católica del Cibao, Hospital Centro Médico V Centenario and Hospital Centro de Especialidades Médicas Vegano, Dominican Republic
- 2 Department of Endovascular Neurological Therapy, Hospital Juarez de Mexico, Mexico City-Mexico
Diego Julian Alvis Peña3,4 ✉
Diego Julian Alvis PeñaCorresponding author- 3 Department of Neurosurgery, Universidad Nacional Autonoma de Mexico, Hospital Juarez de Mexico, Mexico City-Mexico
- 4 Department of Epidemiology, Universidad Surcolombiana, Neiva-Colombia
Martín Roberto Casas Martínez5
Martín Roberto Casas Martínez- 5 Department of Neurosurgery, Universidad Nacional Autonoma de Mexico, Hospital de Queretaro del IMSS, Department of Endovascular Neurological Therapy, Hospital Juarez de México, México City-México
Diana Hernández Santamaría6
Diana Hernández Santamaría- 6 Department of Neurology, Universidad Nacional Autónoma de México, Hospital Juárez de México, Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
Rogelio Nava Esquivel7
Rogelio Nava Esquivel- 7 Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
Fernando Espinosa Lira8
Fernando Espinosa Lira- 8 Department of Neurosurgery, Universidad Nacional Autónoma de México, Hospital Juárez de México, CMDX-México
Fernando Lara Torres9
Fernando Lara Torres- 9 Department of Neurosurgery, Universidad Tecnológico de Monterey, Hospital Ángeles Metropolitano, México City, México, Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
Gustavo Melo Guzman10
Gustavo Melo Guzman- 10 Head of The Department of Neurosurgery, Universidad Nacional Autónoma de México, Hospital Juárez de México, Hospital Ángeles Lomas, CMDX-México, Head of The Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
Show affiliations (10)
- 1Department of Neurosurgery, Universidad Católica del Cibao, Hospital Centro Médico V Centenario and Hospital Centro de Especialidades Médicas Vegano, Dominican Republic
- 2Department of Endovascular Neurological Therapy, Hospital Juarez de Mexico, Mexico City-Mexico
- 3Department of Neurosurgery, Universidad Nacional Autonoma de Mexico, Hospital Juarez de Mexico, Mexico City-Mexico
- 4Department of Epidemiology, Universidad Surcolombiana, Neiva-Colombia
- 5Department of Neurosurgery, Universidad Nacional Autonoma de Mexico, Hospital de Queretaro del IMSS, Department of Endovascular Neurological Therapy, Hospital Juarez de México, México City-México
- 6Department of Neurology, Universidad Nacional Autónoma de México, Hospital Juárez de México, Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
- 7Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
- 8Department of Neurosurgery, Universidad Nacional Autónoma de México, Hospital Juárez de México, CMDX-México
- 9Department of Neurosurgery, Universidad Tecnológico de Monterey, Hospital Ángeles Metropolitano, México City, México, Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
- 10Head of The Department of Neurosurgery, Universidad Nacional Autónoma de México, Hospital Juárez de México, Hospital Ángeles Lomas, CMDX-México, Head of The Department of Endovascular Neurological Therapy, Hospital Juárez de México, CMDX-México
Published
Abstract
BackgroundIntracranial aneurysms are a focal, pathological dilatation in most cerebral arteries affecting 3% to 5% of the world’s population. Rupture of these usually occurs without any predictive signs, with death occurring in 1 in 4 due to subarachnoid hemorrhage. Mortality of those who receive medical attention is 22% to 42%, while 63% of those who survive manage to resume their basic daily activities.
MethodsObservational, descriptive, analytical, retrospective cohort study, to determine the degree of long-term occlusion of stent-assisted coiling in patients with intracranial aneurysms.
ResultsThe mean age was 48, and the most frequent year range was from 30-39, with a percentage of 26.47%. The most prevalent gender was female with 74%. Long-term follow-up showed that treatment with the jailing technique resulted in complete aneurysm occlusion (Raymond-Roy I) in 82.35% of cases.
ConclusionOf the patients treated by the jailing technique, it was observed that it is an effective method for long-term occlusion of small and medium aneurysms. Complications were very low concerning endovascular treatment, as well as complications related to aneurysmal pathology.
1 Introduction#
Intracranial aneurysms are a focal, pathological dilatation in most cerebral arteries affecting 3% to 5% of the world population. Rupture of these usually occurs without any predictive signs, with death occurring in 1 in 4 due to subarachnoid hemorrhage. Mortality of those who do receive medical attention is 22% to 42%, while 63% of those who survive manage to return to work. Spontaneous subarachnoid hemorrhage is associated in 80% of cases with intracranial aneurysms [1] .
Factors associated with aneurysmal rupture can be separated into 2 categories: patient-related characteristics (gender, age, hypertension, smoking, sentinel headache) and aneurysm-related characteristics (size, stress on the aneurysmal wall, location, multiple aneurysms, growth) [1] .
Concerning aneurysmal treatment, the intervention can be divided into surgical treatment with its different aspects (Clipping, Protection, Bypass) and/or endovascular treatment (Coiling, Stent-assisted Coiling, flow diversion) [2] .
Surgery by itself can obtain 1-year occlusion rates of aneurysms with good technique of 90% in expert hands with a rebleeding rate of 0.5% per year, on the other hand, endovascular treatment is more easily reproducible and with the stent-assisted coiling technique the recurrence rate is 14.9% [3] ; while with the use of flow diversion a long-term occlusion rate of 96% was obtained [4] .
The complication rate of intracranial aneurysms that receive surgical treatment is 20%, among which are infarcts, intraparenchymal, or subarachnoid hematomas [1] , while endovascular treatment has a complication rate between 3-7% [4] . In this research, the objective was to determine the degree of long-term occlusion of stent-assisted coiling (jailing technique) in patients with intracranial aneurysms.
2 Materials and Methods#
We conducted an observational, descriptive, retrospective cohort study in a single center of neurosurgery/neurological endovascular therapy. The population consisted of all patients treated with stent-assisted coiling between January 1, 2012, and December 31, 2022, where the following primary outcomes were observed and described: rebleeding and functional outcome and secondary outcomes: mortality at discharge, mortality at six months, trans operative complications, late complications; and at hospital discharge: degree of occlusion at 12 and 24 months. Statistical analysis was performed using measures of central tendency (mean, median, and mode), measures of frequency, and association measure.
3 Results#
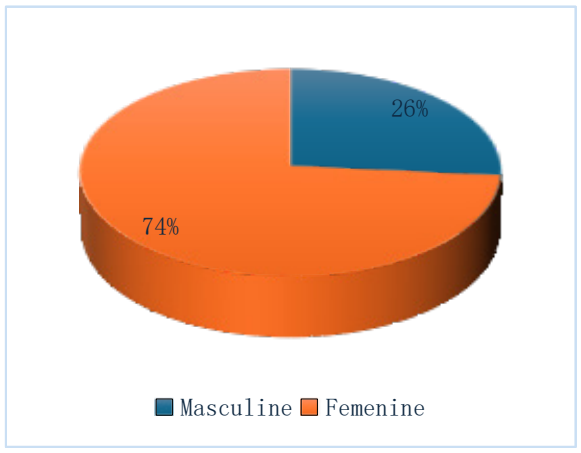
The research included 230 patients with intracranial aneurysms, of which 34 patients met the inclusion criteria. It was observed that 10 patients were men with 26% and 24 patients were women with 74%, the female: male ratio was 3:1 (See Figure 1).
The mean age was 48 years, with a minimum range of 23 years and a maximum range of 58 years, and the most frequent age range was 30-39 years, with a percentage of 26.4% (See Table 1). It was observed that among the non-modifiable risk factors associated with the development of aneurysms in our population sample, systemic hypertension was included with 58.8% and type 2 diabetes with 20.58%, with no other relevant associated pathologies. Among the modifiable risk factors observed in our investigation, smoking was found to be the most frequent risk factor, at 14.7%, followed by hypercholesterolemia at 8.82%.
Table 1 Age range
| Age | Frecuency | Percentaje |
|---|---|---|
| 18-29 | 3 | 8.82 |
| 30-39 | 9 | 26.47 |
| 40-49 | 6 | 17.64 |
| 50-59 | 9 | 26.47 |
| 60-69 | 4 | 11.76 |
| 70 y más. | 3 | 8.82 |
| Total | 34 | 100 |
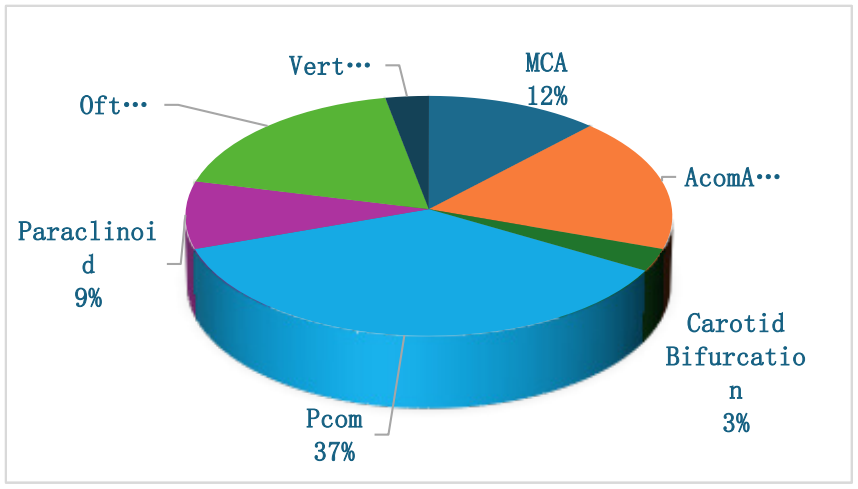
It was determined that within the clinical presentation of patients classified by the Hunt and Hess scale and the World Federation of Neurosurgical Societies (WFNS) scale, grade 1 was the most prevalent at 35.29% and 44.11%, respectively; within the unmodified Fisher imaging classification for subarachnoid hemorrhage (SAH), the most frequent grade was 3 with a percentage of 41.18% (See Table 2). 18% (See Table 2), within the clinic, most patients experienced aneurysm rupture with SAH at 76.47%, and less frequently observed nonspecific symptoms at 17.64%, followed by headache at 5.88%. Within the anatomical location most frequently observed was the aneurysm in the communicating segment of the internal carotid artery with 37%, followed by the anterior communicating artery and the ophthalmic segment of the internal carotid artery at 18% each (See Figure 2).
Table 2 Distribution according to clinical and imaging presentation
| Grade | Hunt y Hess n (%) | WFNS n (%) | Fisher n (%) |
|---|---|---|---|
| 1 | 12 ( 35.29) | 15 (44.11) | 6 (17.65) |
| 2 | 8 (23.52) | 5 (14.71) | 6 (17.65) |
| 3 | 8 (23.52) | 8 (23.52) | 14 (41.18) |
| 4 | 6 ( 17.64) | 3 ( 8.82) | 8 (23.52) |
| 5 | 0 | 3 ( 8.82) | - |
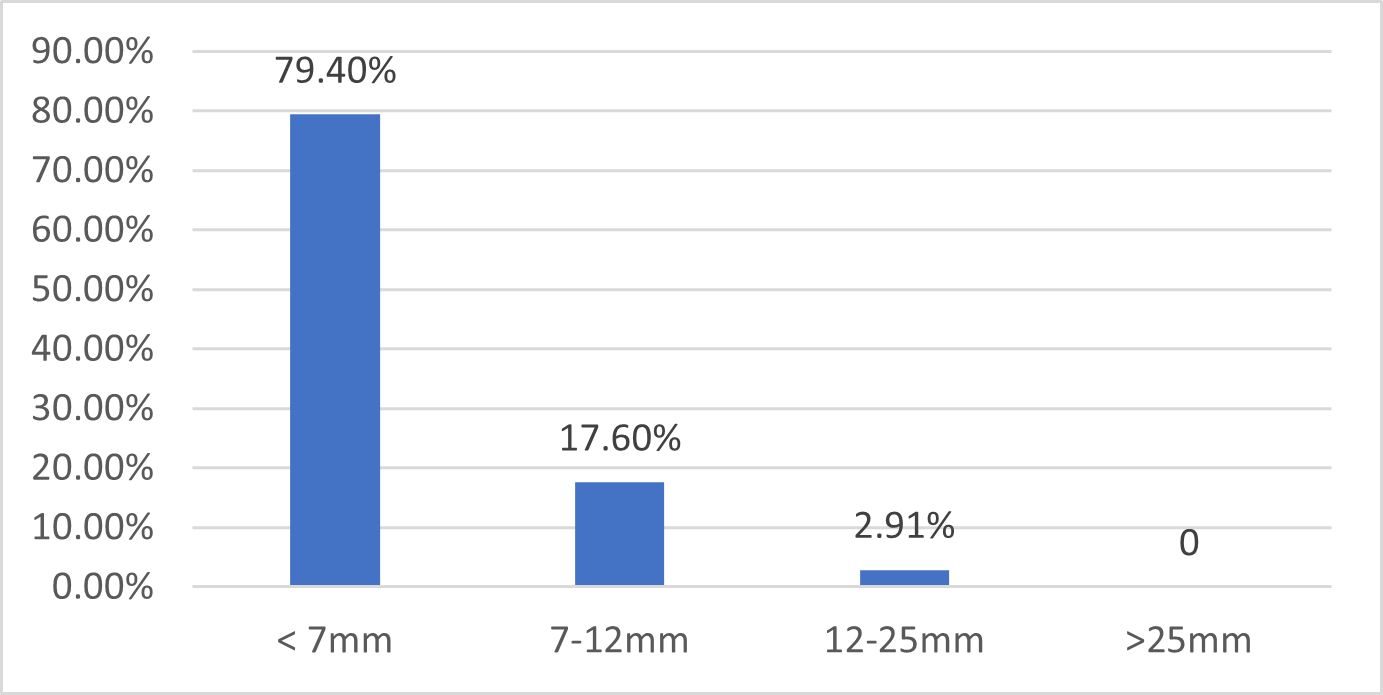
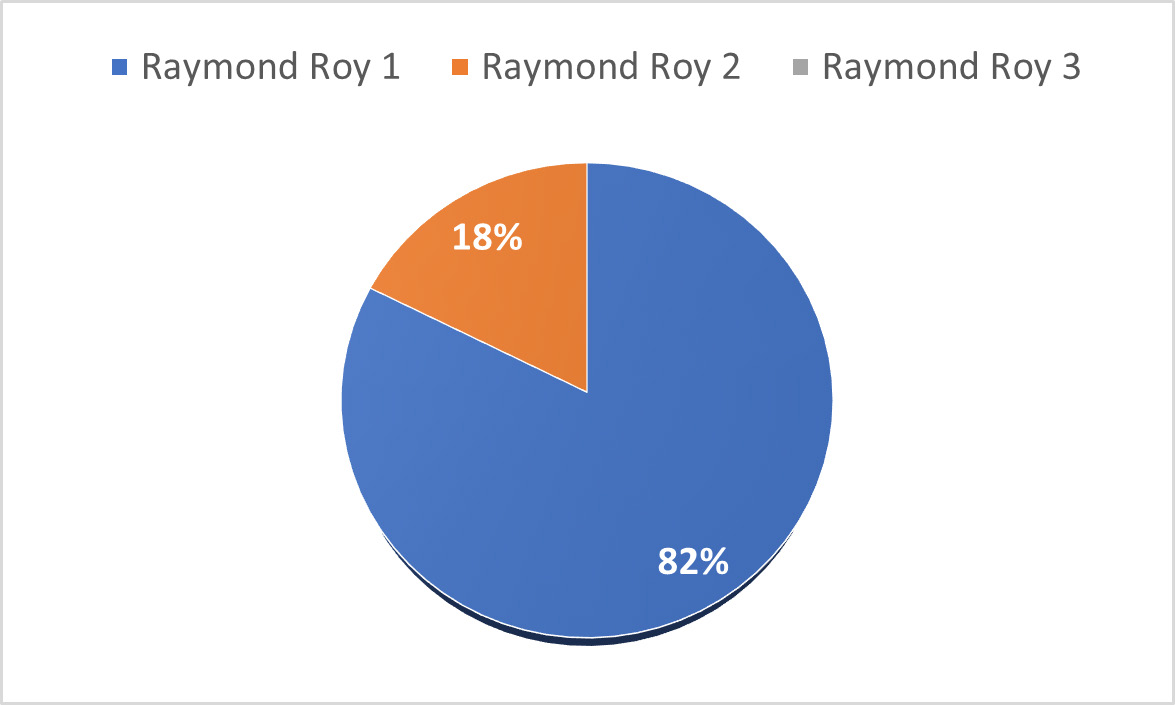
Regarding the size of the aneurysm, most were classified as small (<7mm) with a percentage of 79.4%, followed by medium (7mm-12mm) with 17.6%, large (12mm-25mm) with 2.91% and no cases of giant aneurysms were observed (See Figure 3). During the follow-up of patients, it was observed that treatment with stent-assisted coiling or jailing technique resulted in complete occlusion of the aneurysm or grade I according to the Raymond-Roy classification with 82.35%, grade II of the Raymond-Roy classification with 17.64%, no patients with a Raymond-Roy III classification were observed during follow-up (See Figure 4). No correlation or statistical association was found by Spearman correlation (0.024, P=0.895) between aneurysm size and long-term occlusion with the use of stents in small and medium aneurysms, no correlation or association was observed by Spearman correlation (-0.036, P=0.840) between the degree of occlusion by jailing technique and the location of the aneurysm. No association was observed by Pearson correlation (-0.071, P=0.691) between age and the degree of long-term occlusion by the jailing technique.
No comparison could be made between aneurysms treated only with coils and aneurysms treated with jailing technique, since no aneurysm was treated only with coils with the intention of curing, only to protect and then perform stent-assisted coiling. Complications with the jailing technique were low, reporting vasospasm at 5.8% and hematoma at the puncture site in only one patient at 2.9%.
4 Discussion#
It is well established that the female gender is a risk factor for the development of intracranial aneurysms, being related according to experimental models with the immunity of estrogen influence[5] , in this study resulted in a higher incidence in the female gender, with a ratio of 2.4:1 compared to the male gender, slightly higher than the range of 1.4-1.7 reported by Turan et al[6]. Similarly, Juvela et al. in 1978[7] presented 54% female participation, while Gondar in 2021 reported 86% [8] . The mean age of the individuals studied was 48 years, which is relatively young compared to the mean age of 61.1 years obtained by Zuurbier et al.[9] , the age of 56 years reported by Lindgren in his series of more than 1000 aneurysms[10] , and the 51 years mean age found by Wermer[11] . Regarding Fisher grading, grade III was observed in 41.18% of cases, being the most frequent but less than the 65% reported by Sato[12] . In the Donkerlar study, Fisher III SAH accounted for 10% of the total, while Fisher IV predominated with 60% [13] , which is comparable to the ISAT study where Fisher III SAH was present in 43%[14] .
Finally, the WFNS scale was grade 1 in 44.1% of the patients evaluated, similar to the 47% reported by Donkelar when evaluating his patients upon arrival[13] and to the 37% found by Vergouwen[15] . It is well known that in the traditional literature, it is established that the site of origin of the highest incidence of intracranial aneurysms is in the anterior communicating complex[16] , on the other hand, in our series, we obtained that the main location was the communicating segment of the internal carotid artery (ICA) (35%) relating to other studies reviewed as presented by Greving et al[17] while in the study presented by Hurth the main location was in the middle cerebral artery[18] , all agreeing that the main location is in the anterior circulation.
There are different risk factors associated with the development of intracranial aneurysms, including age, hypertension, smoking, thoracic aortic aneurysms, and hereditary deficiencies (polycystic kidney disease, Ehlers-Danlos syndrome, Marfan syndrome, fibromuscular dysplasia, or history of aneurysmal disease)[18,19] . The risk factors observed in our study showed that hypertension was present in 58.8% of cases, Zurbier in his research showed the same trend related to hypertension in 44% of individuals studied in his work[21,22] , Bechstein similarly in his work found this pathology was present in 65% of the population with ruptured aneurysms and 56% of unruptured aneurysms[22,23] . On the other hand, diabetes type 2 was a diagnosis present in 20.58% of the population, while in the study by Bechstein it was present in 10% of ruptured aneurysms and 12% of unruptured aneurysms[23] . Regarding modifiable risk factors, smoking was the most frequent, with 14.7%.
We obtained a long-term occlusion rate with the jailing technique of 82.35% considered this on the Raymond-Roy I scale, this percentage is much better than that presented by Fern et al which was only 61.5% in which only coiling was performed[24,25] , while Zhang et al obtained a percentage of raymond-roy I occlusion in the coiling group of 55. 92% and a very similar 63.4% in the jailing technique group, much lower than that obtained in our research[25] , Mokin presented total occlusion in 75% of cases being a result more in line with those obtained by us[25,26] .
Aneurysms were small in 79.41% of cases representing a much higher proportion than in the study by Mokin where it represented only 37%, with the largest group represented by medium sized aneurysms[27] . Boisseau et al reported small aneurysms in only 22.2% of patients in their series[28] .
Youmans and Winn in their chapter 424 state that the rate of complications in endovascular treatment reaches a range between 9%-30%[19] , our complication rate was 8.7%, Kwon presented a rate of aneurysmal rupture in 5% of cases when coiling was performed[29] in our series we do not describe this complication.
5 Conclusion#
Of the patients treated by jailing technique, it was observed that it is an effective method for long-term occlusion of small and medium aneurysms. Complications were very low in relation to endovascular treatment, as well as complications related to aneurysmal pathology. It was not possible to compare the results of the jailing technique with the coiling technique alone because no patient underwent coiling alone. It is important to mention that although our research is one of the first in our geographic area and our institution, it must be recognized that being an observational study, it does not generate causality, nor does it calculate and estimate the odds ratio or relative risk; however, this research will serve as a basis for future prospective and analytical research to assess the rate of aneurysmal occlusion in the long term (choice of stent, type of coil, location of the aneurysm).
5.1 Statement of patient consent#
Patient consent is not required as patient identities were not disclosed or compromised.
Declarations
€Funding
◎Competing interests
Article information
- Published
Copyright © 2025 Dr.Diego Julian Alvis Peña. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 29#
- 1
Barak T, Miyagishima D , Yasuno K, Gunnel M,Youmans, Chapter 424, 2023 Edition, Genetics of intracranial Aneurysm, Pag 3400
- 2
Bechstein, M., Gansukh, A., Regzengombo, B., Byambajav, O., Meyer, L., Schönfeld, M., Kniep, H., Hanning, U., Broocks, G., Gansukh, T., & Fiehler, J. (2022). Risk Factors for Cerebral Aneurysm Rupture in Mongolia. Clinical neuroradiology, 32(2), 499–506. https://doi-org.pbidi.unam.mx:2443/10.1007/s00062-021-01051-z
- 3
Boisseau, W., Darsaut, T. E., Fahed, R., Drake, B., Lesiuk, H., Rempel, J. L., Gentric, J. C., Ognard, J., Nico, L., Iancu, D., Roy, D., Weill, A., Chagnon, M., Zehr, J., Lavoie, P., Nguyen, T. N., & Raymond, J. (2023). Stent-Assisted Coiling in the Treatment of Unruptured Intracranial Aneurysms: A Randomized Clinical Trial. AJNR. American journal of neuroradiology, 44(4), 381–389. https://doi-org.pbidi.unam.mx:2443/10.3174/ajnr.A7815
- 4
Britz G, Schaller K, Youmans, The Natural History of Cerebral Aneurysm, Winn R., Chapter 425, 2023 Edition, P 3400-3419
- 5
Brown, R. D., Jr, & Broderick, J. P. (2014). Unruptured intracranial aneurysms: epidemiology, natural history, management options, and familial screening. The Lancet. Neurology, 13(4), 393–404. https://doiorg.pbidi.unam.mx:2443/10.1016/S1474-4422(14)70015-8
- 6
D. Le Roux , Youmans and Sweet, Surgical Decision Making for the treatment of intracranial aneurysm, Chapter 427, Elsevier, edición 2023, , 3428-3457.
- 7
Etminan N, Rinkel GJ. Unruptured intracranial aneurysms: development, rupture and preventive management. Nat Rev Neurol. 2016 Dec;12(12):699-713. doi: 10.1038/nrneurol.2016.150. Epub 2016 Nov 3. Erratum in: Nat Rev Neurol. 2017 Feb 1;13(2):126. PMID: 27808265.
- 8
Ferns, S. P., Sprengers, M. E., van Rooij, W. J., Rinkel, G. J., van Rijn, J. C., Bipat, S., Sluzewski, M., & Majoie, C. B. (2009). Coiling of intracranial aneurysms: a systematic review on initial occlusion and reopening and retreatment rates. Stroke, 40(8), e523–e529. https://doi-org.pbidi.unam.mx:2443/10.1161/STROKEAHA.109.553099
- 9
Froelich, J. J., Neilson, S., Peters-Wilke, J., Dubey, A., Thani, N., Erasmus, A., Carr, M. W., & Hunn, A. W. (2016). Size and Location of Ruptured Intracranial Aneurysms: A 5-Year Clinical Survey. World neurosurgery, 91, 260–265. https://do++i-org.pbidi.unam.mx:2443/10.1016/j.wneu.2016.04.044
- 10
Fuentes, A. M., Stone McGuire, L., & Amin-Hanjani, S. (2022). Sex Differences in Cerebral Aneurysms and Subarachnoid Hemorrhage. Stroke, 53(2), 624–633. https://doi-org.pbidi.unam.mx:2443/10.1161/STROKEAHA.121.037147
- 11
Gondar R, Gautschi OP, Cuony J, Perren F, Jägersberg M, Corniola MV, Schatlo B, Molliqaj G, Morel S, Kulcsár Z, et al. Unruptured intracranial aneurysm follow-up and treatment after morphological change is safe: observational study and systematic review. J Neurol Neurosurg Psychiatry.
- 12
Greving, J. P., Wermer, M. J., Brown, R. D., Jr, Morita, A., Juvela, S., Yonekura, M., Ishibashi, T., Torner, J. C., Nakayama, T., Rinkel, G. J., & Algra, A. (2014). Development of the PHASES score for prediction of risk of rupture of intracranial aneurysms: a pooled analysis of six prospective cohort studies. The Lancet. Neurology, 13(1), 59–66. https://doi-org.pbidi.unam.mx:2443/10.1016/S1474-4422(13)70263-1
- 13
Hurth, H., Steiner, J., Birkenhauer, U., Roder, C., Hauser, T. K., Ernemann, U., Tatagiba, M., & Ebner, F. H. (2021). Relationship of the vascular territory affected by delayed cerebral ischemia and the location of the ruptured aneurysm in patients with aneurysmal subarachnoid hemorrhage. Neurosurgical review, 44(6), 3479–3486. https://doi-org.pbidi.unam.mx:2443/10.1007/s10143-021-01522-4
- 14
Ihn, Y. K., Shin, S. H., Baik, S. K., & Choi, I. S. (2018). Complications of endovascular treatment for intracranial aneurysms: Management and prevention. Interventional neuroradiology : journal of peritherapeutic neuroradiology, surgical procedures and related neurosciences, 24(3), 237–245. https://doi-org.pbidi.unam.mx:2443/10.1177/1591019918758493
- 15
Juvela S, Poussa K, Lehto H, Porras M. Natural history of unruptured intracranial aneurysms: a long-term follow-up study. Stroke. 2013;44:2414– 2421. doi: 10.1161/STROKEAHA.113.001838
- 16
Lindgren, A. E., Koivisto, T., Björkman, J., von Und Zu Fraunberg, M., Helin, K., Jääskeläinen, J. E., & Frösen, J. (2016). Irregular Shape of Intracranial Aneurysm Indicates Rupture Risk Irrespective of Size in a Population-Based Cohort. Stroke, 47(5), 1219–1226. https://doi-org.pbidi.unam.mx:2443/10.1161/STROKEAHA.115.012404
- 17
Mokin, M., Primiani, C. T., Ren, Z., Piper, K., Fiorella, D. J., Rai, A. T., Orlov, K., Kislitsin, D., Gorbatykh, A., Mocco, J., De Leacy, R., Lee, J., Vargas Machaj, J., Turner, R., Chaudry, I., & Turk, A. S. (2020). Stent-assisted coiling of cerebral aneurysms: multi-center analysis of radiographic and clinical outcomes in 659 patients. Journal of neurointerventional surgery, 12(3), 289–297. https://doi-org.pbidi.unam.mx:2443/10.1136/neurintsurg-2019-015182
- 18
Molyneux, A. J., Kerr, R. S., Yu, L. M., Clarke, M., Sneade, M., Yarnold, J. A., Sandercock, P., & International Subarachnoid Aneurysm Trial (ISAT) Collaborative Group (2005). International subarachnoid aneurysm trial (ISAT) of neurosurgical clipping versus endovascular coiling in 2143 patients with ruptured intracranial aneurysms: a randomised comparison of effects on survival, dependency, seizures, rebleeding, subgroups, and aneurysm occlusion. Lancet (London, England), 366(9488), 809–817. https://doi-org.pbidi.unam.mx:2443/10.1016/S0140-6736(05)67214-5
- 19
Oushy, S., Rinaldo, L., Brinjikji, W., Cloft, H., & Lanzino, G. (2020). Recent advances in stent-assisted coiling of cerebral aneurysms. Expert review of medical devices, 17(6), 519–532. https://doi-org.pbidi.unam.mx:2443/10.1080/17434440.2020.1778463
- 20
Pritz MB. Cerebral aneurysm classification based on angioarchitecture. J Stroke Cerebrovasc Dis. 2011 Mar-Apr;20(2):162-7. doi: 10.1016/j.jstrokecerebrovasdis.2009.11.018. Epub 2010 Jul 10. PMID: 20621522.
- 21
Salsac AV, Sparks SR, Lasheras JC. Hemodynamic changes occurring during the progressive enlargement of abdominal aortic aneurysms. Ann Vasc Surg. 2004 Jan;18(1):14-21. doi: 10.1007/s10016-003-0101-3. Epub 2004 Jan 12. PMID: 14712379.
- 22
Sato, H., Kamide, T., Kikkawa, Y., Kimura, T., Kuribara, S., Yanagawa, T., Suzuki, K., Ikeda, T., & Kurita, H. (2021). Clinical Characteristics of Ruptured Intracranial Aneurysm in Patients with Multiple Intracranial Aneurysms. World neurosurgery, 149, e935–e941. https://doi org.pbidi.unam.mx:2443/10.1016/j.wneu.2021.01.072
- 23
Shehata, M. A., Ibrahim, M. K., Ghozy, S., Bilgin, C., Jabal, M. S., Kadirvel, R., & Kallmes, D. F. (2023). Long-term outcomes of flow diversion for unruptured intracranial aneurysms: a systematic review and meta-analysis. Journal of neurointerventional surgery, 15(9), 898–902. https://doi-org.pbidi.unam.mx:2443/10.1136/jnis-2022-019240
- 24
Turan, N., Heider, R. A., Zaharieva, D., Ahmad, F. U., Barrow, D. L., & Pradilla, G. (2016). Sex Differences in the Formation of Intracranial Aneurysms and Incidence and Outcome of Subarachnoid Hemorrhage: Review of Experimental and Human Studies. Translational stroke research, 7(1), 12–19. https://doi-org.pbidi.unam.mx:2443/10.1007/s12975-015-0434-6
- 25
Van Donkelaar, C. E., Bakker, N. A., Birks, J., Veeger, N. J. G. M., Metzemaekers, J. D. M., Molyneux, A. J., Groen, R. J. M., & van Dijk, J. M. C. (2019). Prediction of Outcome After Aneurysmal Subarachnoid Hemorrhage. Stroke, 50(4), 837–844. https://doi-org.pbidi.unam.mx:2443/10.1161/STROKEAHA.118.023902
- 26
Vergouwen, M. D., Germans, M. R., Post, R., Tjerkstra, M. A., Coert, B. A., Rinkel, G. J., Peter Vandertop, W., & Verbaan, D. (2023). Aneurysm treatment within 6 h versus 6-24 h after rupture in patients with subarachnoid hemorrhage. European stroke journal, 8(3), 802–807. https://doi-org.pbidi.unam.mx:2443/10.1177/23969873231173273
- 27
Wermer, M. J., van der Schaaf, I. C., Velthuis, B. K., Majoie, C. B., Albrecht, K. W., & Rinkel, G. J. (2006). Yield of short-term follow-up CT/MR angiography for small aneurysms detected at screening. Stroke, 37(2), 414–418. https://doi-org.pbidi.unam.mx:2443/10.1161/01.STR.0000199077.06390.35
- 28
Zhang G, Wu Y, Wei Y, Xue G, Chen R, Lv N, Zhang X, Duan G, Yu Y, Li Q, Xu Y, Huang Q, Yang P, Zuo Q, Liu J. Stent-assisted coiling vs. coiling alone of ruptured tiny intracranial aneurysms: A contemporary cohort study in a high-volume center. Front Neurol. 2022 Dec 6;13:1076026. doi: 10.3389/fneur.2022.1076026. PMID: 36561296; PMCID: PMC9763558.
- 29
Zuurbier, C. C. M., Molenberg, R., Mensing, L. A., Wermer, M. J. H., Juvela, S., Lindgren, A. E., Jääskeläinen, J. E., Koivisto, T., Yamazaki, T., Uyttenboogaart, M., van Dijk, J. M. C., Aalbers, M. W., Morita, A., Tominari, S., Arai, H., Nozaki, K., Murayama, Y., Ishibashi, T., Takao, H., Gondar, R., … Ruigrok, Y. M. (2022). Sex Difference and Rupture Rate of Intracranial Aneurysms: An Individual Patient Data Meta-Analysis. Stroke, 53(2), 362–369. https://doi org.pbidi.unam.mx:2443/10.1161/STROKEAHA.121.035187