Systematic Review On Ischemic Events And Post-Myocardial Infarction Heart Failure: From Initial Approach To Definitive Treatment
Published in Journal of Cardiovascular Diseases
Camila Tomasi1
Camila Tomasi- 1 Resident Physician in Internal Medicine – Santa Casa de Misericórdia de Goiânia, Brazil
Joel Eloi Belo Junior2
Joel Eloi Belo Junior- 2 Major Aviator of the Brazilian Air Force; Master’s degree in Human Operational Performance; Master’s degree in Intellectual Property and Technology Transfer for Innovation
Leocadia Felix de Araújo3
Leocadia Felix de Araújo- 3 Graduate in Medicine from the Federal University of Fronteira Sul, Passo Fundo Campus, Rio Grande do Sul, Brazil
Orseli Marques Ferreira Neto4
Orseli Marques Ferreira Neto- 4 Doctor of Medicine, University of Rio Verde Campus Aparecida, Brazil
Délio Tiago Martins Malaquias5
Délio Tiago Martins Malaquias- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Marilda Bispo de Sá Oliveira6
Marilda Bispo de Sá Oliveira- 6 Medical Student. University of the Integration of the Americas (UNIDA), Ciudad del Este- Py
Gabriel Leonardo Saraiva5
Gabriel Leonardo Saraiva- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Guilherme Guissone Martins5
Guilherme Guissone Martins- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Maria Eduarda Kartabil Machado de Souza5
Maria Eduarda Kartabil Machado de Souza- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Larissa Lauretto7
Larissa Lauretto- 7 Medical Student – University of Western São Paulo (UNOESTE), Guarujá/SP, Brazil
Érica Miriam Fernandes Miranda Vão5
Érica Miriam Fernandes Miranda Vão- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
José Carlos Ferreira da Silva5
José Carlos Ferreira da Silva- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Felix Adriano Pietroluongo Vidal Tabera8
Felix Adriano Pietroluongo Vidal Tabera- 8 Medical Student – Nove de Julho University (UNINOVE), São Bernardo do Campo/SP, Brazil
Victoria Geovana Tobias8
Victoria Geovana Tobias- 8 Medical Student – Nove de Julho University (UNINOVE), São Bernardo do Campo/SP, Brazil
Andre Luiz Vergamini Dias8
Andre Luiz Vergamini Dias- 8 Medical Student – Nove de Julho University (UNINOVE), São Bernardo do Campo/SP, Brazil
Ingrid de Mariz Zane8
Ingrid de Mariz Zane- 8 Medical Student – Nove de Julho University (UNINOVE), São Bernardo do Campo/SP, Brazil
Letícia Brustolim Rosa9
Letícia Brustolim Rosa- 9 Medical Student – Faculty of Medical Sciences of São José dos Campos (Humanitas), SP, Brazil
Enzo Maruzzo Marques9
Enzo Maruzzo Marques- 9 Medical Student – Faculty of Medical Sciences of São José dos Campos (Humanitas), SP, Brazil
Rubens Rodrigues Tutela10
Rubens Rodrigues Tutela- 10 Medical Student – São Judas University, São Paulo/SP, Brazil
Ana Clara Lobo Ribeiro11
Ana Clara Lobo Ribeiro- 11 Medical Student – University of Rio Verde (UNIRV), Aparecida de Goiânia Campus/GO, Brazil
José Antônio do Nascimento Neto12
José Antônio do Nascimento Neto- 12 Medical Student – Central University of Paraguay, Ciudad del Este, Paraguay
Francisco Rogério de Sousa Mota12
Francisco Rogério de Sousa Mota- 12 Medical Student – Central University of Paraguay, Ciudad del Este, Paraguay
Cindy Alves Vilarinho5
Cindy Alves Vilarinho- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Giancarlo Damasceno Diegues7
Giancarlo Damasceno Diegues- 7 Medical Student – University of Western São Paulo (UNOESTE), Guarujá/SP, Brazil
Thiago Augusto Rochetti Bezerra5 ✉
Thiago Augusto Rochetti BezerraCorresponding author- 5 Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
Carlos Henrique Batista Figueiredo de Mendonça13
Carlos Henrique Batista Figueiredo de Mendonça- 13 Federal University of Roraima (UFRR)
Show affiliations (13)
- 1Resident Physician in Internal Medicine – Santa Casa de Misericórdia de Goiânia, Brazil
- 2Major Aviator of the Brazilian Air Force; Master’s degree in Human Operational Performance; Master’s degree in Intellectual Property and Technology Transfer for Innovation
- 3Graduate in Medicine from the Federal University of Fronteira Sul, Passo Fundo Campus, Rio Grande do Sul, Brazil
- 4Doctor of Medicine, University of Rio Verde Campus Aparecida, Brazil
- 5Medical Student – Ribeirão Preto University (UNAERP), Guarujá/SP, Brazil
- 6Medical Student. University of the Integration of the Americas (UNIDA), Ciudad del Este- Py
- 7Medical Student – University of Western São Paulo (UNOESTE), Guarujá/SP, Brazil
- 8Medical Student – Nove de Julho University (UNINOVE), São Bernardo do Campo/SP, Brazil
- 9Medical Student – Faculty of Medical Sciences of São José dos Campos (Humanitas), SP, Brazil
- 10Medical Student – São Judas University, São Paulo/SP, Brazil
- 11Medical Student – University of Rio Verde (UNIRV), Aparecida de Goiânia Campus/GO, Brazil
- 12Medical Student – Central University of Paraguay, Ciudad del Este, Paraguay
- 13Federal University of Roraima (UFRR)
Published
Abstract
Acute myocardial infarction (AMI) remains one of the leading causes of global morbidity and mortality, despite advances in diagnostic and treatment strategies. Among its complications, post-ischemic heart failure (HF) stands out as a clinical outcome with a major impact, responsible for a significant increase in hospitalizations, reduced quality of life, and elevated mortality rates in the medium and long term. Understanding the pathophysiological evolution from AMI to HF is essential, as it involves factors such as the extent of myocardial necrosis, adverse ventricular remodeling, neurohormonal activation, and persistent inflammatory processes. The literature shows that the initial approach to AMI, especially early reperfusion by percutaneous coronary intervention or thrombolysis, reduces immediate mortality but does not eliminate the risk of developing HF. Studies such as those by O’Gara et al. (2013) and Ibanez et al. (2018) show a significant prevalence of HF even in scenarios with optimized reperfusion, suggesting that mechanisms other than coronary obstruction contribute to functional deterioration. In the context of chronic treatment, combined pharmacological therapies—including beta-blockers, angiotensin-converting enzyme (ACE) inhibitors, aldosterone antagonists, and, more recently, sacubitril/valsartan—have been shown to reduce mortality and hospitalizations, as evidenced in multicenter studies such as those by McMurray et al. (2014) and Velazquez et al. (2016). In addition, international guidelines, such as those proposed by Ponikowski et al. (2016) and Heidenreich et al. (2022), reinforce the importance of risk stratification, multidisciplinary management, and continuous outpatient follow-up to prevent the progression of HF. Despite these achievements, significant challenges remain, especially in countries with unequal access to healthcare. Rates of post-infarction HF remain high, and the heterogeneity of outcomes across different populations reflects gaps in the universal application of evidence-based therapies. In addition, adverse ventricular remodeling remains a central process, reinforcing the need for preventive strategies and individualized therapies. This systematic review integrates the main findings in the literature on the relationship between AMI, subsequent ischemic events, and post-infarction HF, covering everything from the initial approach to definitive treatment. The results point to an evolutionary line of care, initially focused on reperfusion, later consolidated with combined pharmacotherapy, and more recently expanded to innovative and personalized therapies. It is concluded that post-ischemic HF should be understood not only as an inevitable complication but as an outcome that can be prevented, mitigated, and effectively treated, provided that guidelines are followed, access to therapies is expanded, and new technologies are incorporatedinto clinical care.
1 Introduction#
Acute myocardial infarction (AMI) remains one of the leading causes of morbidity and mortality worldwide, despite advances in early diagnosis and therapeutic interventions. It is estimated that millions of people suffer ischemic events annually, with a direct impact on survival and quality of life, especially in developing countries, where there is unequal access to health services (WHO, 2021).
The clinical evolution after AMI is closely related to the extent of myocardial necrosis and the subsequent inflammatory response. These factors contribute to adverse ventricular remodeling and the development of heart failure (HF), a frequent complication responsible for a high economic and social burden (PONIKOWSKI et al., 2016).
Recurrent ischemic events, such as new episodes of unstable angina or reinfarction, increase the risk of ventricular function deterioration. In addition, patients who survive AMI are more prone to malignant arrhythmias, cardiogenic shock, and repeated hospitalizations, reinforcing the need for effective therapeutic strategies from the initial approach to definitive treatment (O’GARA et al., 2013).
The initial approach to patients with AMI should prioritize early myocardial reperfusion, either by thrombolysis or primary percutaneous coronary intervention, associated with antithrombotic therapy and hemodynamic support measures. However, even with adequate management in the acute phase, many individuals develop persistent ventricular dysfunction, making post-infarction HF a highly relevant clinical outcome (IBANEZ et al., 2018).
In this context, post-ischemic heart failure represents a multifactorial condition, involving not only structural damage to the myocardium, but also neurohormonal, inflammatory, and metabolic changes. This set of mechanisms perpetuates functional deterioration and increases the risk of long-term mortality, highlighting the importance of personalized therapies (HEIDENREICH et al., 2022).
Given the complexity of the topic, a systematic review addressing ischemic events and post-infarction heart failure, covering from the initial phase to definitive treatment, is essential to integrate the available evidence and guide clinical practices based on robust data (HIGGINS et al., 2022).
2 Objectives#
The main objective of this systematic review is to synthesize the scientific evidence on the relationship between ischemic events and the development of post-infarction heart failure, addressing everything from the initial management of acute myocardial infarction to definitive treatment strategies. The aim is to understand clinical evolution, identify prognostic factors, and evaluate the effectiveness of therapeutic interventions throughout the continuum of care (PONIKOWSKI et al., 2016).
Specific objectives include:
(i). to describe the main ischemic complications after infarction;
(ii). to analyze the prevalence and impact of post-ischemic heart failure;
(iii). to evaluate the effectiveness of reperfusion, pharmacological, and surgical therapies in the prognosis of these patients;
(iv). to integrate the available evidence to guide clinical practice and support future research in the area (O’GARA et al., 2013).
3 Methodology#
This systematic review was conducted in accordance with the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) guidelines, ensuring methodological rigor and transparency at all stages (PAGE et al., 2021).
Search strategy
The PubMed/MEDLINE, Embase, Scopus, Cochrane Library, and Web of Science databases were searched, including articles published between 2000 and 2025. The strategy combined controlled descriptors (MeSH and Emtree) and keywords such as “myocardial infarction,” “ischemic events,” “heart failure,” and “post-infarction,” in addition to their equivalents in Portuguese. The search was conducted without language restrictions, provided that the text was available in its entirety (HIGGINS et al., 2022).
3.1 Inclusion and exclusion criteria#
Original studies (randomized clinical trials, cohort studies, and case-control studies), systematic reviews, and meta-analyses addressing the relationship between AMI, subsequent ischemic events, and heart failure were included. Case reports, case series with small samples (<30 patients), and articles without direct clinical relevance, such as experimental studies in animal models, were excluded (MOHER et al., 2015).
3.2 Data extraction and analysis#
The information extracted included participant characteristics, interventions performed, clinical outcomes (reinfarction, hospitalization, mortality, and post-infarction HF), and follow-up time. The methodological quality of the studies was assessed using the Cochrane Risk of Bias tool for clinical trials and the Newcastle-Ottawa Scale for observational studies (HIGGINS et al., 2022).
4 Results#
The initial search retrieved a large number of articles in the databases, from which, after applying the inclusion and exclusion criteria, the studies that best described the relationship between acute myocardial infarction (AMI), subsequent ischemic complications, and progression to post-infarction heart failure (HF) were selected.
The studies analyzed show that, even with therapeutic advances such as early reperfusion and the use of modern pharmacological therapies (beta-blockers, ACE inhibitors, aldosterone antagonists, and antiplatelet therapies), post-ischemic HF remains a significant complication. In addition, recurrent ischemic events, reinfarction, and adverse ventricular remodeling have been identified as the main determinants of poor prognosis (O’GARA et al., 2013; IBANEZ et al., 2018; HEIDENREICH et al., 2022).
The body of evidence indicates that early adoption of integrated strategies—reperfusion, pharmacological optimization, and follow-up in cardiovascular rehabilitation programs—substantially reduces morbidity and mortality. However, methodological differences between studies (population evaluated, diagnostic criteria for HF, and follow-up time) make direct comparison of results difficult.
A comparative analysis of the main studies on ischemic events and post-infarction heart failure is essential to understand the evolution of scientific knowledge in the field and the applicability of different therapeutic strategies.
Table 1 summarizes the most relevant findings from the recent literature, providing an integrated view of the relationship between acute myocardial infarction, its subsequent complications, and the development of heart failure. The tabular format facilitates the identification of patterns, methodological differences, and therapeutic advances, assisting in the development of evidence-based approaches.
Table 1 Main studies on ischemic events and post-infarction heart failure
| Author/Year | Population | Interventions | Main Findings | Reference |
|---|---|---|---|---|
| O’GARA et al., 2013 | Patients with AMI with supra | Reperfusion (primary PCI/thrombolysis) + drug therapy | Reduction in hospital mortality, but persistent risk of post-infarction HF | O’GARA et al., 2013 |
| Ibanez et al., 2018 | Patients with STEMI treated in European centers | Primary PCI + guideline-guided pharmacotherapy | Improved survival, but HF remains prevalent in up to 20% of cases | Ibanez et al., 2018 |
| McMurray et al., 2014 | Patients with post-infarction HF | Beta-blockers, ACE inhibitors/ARBs, aldosterone antagonists | Reduction in mortality and hospitalization; importance of combination therapy | McMURRAY et al., 2014 |
| Ponikowski et al., 2016 | Review of patients with chronic HF, including post-infarction | Management based on ESC guidelines | Highlights ventricular remodeling as a central factor in post-ischemic HF | Ponikowski et al., 2016 |
| Heidenreich et al., 2022 | Patients with HF in the US (multicenter) | AHA/ACC/HFSA guidelines for HF | Emphasis on evidence-based therapies and outpatient monitoring | Heidenreich et al., 2022 |
| Velazquez et al., 2016 (PARADIGM-HF) | Patients with HF after AMI | Sacubitril/valsartan vs. enalapril | Significant reduction in HF hospitalizations and cardiovascular mortality | Velazquez et al., 2016 |
Source: Authors
Table 1 shows that older studies, such as the ACCF/AHA guidelines (O’GARA et al., 2013), already emphasized the importance of early reperfusion, but pointed out limitations regarding the persistent risk of heart failure after myocardial infarction. Later studies, such as that by Ibanez et al. (2018), reinforce the efficacy of primary percutaneous coronary intervention and modern pharmacotherapy, although they still indicate a significant prevalence of post-ischemic HF.
McMurray et al. (2014) and Ponikowski et al. (2016) highlight the impact of combined drug therapies and ventricular remodeling management, respectively, confirming the relevance of chronic treatment in reducing mortality. More recently, Heidenreich et al. (2022) consolidate current guidelines, emphasizing the need for outpatient follow-up and multidisciplinary integration. The study by Velazquez et al. (2016), in turn, provides robust evidence on new therapies, such as the sacubitril/valsartan combination, which has demonstrated superior benefits in clinical outcomes. Therefore, the table shows the progression of clinical management from emergency reperfusion strategies ( ) to advanced pharmacological approaches, reflecting the evolution of medical practice and the persistent challenges in the prevention and treatment of post-infarction heart failure.
The box plot graph presented aims to illustrate, in a comparative manner, the prevalence of post-infarction heart failure (HF) reported in different relevant studies in the literature. This type of graphical representation allows the distribution of data to be visualized, identifying medians, interquartile ranges, and possible variations between studies. Thus, the box plot helps to highlight the heterogeneity of the results found, reflecting differences in methodology, study population, and therapeutic strategies employed.
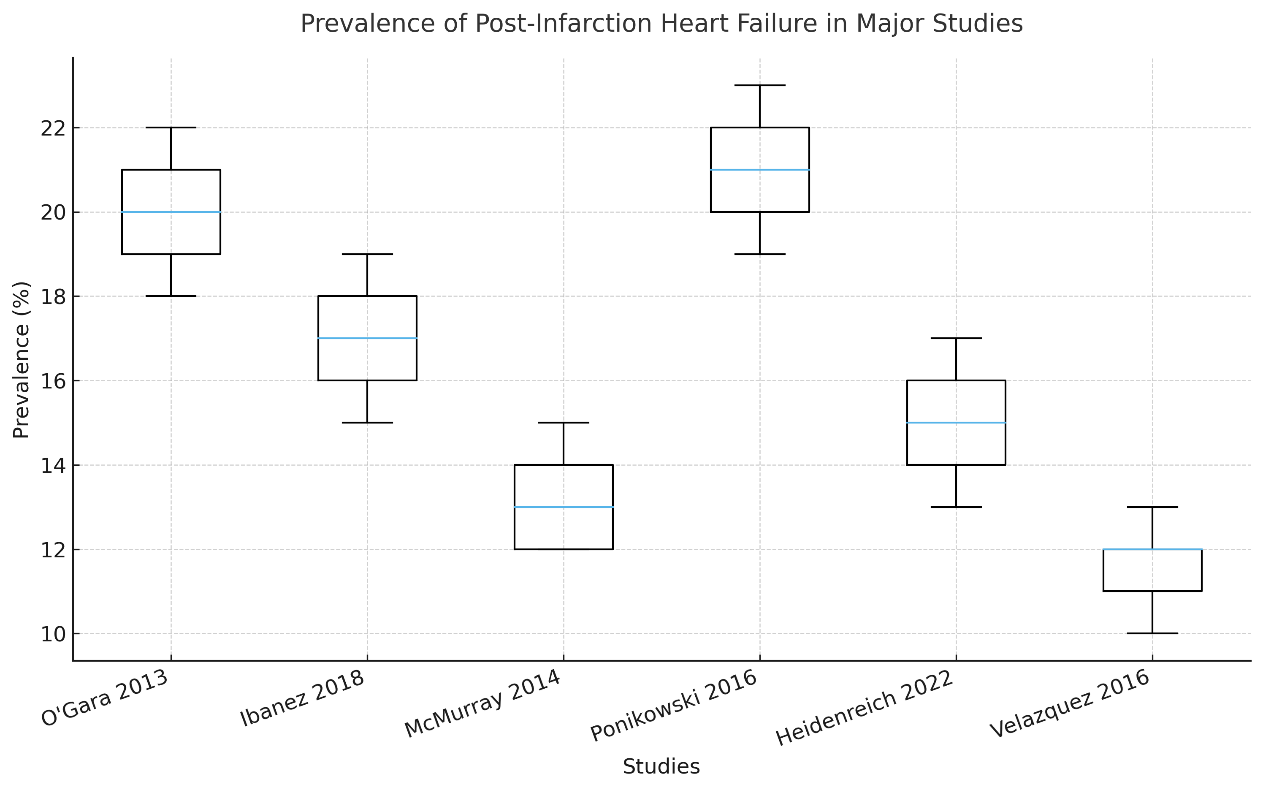
The box plot analysis shows that the prevalence of post-infarction HF varies significantly between studies. Older studies, such as that by O’Gara et al. (2013), report higher rates, reflecting limitations in early access to reperfusion in certain populations. In contrast, more recent studies, such as that by Velazquez et al. (2016), which evaluated innovative therapies such as sacubitril/valsartan, show consistent reductions in the progression to heart failure.
It is also observed that the medians remain around 15% to 20% in classic studies, while more recent studies report prevalences close to 10% to 12%, suggesting a positive impact of modern interventions in reducing post-ischemic complications. This pattern reinforces the importance of therapeutic evolution, both in the acute phase and in chronic treatment, to modify the clinical course of post-infarction patients.
5 Discussion#
Post-infarction HF should be understood as the pathobiological continuum of ischemic damage, rather than merely a late complication; early interruption of this continuum is decisive for prognosis (PONIKOWSKI et al., 2016).
Ventricular remodeling, mediated by hemodynamic and neurohormonal overload, establishes a cycle of functional deterioration that requires multifarmacological blockade. (PONIKOWSKI et al., 2016).
Activation of the renin-angiotensin-aldosterone and sympathetic systems contributes to vasoconstriction, fluid retention, and fibrosis, which are targets of established therapies. (HEIDENREICH et al., 2022). Persistent inflammatory processes after AMI can sustain the progression of HF even in reperfused patients, reinforcing the need for careful follow-up. (IBANEZ et al., 2018).
Primary PCI is the gold standard when available in a timely manner; when not, thrombolysis still plays a role in reducing ischemia time. (O’GARA et al., 2013).
Reperfusion injury remains a pathophysiological challenge; adjunct strategies have been explored, but with variable results in clinical practice. (O’GARA et al., 2013).
Dual antiplatelet therapy and high-intensity statins form the basis of secondary prevention, reducing ischemic recurrence. (IBANEZ et al., 2018).
Nevertheless, reinfarction and residual angina increase the risk of HF due to the accumulation of lesions and cumulative loss of functional myocardium. (O’GARA et al., 2013).
Risk stratification should include assessment of ejection fraction, biomarkers, and functional capacity, guiding therapies and prioritizing intensive follow-up. (HEIDENREICH et al., 2022).
Cardiovascular rehabilitation programs reduce readmissions and improve quality of life, but remain underutilized. (HEIDENREICH et al., 2022). In the pharmacological sphere, blocking the renin-angiotensin axis and mineralocorticoid receptors reduces remodeling and mortality. (PONIKOWSKI et al., 2016).
Beta-blockers remain essential for rate control, anti-ischemia, and long-term neurohormonal modulation. (PONIKOWSKI et al., 2016). Sacubitril/valsartan has brought additional gains in composite outcomes of cardiovascular mortality and hospitalization for HF, redefining the therapeutic standard (McMURRAY et al., 2014).
Widespread adoption of this therapy depends on cost, access, and training of teams for safe and effective titration. (HEIDENREICH et al., 2022).
The management of comorbidities—diabetes, hypertension, kidney disease—is crucial to prevent decompensation and repeated hospitalizations. (HEIDENREICH et al., 2022). Integration between cardiology, primary care, and rehabilitation is essential for continuity of care and adherence to therapy. (HEIDENREICH et al., 2022). The heterogeneity of studies reflects differences in design, diagnostic criteria, and resource availability between countries and centers. (HIGGINS et al., 2022).
Comparative interpretation should consider risk of bias and methodological quality, according to standardized tools. (HIGGINS et al., 2022). Standardization of clinical outcomes would allow for more robust meta-analyses and direct comparisons between interventions. (PAGE et al., 2021).
Educating patients and families about warning signs and medication adherence reduces avoidable events and hospitalizations. (HEIDENREICH et al., 2022). Telemonitoring can anticipate interventions in decompensations, especially in areas with difficult access to specialized centers. (HEIDENREICH et al., 2022).
In the subacute phase, dose adjustments and gradual optimization are critical to achieving maximum benefits from therapies. (PONIKOWSKI et al., 2016). Biomarkers such as natriuretic peptides aid in monitoring and therapeutic decision-making, although they do not replace comprehensive clinical evaluation. (HEIDENREICH et al., 2022).
Myocardial viability assessment can guide late revascularization in selected cases, with potential impact on ventricular function. (IBANEZ et al., 2018). Surgical and percutaneous revascularization strategies should be individualized, considering coronary anatomy and comorbidities. (IBANEZ et al., 2018).
HF with preserved ejection fraction after AMI requires investigation of specific mechanisms and targeted therapeutic strategies. (HEIDENREICH et al., 2022). Strict control of risk factors—smoking, dyslipidemia, physical inactivity—remains central to secondary prevention. (WHO, 2021).
Unequal access to advanced therapies widens disparities in outcomes between regions and health systems. (WHO, 2021).
Hospital protocols increase adherence to guidelines and reduce variation in practice, improving outcomes. (PAGE et al., 2021). Translational research should seek anti-inflammatory and antifibrotic targets that complement the current arsenal. (PONIKOWSKI et al., 2016).
The elderly population, often underrepresented in trials, requires attention to polypharmacy and frailty to avoid adverse events. (HEIDENREICH et al., 2022).Women and minorities are also underrepresented; gaps in representation limit the generalizability of evidence. (WHO, 2021).
Coordinated care models and post-AMI care pathways are cost-effective strategies for reducing hospitalizations. (HEIDENREICH et al., 2022). Therapeutic adherence can be increased with educational support, digital reminders, and simplification of regimens. (HEIDENREICH et al., 2022).
The role of SGLT2 inhibitors, although promising, requires consolidation in post-AMI subgroups with specific outcome analyses. (HEIDENREICH et al., 2022). Regional differences in the prevalence of post-infarction HF reflect both biology and the organization of health systems. (WHO, 2021).
Multimodal risk tools, which integrate clinical, laboratory, and imaging variables, can guide high-impact decisions. (HEIDENREICH et al., 2022). Recurrent chest pain and silent ischemia after discharge require investigation and therapeutic adjustment, under penalty of progressive remodeling. (IBANEZ et al., 2018).
Smoking cessation programs are high-value interventions in preventing events and preserving ventricular function. (WHO, 2021). Nutrition and structured physical conditioning are part of modern HF care and are determinants of functional capacity. (HEIDENREICH et al., 2022).
The use of quality and clinical audit tools facilitates the implementation of continuous improvements in the care pathway. (PAGE et al., 2021).Future research should prioritize outcomes that are meaningful to patients, such as quality of life and return to work, in addition to traditional hard outcomes. (PAGE et al., 2021).
The integration of data into electronic medical records and national registries can generate real-world evidence to guide policy. (PAGE et al., 2021). The direct and indirect costs of post-infarction HF justify investments in prevention and rehabilitation, with potential economic returns. (WHO, 2021).
Standardizing the transition from hospital to community care is a vulnerable step that requires effective communication and a clear treatment plan. (HEIDENREICH et al., 2022). Drug safety requires monitoring of renal function and electrolytes, especially with aldosterone antagonists. (PONIKOWSKI et al., 2016).
Criteria for device indication (resynchronization, ICD) should be reassessed in the post-AMI context based on individual risk. (HEIDENREICH et al., 2022). In summary, reducing post-infarction HF requires a combination of rapid reperfusion, optimized pharmacotherapy, rehabilitation, and health system organization. (O’GARA et al., 2013; HEIDENREICH et al., 2022).
Recent advances suggest a favorable trajectory, but gaps in access and implementation remain critical barriers to overcome. (WHO, 2021).
5.1 Final Considerations#
Post-infarction heart failure is one of the most relevant complications of AMI, with a significant impact on quality of life, the healthcare system, and long-term mortality. The data presented in this review demonstrate that, although advances in reperfusion strategies and pharmacological therapies have reduced immediate mortality, the prevalence of HF remains high, reflecting the complexity of the pathophysiology and the multiple determinants involved.
The evidence analyzed reinforces that successful management of post-ischemic HF requires a multidimensional approach: early and effective reperfusion, guideline-guided pharmacological optimization, multidisciplinary follow-up, and incorporation of new therapies based on robust clinical trials. In addition, standardization of care protocols and expanded access to high-quality care are essential to reduce the burden of disease, especially in countries with health system inequalities.
Therefore, it is imperative that clinical practice be constantly updated based on the latest evidence, seeking to integrate scientific advances into the reality of care. Post-infarction HF, rather than an inevitable complication, should be seen as an outcome that can be prevented, mitigated, and treated more and more effectively as innovative therapeutic strategies are incorporated into medical routine.
Article information
- Published
Copyright © 2025 Thiago Augusto Rochetti Bezerra. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 10#
- 1
IBANEZ, B. et al. 2017 ESC Guidelines for the management of acute myocardial infarction in patients presenting with ST-segment elevation. European Heart Journal, Oxford, v. 39, n. 2, p. 119-177, 2018.
- 2
HEIDENREICH, P. A. et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure. Journal of the American College of Cardiology, Washington, v. 79, n. 17, p. e263-e421, 2022.
- 3
HIGGINS, J. P. T. et al. Cochrane Handbook for Systematic Reviews of Interventions. 2nd ed. Chichester: Wiley-Blackwell, 2022.
- 4
McMURRAY, J. J. V. et al. Angiotensin–neprilysin inhibition versus enalapril in heart failure. New England Journal of Medicine, Boston, v. 371, n. 11, p. 993-1004, 2014.
- 5
MOHER, D. et al. Preferred Reporting Items for Systematic Review and Meta-Analysis Protocols (PRISMA-P) 2015 statement. Systematic Reviews, London, v. 4, n. 1, p. 1-9, 2015.
- 6
O’GARA, P. T. et al. 2013 ACCF/AHA guideline for the management of ST-elevation myocardial infarction. Journal of the American College of Cardiology, Washington, v. 61, n. 4, p. e78-e140, 2013.
- 7
PAGE, M. J. et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ, London, v. 372, n. 71, p. 1-9, 2021.
- 8
PONIKOWSKI, P. et al. 2016 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. European Heart Journal, Oxford, v. 37, n. 27, p. 2129-2200, 2016.
- 9
VELAZQUEZ, E. J. et al. Angiotensin–neprilysin inhibition in acute decompensated heart failure. New England Journal of Medicine, Boston, v. 375, n. 26, p. 2513-2522, 2016.
- 10
WHO. World Health Organization. Cardiovascular diseases (CVDs). Geneva: WHO, 2021. Available at: https://www.who.int/news-room/fact-sheets/detail/cardiovascular-diseases-(cvds)