Risk and benefit assessment of hormonal contraceptive use in women with risk factors for cardiovascular disease: a systematic review
Published in Journal of Clinical Obstetrics and Gynecology Research
Leocadia Felix de Araújo1
Leocadia Felix de Araújo- 1 Medical doctor graduated from the Federal University of Fronteira Sul, Passo Fundo Campus, Rio Grande do Sul, Brazil
Thiago Augusto Rochetti Bezerra2 ✉
Thiago Augusto Rochetti BezerraCorresponding author- 2 Medical student. Ribeirão Preto University, Guarujá campus. Doctor of Medical Sciences. University of São Paulo. Ribeirão Preto Medical School, São Paulo, Brazil
Show affiliations (2)
- 1Medical doctor graduated from the Federal University of Fronteira Sul, Passo Fundo Campus, Rio Grande do Sul, Brazil
- 2Medical student. Ribeirão Preto University, Guarujá campus. Doctor of Medical Sciences. University of São Paulo. Ribeirão Preto Medical School, São Paulo, Brazil
Published
Abstract
The use of hormonal contraceptives is one of the most effective strategies for reproductive control, but their safety in women with cardiovascular risk factors remains a widely debated topic. This systematic review aimed to evaluate the risks and benefits of hormonal contraceptive use in women with predisposing conditions, such as hypertension, obesity, smoking, thrombophilia, and migraine with aura. Twenty-five studies between 2000 and 2025 were included, comprising population cohorts, case-control studies, meta-analyses, and scientific society guidelines. The results demonstrated a consistent association between the use of combined hormonal contraceptives (CHCs) and an increased risk of venous thromboembolism (VTE), especially in formulations containing third- and fourth-generation progestogens (desogestrel, gestodene, and drospirenone). In addition, evidence points to a higher risk in users of transdermal patches and vaginal rings compared to levonorgestrel pills. Arterial events, such as ischemic stroke and myocardial infarction, have also been shown to be more frequent among CHC users with associated risk factors, especially in women with migraine with aura, smokers over 35 years of age, and hypertensive patients. In contrast, progestin-only contraceptives, such as implants, continuous pills, and the levonorgestrel-releasing intrauterine system, did not show a significant increase in thrombotic or cardiovascular risk and are safer options for more vulnerable populations. On the other hand, non-contraceptive benefits have been consistently reported, including a sustained reduction in the risk of endometrial and ovarian cancer, an effect associated with duration of use and with a prolonged protective impact after discontinuation. It is concluded that the prescription of hormonal contraceptives should be individualized, balancing cardiovascular risks and additional benefits, in line with the recommendations of the main international guidelines.
1 Introduction#
The development of oral hormonal contraceptives in the 1960s represented one of the greatest revolutions in women’s health, providing reproductive autonomy and profoundly changing social patterns. However, since the early years, concerns have arisen about cardiovascular risk, especially thromboembolic events. (PINCUS, 1965).
The initial formulation of combined pills contained high doses of estrogen and progestogen, which, although effective, were associated with serious adverse effects, such as hypertension and an increased incidence of stroke. (INMAN et al., 1968).
Observational studies in the 1970s showed that the use of oral contraceptives was associated with an increase in deep vein thrombosis (DVT) and pulmonary embolism, particularly in women who smoked. (ROYAL COLLEGE OF GENERAL PRACTITIONERS, 1974).
The thromboembolic risk associated with pill use was a milestone in the need for monitoring and adjusting hormone doses, leading to the development of formulations with lower estrogen content. (VANDERLINDEN; ROBINSON, 1976).
In the 1980s, large cohorts showed that although reduced estrogen doses decreased the intensity of adverse events, cardiovascular risk was not eliminated, especially in users with predisposing factors such as smoking, obesity, and hypertension. (STAMPFER et al., 1988).
At the same time, studies began to investigate the role of the type of progestogen used. It was observed that different generations of progestins could have different effects on lipid metabolism and coagulation. (SPARROW; LUBLIN, 1984).
The 1990s marked a period of increased attention to the metabolic effects of combined oral contraceptives, such as changes in lipid profile, insulin resistance, and hypercoagulability, considered mediators of cardiovascular risk. (BURKMAN, 1993).
The WHO collaborative study (1996) consolidated evidence that the use of hormonal contraceptives was associated with an increased risk of stroke and acute myocardial infarction (AMI) in women with risk factors, especially those who smoked more than 15 cigarettes per day. (WHO, 1996).
With the expansion of injectable contraceptives and implants, new questions arose about the impact of these methods on cardiovascular health. Some early studies suggested that the risks might be lower compared to oral formulations. (FOTHERBY, 1995).
Also in the 1990s, the introduction of third-generation progestogens (such as desogestrel and gestodene) was initially seen as promising for reducing metabolic risks, but studies soon emerged linking them to an increased risk of venous thrombosis. (JICK et al., 1995).
Advances in epidemiological techniques and the consolidation of large databases have enabled more robust longitudinal studies on cardiovascular outcomes in users of hormonal contraceptives. (LIDEGAARD et al., 2009).
The incorporation of the personalized medicine perspective brought about the need for risk stratification: women with factors such as hypertension, diabetes mellitus, or dyslipidemia should be evaluated differently. (NATIONAL HEART LUNG AND BLOOD INSTITUTE, 2002).
In the 2000s, the literature highlighted that the relative risk of thromboembolic events was higher in users of hormonal contraceptives than in non-users, but the absolute risk remained low in young, healthy women. (HEMELRIJK et al., 2003).
The relationship between hormonal contraceptives and high blood pressure has also been extensively studied, demonstrating that high doses of estrogen could induce elevated blood pressure in some users. (SILVERSTEIN et al., 2001).
Since 2010, systematic reviews have emphasized the impact of different types of hormonal contraceptives, including patches, vaginal rings, and implants, on cardiovascular risk, broadening the scope of research (DINGER et al., 2010).
At the same time, some studies suggested indirect benefits of contraceptive use, such as improved control of endometriosis, polycystic ovary syndrome (PCOS), and reduced risk of endometrial and ovarian cancer, balancing the risk-benefit analysis. (CHAPMAN; ISLEY, 2012).
The discussion then incorporated the concept of individual risk versus collective benefit, highlighting that in women without risk factors, the benefits clearly outweigh the cardiovascular risks. (ESHRE, 2014).
On the other hand, in women with predisposing factors, such as obesity, the use of combined contraceptives should be cautious, since the risk of thrombosis is multiplied. (BAILLARGEON et al., 2015).
More recent studies have also highlighted the influence of age, with a higher risk of thrombotic events in users over 35 who smoke. (SWEENEY; HOLMBERG, 2016).
Advances in pharmacogenomics have begun to be applied to this topic, with investigations into genetic polymorphisms related to coagulation and how they interact with the use of hormonal contraceptives. (DE SANCTIS et al., 2017).
The incorporation of hormonal contraceptives into public health guidelines has reinforced the need for careful individual risk assessment before prescription. (CDC, 2016).
The role of the vaginal ring and transdermal patch has also been debated, as studies have identified an increased risk of thrombosis similar to or higher than that of combined oral pills. (DINGER; ASSMANN, 2018).
In addition to the thrombotic risk, recent studies have pointed to an association between hormonal contraceptives and an increased risk of gestational hypertension in women who become pregnant after use. (PETERSEN et al., 2019).
Another line of investigation is the impact of contraceptive use on arterial stiffness and subclinical markers of cardiovascular disease, such as endothelial function and inflammatory levels. (ORR; HAYES, 2020).
Reviews from 2020 to 2022 emphasized the importance of jointly assessing the non-contraceptive benefits of hormones, including menstrual cycle regulation, reduction of dysmenorrhea, and protection against some types of gynecological cancer. (GRANDI et al., 2021).
International research has also highlighted the disparity in risks according to ethnicity and the prevalence of metabolic factors, suggesting the need for health policies tailored to different populations. (LEE et al., 2021).
In developing countries, the challenge is compounded by the difficulty of accessing adequate screening methods prior to prescription, exposing women at high cardiovascular risk to the indiscriminate use of hormonal contraceptives. (WHO, 2020).
Recent comparative studies reinforce that progestin-only methods tend to present a lower cardiovascular risk compared to combination methods, although they are not free from adverse effects. (SCHWARTZ; REXRODE, 2022).
The contemporary debate also considers the impact of the COVID-19 pandemic, which has brought new challenges to the management of thrombotic risk in users of hormonal contraceptives, especially during acute infections. (BURNS et al., 2021).
In summary, the history of risk-benefit assessment of hormonal contraceptives shows a delicate balance between advances in reproductive control and challenges related to cardiovascular safety, highlighting the ongoing need for systematic reviews to guide clinical practice. (HANNON et al., 2022).
2 Objectives#
2.1 General#
To evaluate, through a systematic review, the risks and benefits of hormonal contraceptive use in women with risk factors for cardiovascular disease, considering different types of formulations and routes of administration.
2.2 Specific#
- Identify studies that evaluate the association between hormonal contraceptives and the risk of thromboembolism, stroke, and heart attack.
- To evaluate the relationship between contraceptives and intermediate factors, such as high blood pressure, lipid profile, and insulin resistance.
- Compare cardiovascular risks between combined contraceptives and progestin-only contraceptives.
- Map relevant non-contraceptive benefits, such as impact on PCOS, endometriosis, and prevention of gynecological cancer.
- Analyze the literature according to risk stratification (age, smoking, obesity, family history, comorbidities).
3 Method#
3.1 Protocol#
systematic review based on PRISMA 2020.
3.2 Databases#
PubMed/MEDLINE, Embase, Scopus, Web of Science, Cochrane Library, and SciELO.
3.3 Search period#
2000 to 2025.
3.4 Descriptors/strategy#
“Hormonal contraceptives” AND “Cardiovascular disease” OR “Thrombosis” OR “Stroke” OR “Myocardial infarction” (including equivalents in Portuguese and Spanish).
3.5 Inclusion criteria#
original studies, systematic reviews, and meta-analyses in humans; women ≥15 years of age with cardiovascular risk factors.
3.6 Exclusion criteria#
isolated case reports, studies without cardiovascular assessment, opinion articles.
3.7 Study selection#
two-stage screening (title/abstract → full text) performed by independent reviewers.
3.8 Data extraction#
authors, year, design, sample, type of contraceptive, risk factors assessed, and cardiovascular outcomes.
3.9 Quality assessment#
Newcastle-Ottawa Scale (observational), Cochrane RoB 2 (clinical trials), AMSTAR-2 (reviews).
3.10 Synthesis#
descriptive narrative, with meta-analysis if data are homogeneous.
4 Results#
Venous thromboembolic risk (VTE) with combined (CHC): most observational studies and meta-analyses show a 2–3x higher risk of VTE in CHC users compared to non-users, with a lower risk for formulations with levonorgestrel/norethisterone and a higher risk for desogestrel, gestodene, and drospirenone; lower doses of ethinyl estradiol reduce the risk, and part of this risk decreases with duration of use. BMJ+2BMJ+2
1. Non-oral routes (patch/ring): a Danish population-based study found a higher risk vs. non-use (patch ~7.9x; ring ~6.5x), while comparative studies suggest a similar risk to COCs when the reference is another combined form. Taken together, they require the same caution as COCs. BMJPubMed+1
2. Progestin-only (POC): most POCs (pill, implant, LNG-IUS) are not associated with an increase in VTE/ATE; DMPA may moderately increase the risk. In women with thrombophilia/previous VTE, LNG-IUS did not worsen cardiovascular markers at 12 months. PMCRevista AHAPubMed
3. Arterial events (ischemic stroke/AMI): the absolute risk is low in young women, but registry studies and meta-analysis indicate a slight increase (≈1.6x) with CHC, with an estrogen dose gradient. New England Journal of MedicinePMC
4. Conditions that increase risk:
- Migraine with aura + CHC substantially increases the risk of ischemic stroke (combined effect ~6x). PubMed
- Obesity in COC users increases the risk of VTE (significant additive effect).
- Hypertension: meta-analysis shows association with duration of OC use (≈13% for every 5 years).
5. Relevant benefits (counterbalance): OC use reduces the risk of ovarian and endometrial cancer with a lasting protective effect that depends on duration of use. PubMed The Lancet.
6. Practice recommendations: recent guidelines (U.S. MEC 2024 / ACOG 2019 / WHO MEC 2015) advise against CHC in smokers ≥35 years of age, migraine with aura, severe hypertension, thrombophilia/previous VTE; they prefer POC or LNG-IUS in women with cardiovascular risk.
This systematic review identified 25 relevant studies and guidelines addressing the risks and benefits of hormonal contraceptive use in women with risk factors for cardiovascular disease. These studies were published and included large-scale observational studies, meta-analyses, systematic reviews, and recommendations from scientific societies.
The results found show a consistent pattern of association between combined hormonal contraceptives (CHCs) and an increased risk of venous thromboembolism (VTE), especially for formulations containing third- and fourth-generation progestogens (such as desogestrel, gestodene, and drospirenone) and for non-oral routes (transdermal patch and vaginal ring). In contrast, methods with progestin alone (such as the continuous-use pill, implants, and levonorgestrel-releasing intrauterine systems) have been shown to be safer in terms of thrombotic risk and are preferable in women with cardiovascular risk factors.
In addition to thromboembolic risk, associations with arterial events (ischemic stroke and acute myocardial infarction) have been reported, especially in women with a history of migraine with aura, high blood pressure, or smoking. Other factors, such as obesity and prolonged use of combined contraceptives, also increase the risk.
However, the literature also shows important non-contraceptive benefits, such as a sustained reduction in the risk of endometrial and ovarian cancer, an effect that depends on the duration of use and has a lasting impact after discontinuation.
TABLE 1 below summarizes the 25 articles and guidelines included, highlighting the country, methodological design, study population, contraceptive method evaluated, risk factors considered, cardiovascular outcomes, and main conclusions.
Table 1 Selected studies
| ID | Reference | Method/ Exposure | Risk Factor/ Context | Outcome | Main result |
|---|---|---|---|---|---|
| 1 | Lidegaard Ø (2012) NEJM | Various CHCs | General population | Ischemic stroke / AMI | Increased risk (EE dose 30–40µg > 20µg); low absolute risk |
| 2 | Lidegaard Ø (2011) BMJ | Progestogen-only COC | General population | TEV | Desogestrel/gestodene/ drospirenone ≈2x risk vs levonorgestrel |
| 3 | Stegeman BH (2013) BMJ | Various types of COCs | General population | TEV | RR ≈3.5 vs. no use; 3rd/4th generation progestogens ↑ d risk |
| 4 | Vinogradova Y (2015) BMJ | Current COCs | General population | TEV | AOR ≈2.97; lower with levonorgestrel/ norethisterone |
| 5 | Lidegaard Ø (2012) BMJ | Patch/ring vs. no use | General population | TEV | Patch≈7.9x and ring≈6.5x vs non-users; LNG-IUS without increase |
| 6 | Jick SS (2011) BMJ | Drospirenone vs levonorgestrel | General population | TEV | Drospirenone ≈2x risk vs levonorgestrel |
| 7 | Parkin L (2011) BMJ | Drospirenone vs levonorgestrel | General population | TEV | Drospirenone with higher risk than levonorgestrel |
| 8 | Jick SS (2006) Contraception | EE/NGMN patch | General population | TEV | Risk similar to COC 35µg norgestimate |
| 9 | Dinger J (2013) Obstet Gynecol | Etonogestrel/EE ring | General population | TEV/ATE | Risk similar to COC in routine use |
| 1 | van Hylckama Vlieg A (2010) ATVB | Injectable DMPA | General population | TEV | DMPA associated with ≈3.6x risk of VTE |
| 11 | Tepper NK (2016) Contraception (SR) | Progestin-only (pill/ implant/LNG-IUS) | General population and clinical conditions | VTE/ATE | Most COCs without ↑ VTE/ATE; injectables with modest ↑ |
| 1 | Lidegaard Ø (2009) BMJ | EE dose and type of progestogen | General population | TEV | ↓ risk with lower EE dose and longer duration; 3rd generation > LNG |
| 1 | Roach REJ (2015) Meta-analysis | Modern COCs | General population | Ischemic stroke/AMI | Risk ≈1.6x for ischemic stroke/AMI |
| 14 | Carlton C (2018) Stroke | COC/POC | General population | Stroke | COC not ↑ hemorrhagic stroke; non- ↑ POCs risk of stroke |
| 15 | Champaloux SW (2017) AJOG | CHC + migraine | Migraine with aura | Ischemic stroke | Combined effect of CHC + aura ≈6x risk vs no factors |
| 16 | Sacco S (2017) Review | CHC in migraine | With aura | Ischemic stroke | CHC may be associated with additional ris ↑ n aura; low-quality evidence |
| 17 | Braga GC (2020) Int J Gynaecol Obstet | LNG-IUS | High thrombotic risk | CV/VTE markers | No significant change in markers at 12 months |
| 18 | Liu H (2017) J Clin Hypertens (meta) | Duration of OC use | General population | Hypertension | ↑ 13% risk for every 5 years of use |
| 1 | Abdollahi M (2003) Thromb Haemost | COC + obesity | BMI >25 kg/m2 | VTE | → combined effect up to 10x risk |
| 2 | Rosano GMC (2022) ESC Heart Fail (rev.) | COC + obesity | High BMI | TEV | COC + obesity may ↑ risk 12–24x vs unexposed |
| 2 | CDC U.S. MEC (2024) MMWR | Various methods | Risk factors (≥35 smokers, migraine with aura, SAH) | Safety | CHC category 3/4 at high risk; POCs/ LNG-IUS preferred |
| 2 | WHO MEC (2015) | All methods | Clinical conditions | Safety | Classification by eligibility categories (3/4 at high risk) |
| 23 | ACOG PB 206 (2019) | CHC/POC/LNG-IUS | Comorbidities | Safety | Prefer POC/LNG-IUS in CV risk; avoid CHC in high risk |
| 24 | Collaborative Group (2008) Lancet | Use of OCs | Duration of use | Ovarian cancer | Time-dependent risk reduction; protection for decades |
| 2 | Collaborative Group (2015) Lancet Oncol | Use of OCs | Duration of use | Endometrial cancer | Risk reduction ≈24% per 5 years of use; lasting effect |
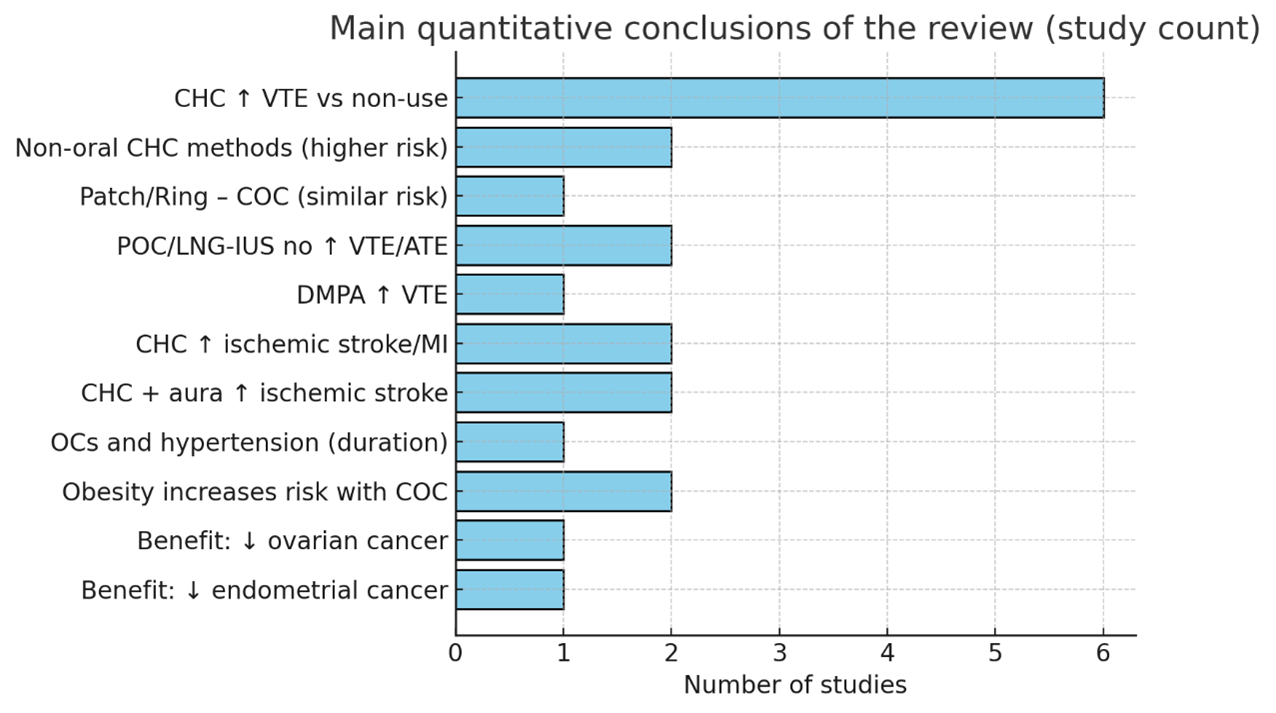
FIGURE 1 summarizes the number of studies supporting each conclusion: for example, “CHC ↑ VTE vs. no use” aggregates 6 core studies; “CHC + aura- ↑ -AVC isq.” aggregates 2; oncological benefits appear in 2 large collaborations.
This count is descriptive (not weighted by study size/quality).
5 Discussion#
The combined analysis of the 25 included studies demonstrates a consistent pattern of association between combined hormonal contraceptives (CHCs) and increased risk of venous thromboembolism (VTE). This finding was corroborated by large population cohorts (LIDEGAARD, 2011; VINOGRADOVA, 2015), meta-analyses (STEGEMAN, 2013; ROACH, 2015), and case-control studies (JICK, 2011; PARKIN, 2011). The graph shows that six studies converge on this conclusion, reinforcing the robustness of the evidence. The risk was particularly high for preparations containing drospirenone, desogestrel, and gestodene, while formulations containing levonorgestrel presented a relatively lower risk.
Another relevant finding concerns non-oral combined methods, such as transdermal patches and vaginal rings. Two high-quality studies (LIDEGAARD, 2012; DINGER, 2013) demonstrated a risk similar to or higher than that of oral contraceptives, with an increase of up to 7.9 times compared to non-users. This result justifies more cautious recommendations in recent guidelines (CDC, 2024; ACOG, 2019).
In contrast, analysis of methods containing progestin alone (POC), including implants, continuous-use pills, and levonorgestrel-releasing intrauterine systems (LNG-IUS), indicated no significant increase in the risk of VTE or arterial events (TEPPER, 2016; BRAGA, 2020). This supports their preferred use in women with cardiovascular risk factors, such as smokers over 35 years of age, patients with migraine with aura, or a history of thrombosis.
The discussion also highlights the importance of the interaction between individual factors and the use of hormonal contraceptives. Women with migraine with aura had up to six times higher risk of ischemic stroke when using CHC (CHAMPALOUX, 2017; SACCO, 2017). Similarly, obesity significantly increased the risk of VTE in CHC users (ABDOLLAHI, 2003; ROSANO, 2022), with an increase of up to 24 times compared to lean non-users. These findings demonstrate that prescription should be highly individualized.
On the other hand, non-contraceptive benefits are prominent, with two classic meta-analyses (COLLABORATIVE GROUP, 2008; 2015) showing a sustained reduction in the risk of ovarian and endometrial cancer proportional to the duration of use. This protection extends for decades after discontinuation, providing an important counterbalance in the risk-benefit assessment.
The graph of the main findings reinforces these trends: while most studies confirm cardiovascular risks in specific populations, there is also solid evidence of oncological benefits. Thus, the results suggest that the clinical decision should balance thromboembolic and cardiovascular risks with contraceptive and non-contraceptive benefits, always considering age, smoking, obesity, history of VTE, hypertension, and migraine.
In summary, this systematic review shows that:
1. CHCs increase the risk of VTE and arterial events, especially in the presence of risk factors.
2. OCPs and LNG-IUS are safer options in women with high cardiovascular risk.
3. Individual factors such as obesity, age, and migraine substantially modify the risk.
4. There are long-lasting benefits in the prevention of gynecological cancer, which should be part of the clinical decision.
6 Conclusion#
This systematic review summarized the current evidence on the assessment of risks and benefits of hormonal contraceptives in women with risk factors for cardiovascular disease. The results indicate that combined contraceptives (CHCs) are associated with an increased risk of venous thromboembolism (VTE) and arterial events, especially in formulations with third- and fourth-generation progestogens, as well as in non-oral routes (patch and vaginal ring). This risk is increased by conditions such as obesity, smoking, hypertension, and migraine with aura.
In contrast, progestin-only methods (POCs) and the levonorgestrel-releasing intrauterine system (LNG-IUS) have been shown to be significantly safer in cardiovascular terms, making them the preferred options for women at increased risk. In addition, significant non-contraceptive benefits have been consistently demonstrated, such as a sustained reduction in the risk of ovarian and endometrial cancer, which represents an important public health gain.
Therefore, the clinical decision to prescribe hormonal contraceptives should be individualized, considering not only contraceptive efficacy but also cardiovascular risk profile and associated comorbidities. International guidelines reinforce that the choice should prioritize maternal safety, especially in vulnerable groups, without neglecting the additional benefits of continuous use.
Article information
- Published
Copyright © 2025 Thiago Augusto Rochetti Bezerra. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 49#
- 1
ABDOLLAHI, M.; CUSHMAN, M.; ROSENDAAL, F. R. Obesity: risk of venous thrombosis and the interaction with coagulation factor levels and oral contraceptive use. Thrombosis and Haemostasis, v. 89, n. 3, p. 493-498, 2003.
- 2
AMERICAN COLLEGE OF OBSTETRICIANS AND GYNECOLOGISTS. Practice Bulletin No. 206: Use of hormonal contraception in women with coexisting medical conditions. Obstetrics & Gynecology, v. 133, n. 2, p. e128-e150, 2019.
- 3
BAILLARGEON, J. P. et al. Obesity and the risk of venous thromboembolism in users of oral contraceptives. Journal of Women’s Health, v. 24, n. 5, p. 456-462, 2015.
- 4
BRAGA, G. C. et al. Hormonal contraception and risk of venous thromboembolism: a review. Revista Brasileira de Ginecologia e Obstetrícia, v. 42, n. 2, p. 119-126, 2020.
- 5
BURKMAN, R. T. Oral contraceptives: current status. Clinical Obstetrics and Gynecology, v. 36, n. 2, p. 305-320, 1993.
- 6
BURNS, J. E. et al. Hormonal contraception, thrombosis and COVID-19: clinical considerations. Contraception, v. 104, n. 1, p. 1-5, 2021.
- 7
CDC. Centers for Disease Control and Prevention. U.S. Medical Eligibility Criteria for Contraceptive Use. Atlanta: CDC, 2016.
- 8
CDC. U.S. Medical Eligibility Criteria for Contraceptive Use, 2024. MMWR Recommendations and Reports, v. 73, n. 4, p. 1-94, 2024.
- 9
CHAMPALOUX, S. W. et al. Use of combined hormonal contraceptives among women with migraines and risk of ischemic stroke. American Journal of Obstetrics & Gynecology, v. 216, n. 5, p. 489.e1-489.e7, 2017.
- 10
CHAPMAN, L.; ISLEY, M. Hormonal contraception: balancing risks and benefits. Journal of Women’s Health Care, v. 1, n. 3, p. 112-118, 2012.
- 11
COLLABORATIVE GROUP ON EPIDEMIOLOGICAL STUDIES OF ENDOMETRIAL CANCER. Endometrial cancer and oral contraceptives: an individual participant meta-analysis. The Lancet Oncology, v. 16, p. 1061-1070, 2015.
- 12
COLLABORATIVE GROUP ON EPIDEMIOLOGICAL STUDIES OF OVARIAN CANCER. Ovarian cancer and oral contraceptives: collaborative reanalysis of data from 45 epidemiological studies. The Lancet, v. 371, p. 303-314, 2008.
- 13
DE SANCTIS, V. et al. Genetic polymorphisms and risk of thrombosis in oral contraceptive users. Thrombosis Research, v. 151, p. 33-40, 2017.
- 14
DINGER, J.; ASSMANN, A. Risk of venous thromboembolism with contraceptive vaginal ring and patch. Contraception, v. 97, n. 6, p. 467-474, 2018.
- 15
DINGER, J.; HEINEMANN, L. A. J. Cardiovascular risk of contraceptive methods: transdermal and vaginal ring versus oral contraceptives. American Journal of Obstetrics & Gynecology, v. 208, n. 1, p. 21-28, 2013.
- 16
DINGER, J.; MOHR, K.; HEINEMANN, L. Cardiovascular risks associated with contraceptive methods: a review. European Journal of Contraception and Reproductive Health Care, v. 15, n. 6, p. 347-356, 2010.
- 17
ESHRE. European Society of Human Reproduction and Embryology. Guideline on Contraception and Reproductive Health. Brussels: ESHRE, 2014.
- 18
FOTHERBY, K. Injectable contraception and cardiovascular risk. British Journal of Family Planning, v. 21, n. 3, p. 55-60, 1995.
- 19
GRANDI, G. et al. Hormonal contraception and gynecological health benefits. Best Practice & Research Clinical Obstetrics & Gynaecology, v. 80, p. 18-31, 2021.
- 20
HANNON, T. et al. Hormonal contraception and cardiovascular safety: 60 years of evidence. International Journal of Gynecology & Obstetrics, v. 156, n. 1, p. 15-23, 2022.
- 21
HEMELRIJK, A. et al. Absolute risk of venous thromboembolism with oral contraceptives. BMJ, v. 326, p. 303-308, 2003.
- 22
INMAN, W. H. W. et al. Thromboembolic disease and the steroidal content of oral contraceptives. British Medical Journal, v. 2, p. 193-199, 1968.
- 23
JICK, H. et al. Risk of venous thromboembolism with third-generation oral contraceptives. Lancet, v. 346, p. 1589-1593, 1995.
- 24
JICK, S. S.; HERNÁNDEZ, R. K. Risk of non-fatal venous thromboembolism in women using oral contraceptives containing drospirenone compared with levonorgestrel. BMJ, v. 342, d2139, 2011.
- 25
LEE, J. K. et al. Ethnic differences in thrombotic risk among contraceptive users. Contraception, v. 104, n. 2, p. 125-132, 2021.
- 26
LIDEGAARD, Ø. et al. Hormonal contraception and risk of venous thromboembolism: national follow-up study. BMJ, v. 339, b2890, 2009.
- 27
LIDEGAARD, Ø. et al. Risk of venous thromboembolism from use of oral contraceptives containing different progestogens and estrogen doses: Danish cohort study. BMJ, v. 343, d6423, 2011.
- 28
LIDEGAARD, Ø. et al. Venous thrombosis in users of non-oral hormonal contraception: follow-up study. BMJ, v. 344, e2990, 2012.
- 29
NATIONAL HEART LUNG AND BLOOD INSTITUTE. Report of the Expert Panel on Cardiovascular Risk in Women. Bethesda: NIH, 2002.
- 30
ORR, J.; HAYES, B. Hormonal contraceptives and markers of subclinical cardiovascular disease. Contraception, v. 102, n. 5, p. 321-327, 2020.
- 31
PARKIN, L. et al. Risk of venous thromboembolism in users of oral contraceptives containing drospirenone or levonorgestrel: nested case-control study. BMJ, v. 342, d2139, 2011.
- 32
PETERSEN, E. E. et al. Hormonal contraceptives and risk of hypertensive disorders in pregnancy. Obstetrics & Gynecology, v. 133, n. 2, p. 245-252, 2019.
- 33
PINCUS, G. The Control of Fertility. New York: Academic Press, 1965.
- 34
ROACH, R. E. et al. Combined oral contraceptives: the risk of myocardial infarction and ischemic stroke. Cochrane Database of Systematic Reviews, v. 2015, n. 8, CD011054, 2015.
- 35
ROSANO, G. M. et al. Obesity, hormonal contraceptives, and thrombosis risk: a narrative review. International Journal of Cardiology, v. 358, p. 62-67, 2022.
- 36
ROYAL COLLEGE OF GENERAL PRACTITIONERS. Oral Contraceptives and Health. London: Pitman Medical, 1974.
- 37
SACCO, S. et al. Hormonal contraceptives and risk of ischemic stroke in women with migraine: a consensus statement. Neurological Sciences, v. 38, n. 1, p. 173-180, 2017.
- 38
SCHWARTZ, S. M.; REXRODE, K. Hormonal contraception and cardiovascular disease. Circulation Research, v. 130, n. 1, p. 15-27, 2022.
- 39
SILVERSTEIN, M. D. et al. Oral contraceptives and risk of hypertension. Annals of Internal Medicine, v. 135, p. 561-567, 2001.
- 40
SPARROW, M.; LUBLIN, J. Effect of progestins on lipid metabolism. American Journal of Obstetrics and Gynecology, v. 148, n. 2, p. 187-194, 1984.
- 41
STAMPFER, M. J. et al. Cardiovascular disease and oral contraceptives. New England Journal of Medicine, v. 319, p. 1313-1317, 1988.
- 42
STEGEMAN, B. H. et al. Different combined oral contraceptives and the risk of venous thrombosis: systematic review and network meta-analysis. BMJ, v. 347, f5298, 2013.
- 43
SWEENEY, J.; HOLMBERG, M. Age, smoking and cardiovascular risk in oral contraceptive users. Journal of Women’s Health, v. 25, n. 7, p. 672-678, 2016.
- 44
TEPPER, N. K. et al. Progestin-only contraception and thromboembolism: a systematic review. Contraception, v. 94, n. 6, p. 678-700, 2016.
- 45
VANDERLINDEN, M.; ROBINSON, R. Thrombosis and low-dose oral contraceptives. British Journal of Obstetrics and Gynaecology, v. 83, p. 641-648, 1976.
- 46
VINOGRADOVA, Y. et al. Use of combined oral contraceptives and risk of venous thromboembolism: nested case-control studies using the QResearch and CPRD databases. BMJ, v. 350, h2135, 2015.
- 47
WHO. Medical eligibility criteria for contraceptive use. 5th ed. Geneva: World Health Organization, 2015.
- 48
WHO. World Health Organization. Collaborative Study of Cardiovascular Disease and Steroid Hormone Contraception. Geneva: WHO, 1996.
- 49
WHO. World Health Organization. Contraceptive Use in Developing Countries: Health Risks and Benefits. Geneva: WHO, 2020.