Tissue Pharmacokinetics Of Lipid-Based Berberine Formulations: Relevance To Hepatic And Intestinal Exposure
Krathish Bopanna1 ✉
Krathish BopannaCorresponding author- 1 Clinical Pharmacology & Pharmacokinetics, Tejhana, Bengaluru, India
Dinesh KG2
Dinesh KG- 2 PK & PD studies, Radiant Research Pvt Ltd, Bengaluru, India
S Mehkri3
S Mehkri- 3 Product Development, Bio-gen Extracts Pvt Limited, Bengaluru, India
Show affiliations (3)
- 1Clinical Pharmacology & Pharmacokinetics, Tejhana, Bengaluru, India
- 2PK & PD studies, Radiant Research Pvt Ltd, Bengaluru, India
- 3Product Development, Bio-gen Extracts Pvt Limited, Bengaluru, India
Published
Abstract
Berberine, a plant-derived isoquinoline alkaloid, is widely recognised for its hypoglycaemic, hypolipidaemic, and insulin-sensitising effects; however, its clinical application is limited by poor oral bioavailability resulting from poor aqueous solubility, intestinal P-glycoprotein–mediated efflux, and extensive first-pass metabolism. Emerging evidence suggests that berberine’s pharmacological activity may be more closely associated with tissue exposure in metabolically active organs than with systemic plasma concentrations alone. In the present study, the influence of formulation strategies on the plasma pharmacokinetics and tissue distribution of berberine was evaluated using lipid-based and surfactant-assisted formulations. Following oral administration in rats, plasma and tissue concentrations (liver, intestine, and brain) were quantified using a validated LC–MS/MS method, and pharmacokinetic parameters were determined through noncompartmental analysis. Among all formulations, the lipid-encapsulated formulation significantly enhanced tissue exposure, achieving approximately 1.75-fold higher hepatic and 1.60-fold higher intestinal concentrations compared to standard berberine, accompanied by statistically significant increases in systemic exposure. Increased tissue exposure in these metabolically relevant organs may be associated with berberine’s reported effects on hepatic metabolism and intestinal signalling pathways. Despite these improvements, brain concentrations remained low across all formulations, indicating limited penetration across the blood– brain barrier.Overall, the findings support the concept that tissue-specific pharmacokinetics may provide additional insight into understanding berberine’s metabolic activity beyond plasma concentrations alone, and highlight the importance of formulation strategies that enhance organ- specific exposure.
1 Introduction#
Berberine is a naturally occurring isoquinoline alkaloid extracted from medicinal plants such as Berberis aristata, Coptis chinensis, and Hydrastis canadensis. Recently, berberine has attracted scientific interest for its potential to manage metabolic conditions such as type 2 diabetes, dyslipidaemia, and obesity (Feng et al., 2019; Xu et al., 2020). Numerous studies show that berberine improves metabolism by enhancing glucose uptake, decreasing hepatic glucose production, regulating lipid metabolism, and improving insulin sensitivity (Han et al., 2011; Liu et al., 2025). These effects have been associated with activation of AMP-activated protein kinase (AMPK), a crucial cellular energy regulator. When activated, AMPK inhibits hepatic gluconeogenesis, promotes glucose uptake in peripheral tissues, and reduces hepatic lipogenesis (Long, 2006). Additionally, berberine affects cholesterol metabolism by downregulating proprotein convertase subtilisin/kexin type 9 (PCSK9), thereby increasing LDL receptor levels and enhancing LDL cholesterol clearance. Despite these pharmacological benefits, berberine’s pharmacokinetics remain a major challenge due to its poor oral bioavailability (Ai et al., 2021).
A notable aspect of berberine pharmacology is the apparent disconnect between its low systemic bioavailability and its significant metabolic effects. When taken orally, berberine undergoes extensive pre-systemic metabolism, yielding very low plasma levels of the unchanged compound (Kwon et al., 2020; Murakami et al., 2023). Several pharmacokinetic studies report oral bioavailability below 1%, primarily due to poor intestinal permeability, P-glycoprotein-mediated efflux, and substantial first-pass metabolism in the liver and intestinal wall (Murakami et al., 2023). This phenomenon is often referred to as the “berberine bioavailability paradox,” in which pharmacological effects appear disproportionate to circulating plasma concentrations (Cao et al., 2021). Emerging evidence suggests that this paradox may be better explained by organ-specific distribution and tissue exposure rather than plasma concentrations alone (Ai et al., 2021).
Most pharmacokinetic studies measure plasma concentrations to estimate systemic exposure. However, for compounds such as berberine that exert pharmacological effects within specific organs, plasma pharmacokinetics may not accurately reflect biologically relevant tissue exposure (Choi, 2020; Ibarra et al., 2020). Many of berberine's reported metabolic effects are associated with hepatic and intestinal pathways, including AMPK activation, lipid metabolism, and modulation of the gut environment (Ataei et al., 2022; Wang et al., 2022; Yang et al., 2023). Berberine has also been reported to influence gut microbiota composition, intestinal barrier function, and modulate pathways associated with GLP-1 secretion from L-cells. These mechanisms suggest that tissue distribution may provide additional insight into berberine’s metabolic activity beyond plasma concentrations alone.
Traditional berberine formulations face limitations, and various strategies are being explored to improve oral absorption and pharmacokinetic performance (Murakami et al., 2023; Thomas et al., 2021). Lipid-based and surfactant-assisted formulations have shown potential in enhancing the oral absorption of poorly soluble compounds (Mohite et al., 2023).
This study aimed to evaluate how formulation strategies influence the plasma pharmacokinetics and tissue distribution of berberine, with particular emphasis on hepatic and intestinal exposure. By quantifying berberine concentrations in plasma and metabolically relevant tissues, the study sought to determine whether lipid-based formulations could enhance organ-specific exposure and provide further insight into berberine's tissue-centric pharmacokinetic behaviour.
2 Materials and Methods#
2.1 Materials#
All formulations contained berberine hydrochloride as the active ingredient. All solvents used in chromatographic analysis, including acetonitrile and methanol, were of LC–MS grade, and water was purified through a laboratory-grade system. The remaining reagents and chemicals were of analytical grade and used as received.
2.2 Experimental Animals#
All animal experiments strictly followed the ARRIVE 2.0 guidelines for reporting animal research and adhered to national regulations on laboratory animal care and use. The protocol was reviewed and approved by the Institutional Animal Ethics Committee (IAEC), established under CPCSEA regulations of the Government of India. Procedures took place in a CPCSEA-registered facility, with measures to minimise animal suffering and reduce the number of animals used. The animals were housed in standard cages with a 12-hour light– dark cycle and maintained at a consistent temperature and humidity. They had unrestricted access to a standard diet and water during acclimatisation. Before pharmacokinetic testing, animals fasted overnight but had continuous access to water to minimise variability in drug absorption.
2.3 Formulation Design Strategy#
This study aimed to enhance the oral delivery of berberine by modifying its solubility, permeability, and lipid absorption pathways. Berberine's poor water solubility and limited ability to cross the intestinal lining hinder its systemic absorption after oral intake. Additionally, berberine is a substrate for intestinal efflux transporters such as P-glycoprotein, further reducing its bioavailability.
Accordingly, lipid-based and surfactant-assisted formulation approaches were evaluated to assess their influence on plasma pharmacokinetics and tissue distribution of berberine.
2.4 Preparation of Berberine Formulations#
Five distinct berberine formulations were prepared to evaluate the influence of formulation design on pharmacokinetic and tissue distribution behaviour.
- Standard Berberine
- Surfactant-Enhanced Berberine
- Lipid-Enhanced Berberine (Processed)
- Lipid-Enhanced Berberine (Unprocessed)
- Lipid-Encapsulated Berberine (AbsorBerine®)
2.5 Plasma Pharmacokinetic Study#
Animals were randomly assigned to five experimental groups, each comprising eight animals, based on the formulations under investigation. All animals were fasted overnight prior to dosing, with free access to water, to minimise variability in absorption.
Each group received a single oral dose of berberine at 50 mg/ kg body weight, administered via oral gavage. The dosing volume was adjusted according to each animal's body weight to ensure accurate dosing. Following administration of the test formulations, blood samples (approximately 500 µL) were collected from each animal at predefined time intervals: 0 h (pre-dose), 0.25, 0.5, 1, 2, 4, 6, 8, 12, and 24 hours post-dose. Blood samples were collected via an appropriate route (e.g., retro-orbital plexus or tail vein) into pre-labelled microcentrifuge tubes containing an anticoagulant such as EDTA to prevent clotting.
The collected blood samples were immediately processed by centrifugation at 6000 rpm for 20 minutes at a controlled temperature to separate plasma. The clear supernatant (plasma) was carefully transferred into clean, labelled tubes without disturbing the cellular components. All plasma samples were stored at −80 °C until further quantitative analysis. Prior to analysis, samples were thawed under controlled conditions and prepared using validated sample preparation techniques. Plasma concentrations were determined using a suitable and validated analytical method, liquid chromatography–tandem mass spectrometry (LC-MS/ MS), to evaluate pharmacokinetic parameters. Eight animals per group were used for plasma pharmacokinetic analysis.
2.6 Tissue Distribution Study#
At predetermined time points of 8 and 24 hours post-dose, four rats from each experimental group were humanely euthanised in accordance with institutional ethical guidelines. Immediately after euthanasia, vital organs, including the liver, intestine, and brain, were carefully excised for distribution analysis. Collected tissue samples were rinsed thoroughly with ice-cold normal saline to remove residual blood and minimise contamination.
Each tissue sample was then blotted dry, weighed accurately, and transferred into pre-labelled homogenisation tubes. Tissues were homogenised using an appropriate buffer system under controlled conditions to obtain uniform and reproducible tissue homogenates. Homogenisation was carried out using a mechanical homogeniser while maintaining low temperatures to prevent analyte degradation.
Simultaneously, blood samples collected from the animals were processed by centrifugation at 6000 rpm for 20 minutes under controlled temperature conditions to separate plasma. The resulting plasma was carefully collected and stored appropriately for subsequent analysis.
All prepared tissue homogenates and plasma samples were stored under appropriate conditions (e.g., −20°C or −80°C) until further quantitative analysis using LC-MS/MS. Four animals per group were used for tissue distribution analysis at each sampling time point.
2.7 LC–MS/MS Analytical Method#
Berberine levels in plasma and tissue samples were quantified using a validated LC–MS/MS method. Sample preparation involved protein precipitation followed by centrifugation prior to LC–MS/MS analysis. Calibration curves were constructed from standard solutions across a relevant concentration range. The method was validated in accordance with bioanalytical guidelines, confirming linearity, accuracy, precision, and recovery. Only parent berberine concentrations were quantified in the present study.
2.8 Pharmacokinetic and Statistical Analysis#
Plasma concentration–time data were analysed through noncompartmental analysis to derive pharmacokinetic parameters including Cmax, Tmax, elimination half-life, and AUC. Tissue concentrations were reported as mean ± standard deviation. All quantitative data are presented as mean ± standard deviation (SD). Statistical comparisons between groups were performed using one-way ANOVA followed by Tukey’s post hoc test. Relative fold-changes in tissue concentrations were calculated using the standard formulation as the reference group. Pearson correlation analysis was performed to evaluate associations between plasma pharmacokinetic parameters and tissue concentrations. A p-value < 0.05 was considered statistically significant.
2.9 Dose Calculation and Formulation Normalisation#
To enable comparison across different formulations, all treatment groups were adjusted to provide an identical active berberine dose of 50 mg/kg body weight. Because the formulations contained varying amounts of excipients, the total administered mass of each formulation differed slightly between groups. For each formulation, the calculated powder weight was combined with a dosing medium to reach a final volume of 1 mL per animal.
2.10 Bioanalytical Method Validation#
The method for measuring berberine in plasma and tissue samples was validated in accordance with established bioanalytical guidelines. The method demonstrated acceptable linearity, accuracy, precision, sensitivity, and recovery for quantification of berberine in plasma and tissue matrices. A limitation of the study is that metabolite profiling of berberine was not performed due to insufficient sample volume available for analysis.
2.11 Determination of Tissue Concentrations#
Berberine concentrations in tissue samples were expressed as ng/mL tissue homogenate. Mean values are presented for each treatment group at each sampling time point. To facilitate comparison between groups, tissue concentration values were normalised to account for variations in tissue weight and homogenisation volume.
2.12 Correlation Analysis Between Plasma and Tissue Exposure#
To further investigate the connection between systemic exposure and organ-specific drug delivery, a correlation analysis was performed between plasma pharmacokinetic parameters and tissue concentrations.
Pearson correlation coefficients (r) were used to assess the strength of the association between:
- plasma AUC and liver concentration
- plasma AUC and intestinal concentration
- plasma Cmax and tissue concentrations
This analysis aimed to determine whether plasma pharmacokinetic parameters can reliably predict berberine concentrations in key metabolic tissues. Correlation coefficients were interpreted according to standard statistical conventions:
| r value | Interpretation |
|---|---|
| 0.0–0.2 | Very weak correlation |
| 0.2–0.4 | Weak correlation |
| 0.4–0.6 | Moderate correlation |
| 0.6–0.8 | Strong correlation |
| 0.8–1.0 | Very strong correlation |
3 Results#
3.1 Overview of Pharmacokinetic and Tissue Distribution Outcomes#
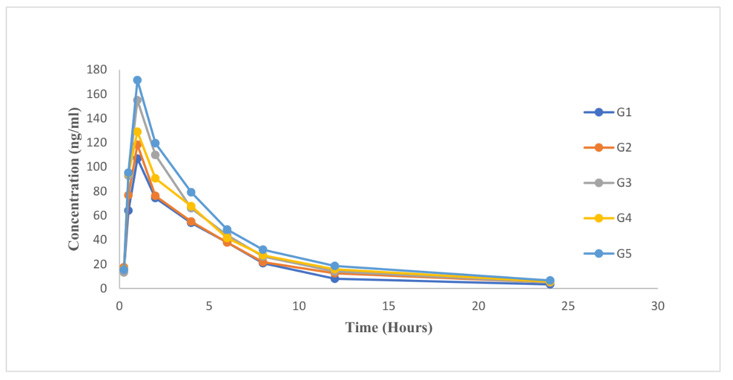
Plasma pharmacokinetic and tissue distribution profiles were assessed across five formulation groups. Distinct formulation-dependent differences were observed in both systemic exposure and organ distribution. Compared with the standard formulation (G1), the lipid-based formulations, particularly G3 and G5, showed higher plasma exposure and greater accumulation in the liver and intestine, with G5 demonstrating the highest concentrations across the measured tissues.
3.2 Plasma Pharmacokinetic Profiles#
After oral administration, plasma concentrations of berberine increased rapidly, with early peak levels observed across all groups. Systemic exposure increased across the formulations, with the lipid-encapsulated formulation (G5) showing the highest plasma Cmax and AUC values, followed by the phospholipid-based formulations (G3 and G4). The surfactant-based formulation (G2) produced a smaller increase relative to G1.
Table 1 Plasma Pharmacokinetic Parameters of Berberine.
| Parameter | G1 Standard | G2 Surfactant | G3 Lipid Processed | G4 Lipid Unprocessed | G5 Lipid Encapsulated |
|---|---|---|---|---|---|
| n | 8 | 8 | 8 | 8 | 8 |
| Cmax (ng/mL) | 106.9±17.1 | 118.2±18.9 | 154.8±24.7 | 128.9±20.6 | 171.4±27.4 |
| Kel (h- 1) | 0.155±0.019 | 0.134±0.016 | 0.148±0.018 | 0.135±0.016 | 0.139±0.017 |
| t½ (h) | 4.51±0.54 | 5.17±0.62 | 4.70±0.56 | 5.14±0.61 | 4.99±0.59 |
| AUC0–t | 548.9±76.8 | 615.7±86.2 | 758.7±106.2 | 730.8±102.3 | 885.3±123.9 |
| AUC0–∞ | 571.0±79.9 | 652.5±91.3 | 792.4±110.9 | 771.6±108.0 | 933.1±130.6 |
| Rel. BA (%) | 100 | 112 | 138 | 133 | 161 |
Plasma pharmacokinetic parameters after oral administration of berberine formulations, normalised to an equivalent dose. The lipid-encapsulated formulation (G5) showed the highest systemic exposure, with statistically significant increases in both Cmax and AUC0–∞ (p < 0.001). Phospholipid-based formulations (G3 and G4) showed intermediate improvements, whereas the surfactant-only formulation (G2) showed relatively modest changes (Table 2).
Elimination parameters (Kel and t½) remained similar across groups, indicating that the formulation mainly affected absorption rather than elimination kinetics. The data indicate a formulation-dependent increase in systemic exposure, with relative bioavailability increasing from 100% in standard berberine to 161% in the lipid-encapsulated formulation.
3.3 Statistical Analysis of Plasma Pharmacokinetics#
One-way ANOVA showed significant differences among formulations for Cmax and AUC0–∞
Table 1.1 One-Way ANOVA Results.
| Parameter | F-statistic | p-value | Interpretation |
|---|---|---|---|
| Cmax | 21.80 | p<0.0001 | Highly significant |
| AUC0–∞ | 14.10 | p<0.0001 | Highly significant |
Tukey’s post hoc test indicated that G3 and G5 showed significantly higher values than G1, while G2 did not differ significantly from G1.
Pairwise comparison of Cmax values across formulations. Lipid-based formulations, especially G3 and G5, showed significant increases compared to the standard formulation. The surfactant-only formulation did not demonstrate a statistically significant improvement.
Table 1.2 Tukey Post-Hoc Results (Cmax).
| Comparison | Mean Difference | p-value | Significance |
|---|---|---|---|
| G1 vs G2 | 11.38 | 0.63 | Not significant |
| G1 vs G3 | 47.95 | <0.001 | Significant |
| G1 vs G4 | 22.03 | 0.09 | Not significant |
| G1 vs G5 | 64.57 | <0.001 | Highly significant |
| G2 vs G3 | 36.57 | 0.003 | Significant |
| G2 vs G4 | 10.65 | 0.68 | Not significant |
| G2 vs G5 | 53.19 | <0.001 | Highly significant |
| G3 vs G4 | −25.92 | 0.039 | Significant |
| G3 vs G5 | 16.62 | 0.28 | Not significant |
| G4 vs G5 | 42.54 | 0.0007 | Significant |
Pairwise comparison of systemic exposure. Significant increases were observed for lipid-based formulations relative to the standard formulation, with the highest increase in G5.
Table 1.3 Tukey Post-Hoc Results (AUC0–∞)
| Comparison | Mean Difference | p-value | Significance |
|---|---|---|---|
| G1 vs G2 | 81.52 | 0.54 | Not significant |
| G1 vs G3 | 221.47 | 0.005 | Significant |
| G1 vs G4 | 200.61 | 0.012 | Significant |
| G1 vs G5 | 362.15 | <0.001 | Highly significant |
| G2 vs G3 | 139.95 | 0.106 | Not significant |
| G2 vs G4 | 119.09 | 0.206 | Not significant |
| G2 vs G5 | 280.63 | 0.0006 | Significant |
| G3 vs G4 | −20.86 | 0.994 | Not significant |
| G3 vs G5 | 140.68 | 0.103 | Not significant |
| G4 vs G5 | 161.54 | 0.05 | Significant |
Table 1.4 Ranking of Formulations
| Rank | Formulation | AUC0–∞ | Relative Bioavailability |
|---|---|---|---|
| 1 | G5 Lipid Encapsulated | 933.12 | 161% |
| 2 | G3 Lipid Processed | 792.44 | 138% |
| 3 | G4 Lipid Unprocessed | 771.57 | 133% |
| 4 | G2 Surfactant | 652.48 | 112% |
| 5 | G1 Standard | 570.97 | 100% |
Ranked by AUC0–∞, G5 showed the highest systemic exposure, followed by G3, G4, G2, and G1.
3.4 Tissue Distribution of Berberine#
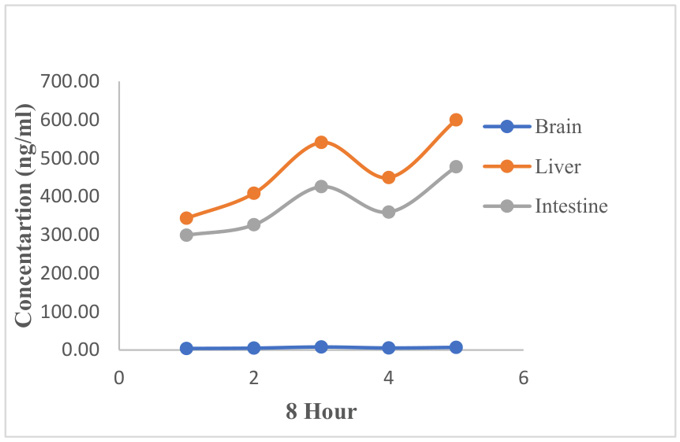
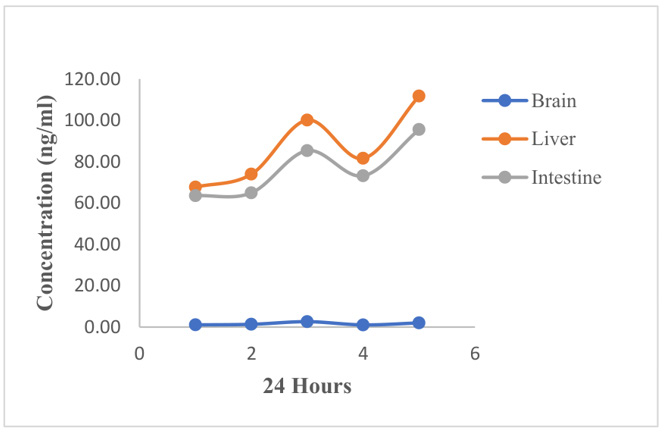
Tissue distribution was assessed at 8 and 24 h post-dose in liver, intestine, and brain (n=4 per time point).
Table 2 Mean Tissue concentrations of berberine across the brain, liver and intestine
| Group | Brain (8h) | Liver (8h) | Intestine (8h) | Brain (24h) | Liver (24h) | Intestine (24h) |
|---|---|---|---|---|---|---|
| G1 | 3.99 ± 0.32 | 343.33 ± 27.47 | 299.17 ± 23.93 | 1.05 ± 0.08 | 67.70 ± 5.42 | 63.56 ± 5.08 |
| G2 | 4.92 ± 0.39 | 408.35 ± 32.67 | 326.30 ± 26.10 | 1.33 ± 0.11 | 73.96 ± 5.92 | 64.95 ± 5.20 |
| G3 | 7.93 ± 0.63 | 540.74 ± 43.26 | 425.52 ± 34.04 | 2.60 ± 0.21 | 100.12 ± 8.01 | 85.34 ± 6.83 |
| G4 | 5.31 ± 0.42 | 449.32 ± 35.95 | 359.37 ± 28.75 | 1.05 ± 0.08 | 81.60 ± 6.53 | 73.17 ± 5.85 |
| G5 | 6.92 ± 0.55 | 599.57 ± 47.97 | 477.25 ± 38.18 | 2.01 ± 0.16 | 111.76 ± 8.94 | 95.54 ± 7.64 |
At 8 h, berberine concentrations were highest in the liver, followed by intestine, with the lowest levels observed in the brain across all groups. G5 showed the highest tissue concentrations at 8 h (liver: 599.57 ± 47.97; intestine: 477.25 ± 38.18; brain: 6.92 ± 0.55), followed by G3 and G4. At 24 h,tissue concentrations decreased in all groups, but the same ranking pattern was maintained, with G5 remaining highest (liver: 111.76 ± 8.94; intestine: 95.54 ± 7.64; brain: 2.01 ± 0.16).
3.5 Hepatic Distribution#
Hepatic concentrations were highest among the measured tissues at both time points. At 8 h, G5 showed the highest liver concentration, followed by G3 and G4, whereas G1 showed the lowest concentration. At 24 h, liver concentrations declined across all groups but remained highest in G5. Compared with G1, hepatic exposure was approximately 1.75-fold higher in G5 and 1.57-fold higher in G3, with G4 showing a more moderate increase.
3.6 Intestinal Distribution#
Intestinal concentrations followed the same general pattern as hepatic concentrations, with the highest values at 8 h and lower values at 24 h across all groups. G5 showed the highest intestinal concentrations at both time points, followed by G3 and G4, while G1 remained the lowest. Compared with G1, intestinal exposure was approximately 1.60-fold higher in G5 and 1.42-fold higher in G3.
3.7 Brain Distribution#
Brain concentrations remained low across all formulations at both time points. Slight increases were observed in G3 and G5, but brain exposure remained minimal compared with liver and intestine.
3.8 Statistical Comparison of Tissue Concentrations#
Table 3 ANOVA Results.
| Tissue | F-value | p-value | Significant Groups |
|---|---|---|---|
| Liver | 18.3 | <0.001 | G3, G5 > G1 |
| Intestine | 14.7 | <0.001 | G3, G5 > G1 |
| Brain | 3.2 | 0.04 | G3 > G1 |
Statistical confirmation of formulation-dependent differences in tissue exposure.
3.9 Fold-Change in Tissue Exposure#
Table 4 Fold Change Formulation Liver Intestine.
| G2 | 1.19× | 1.09× |
|---|---|---|
| G3 | 1.57× | 1.42× |
| G4 | 1.31× | 1.20× |
| G5 | 1.75× | 1.60× |
Relative fold-change analysis showed the greatest increase with G5 (liver: 1.75×; intestine: 1.60×), followed by G3 (liver: 1.57×; intestine: 1.42×) and G4 (liver: 1.31×; intestine: 1.20×). G2 produced smaller increases relative to G1.
3.10 Plasma–Tissue Relationship#
Correlation analysis between plasma concentrations and tissue levels revealed a moderate positive relationship (Pearson's r = 0.58, R2 = 0.34, p = 0.048), suggesting that plasma exposure alone may not fully predict tissue distribution patterns.
4 Discussion#
The present study demonstrates formulation-dependent differences in the plasma pharmacokinetics and tissue distribution of berberine, particularly in the liver and intestine.
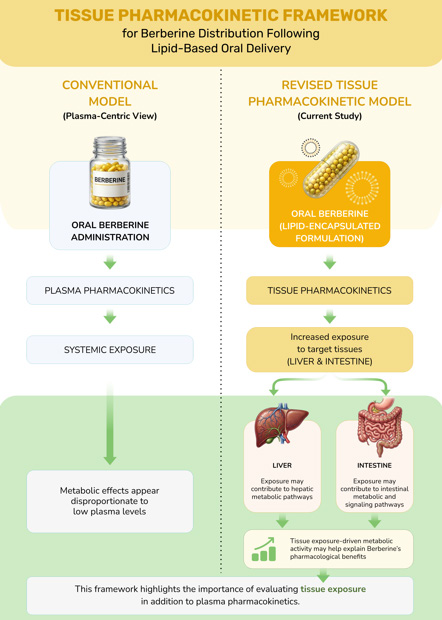
The rise in hepatic and intestinal concentrations, particularly with lipid-based formulations, may help explain the long-standing gap between berberine’s low systemic plasma levels and its potent pharmacological activity. Although this paradox has often been attributed to extensive intestinal efflux and first-pass metabolism, increasing evidence suggests that drug disposition within target tissues can differ from circulating plasma levels, particularly for compounds with high intracellular affinity and transporter-mediated uptake (Liu et al., 2010; Tsai & Tsai, 2004; Varma et al., 2012). In this context, berberine exhibits features suggestive of a “tissue exposure–driven pharmacology” model, in which intracellular concentration gradients, rather than systemic availability, influence pharmacodynamic outcomes.
The enhanced hepatic and intestinal exposure observed with lipid-based formulations is relevant because these tissues are considered major sites of berberine activity. Previous studies have associated hepatic berberine exposure with AMPK activation, regulation of lipid metabolism, and modulation of cholesterol homeostasis, while intestinal exposure has been linked to effects on gut microbiota composition and incretin-related pathways. The present findings may be consistent with the hypothesis that tissue-specific pharmacokinetics may contribute importantly to berberine’s metabolic effects.
4.1 Hepatic Pharmacokinetics and AMPK–PCSK9 Axis#
The liver was considered to be the primary site of berberine accumulation across all formulations, with the lipid-encapsulated formulation achieving approximately 1.75-fold higher hepatic concentrations than standard berberine. This increased accumulation may reflect not only improved passive permeability but also enhanced interaction with liver uptake transporters such as organic cation transporter 1 (OCT1), which facilitates intracellular drug accumulation (Nies et al., 2011). At the molecular level, berberine inhibits mitochondrial respiratory complex I, raising the intracellular AMP/ATP ratio and activating AMP-activated protein kinase (AMPK), a crucial regulator of cellular energy balance (Turner et al., 2008;
Hawley et al., 2010 ; Herzig & Shaw, 2018). The increased hepatic concentrations achieved with lipid-based formulations may support greater tissue exposure, potentially through improved intracellular retention and mitochondrial localisation. Since mitochondrial membrane potential may facilitate accumulation of cationic molecules such as berberine, higher intracellular concentrations may lead to preferential subcellular localisation, potentially influencing metabolic signalling pathways (Pereira et al., 2007).
4.2 Intestinal Pharmacokinetics and Microbiome–Incretin Axis#
In addition to hepatic accumulation, there were notable increases in intestinal berberine levels, especially with lipid-based formulations. The intestine is increasingly recognised as a key metabolic organ involved in berberine activity that coordinates nutrient sensing, microbial interactions, and hormonal regulation. Changes in gut microbiota induced by berberine may be consistently associated with higher levels of SCFA-producing bacteria and improved metabolic health as suggested by previous studies (Zhang et al., 2012; Feng et al., 2019; Ridlon et al., 2014; Sayin et al., 2013; Drucker, 2018). Reported effects of berberine on intestinal epithelial cells, such as increasing tight junction proteins and inhibiting inflammatory pathways like NF-κB, may help reinforce gut barrier integrity and reduce metabolic endotoxemia (Chen et al., 2011; Li et al., 2014). These combined mechanisms suggest that the intestine may play an important role in berberine’s systemic benefits.
4.3 Plasma Pharmacokinetics and the bioavailability paradox#
While this study primarily focused on tissue distribution, plasma pharmacokinetics were also examined to assess systemic exposure. The approximate 61% increase in relative bioavailability, together with enhanced tissue accumulation underscores potential limitations of relying solely on plasma-based pharmacokinetic models. For an active substance like berberine, extensive intestinal efflux, first-pass metabolism, and rapid tissue uptake mean that plasma levels provide only a transient and incomplete picture of drug distribution (Pan et al., 2002; Liu et al., 2010). Additionally, enterohepatic recirculation sustains tissue exposure even when plasma levels are low, creating a disconnect between systemic and local pharmacokinetics (Zuo et al., 2006). The role of active metabolites further complicates this, as some berberine metabolites have equal or higher activity and may distribute differently from the parent compound (Spinozzi et al., 2014). Pharmacodynamically, data suggest a threshold effect: once intracellular concentrations exceed a certain level, pathways such as AMPK become increasingly activated. This results in nonlinear relationships between plasma levels and therapeutic effects, a pattern well recognised in systems pharmacology (Mager & Jusko, 2008).
4.4 Mechanistic Role of Lipid-Based Formulation Strategies#
The enhanced tissue distribution observed with lipid-based formulations arises from multiple interconnected mechanisms. Lipid excipients improve drug solubilization and facilitate the formation of mixed micelles, increasing drug absorption (Pouton, 2006; Porter et al., 2007). Certain surfactants have been reported to inhibit efflux transporters and alter membrane fluidity, thereby enhancing transcellular transport (Collnot et al., 2007). Moreover, lipid digestion products support chylomicron formation, promoting lymphatic transport and partially bypassing hepatic first-pass metabolism (Trevaskis et al., 2008). Phospholipid complexation increases drug lipophilicity and membrane affinity, aiding cellular delivery and retention (Dahan & Hoffman, 2008). These systems also protect against chemical and enzymatic degradation in the gastrointestinal tract. Unlike liposomal systems, lipid matrix-based systems may offer advantages including higher active loading and simplified formulation architecture, making them more applicable for translation into clinical use (Sercombe et al., 2015).
4.5 Translational Implications and Future Clinical Evaluation#
The present study demonstrates that formulation strategy plays a critical role in modulating the tissue pharmacokinetics of berberine, with lipid-based systems significantly enhancing drug exposure in metabolically active organs. Consistent with previous pharmacokinetic studies, berberine exhibited preferential accumulation in the liver and intestine, despite low systemic exposure. This tissue-dominant distribution profile is well documented, with studies reporting that berberine undergoes extensive intestinal first-pass elimination and exhibits markedly higher hepatic exposure up to several-fold greater than plasma levels, potentially contributing to the disconnect between plasma concentration and pharmacological effect. Furthermore, berberine was rapidly and widely distributed across multiple organs, with tissue concentrations often exceeding plasma levels within hours of administration, reinforcing the potential importance of tissue pharmacokinetics in understanding its therapeutic actions.
Among the tested formulations, the lipid-encapsulated system showed the greatest increase in tissue exposure, achieving significantly higher hepatic and intestinal concentrations than the standard formulation. This superior performance can be attributed to improved solubility, enhanced membrane permeability, and, critically, engagement of endogenous lipid absorption pathways, such as chylomicron-mediated lymphatic transport. These mechanisms may enable partial bypass of intestinal and hepatic first-pass metabolism, thereby increasing both systemic availability and targeted delivery to metabolically relevant organs. A key finding of this study is that surfactant-based systems did not outperform lipid-based formulations. While surfactants are effective at improving drug solubilisation and may partially inhibit efflux transporters such as P-glycoprotein, they lack the ability to exploit physiological lipid transport pathways. As a result, surfactant systems primarily enhance dissolution without significantly improving post-absorptive transport or organ-specific targeting. In contrast, lipid-based systems provide structural compatibility with biological membranes and facilitate entry into lipid-processing pathways, potentially resulting in improved absorption kinetics and enhanced tissue deposition. This mechanistic distinction highlights the potential importance of formulation strategies that align with physiological transport processes rather than relying solely on solubilisation enhancement.
An important distinguishing feature of this work is the comparison of the highly active lipid encapsulation system with conventional liposomal delivery approaches. Traditional liposomal systems, while effective at improving solubility, are often constrained by low active-loading capacity, structural instability, and complex manufacturing requirements. In contrast, the present system achieves high active loading (>85% berberine content) while improving tissue exposure and simplifying the formulation architecture. Unlike liposomes, which rely on bilayer vesicular encapsulation, this system enables more efficient incorporation of berberine within a lipid matrix, potentially enhancing stability and delivery efficiency. This may represent a potentially useful approach in formulation design, offering improved scalability and translational potential.
Despite these promising findings, several limitations should be considered. First, the study was conducted in an animal model, and although rodent data provide valuable mechanistic insights, interspecies differences in metabolism, transporter expression, and gut microbiota may limit direct extrapolation to human pharmacokinetics. Second, tissue distribution was assessed at discrete time points, which may not fully capture the dynamic processes of absorption, redistribution, and elimination. Third, metabolite profiling was not performed due to limited sample volume. This represents an important limitation, as berberine undergoes extensive biotransformation into active metabolites, including demethyleneberberine, thalifendine, and berberrubine, which are known to contribute significantly to its pharmacological effects and tissue distribution. Additionally, the study employed a single-dose design, which does not reflect chronic dosing conditions under which berberine is typically used clinically. Repeated dosing may lead to tissue accumulation and modulation of gut microbiota, potentially altering both pharmacokinetics and pharmacodynamics over time.
Future studies should address these limitations by incorporating metabolite profiling, longitudinal sampling, and repeated dosing regimens to better characterise steady-state tissue distribution. The application of physiologically based pharmacokinetic (PBPK) modelling may further enhance translational predictability by integrating tissue-specific distribution, transporter activity, and metabolic pathways. Importantly, clinical translation will require well-designed human pharmacokinetic studies that go beyond plasma measurements to include biomarkers of tissue activity, such as hepatic lipid metabolism, AMPK activation, and modulation of the gut microbiota. From a translational standpoint, the findings of this study highlight a paradigm shift in drug development for compounds such as berberine. Rather than focusing solely on increasing plasma exposure, formulation strategies should prioritise targeted delivery to organs where pharmacological activity occurs. Lipid-based systems, as demonstrated here, offer a promising approach to achieving this objective. By enhancing tissue exposure in the liver and intestine, such systems may support improved delivery to metabolically relevant organs and warrant further clinical investigation.
In conclusion, this study reinforces the concept that tissue-specific pharmacokinetics are central to understanding berberine’s therapeutic effects. The superior performance of lipid-based formulations, combined with their mechanistic advantages over surfactant-based systems and conventional liposomal approaches, supports their potential as a clinically relevant strategy for enhancing tissue delivery of berberine and other poorly bioavailable compounds (Yin et al., 2008; Wei et al., 2021; Lan et al., 2015). Future clinical trials should include advanced biomarkers such as metabolomics and microbiome analysis to better understand its mechanisms. Additionally, differences in transporter levels and microbiome composition may affect individual responses, emphasising the need for personalised treatment strategies (Zhang et al., 2020). If these findings are confirmed in humans, tissue-targeted formulation approaches may help improve the therapeutic potential of berberine and similar compounds, especially those with limited systemic bioavailability.
5 Conclusion#
The present study demonstrates that formulation strategy significantly influences both the plasma pharmacokinetics and tissue distribution of berberine following oral administration. The observed divergence between plasma and tissue pharmacokinetics highlights the importance of evaluating tissue-specific drug distribution in addition to conventional plasma-based pharmacokinetic parameters. Such insights are important for understanding organ-specific distribution and formulation performance.
Among the evaluated systems, the lipid-encapsulated formulation showed the greatest enhancement in systemic exposure as well as hepatic and intestinal tissue concentrations compared with the standard formulation. Notably, the increase in tissue exposure was more pronounced than the increase in plasma bioavailability, supporting the concept that tissue pharmacokinetics may contribute to understanding the biological activity of berberine.
The preferential accumulation observed in the liver and intestine is consistent with the known metabolic relevance of these tissues in berberine pharmacology. These findings suggest that lipid-based formulation strategies may enhance tissue exposure more effectively than surfactant-only systems and may therefore represent a promising approach for improving berberine delivery to metabolically active organs. Compared with conventional liposomal approaches, lipid matrix–based systems may also offer advantages including higher active loading and simplified formulation architecture.
A limitation of the present study is that only parent berberine concentrations were quantified, while metabolite profiling was not performed. Future studies incorporating metabolite analysis, pharmacodynamic biomarkers, and clinical evaluation may provide additional insight into the relationship between tissue exposure and biological activity.
Overall, the study highlights the importance of evaluating tissue pharmacokinetics alongside plasma exposure when assessing berberine formulation performance. Enhanced hepatic and intestinal exposure achieved through lipid-based formulations may have translational relevance for future nutraceutical and metabolic health applications.
6 Declarations#
6.1 Ethics Approval and ARRIVE Compliance#
All animal experiments followed the ARRIVE 2.0 guidelines for reporting animal research. The protocol was approved by the Institutional Animal Ethics Committee (IAEC) under CPCSEA regulations by the Government of India. All procedures were conducted in a CPCSEA-registered facility, with efforts to minimize animal suffering and reduce the number of animals used.
Declarations
✓Patient consent
€Funding
◎Competing interests
▤Data availability
♥Acknowledgements
Article information
- Published
Copyright © 2026 Krathish Bopanna. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 48#
- 1
Ai, X., Yu, P., Peng, L., Luo, L., Liu, J., Li, S., et al. (2021). Berberine: A review of its pharmacokinetic properties and therapeutic potentials in diverse vascular diseases. Frontiers in Pharmacology, 12, 762654.
- 2
Beraldo-de-Araújo, V. L., Beraldo-de-Araújo, A., Costa, J. S. R., et al. (2019). Excipient–excipient interactions in nanocarrier development. Scientific Reports, 9, 1–12.
- 3
Brusq, J. M., Ancellin, N., Grondin, P., et al. (2006). Inhibition of lipid synthesis through activation of AMP kinase: An additional mechanism for the hypolipidemic effects of berberine. Journal of Lipid Research, 47(6), 1281–1288.
- 4
Cai, Y., Yang, Q., Yu, Y., et al. (2023). Efficacy and mechanisms of berberine in lipid metabolic diseases. Frontiers in Pharmacology, 14, 1283784.
- 5
Cao, R. Y., Zhang, Y., Feng, Z., et al. (2021).Berberine in atherosclerosis: Gut–heart axis insights. Frontiers in Pharmacology, 12, 764994.
- 6
Cameron, J., Ranheim, T., Kulseth, M. A., Leren, T. P., & Berge, K. E. (2008).Berberine decreases PCSK9 expression in HepG2 cells. Atherosclerosis, 201(2), 266–273.
- 7
Chaturvedi, S., Verma, A., & Saharan, V. A. (2020).Lipid drug carriers for enhanced bioavailability. Advanced Pharmaceutical Bulletin, 10(4), 524–538.
- 8
Choi, Y. H. (2020).Interpretation of drug interaction using tissue exposure changes. Pharmaceutics, 12(5), 417.
- 9
Collnot, E. M., Baldes, C., Wempe, M. F., et al. (2007). Influence of vitamin E TPGS on P-glycoprotein transport activity. Journal of Controlled Release, 111(1–2), 35–40.
- 10
Dahan, A., & Hoffman, A. (2008).Rationalizing the selection of oral lipid-based drug delivery systems. Pharmaceutical Research, 25(9), 2163–2174.
- 11
Drucker, D. J. (2006).The biology of incretin hormones. Cell Metabolism, 3(3), 153–165.
- 12
Drucker, D. J. (2018).Mechanisms of action and therapeutic application of glucagon-like peptide-1. Cell Metabolism, 27(4), 740–756.
- 13
Feng, R., Shou, J. W., Zhao, Z. X., et al. (2015).Gut microbiota transforms berberine into its absorbable form. Scientific Reports, 5, 12155.
- 14
Feng, R., Zhang, Y., Guo, Y., et al. (2019).Gut microbiota regulates berberine metabolism and bioavailability. Frontiers in Pharmacology, 10, 1–12.
- 15
Feng, X., Sureda, A., Jafari, S., et al. (2019).Berberine in cardiovascular and metabolic diseases: From mechanisms to therapeutics.Theranostics, 9(7), 1923–1951.
- 16
Han, J. L., Lin, H., & Huang, W. (2011).Gut microbiota modulation as an anti-diabetic mechanism of berberine. Medical Science Monitor, 17(7), RA164–RA167.
- 17
Hawley, S. A., Ross, F. A., Chevtzoff, C., et al. (2010). Mechanisms of AMPK activation. Cell Metabolism, 11(6), 554–565.
- 18
Herzig, S., & Shaw, R. J. (2018).AMPK and mitochondrial homeostasis. Nature Reviews Molecular Cell Biology, 19(2), 121–135.
- 19
Kong, W. J., Wei, J., Abidi, P., et al. (2004).Berberine is a novel cholesterol-lowering drug distinct from statins. Nature Medicine, 10(12), 1344–1351.
- 20
Lan, J., Zhao, Y., Dong, F., et al. (2015).Meta-analysis of berberine in type 2 diabetes. Journal of Ethnopharmacology, 161, 69–81.
- 21
Li, Z., Geng, Y. N., Jiang, J. D., & Kong, W. J. (2014). Antioxidant and anti-inflammatory effects of berberine. Journal of Translational Medicine, 12, 239.
- 22
Lin, J. H. (1998).Role of pharmacokinetics in drug development. Pharmacological Reviews, 50(2), 131–159.
- 23
Liu, Y. T., Hao, H. P., Xie, H. G., et al. (2010).Extensive intestinal elimination and hepatic distribution of berberine. Drug Metabolism and Disposition, 38(10), 1779–1784.
- 24
Ma, B. L., Ma, Y. M., Shi, R., et al. (2010).Tissue distribution of berberine. European Journal of Pharmacology, 646(1–3), 1–7.
- 25
Mager, D. E., & Jusko, W. J. (2008).Translational PK– PD modeling. Journal of Pharmacokinetics and Pharmacodynamics, 35(1), 1–23.
- 26
Nies, A. T., Koepsell, H., Winter, S., & Schwab, M. (2011). Organic cation transporters in drug disposition. Drug Metabolism Reviews, 43(4), 499–525.
- 27
Pan, G. Y., Wang, G. J., Liu, X. D., et al. (2002).P-glycoprotein involvement in berberine absorption. Pharmacology & Toxicology, 91(4), 193–197.
- 28
Pereira, G. C., Branco, A. F., Matos, J. A., et al. (2007). Mitochondrial effects of berberine. Journal of Pharmacology and Experimental Therapeutics, 322(2), 871–879.
- 29
Porter, C. J. H., Trevaskis, N. L., & Charman, W. N. (2007). Lipid-based drug delivery systems. Nature Reviews Drug Discovery, 6(3), 231–248.
- 30
Pouton, C. W. (2006).Formulation of poorly water-soluble drugs. European Journal of Pharmaceutical Sciences, 29(3–4), 278–287.
- 31
Ridlon, J. M., Kang, D. J., & Hylemon, P. B. (2014).Bile acid metabolism by gut microbiota. Journal of Lipid Research, 47(2), 241–259.
- 32
Sayin, S. I., Wahlström, A., Felin, J., et al. (2013).Gut microbiota regulates bile acid metabolism and FXR signaling. Cell Metabolism, 17(2), 225–235.
- 33
Sercombe, L., Veerati, T., Moheimani, F., et al. (2015). Liposome drug delivery challenges. Frontiers in Pharmacology, 6, 286.
- 34
Smith, D. A., Beaumont, K., Maurer, T. S., & Di, L. (2018). Relevance of half-life in drug design. Journal of Medicinal Chemistry, 61(10), 4273–4282.
- 35
Spinozzi, S., Colliva, C., Camborata, C., et al. (2014). Berberine metabolites and pharmacokinetics. Journal of Natural Products, 77(4), 766–772.
- 36
Sun, R., Yang, N., Kong, B., et al. (2017).Berberine modulates gut microbiota and GLP-1 secretion. Gut Microbes, 8(2), 127–140.
- 37
Tolhurst, G., Heffron, H., Lam, Y. S., et al. (2012).SCFAs stimulate GLP-1 secretion. Diabetes, 61(2), 364–371.
- 38
Trevaskis, N. L., Charman, W. N., & Porter, C. J. (2008). Lymphatic drug transport. Advanced Drug Delivery Reviews, 60(6), 702–716.
- 39
Tsai, P. L., & Tsai, T. H. (2004).Hepatobiliary excretion of berberine. Journal of Pharmaceutical Sciences, 93(6), 140–150.
- 40
Turner, N., Li, J. Y., Gosby, A., et al. (2008).Berberine activates AMPK. Diabetes, 57(5), 1414–1418.
- 41
Varma, M. V. S., Lai, Y., Feng, B., et al. (2012).PBPK modeling approaches. Clinical Pharmacology & Therapeutics, 92(1), 40–51.
- 42
Viollet, B., Guigas, B., Sanz Garcia, N., et al. (2009). Molecular mechanisms of AMPK. Annual Review of Nutrition, 29, 157–180.
- 43
Wang, Y., Shou, J. W., Li, X. Y., et al. (2017).Berberine-induced metabolites improve metabolism. Metabolism, 70, 72–84.
- 44
Wei, X., Wang, C., Hao, S., et al. (2021).Therapeutic effects of berberine in metabolic diseases. Frontiers in Pharmacology, 12, 653201.
- 45
Yin, J., Xing, H., & Ye, J. (2008).Berberine in type 2 diabetes. Metabolism, 57(5), 712–717.
- 46
Zhang, X., Zhao, Y., Zhang, M., et al. (2012).Gut microbiota changes with berberine. PNAS, 109(20), E1379–E1387.
- 47
Zhang, Y., Gu, Y., Ren, H., et al. (2020).Gut microbiome-related effects of berberine. Nature Communications, 11, 1–12.
- 48
Zuo, F., Nakamura, N., Akao, T., & Hattori, M. (2006). Pharmacokinetics of berberine and metabolites. Drug Metabolism and Disposition, 34(12), 2064–2072.