Video-Assisted Thoracic Surgery (VATS) as First-Line Approach in Thoracic Trauma: A Single-Center Case Series
Published in Annals of Thoracic Surgery
Iuorio A.1
Iuorio A.- 1 Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
Torretta G.1
Torretta G.- 1 Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
Limone M.1
Limone M.- 1 Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
Fusco P.1
Fusco P.- 1 Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
Storti A.1
Storti A.- 1 Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
Merciai F.2
Merciai F.- 2 Department of Intensive Care, Umberto I Hospital, Nocera Inferiore, Italy.
Carelli E.3
Carelli E.- 3 Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
De Ruberto E.3
De Ruberto E.- 3 Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
Mottola E.3
Mottola E.- 3 Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
Martone M.3
Martone M.- 3 Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
Salvi R.3
Salvi R.- 3 Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
Show affiliations (3)
- 1Department of Intensive Care, AORN Moscati Hospital, Avellino, Italy.
- 2Department of Intensive Care, Umberto I Hospital, Nocera Inferiore, Italy.
- 3Department of Thoracic Surgery, AORN Moscati Hospital, Avellino, Italy.
Published
Abstract
BackgroundThoracic trauma is one of the major causes of morbidity and mortality among trauma patients worldwide [1,2]. Video-assisted thoracic surgery (VATS) has evolved as a diagnostic and therapeutic approach for hemodynamically stable thoracic trauma patients [3–5]. This study aims to evaluate clinical outcomes and feasibility of early VATS as a first-line surgical option for thoracic trauma in selected cases.
MethodsWe present a case series of seven patients with thoracic trauma undergoing VATS between 2023 and 2025. Collected variables included demographics, injury mechanisms, intraoperative findings, need for conversion, complications, and hospital stay. Primary outcomes were technical success and safety; secondary outcomes included duration of hospital stay and postoperative complications.
ResultsIn all cases, undetected pulmonary parenchymal injuries were identified and repaired thoracoscopically. No conversions to thoracotomy were required. Patients demonstrated shorter hospital stays (8.7± 3.4 days) and no postoperative infections or major complications.
ConclusionsEarly VATS appears to be a safe, minimally invasive, and effective first-line option for selected stable thoracic trauma, allowing accurate diagnosis, targeted intervention, and rapid recovery with minimal morbidity. Major multicenter studies are required to validate these preliminary results.
1 Introduction#
Thoracic trauma accounts for up to 25% of trauma-related deaths and frequently coexists with multisystemic injuries[1,6]. The conventional management of thoracic injuries relies on tube thoracostomy for drainage or open thoracotomy for uncontrolled bleeding. Video-assisted thoracic surgery (VATS) has emerged as a valuable diagnostic and therapeutic alternative approach for trauma management[3,7–9]. Several studies suggest that early thoracoscopic intervention (<72 hours) reduces postoperative complications such as retained hemothorax, empyema, and pneumonia[10–13]. The aim of this study is to describe a single-center experience to evaluate the clinical efficacy and safety of early VATS as the initial surgical strategy in hemodynamically stable thoracic trauma.
2 Materials and Methods#
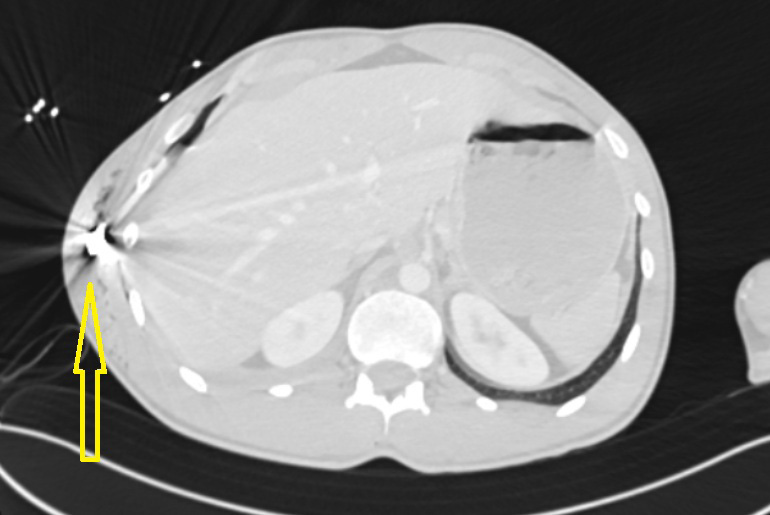
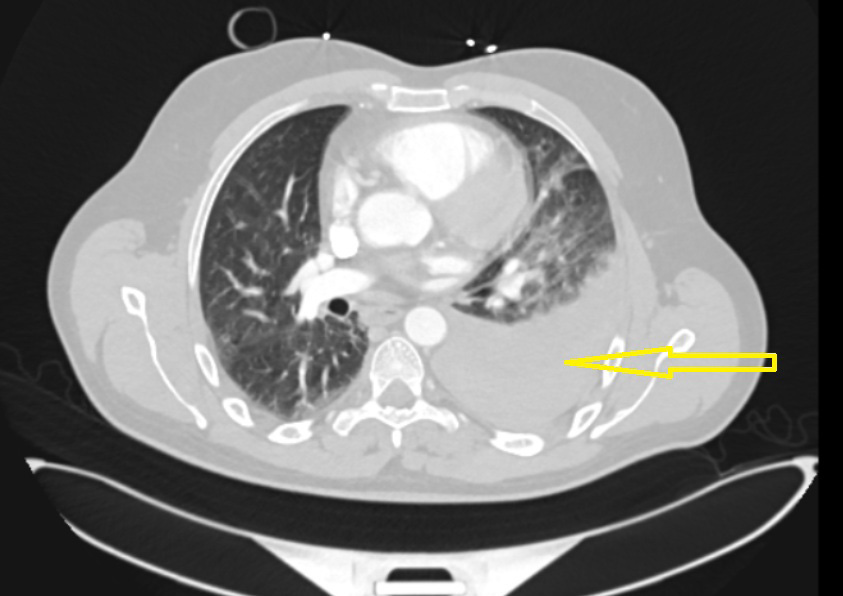
This retrospective case series included seven adult patients with thoracic trauma who underwent VATS between January 2023 and March 2025 in Moscati Hospital, Italy. Our institution is a second-level emergency care center with a high annual volume of thoracic elective surgery procedures performed via VATS, amounting approximately 220 cases per year. Inclusion criteria were hemodynamic stability (systolic blood pressure ≥ 90 mmHg), absence of massive hemothorax (>1500 mL), and no indication for emergency thoracotomy[14,15]. All patients underwent preoperative chest radiography in shock room and CT total body to confirm diagnosis (Figure A, B). Written informed consent was obtained before surgery. Procedures were performed under general anesthesia with single-lung ventilation. A standard thoracoscopic three-port technique was used: one 10-mm thoracoscope port and two 5-mm working ports. Injuries were managed with hemostasis, clot evacuation, parenchymal repair, or foreign body removal. No conversion to thoracotomy was needed for uncontrolled hemorrhage or inadequate visualization[16]. Primary endpoints were technical success and conversion rate; secondary endpoints were postoperative complications, ICU stay, and hospital length of stay[17].
3 Results#
Data were analyzed using descriptive statistics, including means, ranges, and frequencies. Seven male patients (mean age 42.3 years, range 18–73) underwent early VATS following thoracic trauma. Mechanisms included stab wounds (n=4), gunshot wounds (n=2), and multiple penetrating injuries (n=2). Preoperative CT demonstrated pneumothorax in all and hemothorax in four patients. Two retained metallic fragments were identified and removed thoracoscopically. Mean operative time was 83 ± 22 minutes, estimated blood loss 180 mL (range 80–700), and no intraoperative conversions. Postoperatively, chest tubes were removed after a mean of 3.6 ± 1.2 days. No patients developed empyema, air leaks, or respiratory failure. Two patients required short-term ICU observation for comorbidities prior to the trauma (48 hours). All patients were discharged in good condition with radiographic confirmation of lung re-expansion[18–20], (Table 1), see Video in Supplement Material Section.
Table 1 Variables included of the selected patients.
| Patient | Age | Sex | Injury Mechanism | Imaging | VATS Findings | Conversion | LOS (days) | Complications |
|---|---|---|---|---|---|---|---|---|
| M.C. | 73 | M | Multiple sharp injuries | Left pneumothorax | Apical lobe laceration + hemothorax | No | 8 | None |
| L.F. | 42 | M | Stab wound | Hemopericardium + hemothorax | Lingula laceration | No | 11 | None |
| S.G. | 18 | M | Gunshot | Retained bullet | Foreign body removal | No | 4 | None |
| H.A. | 47 | M | Multiple penetrating wounds | Pneumo-hemothorax | Multiple parenchymal lacerations | No | 14 | None |
| D.G.A. | 59 | M | Stab wound | Active blush | Apical subsegment injury | No | 5 | None |
| C.S. | 36 | M | Stab wound | Pneumothorax | Apical subsegment injury | No | 9 | None |
| R.L. | 21 | M | Gunshot | Pneumo-hemothorax | Bullet retrieval | No | 10 | None |
4 Comment#
Our experience supports the growing evidence that early VATS is a valid alternative to thoracotomy for hemodynamically stable thoracic trauma patients. The absence of conversions and major complications aligns with reports from multicenter series[21,22]. Early thoracoscopic evacuation of hemothorax shows significant advantages in terms on empyema rates, pulmonary complications, and hospitalization stay[10,12,23]. In experienced hands and in a high-volume center performing thoracic surgery procedures via VATS, this procedure offers diagnostic clarity, identifying occult diaphragmatic or parenchymal injuries not visible on imaging[24]. Indeed, in our series, postoperative pain was reduced, mobilization was faster, opioid use was lower, pulmonary function was improved [25–27]. Future multicenter prospective studies are needed to establish standardized algorithm for timing and indications of early thoracoscopic intervention in trauma care.
5 Conclusions#
Our single center experience shows that early VATS is a safe and effective minimally invasive technique for managing selected hemodynamically stable thoracic trauma patients in center with a high volume of these thoracic procedures. Compared to thoracotomy and the placement of the only chest drain, it provides definitive diagnosis and treatment in a single procedure reducing morbidity and hospital stay by improving prognosis and long-term outcomes. Larger studies are recommended to consolidate these findings and establish guidelines for the widespread use of VATS in thoracic trauma management.
Declarations
◎Competing interests
Article information
- Published
Copyright © 2026 Angela Iuorio. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 25#
- 1
American College of Surgeons. ATLS: Advanced Trauma Life Support. 10th ed. Chicago: ACS; 2018.
- 2
O’Connor JV, Adamski J. The diagnosis and treatment of non-cardiac thoracic trauma. J R Army Med Corps. 2010;156(1):5–14. doi:10.1136/jramc-156-01-02
- 3
Lodhia JV, Konstantinidis K, Papagiannopoulos K. The role of VATS in thoracic trauma. Ann Thorac Surg. 2021;112(4):1123–1132. doi:10.1016/j.athoracsur.2020.09.031
- 4
Meyer DM, Jessen ME, Wait MA, Estrera AS. Early thoracoscopic evacuation of retained hemothorax. Ann Thorac Surg. 1997;64(5):1396–1400. doi:10.1016/S0003-4975(97)00892-1
- 5
Smith JW, Franklin GA, Harbrecht BG, Richardson JD. Early VATS for blunt chest trauma. Ann Thorac Surg. 2011;91(6):1832–1837. doi:10.1016/j.athoracsur.2011.01.061
- 6
Battle CE, Evans PA. Epidemiology and outcomes of chest trauma. Trauma. 2015;17(2):145–152. doi:10.1177/1460408614553418
- 7
Lang-Lazdunski L, Coonar AS. The role of video-assisted thoracic surgery in chest trauma. Eur J Cardiothorac Surg. 2004;26(2):387–391. doi:10.1016/j.ejcts.2004.03.025
- 8
Ahmed N, Jones D. VATS in trauma: Indications and techniques. J Trauma Acute Care Surg. 2004;56(3):659–668. doi:10.1097/01.TA.0000122554.90369.93
- 9
Kim YT, Sung SW, Park JD, Kim JH. Thoracoscopy for post-traumatic hemothorax. Ann Thorac Surg. 2001;71(5):1827–1831. doi:10.1016/S0003-4975(01)02488-5
- 10
DuBose J, Inaba K, Demetriades D. Retained hemothorax management. Am Surg. 2012;78(10):1223–1227. doi:10.1177/000313481207801016
- 11
Eastern Association for the Surgery of Trauma (EAST) Guidelines. Management of hemothorax. J Trauma Acute Care Surg. 2021;91(6):1121–1130. doi:10.1097/TA.0000000000003471
- 12
Matsumoto J, Lohman BD, Morimoto K, et al. Thoracoscopic evacuation of retained hemothorax. Surg Endosc. 2015;29(2):469–473. doi:10.1007/s00464-014-36785
- 13
Subotic D, Mandaric D, Savic D, et al. Early thoracoscopy reduces complications. Interact Cardiovasc Thorac Surg. 2019;29(5):722–728. doi:10.1093/icvts/ivz183
- 14
WSES Guidelines for Thoracic Trauma. World J Emerg Surg. 2023;18(1):35. doi:10.1186/s13017-023-00506-1
- 15
Karmy-Jones R, Nathens AB. Thoracic trauma management. Chest. 2004;125(4):1451–1464. doi:10.1378/chest.125.4.1451
- 16
Inci I, Ozçelik C, Nizam O, et al. Thoracoscopic management of retained hemothorax. Eur J Cardiothorac Surg. 1999;16(4):394–397. doi:10.1016/S1010-7940(99)00268-8
- 17
Wu YC, Chen CW, Lin LC, et al. Early VATS in post-traumatic hemothorax. J Thorac Dis. 2016;8(7):1629–1635. doi:10.21037/jtd.2016.05.32
- 18
Fraga GP, Kim FL, Araujo S, Mantovani M. Thoracoscopy in penetrating trauma. World J Surg. 2009;33(12):2475–2481. doi:10.1007/s00268-009-0198-y
- 19
Wang C, Chen X, Guo Y, et al. Early thoracoscopy vs conservative management. Ann Thorac Surg. 2022;113(3):867–875. doi:10.1016/j.athoracsur.2021.07.037
- 20
Sakurai T, Terashita Y, Saito K, et al. Benefits of early VATS in acute trauma. Gen Thorac Cardiovasc Surg. 2020;68(5):503–510. doi:10.1007/s11748-020-01252-1
- 21
Lodhia JV, et al. Early VATS for trauma: Outcomes. Ann Thorac Surg. 2021;112(4):1123–1132. doi:10.1016/j.athoracsur.2020.09.031
- 22
Guo Y, Zheng W, Liu D, et al. Timing of VATS intervention: Meta-analysis. J Cardiothorac Surg. 2023;18(1):112. doi:10.1186/s13019-023-02161-7
- 23
Prokakis C, Koletsis E, Dedeilias P, et al. Video-assisted thoracic surgery in thoracic trauma. Eur J Trauma Emerg Surg. 2023;49(1):45–54. doi:10.1007/s00068-022-02084-7
- 24
LeBlanc KA, Tucker WY. Thoracoscopy in trauma: Review. Surg Endosc. 1995;9(8):961–965. doi:10.1007/BF00188776
- 25
Karmy-Jones R, Nathens AB. Thoracoscopy in trauma: Current perspectives. Trauma Surg Acute Care Open. 2024;9(1): e001421. doi:10.1136/tsaco-2024-001421.