Predictors of Short Term Functional Outcomes of Stroke Patients Admitted to Saint Pauls Hospital Millennium Medical College Addis Ababa Ethiopia A Prospective Cohort Study
Mohammed Kedir Shukri1 ✉
Mohammed Kedir ShukriCorresponding author- 1 Saint Paul’s Hospital Millennium Medical College, Addis Ababa, Ethiopia
Tsion Haile Woldemariam2 ✉
Tsion Haile WoldemariamCorresponding author- 2 Arbaminch University College of Medicine and Health Sciences, Arbaminch, Ethiopia
Betelhem Molla Dumessa1
Betelhem Molla Dumessa- 1 Saint Paul’s Hospital Millennium Medical College, Addis Ababa, Ethiopia
Esmael Mohammed Dawud1
Esmael Mohammed Dawud- 1 Saint Paul’s Hospital Millennium Medical College, Addis Ababa, Ethiopia
Yishak Abrham Bosha3
Yishak Abrham Bosha- 3 Wolaita Sodo University, Wolaita Sodo, Ethiopia
Weys Nesru Neda4
Weys Nesru Neda- 4 Uppsala University, Uppsala, Sweden
Abdurrhman Kedir Hamza5
Abdurrhman Kedir Hamza- 5 Addis Ababa University, Addis Ababa, Ethiopia
Mihiret Legese Nadew1
Mihiret Legese Nadew- 1 Saint Paul’s Hospital Millennium Medical College, Addis Ababa, Ethiopia
Show affiliations (5)
- 1Saint Paul’s Hospital Millennium Medical College, Addis Ababa, Ethiopia
- 2Arbaminch University College of Medicine and Health Sciences, Arbaminch, Ethiopia
- 3Wolaita Sodo University, Wolaita Sodo, Ethiopia
- 4Uppsala University, Uppsala, Sweden
- 5Addis Ababa University, Addis Ababa, Ethiopia
Published
Abstract
BackgroundStroke is a leading cause of adult disability worldwide, with motor impairments such as hemiparesis significantly reducing quality of life. Identifying clinical and sociodemographic predictors of short-term functional recovery is essential to optimize rehabilitation strategies, especially in resource-limited settings like Ethiopia.
ObjectiveTo identify predictors of short-term functional outcomes among stroke patients admitted to Saint Paul’s Hospital Millennium Medical College from May 1 to October 30, 2023.
MethodsThis prospective cohort study enrolled 152 consecutive adult stroke patients confirmed by clinical and radiological criteria. Functional recovery was assessed at three weeks post-stroke using the Functional Independence Measure (FIM). Data on demographics, stroke characteristics, comorbidities, physiotherapy care (enrolment, timing, intensity), and hospital service factors were collected. Bivariate and multivariate logistic regression analyses identified independent predictors of functional improvement.
ResultsAmong participants, 39.5% received physiotherapy during hospitalization. Physiotherapy enrolment was strongly associated with improved short-term functional recovery (adjusted odds ratio [AOR] = 5.36; 95% confidence interval [CI], 4.50–10.75; p = 0.006). Greater physiotherapy intensity (total hours) also predicted better outcomes (AOR = 1.35; 95% CI, 1.17–1.56; p < 0.001). Older age, presence of comorbidities, and in-hospital complications were negatively associated with recovery. Timing of physiotherapy initiation was not significantly linked to outcomes.
ConclusionPhysiotherapy enrolment and intensity are key determinants of short-term functional recovery after stroke. Expanding access and ensuring adequate rehabilitation dosage should be prioritized in stroke care protocols in Ethiopia.
1 Introduction#
Stroke remains a major cause of adult disability globally, accounting for approximately 11% of deaths and a leading contributor to long-term neurological impairment[1, 2]. In Ethiopia and other low- and middle-income countries (LMICs), the burden is rising due to increasing prevalence of risk factors such as hypertension, diabetes mellitus, and sedentary lifestyles, compounded by limited access to comprehensive stroke care and rehabilitation services[3].
Motor impairments, especially hemiparesis, are common after stroke and severely limit mobility and independence in activities of daily living (ADLs), impacting patients’ quality of life and social participation[4]. Functional recovery during the early post-stroke period is a critical determinant of long-term prognosis and quality of life[5, 6].
Rehabilitation, particularly physiotherapy, is essential to promote motor recovery, prevent secondary complications, and facilitate reintegration into the community. Evidence from high-resource settings indicates that early initiation and adequate intensity of physiotherapy improve functional independence and reduce disability[7, 8]. However, in Ethiopia, rehabilitation services are often limited by resource constraints, staffing shortages, and lack of standardized protocols.
Multiple factors influence stroke recovery trajectories, including patient age, stroke severity, comorbidities, and in-hospital complications[9, 10]. Identifying predictors of functional outcomes in the Ethiopian context is crucial to tailor rehabilitation interventions and improve patient care.
This study aimed to evaluate predictors of short-term functional outcomes among stroke patients admitted to Saint Paul’s Hospital Millennium Medical College, focusing on the role of physiotherapy care and individual clinical factors during the first three weeks post-stroke. The findings will inform evidence-based rehabilitation protocols and policy development in Ethiopia.
2 Methods#
2.1 Study Design and Setting#
This prospective cohort study was conducted at Saint Paul’s Hospital Millennium Medical College (SPHMMC), a tertiary referral hospital in Addis Ababa, Ethiopia. The hospital’s Internal Medicine Department includes a neurology unit with a dedicated stroke ward and an on-site rehabilitation center staffed by specialized physiotherapists and nurses.
2.2 Study Period#
Data were collected from May 1 to October 30, 2023.
2.3 Population#
- Source population: All adult patients admitted to the medical wards of SPHMMC during the study period.
- Study population: All newly diagnosed stroke patients admitted to SPHMMC who met eligibility criteria.
2.4 Eligibility Criteria#
- Inclusion: Adults aged ≥18 years with clinically and radiologically confirmed ischemic or hemorrhagic stroke.
- Exclusion: Patients with pre-stroke disability (modified Rankin Scale >2), those transferred from other facilities >48 hours after stroke onset, and patients with severe cognitive impairment assessed using the Mini-Mental State Examination (MMSE) score <18, precluding informed consent or reliable functional assessment.
2.5 Sample Size Determination and Sampling Technique#
A total of 152 consecutive eligible stroke patients were enrolled until the sample size was reached. Consecutive sampling minimized selection bias.
2.6 Data Collection Tools and Techniques#
A pilot study validated the use of the Functional Independence Measure (FIM) in the local context. Data were collected using structured checklists covering sociodemographic variables, stroke characteristics, admission NIH Stroke Scale (NIHSS) scores, comorbidities, physiotherapy care details (enrolment, timing, intensity), and hospital service factors.
Eight internal medicine residents, trained in a two-hour session on standardized assessment and data recording, collected data. Supervisors ensured data completeness and consistency.
Functional recovery was assessed at discharge or three weeks post-stroke during outpatient follow-up. For patients hospitalized beyond three weeks, assessment was conducted as inpatients.
2.7 Variables#
Independent variables: Age, sex, educational status; comorbidities (diabetes mellitus, hypertension, heart failure, dyslipidemia, chronic kidney disease); stroke type (ischemic or hemorrhagic), location (cortical or subcortical); stroke severity (NIHSS score); sensory loss; physiotherapy enrolment; physiotherapy intensity (total hours/session); timing of physiotherapy initiation.
Dependent variable: Functional recovery measured by change in FIM score at three weeks post-stroke.
2.8 Outcome Measures#
Stroke severity: NIHSS score categorized as minor (1–4), moderate (5–15), and moderate to severe (>15).
Functional outcome: FIM total score (range 18–126), with higher scores indicating greater independence. A significant improvement was defined as a meaningful increase in FIM score leading to functional independence (>108).
2.9 Data Processing and Analysis#
Data were entered and analyzed using SPSS v26. Descriptive statistics summarized baseline characteristics. Associations between predictors and functional outcomes were assessed with chi-square tests for categorical variables and independent t-tests for continuous variables. Variables with p < 0.20 in bivariate analysis were included in multivariate binary logistic regression to identify independent predictors of functional improvement. Odds ratios (ORs) with 95% confidence intervals (CIs) were reported. Statistical significance was set at p < 0.05.
Missing data were minimal (<5%) and handled using listwise deletion.
2.10 Ethical Considerations#
The SPHMMC Institutional Review Board approved the study. Written informed consent was obtained from all participants or their caregivers. Confidentiality was maintained throughout.
3 Result#
3.1 Participant Characteristics#
Among 152 stroke patients, 72 (47.4%) were male and 80 (52.6%) female. The mean age was 63.0 ± 15.85 years (range 25–89). Sociodemographic characteristics and physiotherapy enrolment are summarized in Table 1.
Males had higher physiotherapy enrolment (44%) than females (35%). Enrolment varied by residence, highest among Oromia residents (57.1%) and lowest among Amhara (11.1%). Educational status influenced enrolment; inidividuals with a college degree had the highest participation rate (55%), while those with no formal education had the lowest (26.1%).
Table 1 Sociodemographic characteristics and physiotherapy enrolment of the study participants.
| Variables | Categories | Enrolment in Physiotherapy care | |
|---|---|---|---|
| Yes (%) | No (%) | ||
| Sex | Male | 32(44%) | 40(55.6%) |
| Female | 28(35%) | 52(65%) | |
| Address | Addis Ababa | 26(33.3%) | 52(66.7%) |
| Oromia | 24(57.1%) | 18(42.9%) | |
| Amhara | 2(11.1%) | 16(88.9%) | |
| Tigray | 2(33.3%) | 4(66.7%) | |
| Others | 6(75%) | 2(25%) | |
| Educational Status | Primary school | 10(29.4%) | 24(70.6%) |
| High school | 16(50%) | 16(50%) | |
| College degree | 22(55%) | 18(45%) | |
| No formal education | 12(26.1%) | 34(73.9%) | |
3.2 Clinical Characteristics and Physiotherapy Enrolment#
Patients without comorbidities were more likely to receive physiotherapy (63.3%) compared to those with comorbidities (23.9%). Ischemic stroke patients had higher enrolment (46.3%) than hemorrhagic stroke patients (31.4%). Stroke severity influenced enrolment: 47.2% of mild, 43.8% of moderate, and 25% of severe cases were enrolled. Absence of sensory impairment was associated with higher enrolment (44.7% vs. 31%). Mean admission FIM score was 67.66 ± 27.08, indicating moderate functional status (Table 2).
Table 2 Clinical Characteristics and Physiotherapy Enrolment of study participants.
| Variables | Categories | Enrolment in physiotherapy | |
|---|---|---|---|
| Yes (%) | No (%) | ||
| Presence of comorbidities | Yes | 22(23.9%) | 70(76.1%) |
| No | 38(63.3%) | 22(36.7%) | |
| Stroke Types | Ischemic | 38(46.3%) | 44(53.7%) |
| Hemorrhagic | 22(31.4%) | 48(68.6%) | |
| Stoke Localization | Cortical | 34(39.5%) | 50(60.5%) |
| Subcortical | 26(39.4%) | 40(60.6%) | |
| NIHSS at admission | Mild | 34(47.2%) | 38(52.8%) |
| Moderate | 14(43.8%) | 18(56.3%) | |
| Severe | 12(25%) | 36(75%) | |
| Sensory Impairment | Yes | 18(31%) | 40(69%) |
| No | 42(44.7%) | 52(55.3%) | |
| FIM Score at admission | Mean(SD) | 67.66(SD: 27.084) | |
FIM: Functional Independence measure NIHSS: Nation Institute of Health Stroke Scale SD: Standard Deviation
3.3 Physiotherapy Care and Hospital Services#
Only 39.5% (n=60) of patients received physiotherapy during hospitalization. Timing of initiation was delayed; only 6.6% started within 48 hours, 18.4% between 48 hours and 7 days, and 10.5% after 10 days. A majority (60.5%) did not receive inpatient physiotherapy. Hospital physiotherapy service availability was reported by 31.6%, but only 1.3% experienced regular service provision. Mean total physiotherapy duration was 1.50 ± 6.03 hours. Average inpatient stay was 10.99 ± 5.48 days (Table 3).
Medical treatments administered included anti-ischemic therapy (35.5%), antihypertensive agents (39.5%), anticoagulation (7.9%), and combined treatments (17.1%). In-hospital complications were common, with pneumonia affecting 40.3% of patients, followed by upper gastrointestinal bleeding (17.9%), venous thromboembolism (10.4%), acute kidney injury (9.0%), urinary tract infections (6.0%), and other complications (16.4%).
Table 3 Physiotherapy care and other treatment related factors.
| Variables | Categories | Frequency | Percentage (%) |
|---|---|---|---|
| Physiotherapy care enrolment | Enrolled | 60 | 39.5 |
| Not-enrolled | 92 | 60.5 | |
| Timing of initiation of physiotherapy | Within 48hrs | 10 | 6.58 |
| 48hrs- 7 days | 28 | 18.4 | |
| 7 days- 10 days | 6 | 3.9 | |
| After 10 days | 16 | 10.5 | |
| Not received as inpatient | 92 | 60.5 | |
| Physiotherapy service of the hospital | Availability of the service | 48 | 31.6 |
| Regularity of the service | 2 | 1.3 | |
| Medical treatments received | Anti-ischemic | 54 | 35.5 |
| Antihypertensive | 60 | 39.5 | |
| Anticoagulation | 12 | 7.89 | |
| Combined treatments | 26 | 17.1 | |
| In hospital complications developed | Pneumonia | 61 | 40.3 |
| Urinary tract infections | 9 | 6.0 | |
| Acute Kidney Injury | 14 | 9.0 | |
| Venous thromboembolism | 16 | 10.4 | |
| UGIB | 27 | 17.9 | |
| Others | 25 | 16.4 | |
| Total hours of physiotherapy received | Mean(SD) | 1.50 hours (6.031) | |
| Length of stay as an inpatient | Mean(SD) | 10.99 days (SD 5.483) | |
3.4 Functional Outcomes#
At three weeks, mean FIM score improved to 71.05 ± 30.97. The change ranged from –6 to +14 points. Forty percent of patients reached high functional independence (FIM > 80). Forty-three percent showed statistically significant functional improvement (Figure 1).
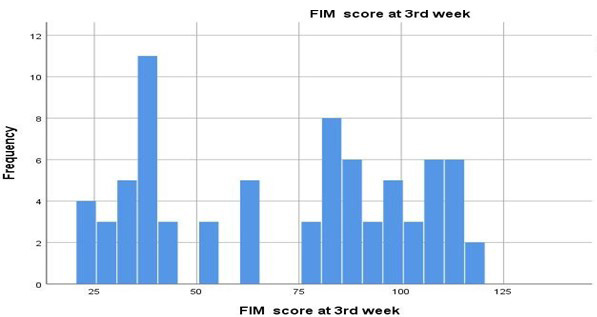
Mean-71.05, SD-30.968 N= 152
3.5 Predictors of Functional Recovery#
Multivariate logistic regression identified physiotherapy enrolment (AOR = 5.36; 95% CI, 4.50–10.75; p = 0.006) and physiotherapy intensity (AOR = 1.35; 95% CI, 1.17–1.56; p < 0.001) as significant positive predictors of functional recovery.
Older age was negatively associated with recovery (AOR = 0.94; 95% CI, 0.88–1.00; p = 0.048). Presence of comorbidities (AOR = 0.05; 95% CI, 0.004–0.53; p = 0.013) and in-hospital complications (AOR = 0.003; 95% CI, 0.000–0.049; p < 0.001) were strongly negatively associated.
Stroke type, stroke localization, sex, NIHSS score, timing of physiotherapy initiation, medical treatments, and length of stay were not significantly associated after adjustment (Tables 4 and 5).
Table 4 Association of predictive factors with functional recovery in short-term (FIM score change at third week)

Shown as printed in the PDF. View in PDF (page 5)
Table 5 Association of predictive factors with functional recovery in short-term (FIM score change at third week)
| Variables | Mean (SD) | AOR (95%CI) | P value |
|---|---|---|---|
| Age | 63 (15.85) | 0.877-1.000 | 0.040 |
| NIHSS at admission | 13.54 (13.633) | 0.905-1.076 | 0.761 |
| The initial hour of the visit to the ED | 21.92 (24.175) | 0.951-1.016 | 0.299 |
| Total physiotherapy hours | 4.92 (6.031) | 1.169-1.1564 | 0.000 |
| Length of stay in hospital | 10.99 (5.483) | 0.768-1.031 | 0.120 |
FIM: Functional independence measure, AOR: adjusted odds ratio, CI: confidence interval. ER: Emergency department SD: standard deviation
4 Discussion#
This study highlights the critical role of physiotherapy enrolment and intensity in enhancing short-term functional recovery among stroke patients in Ethiopia. Despite physiotherapy’s proven benefits, only 39.5% of patients received inpatient physiotherapy, with very few starting within 48 hours. This low enrolment and delayed initiation likely reflect systemic barriers such as limited staffing, resource constraints, and lack of standardized rehabilitation protocols common in LMICs[11-13].
The strong positive association between physiotherapy intensity and recovery underscores the need to not only expand access but also ensure adequate session frequency and duration to maximize patient outcomes[14-16]. The absence of a significant association between timing of initiation and recovery may be due to the small proportion receiving early therapy and insufficient power to detect differences[17, 18].
Sociodemographic disparities in physiotherapy enrolment suggest inequities in access potentially driven by socioeconomic status, health literacy, and geographic proximity to services[19,20]. Clinical selection bias may favor patients with milder strokes and fewer comorbidities for rehabilitation[21, 22], highlighting the need for inclusive rehabilitation policies.
Older age, comorbidities, and in-hospital complications were negatively associated with recovery, consistent with literature indicating these factors hinder post-stroke rehabilitation[23-26]. These findings emphasize the importance of comprehensive management of comorbid conditions and prevention of complications during acute care.
Limitations include the single-center design and modest sample size, which may limit generalizability. The observational design precludes causal inference, and unmeasured confounders may exist.
5 Conclusion#
Physiotherapy enrolment and intensity are key determinants of short-term functional recovery after stroke. To improve outcomes, Ethiopian stroke care protocols should prioritize expanding physiotherapy services, ensuring early and adequate rehabilitation dosing, and addressing sociodemographic and clinical disparities. Comprehensive management of comorbidities and prevention of complications are also essential to optimize recovery.
6 Declarations#
Declarations
✓Patient consent
€Funding
◎Competing interests
▤Data availability
Article information
- Published
Copyright © 2025 Mohammed Kedir Shukri, Tsion Haile Woldemariam. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 26#
- 1
World Stroke Organization. Global Stroke Fact Sheet 2025. Int J Stroke. 2025;20(2):132-144.
- 2
Feigin VL, Norrving B, Mensah GA. Global burden of stroke. Circ Res. 2017;120(3):439-448. doi:10.1161/CIRCRESAHA.116.308413.
- 3
Alene M, Assemie MA, Yismaw L, et al. Magnitude of risk factors and in-hospital mortality of stroke in Ethiopia: a systematic review and meta-analysis. BMC Neurol. 2020;20(1):309. doi:10.1186/s12883-020-01870-6.
- 4
Langhorne P, Bernhardt J, Kwakkel G. Stroke rehabilitation. Lancet. 2011;377(9778):1693-1702. doi:10.1016/S0140-6736(11)60325-5.
- 5
Chen WC, Hsiao MY, Wang TG. Prognostic factors of functional outcome in post-acute stroke in the rehabilitation unit. J Formos Med Assoc. 2022;121(3):670-678. doi:10.1016/j.jfma.2021.07.009.
- 6
Stineman MG, Jette AM, Fiedler RC, et al. A prediction model for functional recovery in stroke. Stroke. 1997;28(3):550-556. doi:10.1161/01.STR.28.3.550.
- 7
Wei X, Sun S, Zhang M, et al. A systematic review and meta-analysis of clinical efficacy of early and late rehabilitation interventions for ischemic stroke. BMC Neurol. 2024;24(1):91. doi:10.1186/s12883-024-03565-8
- 8
Miranda JDA, Borges VM, Bazan R, et al. Early mobilization in acute stroke phase: a systematic review. Top Stroke Rehabil. 2023;30(2):157-168. doi:10.1080/10749357.2021.2008595.
- 9
Alawieh A, Zhao J, Feng W. Factors affecting post-stroke motor recovery: implications on Neurotherapy after brain injury. Behav Brain Res. 2018;340:94-101. doi:10.1016/j.bbr.2016.08.029.
- 10
Li X, He Y, Wang D, Rezaei MJ. Stroke rehabilitation: from diagnosis to therapy. Front Neurol. 2024;15:1402729. doi:10.3389/fneur.2024.1402729.
- 11
Bettger JP, Liu C, Gandhi DBC, et al. Emerging areas of stroke rehabilitation research in low- and middle-income countries: a scoping review. Stroke. 2019;50(11):e123-e132. doi:10.1161/STROKEAHA.119.023565.
- 12
Gandhi DBC, Kamalakannan S, Urimubenshi G, et al. Stroke rehabilitation clinical practice guidelines in low- and middle-income countries: a systematic review of quality and unique features. Cerebrovasc Dis. 2024. doi:10.1159/000539999.
- 13
Miranda JDA, Borges VM, Bazan R, et al. Early mobilization in acute stroke phase: a systematic review. Top Stroke Rehabil. 2023;30(2):157-168. doi:10.1080/10749357.2021.2008595.
- 14
Veerbeek JM, Kwakkel G, van Wegen E, Ket JC, Heymans MW. Early prediction of the outcome of activities of daily living after stroke: a systematic review. Stroke. 2014;45(2):448-455. doi:10.1161/STROKEAHA.113.002820.
- 15
Pollock A, Baer G, Campbell P, Choo PL. Physical rehabilitation approaches for the recovery of function and mobility following stroke. Cochrane Database Syst Rev. 2014;(4):CD001920. doi:10.1002/14651858.CD001920.pub3.
- 16
Langhorne P, Bernhardt J, Kwakkel G. Stroke rehabilitation. Lancet. 2011;377(9778):1693-1702. doi:10.1016/S0140-6736(11)60325-5.
- 17
Wei X, Sun S, Zhang M, et al. A systematic review and meta-analysis of clinical efficacy of early and late rehabilitation interventions for ischemic stroke. BMC Neurol. 2024;24(1):91. doi:10.1186/s12883-024-03565-8
- 18
Miranda JDA, Borges VM, Bazan R, et al. Early mobilization in acute stroke phase: a systematic review. Top Stroke Rehabil. 2023;30(2):157-168. doi:10.1080/10749357.2021.2008595.
- 19
Bettger JP, Liu C, Gandhi DBC, et al. Emerging areas of stroke rehabilitation research in low- and middle-income countries: a scoping review. Stroke. 2019;50(11):e123-e132. doi:10.1161/STROKEAHA.119.023565.
- 20
Gandhi DBC, Kamalakannan S, Urimubenshi G, et al. Stroke rehabilitation clinical practice guidelines in low- and middle-income countries: a systematic review of quality and unique features. Cerebrovasc Dis. 2024. doi:10.1159/000539999.
- 21
Alawieh A, Zhao J, Feng W. Factors affecting post-stroke motor recovery: implications on Neurotherapy after brain injury. Behav Brain Res. 2018;340:94-101. doi:10.1016/j.bbr.2016.08.029.
- 22
Chen WC, Hsiao MY, Wang TG. Prognostic factors of functional outcome in post-acute stroke in the rehabilitation unit. J Formos Med Assoc. 2022;121(3):670-678. doi:10.1016/j.jfma.2021.07.009.
- 23
Lee KB, Kim J, Kim Y, et al. Effects of age on long-term functional recovery in patients with stroke. Front Neurol. 2020;11:755887. doi:10.3389/fneur.2020.755887.
- 24
Endel E, Kiechl S, Willeit J, et al. Functional recovery after ischemic stroke—a matter of age: data from the Austrian Stroke Unit Registry. Stroke. 2012;43(4):1090-1095. doi:10.1161/STROKEAHA.111.639750.
- 25
Bagg S, Pombo AP, Hopman W. Effect of age on functional outcomes after stroke rehabilitation. Stroke. 2002;33(1):179-185. doi:10.1161/hs0102.1012.
- 26
Kim J, Lee S, Park J, et al. Modification of the effects of age on clinical outcomes through lifestyle-related factors after acute ischemic stroke. Neurobiol Aging. 2023;120:1-10. doi:10.1016/j.neurobiolaging.2023.01.005.