Right Ventricle Myocardial Abscess Developed after Penetrating Cardiac Injury
Published in Journal of Cardiovascular Diseases
Andrea Ardigò
Andrea Ardigò More articles by this author →Salvatore Poddi
Salvatore Poddi More articles by this author →Alessio Rungatscher ✉
Alessio RungatscherCorresponding author More articles by this author →
Published
Abstract
Myocardial abscess is a life-threatening condition characterized by a suppurative infection of the myocardium. It typically arises as a complication of infective endocarditis or, less frequently, other conditions such as sepsis or myocardial infarction. The most common localizations are the left ventricular wall and the interventricular septum. Isolated myocardial abscesses are exceedingly rare. In this report, we present the case of a 43-year-old woman who presented with a right ventricle myocardial abscess 6 months after surgical repair of a penetrating cardiac injury. To our knowledge, this is the first reported case of isolated right ventricle myocardial abscess after penetrating cardiac injury.
1 Introduction#
Myocardial abscess is a life-threatening condition characterized by a suppurative infection of the myocardial tissue. It most commonly develops through direct extension from an adjacent infected structure, as seen in cases of infective endocarditis or, less frequently, pericarditis, or through dissemination during bacteriemia[1,2]. In the latter scenario, it usually manifests as a complication of myocardial infarction, cardiac pseudoaneurysm or hematoma[3]. The most common localizations are the left ventricular wall and the interventricular septum. The incidence of isolated myocardial abscesses remains elusive due to their extreme rarity, with only few documented cases. Although myocardial abscesses without infective endocarditis can lead to clinical manifestations (as persistent fever or EKG abnormalities), they are often clinically silent, contributing to a relatively high rate of occasional or post-mortem diagnosis[4].
Herein we report the case of a 43-year-old woman who presented with a right ventricle myocardial abscess six months after undergoing surgical repair of a penetrating cardiac injury.
2 Case Presentation#
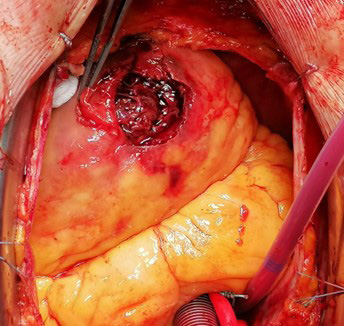
A 43-year-old woman was rescued at home after stabbing. Upon arrival at the Emergency Department, she was in profound hemorrhagic shock. Multiple penetrating wounds were present, mostly involving the left lateral and posterior chest and the left superior limb. One of the chest wounds was parasternal, located in the left fifth intercostal space. Transthoracic echocardiography revealed severe hemopericardium with signs of cardiac tamponade. During emergent cardiac surgery, a 3-cm lesion in the right ventricle was identified (Figure 1). Repair was successfully performed using interrupted 3-0 polypropylene sutures reinforced with two Teflon strips. Post-operative course was uneventful, and the patient was discharged on the fifth post-operative day.
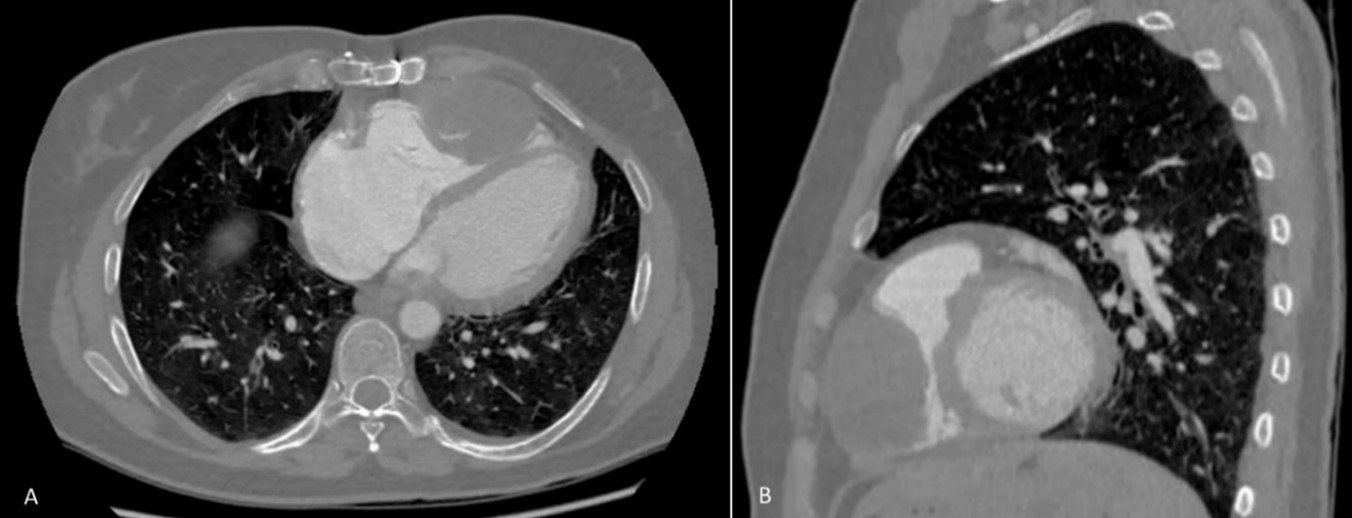
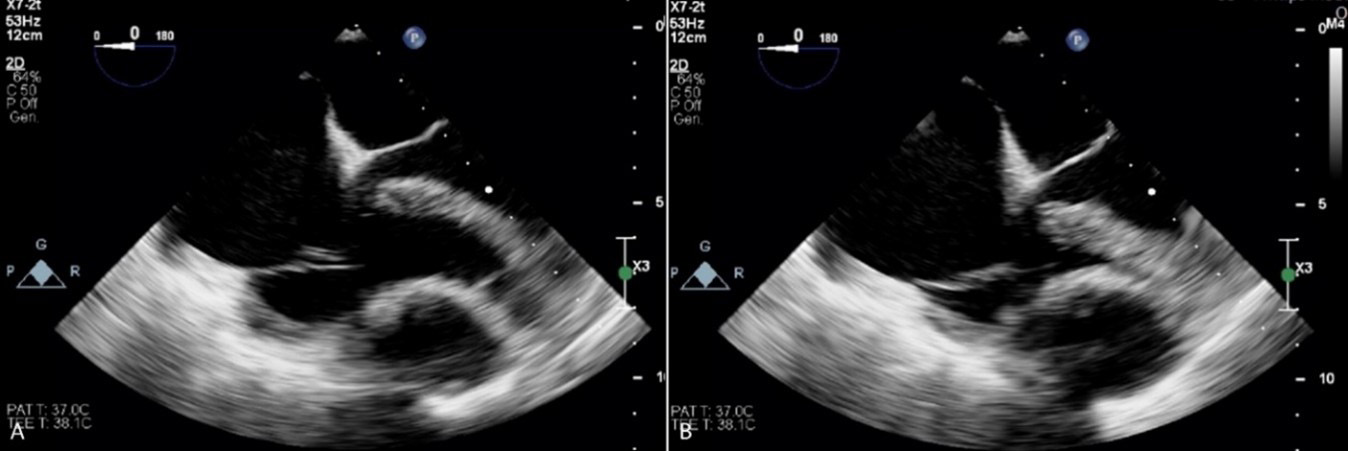
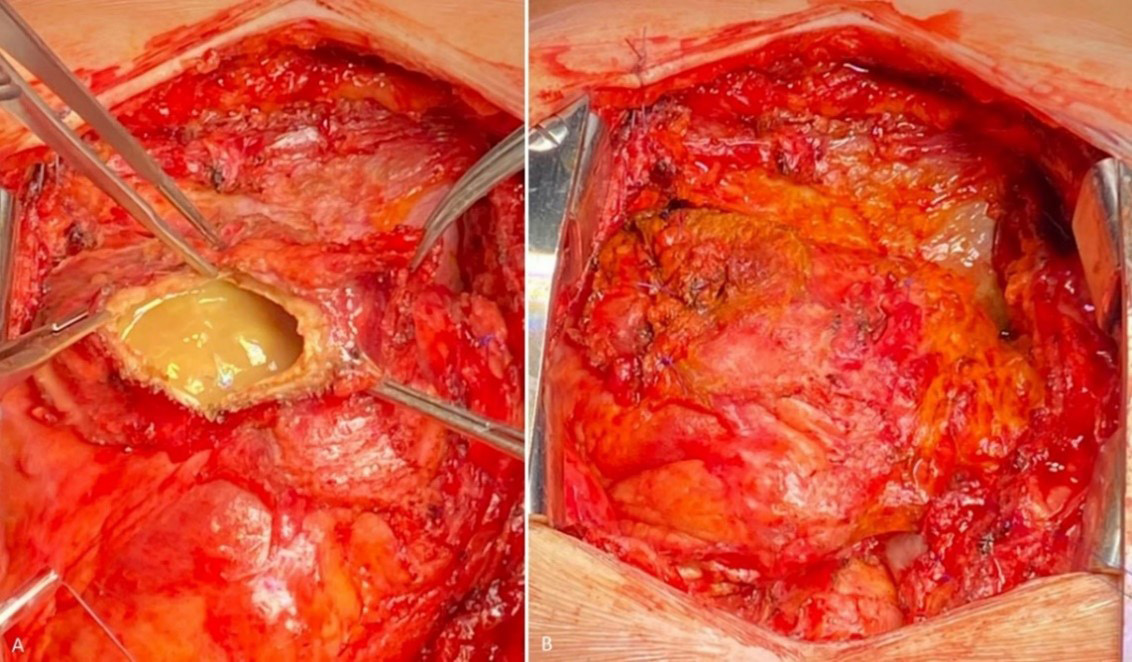
Six months later, the woman presented at the Emergency Department complaining of chest pain and dyspnea. Blood tests including inflammatory markers, EKG, and a chest X-ray were unremarkable. Chest CT-scan was then performed, showing a subepicardial right ventricular oval formation (5.2 x 3.8 x 5.6 cm), with light contrast wall enhancement and fluid content, compressing the right ventricle cavity (Figure 2). Transesophageal echocardiography was consistent with this finding (Figure 3). After uneventful re-sternotomy and lysis of adhesions, the formation was identified in the anterior mid-apical wall of the right ventricle. The right atrium and ascending aorta were prepared for eventual emergent cardiopulmonary bypass. The cavity was incised, revealing purulent content. The abscess was completely evacuated, and specimens were sent for microbiological analysis. The right ventricle wall integrity was restored with interrupted 4-0 polypropylene sutures (Figure 4).
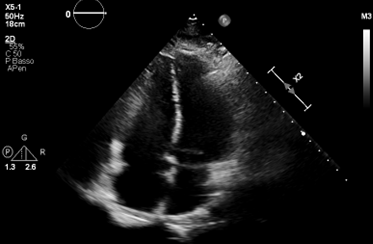
Intravenous, empirical broad-spectrum antibiotic therapy with vancomycin and piperacillin/tazobactam was initiated. On the first post-operative day, the patient was transferred to the step-down unit, and chest drains were removed. Microbiological analysis of drained fluid yielded negative results, as did blood cultures. Throughout the post-operative course, the patient remained afebrile. Blood inflammatory markers showed only slight elevation, steadily decreasing in the subsequent days until normalization. Post-operative transthoracic echocardiography revealed good biventricular function and absence of residual infection (Figure 5). On post-operative day 11, the patient was transferred to a cardiac rehabilitation facility, where intravenous antibiotic therapy continued until post-operative day 30. Prior to discontinuation, a PET-CT scan was performed to exclude infection dissemination. At 2-month follow-up, the patient was asymptomatic; transthoracic echocardiography showed no recurrence.
3 Discussion#
Myocardial abscesses are typically found in patients affected by infective endocarditis[3]. Myocardial abscesses without infective endocarditis are exceedingly rare and mainly consist of abscesses located in an infarcted area of the left ventricle wall or post-mortem findings in patients who died from sepsis[5-7]. We found only one published case of an isolated right ventricle myocardial abscess, which occurred in a 3-year-old child diagnosed with leg osteomyelitis[8]. To our knowledge, this is the first reported case of an isolated right ventricle myocardial abscess following a penetrating cardiac injury.
A recent report described the case of an incidental intraoperative diagnosis of a left ventricle myocardial abscess in a 47-year-old man who underwent elective aortic valve replacement[9]. Similarly, in our case, the patient did not present signs of infection. She remained persistently afebrile, and blood inflammatory markers were within the normal range. Considering that clinical presentation and initial routine tests may often be unremarkable, a high index of suspicion for infection should be maintained in patients with a history of penetrating cardiac injury. In such cases, a chest CT scan may be highly valuable for diagnosis and surgical treatment planning.
4 Conclusion#
Myocardial abscesses are a rare complication of penetrating cardiac injuries. Since the clinical presentation can be subtle, maintaining a high index of suspicion is important for timely diagnosis and effective treatment.
Declarations
⚖Ethics statement
✓Patient consent
€Funding
✎Author contributions
◎Competing interests
Article information
- Published
Copyright © 2025 Alessio Rungatscher MD PhD. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 9#
- 1
Walker N, Bhan A, Desai J, Monaghan MJ. Myocardial abscess: a rare complication of valvular endocarditis demonstrated by 3D contrast echocardiography. Eur J Echocardiogr J Work Group Echocardiogr Eur Soc Cardiol. 2010;11(10):E37. doi:10.1093/ejechocard/jeq090.
- 2
Yoon JK, Rahimi MB, Fiore A, Schowengerdt K, Jureidini SB. Bacterial pancarditis with myocardial abscess: successful surgical intervention in a 14-month-old boy. Tex Heart Inst J. 2015;42(1):55-57. doi:10.14503/THIJ-13-3685.
- 3
Chakrabarti J. Diagnostic evaluation of myocardial abscesses. A new look at an old problem. Int J Cardiol. 1995;52(3):189-196. doi:10.1016/0167-5273(95)02484-0.
- 4
Sanson J, Slodki S, Gruhn JG. MYOCARDIAL ABSCESSES. Am Heart J. 1963;66:301-308. doi:10.1016/0002-8703(63)90260-6.
- 5
Behnam R, Walter S, Hanes V. Myocardial abscess complicating myocardial infarction. J Am Soc Echocardiogr Off Publ Am Soc Echocardiogr. 1995;8(3):334-337. doi:10.1016/s0894-7317(05)80045-8.
- 6
Grant R, Page S, Iyer A. Contained myocardial abscess following a myocardial infarction. J Card Surg. 2018;33(3):144-145. doi:10.1111/jocs.13555.
- 7
Ryon DS, Pastor BH, Myerson RM. Abscess of the myocardium. Am J Med Sci. 1966;251(6):698-705.
- 8
Ahmad T, Pasarad AK, Kishore KS, Maheshwarappa NN. Right ventricular wall abscess in structurally normal heart after leg osteomyelitis: First case. Asian Cardiovasc Thorac Ann. 2016;24(7):692-695. doi:10.1177/0218492315589670.
- 9
Garg M, Bhargava J, Garg M, Garg S. Isolated myocardial abscess cavity: An incidental finding on intraoperative transesophageal echocardiography. Ann Card Anaesth. 2021;24(3):411-414. doi:10.4103/aca.ACA_136_19