Anatomic variations of terminal portion of Thoracic Duct: A systematic review
Adilson J.M. de Oliveira1 ✉
Adilson J.M. de OliveiraCorresponding author- 1 CEDUMED Department, Agostinho Neto University Medical School, Luanda, Angola; Neurosurgery Discipline, Jean Piaget University Medical School, Luanda, Angola
Mario Gilberto Siqueira2
Mario Gilberto Siqueira- 2 Peripheral Nerves Surgery Unit, Department of Neurosurgery, University of São Paulo Medical School, São Paulo, SP, Brazil
Lissa Éllen Pereira Sousa3
Lissa Éllen Pereira Sousa- 3 Anhembi Morumbi University Medical School, São Paulo, Brazil
Pedro Gonçalves Alcantara4
Pedro Gonçalves Alcantara- 4 Caxias do Sul University Medical School, Rio Grande do Sul, Angola
Pedro Lucas Carneiro Ferreira4
Pedro Lucas Carneiro Ferreira- 4 Caxias do Sul University Medical School, Rio Grande do Sul, Angola
Show affiliations (4)
- 1CEDUMED Department, Agostinho Neto University Medical School, Luanda, Angola; Neurosurgery Discipline, Jean Piaget University Medical School, Luanda, Angola
- 2Peripheral Nerves Surgery Unit, Department of Neurosurgery, University of São Paulo Medical School, São Paulo, SP, Brazil
- 3Anhembi Morumbi University Medical School, São Paulo, Brazil
- 4Caxias do Sul University Medical School, Rio Grande do Sul, Angola
Published
Abstract
BackgroundThe thoracic duct (TD) is the largest lymphatic vessel responsible for returning lymph and chyle to the venous system. Its terminal anatomy shows notable variability, which has clinical implications for surgeries and interventions in the cervical and thoracic regions.
ObjectiveTo systematically review anatomical studies on the terminal portion of the TD, identifying and categorizing variations in its termination site.
MethodsA systematic review of nine anatomical studies involving 406 human cadavers was conducted. Data on the TD termination sites were extracted and analyzed to assess variability and prevalence.
ResultsThe venous angle, defined as the junction of the left internal jugular and subclavian veins, was the most frequent termination site, observed in approximately 63% of cases. The left internal jugular vein and left subclavian vein were less commonly reported as termination sites, accounting for 18% and 2% of cases, respectively. The remaining cases showed a variety of anatomical variations or lacked a clear dominant pattern.
ConclusionsSignificant variability exists in the terminal anatomy of the TD, emphasizing the need for clinicians to be aware of these differences to reduce surgical risks. Further research with larger samples and modern techniques is warranted to enhance anatomical understanding and improve clinical outcomes.
1 Introduction#
The thoracic duct (TD) is the largest lymphatic vessel in the human body and plays a key role in returning lymph and chyle to the systemic venous circulation. It usually measures between 38 and 45 cm in length and 2 to 5 mm in diameter.1 The duct begins in the abdomen at the upper part of the cisterna chyli, located behind the abdominal aorta and in front of the first and second lumbar vertebrae. This structure is formed by the joining of the right and left lumbar trunks along with the intestinal trunk.2,3
From there, the TD follows a complex and variable path. It ascends through the aortic hiatus of the diaphragm into the posterior mediastinum, traveling upward between the thoracic aorta and azygos vein, just behind the esophagus. Near the seventh cervical vertebra, it curves laterally and forward, usually arching behind the left carotid sheath and rising a few centimeters above the clavicle before draining into the venous system—most commonly at the junction of the left internal jugular and subclavian veins, known as the left venous angle.4,5
Despite this general pattern, the terminal segment of the thoracic duct shows significant anatomical variation. Variations include differences in drainage sites, the presence of one or multiple terminal branches, duplication or even triplication of the duct, and alternate drainage into veins such as the external jugular, vertebral, or brachiocephalic veins. The number and position of valves near the termination can also vary.5,6 These differences are particularly important in clinical contexts such as neck dissections, thoracic surgeries, central venous catheter placement, and lymphatic imaging. Injury to the TD during these procedures may lead to complications like chylothorax or chylous fistula, which can significantly affect recovery.7
Although the clinical importance of the thoracic duct’s terminal anatomy is clear, it is often overlooked in surgical and radiological practice. Because of the wide range of anatomical patterns reported, a thorough synthesis of existing studies is necessary to support clinical decisions and education. This systematic review aims to collect and classify the anatomical variations of the thoracic duct’s terminal portion, examining their frequency, morphology, and relevance for clinical practice.8,9
2 Methods#
This systematic review was conducted in accordance with the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) guidelines. The aim was to identify, synthesize, and analyze anatomical variations in the terminal portion of the thoracic duct in humans, based on cadaveric and clinical studies.
2.1 Eligibility Criteria#
Studies were included if they met the following criteria:
- Original research articles published in English;
- Conducted on adult human subjects or cadaveric specimens;
- Provided explicit anatomical descriptions of the thoracic duct termination, including its venous drainage site, number of terminal branches, and positional variants.
The following were excluded:
- Studies not describing the terminal portion of the thoracic duct;
- Review articles, case reports, editorials, letters to the editor, conference abstracts, and animal studies.
2.2 Information Sources and Search Strategy#
A comprehensive literature search was conducted in two electronic databases: PubMed and Google Scholar. The final search was performed in April 2025, and no restrictions were placed on publication date.
The search strategy used the terms:
“Thoracic Duct” AND (“Anatomy” OR “Variations”)
In both databases, filters were applied to restrict results to:
- Studies in English;
- Studies involving human subjects (in vivo or cadaveric).
2.3 Study Selection#
After deduplication, all titles and abstracts retrieved from the databases were screened independently by two reviewers. Full-text articles were obtained for all studies meeting the inclusion criteria or when abstracts provided insufficient detail. Disagreements were resolved through discussion or by consulting a third reviewer.
2.4 Data Extraction#
Two reviewers independently extracted data using a standardized form. Extracted variables included:
- Author(s) and publication year;
- Study type and population (cadaveric vs. clinical);
- Sample size;
- Anatomical method used (e.g., dissection, imaging, surgical report);
- Description of the thoracic duct termination: number of ducts, site of venous drainage, presence of anatomical variations.
2.5 Data Synthesis#
Due to heterogeneity in study designs and reported outcomes, a qualitative synthesis was performed. Identified anatomical variations were categorized based on the number of terminal ducts and the specific veins into which they drained.
3 Results#
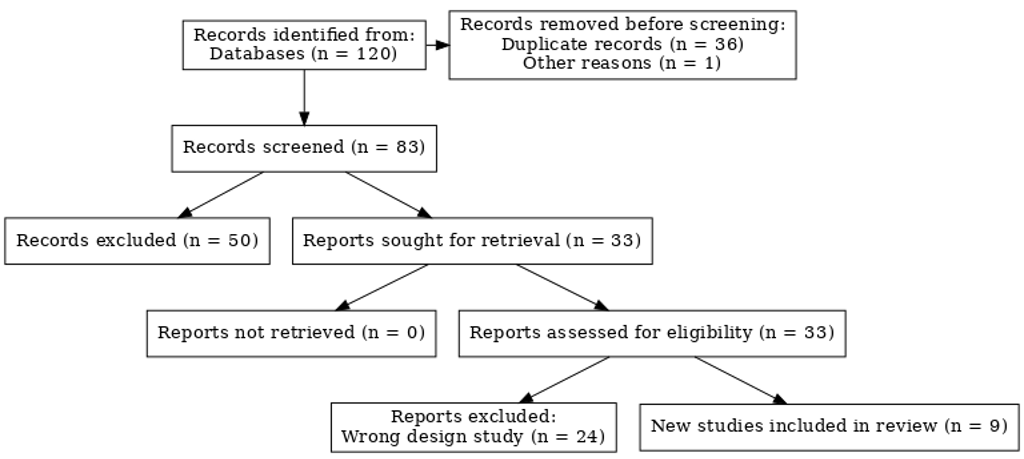
A total of 120 records were identified through databases. After removing duplicates and irrelevant studies, 33 full-text reports were assessed, with 24 excluded due to inappropriate study design. Nine studies were ultimately included in the final synthesis. As it is in figure 1.
Nine anatomical studies were reviewed, covering a total of 406 human cadavers. The most common termination sites of the thoracic duct (TD) differed across studies and geographic areas.10-18
In most cases, the TD ended at the venous angle (VA)—the junction of the left internal jugular and left subclavian veins— reported in five studies and observed in 255 of the 406 specimens (62.8%). Two studies found the left internal jugular vein (LIJV) as the most frequent site, totaling 73 cadavers (18.0%). Termination into the left subclavian vein (LSV) was noted in nine specimens (2.2%) in a single study. The remaining 17% included varied anatomical descriptions or cases where no clear dominant pattern was identified.
The table 1 summarizes each study, including the country of origin, year, specimen type (fresh or formalin-fixed), sample size, and the most frequently observed termination site.
Table 1 Thoracic Duct Termination in included studies.
| Author | Country | Year | Type of Specimens | N | More frequent Termination of TD | % |
|---|---|---|---|---|---|---|
| Davis, H | EUA | 1915 | Fresh | 22 | Venous Angle | 100 |
| Greenfield and Gottlieb | EUA | 1956 | Fresh | 25 | Internal Jugular Vein | 100 |
| Shimada, K | Japan | 1997 | Formalin-fixed | 100 | Venous Angle | 38 |
| Langford, R | United Kingdom | 1999 | Formalin-fixed | 24 | Venous Angle | 64.3 |
| Akali, O | Turkey | 2006 | Formalin-fixed | 9 | Subclavian vein | 100 |
| Thirupathirao, V | India | 2013 | Formalin-fixed | 45 | Venous Angle | 100 |
| Louzada, A | Brazil | 2016 | Fresh | 25 | Venous Angle | 60 |
| Bapuji, P | India | 2018 | Formalin-fixed | 45 | Internal Jugular Vein | 42.2 |
| Rabattu, P | France | 2021 | Formalin-fixed | 70 | Venous Angle | 52 |
4 Discussion#
The anatomy of the terminal portion of the thoracic duct has long been described as variable,4 and this review reinforces just how much that variability matters—especially in clinical practice. While certain patterns are frequently mentioned in the literature, the truth is that anatomical presentations can differ considerably depending on how, when, and even in what condition the body was studied.19-21 This highlights the importance of considering methodological aspects, such as specimen preservation and dissection techniques, when interpreting anatomical data.
Understanding this region in detail goes far beyond academic interest. In surgeries involving the lower cervical region—like neck dissections, thoracic inlet access, or even routine placement of central venous catheters—having a precise idea of where the thoracic duct is likely to terminate can make the difference between a smooth procedure and a serious complication.22,23 Injuries to the duct can result in conditions like chylothorax or persistent lymphatic leaks, both of which can significantly affect recovery. 22,23 When surgeons are aware of potential variations, they’re better prepared to avoid or manage these issues.22-24
One of the challenges we encountered while reviewing the literature was the age and inconsistency of many of the studies. Several were conducted decades ago, with small sample sizes and without the benefit of modern tools that can enhance anatomical accuracy—such as high-resolution imaging or fluorescence-guided dissection. Additionally, the frequent use of formalin-fixed specimens raises concerns, as tissue changes due to fixation can obscure delicate structures and lead to misinterpretation.
There’s a clear need for new anatomical studies that use up-to-date methodologies, larger and more diverse sample populations, and ideally, a combination of cadaveric and imaging-based approaches. As our surgical techniques evolve, so too should our anatomical knowledge—grounded in evidence that reflects current clinical reality. Investing in this kind of research not only fills gaps in our understanding but also translates directly into better, safer care for patients.
Comparing the data from the present systematic review with the largest series of dissections in fresh cadavers, which included a sample size of 73 specimens25 , it is understood that there are likely two predominant anatomical patterns in most individuals. In that study, among the 72 specimens analyzed, the thoracic duct terminated in the internal jugular vein in 50% of cases and at the venous angle in 45% of cases.25 These were also the two most prevalent anatomical locations reported in the studies included in the review.
5 Conclusion#
This review shows that the terminal anatomy of the thoracic duct is more variable than traditionally described. Although the venous angle remains a commonly reported drainage site, the range of variations observed across studies highlights the need for careful anatomical consideration in clinical practice
Article information
- Published
Copyright © 2026 Adilson J.M. de Oliveira. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 25#
- 1
Ammar K, Tubbs RS, Smyth MD, Wellons JC 3rd, Blount JP, Salter G, Oakes WJ. Anatomic landmarks for the cervical portion of the thoracic duct. Neurosurgery. 2003 Dec;53(6):1385-7; discussion 1387-8. doi: 10.1227/01.neu.0000093826.31666.a5.
- 2
Skandalakis JE, Skandalakis LJ, Skandalakis PN. Anatomy of the lymphatics. Surg Oncol Clin N Am. 2007 Jan;16(1):1-16. doi: 10.1016/j.soc.2006.10.006.
- 3
Derakhshan A, Lubelski D, Steinmetz MP, Corriveau M, Lee S, Pace JR, Smith GA, Gokaslan Z, Bydon M, Arnold PM, Fehlings MG, Riew KD, Mroz TE. Thoracic duct injury following cervical spine surgery: a multicenter retrospective review. Global Spine J. 2017 Apr;7(1 Suppl):115S-119S. doi: 10.1177/2192568216688194.
- 4
Langevin HM, Huijing PA. Communicating about fascia: history, pitfalls, and recommendations. Int J Ther Massage Bodywork. 2009 Dec 7;2(4):3-8. doi: 10.3822/ijtmb.v2i4.63.
- 5
Hematti H, Mehran RJ. Anatomy of the thoracic duct. Thor Surg Clin. 2011 May 1;21(2):229-38. doi: 10.1016/j.thorsurg.2011.01.002.
- 6
Gottlieb Mi, Greenfield J. Variations in the terminal portion of the human thoracic duct. AMA Arch Surg. 1956 Dec;73(6):955-9. doi: 10.1001/archsurg.1956.01280060055012.
- 7
Delaney SW, Shi H, Shokrani A, Sinha UK. Management of Chyle Leak after head and neck surgery: review of current treatment strategies. Int J Otolaryngol. 2017;2017:8362874. doi: 10.1155/2017/8362874.
- 8
Allen DP, Briggs CE. Wounds of the thoracic duct occurring in the neck: report of two cases; resume of seventeen cases. Am J Med 1969; 401-4.
- 9
Leung S, Zlotolow DA, Kozin SH, Abzug JM. Surgical Anatomy of the supraclavicular brachial plexus. J Bone Joint Surg Am. 2015 Jul 1;97(13):1067-73. doi: 10.2106/JBJS.N.00706.
- 10
Davis H. (1915). The thoracic duct in man. Journal of Anatomy, 49(3), 259–270.
- 11
Greenfield LJ, Gottlieb RO. (1956). Lymphatic termination in man. Surgery, 39(2), 293–302.
- 12
Shimada K. (1997). Anatomic variations of the thoracic duct termination. Okajimas Folia Anatomica Japonica, 74(4), 205–210.
- 13
Langford R. (1999). Anatomical variations in the termination of the thoracic duct: cadaveric study. Clinical Anatomy, 12(2), 124–129.
- 14
Akalın O. (2006). Anatomical study of thoracic duct variations in Turkish cadavers. Surgical and Radiologic Anatomy, 28(1), 77–81.
- 15
Umeshchandra V. (2013). Terminal course of the thoracic duct in Indian cadavers. Indian Journal of Anatomy, 2(1), 12–16.
- 16
Louzada, A.C.S., Lim, S.J., Pallazzo, J.F. et al. Biometric measurements involving the terminal portion of the thoracic duct on left cervical level IV: an anatomic study. Anat Sci Int 91, 274–279 (2016). https://doi.org/10.1007/s12565-015-0295-9.
- 17
Baguli P. (2018). Morphological study of the thoracic duct termination in Eastern India. Journal of Clinical and Diagnostic Research, 12(5), AC01–AC04.
- 18
Babuty P. (2021). Cadaveric dissection of thoracic duct terminal anatomy in France. Annales d’Anatomie, 233, 151627.
- 19
Bellier A, Pardo Vargas JS, Cassiba J, Desbrest P, Guigui A, Chaffanjon P. Anatomical variations in distal portion of the thoracic duct - a systematic review. Clin Anat. 2020 Jan;33(1):99-107. doi: 10.1002/ca.23476.
- 20
O’Hagan LA, Windsor JA, Itkin M, Russell PS, Phillips AR, Mirjalili SA. The lymphovenous junction of the thoracic duct: a systematic review of its structural and functional anatomy. Lymphat Res Biol. 2021 Jun 1;19(3):215-22. doi: 10.1089/lrb.2020.0010.
- 21
Delaney SW, Shi H, Shokrani A, Sinha UK. Management of Chyle Leak after head and neck surgery: review of current treatment strategies. Int J Otolaryngol. 2017;2017:8362874. doi: 10.1155/2017/8362874.
- 22
Jortay A, Bisschop P. Bilateral chylothorax after left radical neck dissection. Acta Otorhinolaryngol Belg. 2001;55(4):285-9.
- 23
Stuart WJ. Operative injuries of the thoracic duct in the neck. Edinb Med J. 1907 Oct;22(4):301-17.
- 24
Nussenbaum B, Liu JH, Sinard RJ. Systematic management of chyle fistula: the Southwestern experience and review of the literature. Otolaryngol Head Neck Surg. 2000 Jan;122(1):31-8. doi: 10.1016/S0194-5998(00)70174-4.
- 25
Oliveira AJM de. Anatomia retro e supraclavicular do ducto torácico aplicada à cirurgia de plexo braquial [Internet]. 2024;[citado 2025 maio 30 ] Available from: https://www.teses.usp.br/teses/disponiveis/5/5138/tde-28012025-174340/