Chronic Cervical Pain and the Prefrontal Cortex: Impacts on Cervical Movements and Verticality Perception
Luciane Aparecida Pascucci Sande de Souza ✉
Luciane Aparecida Pascucci Sande de SouzaCorresponding author- Department of Applied Physical Therapy, Federal University of Triângulo Mineiro (UFTM), Uberaba, Minas Gerais, Brazil.
Show affiliations (1)
- Department of Applied Physical Therapy, Federal University of Triângulo Mineiro (UFTM), Uberaba, Minas Gerais, Brazil.
Published
Abstract
Chronic neck pain is one of the leading causes of disability worldwide, resulting in functional deficits and significant public health impacts. Its long-term presence leads to proprioceptive difficulties, muscle fatigue, and impaired sensorimotor integration, both peripherally and centrally. This study investigated changes in prefrontal cortex activation during cervical movements and its association with verticality perception in individuals with chronic neck pain. A cross-sectional study was conducted with 16 volunteers (8 with pain and 8 healthy controls), aged 18 to 59, matched by age and sex. Assessments included prefrontal cortex activation using fNIRS during cervical movements, subjective visual vertical (SVV) test, joint position sense (JPE) test, pain intensity, and neck disability index (NDI). No significant differences were found in prefrontal cortex activation, SVV, or JPE between groups. However, the healthy group showed a high correlation (R > 0.7) between brain activation and cervical movements, a pattern absent in the pain group, which had a median pain score of 6.25 (VAS) and mild to moderate disability (NDI = 15.87). The absence of intragroup correlation in individuals with pain suggests compensatory neuromuscular or sensory adaptations, which may be detrimental over time. These findings indicate that individuals with chronic neck pain and mild to moderate disability do not exhibit changes in prefrontal cortex activation or verticality perception, but may develop adaptive mechanisms that warrant further investigation.
1 Introduction#
Neck pain is defined as a painful condition located between the superior nuchal line and the spinous processes of the first thoracic vertebra, potentially affecting other skeletal segments such as the upper limbs, head, and trunk[1]. When chronic, this pain persists for more than 12 weeks without complete recovery, with a prevalence of approximately 8% in the Western population. About 23% of cases last more than a month, and 48% persist for over a year, being more common in women than in men across all age groups[2, 3]. Consequently, diagnosis and treatment often extend over long periods, resulting in increased work absenteeism and higher costs associated with managing the condition[2].
This condition is associated with functional impacts, such as reduced mobility, impaired movement coordination, and neurological signs, which compromise neck functionality and quality of life[1, 2]. Over time, individuals with this condition tend to develop proprioceptive alterations[4], resulting from increased fatigue, reduced functionality, and imbalance between superficial and deep cervical muscles, leading to sensorimotor and postural dysfunctions[5]. Given the wide variety of symptoms and the scarcity of effective treatments, research has shifted focus to central alterations, considering structural and functional changes in different areas of the central nervous system, rather than focusing solely on the musculoskeletal system[6].
The prefrontal cortex has become a focus of research on chronic pain, particularly due to the long-term impact of this condition. Beyond physical impairments, chronic pain affects cognitive and emotional functions and is associated with disorders such as anxiety and depression[7]. This brain region is involved not only in motor planning but also in pain anticipation and discomfort[8], as well as in modulating anxiety symptoms triggered by this condition[9]. Studies show that individuals with chronic low back pain, for example, exhibit alterations in prefrontal cortex activity, the intensity of which varies with pain severity[10].
In the context of chronic neck pain, a case-control study by Zoete et al. (2021) investigated individuals with idiopathic chronic neck pain and observed reduced volume and cortical thickness in brain regions, including the prefrontal, frontal, parietal, occipital, and temporal cortices. These alterations were correlated with pain intensity and depressive symptoms. Another study by Zhang et al. (2024) identified extensive central remodeling, with altered functional activity in various areas, particularly the prefrontal cortex, associated with functional disability and emotional factors.
Although the impact of chronic neck pain on brain alterations is widely studied, there remains a need for investigations correlating these dysfunctions with other variables, such as neck movement itself. This approach could elucidate potential changes in brain activity during movements that cause pain, as well as difficulties in postural orientation[5]. Such findings could contribute to a broader understanding of the mechanisms involved and the development of more precise and effective therapeutic interventions.
In this sense, verticality perception depends on the integration of the central nervous system with the vestibular, visual, and particularly proprioceptive systems from neck muscles and joints. When any of these systems is altered, as in chronic neck pain, there is a distortion in verticality perception[5]. A meta-analysis by Gaitán et al. (2020) on visual verticality perception in spinal diseases highlighted the scarcity of studies focused on the cervical spine and the need for a better understanding of proprioceptive and postural alterations in this population.
Therefore, this study aims to investigate whether changes occur in prefrontal cortex activation during cervical movements and whether these changes are correlated with verticality perception in individuals with chronic neck pain.
2 Materials and Methods#
2.1 Trial design, location, and setting#
This observational cross-sectional study was approved by the research ethics committee (CAAE: 74740323.3.0000.5154) and followed the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines. The study was conducted at the Neuroscience and Motor Control Laboratory (NEUROCOM) of the Federal University of Triângulo Mineiro (UFTM) in Uberaba, Minas Gerais, Brazil, starting in March 2023
2.2 Participants#
Participants aged 18 to 59 years, of both sexes, were recruited through social media and personal contact. The chronic neck pain group included individuals with self-reported pain for more than three months, without traumatic, neurological, or musculoskeletal causes, while the control group consisted of healthy individuals without neck pain, matched by age and sex. Exclusion criteria included fractures, neoplasms, spinal stenosis, neurological or cognitive dysfunctions, and cervical trauma. All participants were literate and signed the Informed Consent Form.
2.3 Assessments#
In individuals with chronic neck pain, pain intensity was quantified using two tools: the Visual Analog Scale (VAS) and the Neck Disability Index (NDI). The VAS allows individuals to subjectively report pain intensity on a scale from 0 to 10, where 0 represents “no pain” and 10 corresponds to “the worst pain possible”[14]. The NDI is a questionnaire composed of 10 sections assessing aspects such as pain intensity, personal care, lifting capacity, reading, headaches, concentration, work, driving, sleep, and leisure. Each item is scored from 0 to 5, totaling a maximum score of 50 points. Based on the final score, functional disability is classified as: none (0-4), mild (5-14), moderate (15-24), severe (25-34), or complete (>34)[15].
For both groups, assessments included prefrontal cortex activation during cervical movements, joint position sense (JPS), and subjective visual vertical (SVV).
Cortical activity was assessed using functional Near-Infrared Spectroscopy (fNIRS), which measures cerebral oxygenation through infrared light emission. The device was positioned on the frontal region of the head, following the international 10-20 EEG system, with sensors at Fp1 and Fp2. The emitted infrared light penetrates brain tissue, interacts with oxygenated (HbO2) and deoxygenated hemoglobin (Hb), and returns to the receiver, allowing indirect calculation of brain activity[16]. Readings were taken for 60 seconds for each cervical movement, with initial measurements at rest (20 seconds in a neutral position) and during movement execution. Data were collected in JSON format and analyzed using MONGOGB and Excel software for extraction and statistical analysis.
Verticality perception was assessed using an opaque bucket, without light entry, with a vertical red line on the internal bottom aligned at 0° of a digital inclinometer (Clinometer App, Tue Nguyen Minh). The participant, seated with their head vertically aligned, was instructed to identify when the line was at true vertical after random bucket movements (three clockwise and three counterclockwise movements, up to 30°). Angular error was recorded on the external scale of the bucket, providing data on the individual’s ability to perceive verticality in an environment without visual references[17, 18].
Joint position sense was assessed using a laser headband and a 40x40 cm target positioned 90 cm from the participant. The volunteer was instructed to perform cervical movements (flexion, extension, left and right lateral rotation) and return to the initial position (center of the target) three times with eyes open and three times with eyes closed. (Figure 1).
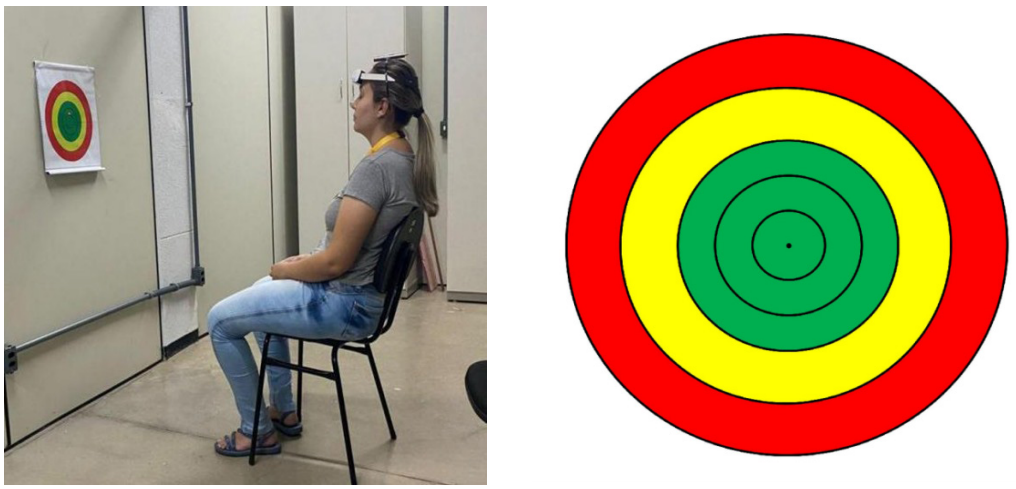
Note: a) volunteer positioning b) target Source: author’s, 2024
The final position was marked on the target, and the angular deviation was calculated using the Pythagorean theorem (C = √(x2 + y2)) and converted into degress ( (α = tan- 1(c/90))[19]. The average angular deviations were used for analysis. (Figure 2)
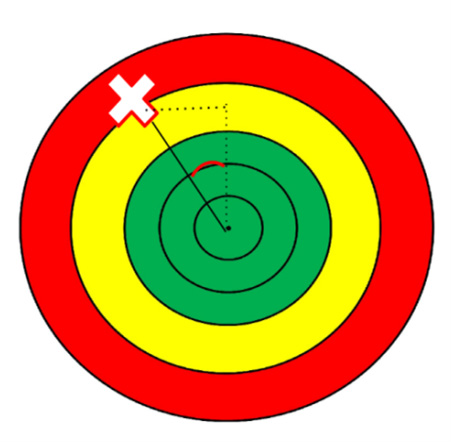
Source: author’s, 2024
3 Statistical Analysis#
Data were assessed for normality using the Shapiro-Wilk test. Descriptive statistics were used for sample characterization. For between-group analysis, the Mann-Whitney U test was used. To verify possible associations within each group, Pearson’s correlation test was used. Statistical significance was set at p ≤ .05. Data were analyzed using Statistica 7.0.
4 Results#
The study included 16 individuals, 8 with chronic neck pain and 8 healthy controls, with a mean age of 27 years and an average BMI of 28.36. Both groups showed deviations in verticality perception within the normal range (-2.5° to 2.5°)[20]. In the pain group, the median pain intensity was 6.25 (VAS), and the level of functional disability (NDI) was classified as mild to moderate (median = 15.87/50). (Table 1).
Table 1 Sample Characterization.
| Variables | In pain (n=8) | No dor (n=8) | General (n=16) |
|---|---|---|---|
| Age (years) | 27 (21-37) | 27 (21-37) | 27 (21-37 ) |
| Sex | |||
| Male, n (%) | 2 (12,5) | 2 (12,5 ) | 4 (25) |
| Female, n (%) | 6 (37,5) | 6 (37,5) | 12 (12,5) |
| IMC | 29.40 | 27.22 | 28.36 |
| SVV (°) | 1,125 (0- 1,5) | 0,812 (0-1) | 0,968 (0-2) |
Legend: Cm: centimeters; n: number; Kg: kilograms; (1) p value of comparison between the group with pain and asymptomatic
No significant differences were observed in prefrontal cortex activation during cervical movements (flexion, extension, lateral rotation) between groups (U = 28.17; p = 0.70). However, intragroup analysis revealed distinct patterns: the healthy group showed a strong correlation (R > 0.7)[21] between brain activation and cervical movements, while the pain group did not demonstrate a clear activation pattern. (Tables 2 and 3).
Table 2 Intragroup Correlation of Prefrontal Cortex Activation Level in Asymptomatic Individuals.
| OF | CF | OE | CE | OLR L | CLR L | OLR R | CLR R | |
|---|---|---|---|---|---|---|---|---|
| OF | 1,00 | 0,97 | 0,93 | 0,93 | 0,90 | 0,91 | 0,92 | 0,93 |
| CF | 0,97 | 1,00 | 0,90 | 0,92 | 0,88 | 0,89 | 0,91 | 0,92 |
| OE | 0,93 | 0,90 | 1,00 | 0,90 | 0,98 | 0,98 | 0,98 | 0,94 |
| CE | 0,93 | 0,92 | 0,90 | 1,00 | 0,85 | 0,87 | 0,90 | 0,91 |
| OLR L | 0,90 | 0,88 | 0,98 | 0,85 | 1,00 | 0,98 | 0,97 | 0,93 |
| CLR L | 0,91 | 0,89 | 0,98 | 0,87 | 0,98 | 1,00 | 1,00 | 0,97 |
| OLR R | 0,92 | 0,91 | 0,98 | 0,90 | 0,97 | 1,00 | 1,00 | 0,98 |
| CLR R | 0,93 | 0,92 | 0,94 | 0,91 | 0,93 | 0,97 | 0,98 | 1,00 |
Source: author’s, 2025
Legend: OF: flexion with eyes open; CF: flexion with eyes closed; OE: extension with eyes open; CE: extension with eyes closed; OLR L: left lateral rotation with eyes open; CLR L: right lateral rotation with eyes closed; OLR R: right lateral rotation with eyes open; CLR R: lateral rotation with eyes closed.
Table 3 Intragroup Correlation of Prefrontal Cortex Activation Level in Individuals with Chronic Neck Pain.
| OF | CF | OE | CE | OLR L | CLR L | OLR R | CLR R | |
|---|---|---|---|---|---|---|---|---|
| OF | 1,00 | -0,19 | 0,77 | 0,70 | 0,74 | 0,70 | 0,64 | 0,68 |
| CF | -0,19 | 1,00 | -0,12 | -0,14 | 0,15 | 0,01 | 0,11 | 0,04 |
| OE | 0,77 | -0,12 | 1,00 | 0,97 | 0,81 | 0,92 | 0,89 | 0,95 |
| CE | 0,70 | -0,14 | 0,97 | 1,00 | 0,87 | 0,94 | 0,93 | 0,96 |
| OLR L | 0,74 | 0,15 | 0,81 | 0,87 | 1,00 | 0,91 | 0,95 | 0,92 |
| CLR L | 0,70 | 0,01 | 0,92 | 0,94 | 0,91 | 1,00 | 0,97 | 0,99 |
| OLR R | 0,64 | 0,11 | 0,89 | 0,93 | 0,95 | 0,97 | 1,00 | 0,99 |
| CLR R | 0,68 | 0,04 | 0,95 | 0,96 | 0,92 | 0,99 | 0,99 | 1,00 |
Source: author’s, 2025
Legend: OF: flexion with eyes open; CF: flexion with eyes closed; OE: extension with eyes open; CE: extension with eyes closed; OLR L: left lateral rotation with eyes open; CLR L: right lateral rotation with eyes closed; OLR R: right lateral rotation with eyes open; CLR R: lateral rotation with eyes closed.
Regarding subjective visual vertical (SVV) and joint position sense (JPS), there were no significant differences between groups (SVV: U = 22.50; p = 0.295; JPS: p = 0.244). However, in the healthy group, a strong correlation (R > 0.7) was observed between SVV and prefrontal cortex activation, suggesting a consistent sensorimotor integration pattern absent in the pain group. (Table 4)
Table 4 Intragroup Correlation of Prefrontal Cortex Activation Level and SVV in Asymptomatic Individuals.
| SVV | |
|---|---|
| OF | 0,88 |
| CF | -0,19 |
| OE | 0,85 |
| CE | 0,83 |
| OLR L | 0,75 |
| CLR L | 0,74 |
| OLR R | 0,69 |
| CLR R | 0,74 |
Source: author’s, 2025
Legend: OF: flexion with eyes open; CF: flexion with eyes closed; OE: extension with eyes open; CE: extension with eyes closed; OLR L: left lateral rotation with eyes open; CLR L: right lateral rotation with eyes closed; OLR R: right lateral rotation with eyes open; CLR R: lateral rotation with eyes closed
5 Discussion#
The results of this study demonstrated that individuals with chronic neck pain and mild to moderate functional disability did not show significant changes in prefrontal cortex activation during cervical movements, nor in verticality perception or joint position sense. However, a consistent intragroup behavior was observed in the healthy group, with a high correlation between brain activation and cervical movements, as well as a proportional relationship between prefrontal cortex activation and verticality perception. This pattern was not identified in the pain group, suggesting that the presence of pain may lead to neuromuscular or sensory adaptations, albeit not detectable by the methods used[22].
These findings are partially aligned with Bakhtadze et al. (2012), who found no significant differences in cerebral perfusion in mild cases of chronic neck pain but observed reductions in frontal and parietal regions in moderate to severe cases. Additionally, De Pauw et al. (2017) identified alterations in broader neural networks, such as the parahippocampal, temporal lobe, and cerebellum, suggesting that chronic neck pain may involve multiple brain regions.
Regarding verticality perception and joint position sense, the results corroborate Zoete et al. (2017), who found no significant differences in sensorimotor control in individuals with idiopathic chronic neck pain. The absence of differences may be related to the heterogeneity of pain levels, disability, and small sample size.
The lack of significant changes in brain activation and sensory variables suggests that, in mild to moderate cases, compensatory mechanisms of the central nervous system may be sufficient to maintain functionality. However, the difference in intragroup behavior between groups indicates that chronic neck pain may lead to adaptive motor strategies, such as reduced movement amplitude or more rigid patterns, as a protective mechanism against pain[22, 25]. These adaptations may have long-term repercussions, influencing the progression of the condition or response to treatment.
This study has limitations, such as the small sample size and the restricted evaluation of the prefrontal cortex, which may not fully reflect the neural alterations associated with chronic neck pain. Future research should include larger samples and investigate other brain regions during cervical movements.
6 Conclusion#
This study demonstrated that individuals with chronic neck pain and mild to moderate functional disability did not show significant changes in prefrontal cortex activation during cervical movements, nor in verticality perception or joint position sense.
Declarations
♥Acknowledgements
Article information
- Published
Copyright © 2025 Luciane Aparecida Pascucci Sande de Souza. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 25#
- 1
BLANPIED, P. R.; GROSS, A. R.; ELLIOTT, J. M. et al. Neck Pain: Revision 2017. Journal of Orthopaedic & Sports Physical Therapy, v. 47, n. 7, p. A1-A83, 2017.
- 2
FANDIM J, NITZSCHE R, MICHALEFF Z, OLIVIERA PENA COSTA L, SARAGIOTTO B. The contemporary management of neck pain in adults. Pain Manag 2021;11(1):75–87.
- 3
FEJER, R.; HARTVIGSEN, J. The prevalence of neck pain in the world population: a systematic critical review of the literature. European Spine Journal, v. 15, n. 6, p. 834-848, 2006.
- 4
CLARK, N. C.; RÖIJEZON, U.; TRELEAVEN, J. Proprioception in musculoskeletal rehabilitation. Part 2: Clinical assessment and intervention. Manual Therapy, v. 20, n. 3, p. 378-387, 2015.
- 5
BLOMGREN, J.; STRANDELL, E.; JULL, G.; VIKMAN, I.; RÖIJEZON, U. Effects of deep cervical flexor training on impaired physiological functions associated with chronic neck pain: a systematic review. BMC Musculoskeletal Disorders, v. 19, n. 1, p. 415, 2018.
- 6
DEPAUW, R.; COPPIETERS, I.; MEESUS, M.; CAEYENBERGHS, K.; DANNELS, L.; CAGNIE, B. Is Traumatic and Non-Traumatic Neck Pain Associated with Brain Alterations? - A Systematic Review. Pain Physician, v. 20, n. 4, p. 245-260, 2017.
- 7
KUMMER K, SHEETS PL. Targeting Prefrontal Cortex Dysfunction in Pain. J Pharmacol Exp Ther. 2024 May 21;389(3):268-276. doi: 10.1124/jpet.123.002046. PMID: 38702195; PMCID: PMC11125798.4
- 8
LORENZ J, CROSS DJ, MINOSHIMA S, MORROW TJ, PAULSON PE, Casey KL (2002) A unique representation of heat allodynia in the human brain. Neuron 35:383–393.
- 9
OCHSNER KN, LUDLOW DH, KNIERIM K, HANELIN J, RAMACHANDRAN T, GLOVER GC, Mackey SC (2006) Neural correlates of individual differences in pain-related fear and anxiety. Pain 120:69–77
- 10
BALIKI MN, CHIALVO DR, GEHA PY, LEVY RM, HARDEN RN, PARRISH TB, APKARIAN AV (2006) Chronic pain and the emotional brain: specific brain activity associated with spontaneous fluctuations of intensity of chronic back pain. J Neurosci 26:12165–12173
- 11
DE ZOETE, R. M. J.; STANWELL, P.; WEBER, K. A.; SNODGRASS, S. J. Differences in Structural Brain Characteristics Between Individuals with Chronic Nonspecific Neck Pain and Asymptomatic Controls: A Case-Control Study. Journal of Pain Research, v. 15, p. 521-531, 2022.
- 12
ZHANG, W.; CHEN, Z. Functional Brain Changes in Younger Population of Cervical Spondylosis Patients with Chronic Neck Pain. Journal of Pain Research, v. 17, p. 4433-4445, 2024.
- 13
OBRERO-GAITÁN E, MOLINA F, DEL-PINO-CASADO R, IBÁÑEZ-VERA AJ, RODRÍGUEZ-ALMAGRO D, LOMAS-VEGA R. Visual Verticality Perception in Spinal Diseases: A Systematic Review and Meta-Analysis. J Clin Med. 2020 Jun 3;9(6):1725. doi: 10.3390/jcm9061725. PMID: 32503240; PMCID: PMC7356295.
- 14
PRICE, J.; RUSHTON, A.; TYROS, V. et al. Expert consensus on the important chronic non-specific neck pain motor control and segmental exercise and dosage variables: An international e-Delphi study. PLOS ONE, v. 16, n. 7, p. e0253523, 2021.
- 15
VERNON, H. The Neck Disability Index: state-of-the-art, 1991-2008. Journal of Manipulative and Physiological Therapeutics, v. 31, n. 7, p. 491-502, 2008.
- 16
SERRA-SALA, M.; TIMONEDA-GALLART, C.; PÉREZ-ÁLVAREZ, F. Utilidade clínica da hemoencefalografia além do neurofeedback. Neuropsiquiatria, v. 12, p. 1173-1180, 2016.
- 17
AGOSTINI, L. S.; RODRIGUES, P. S. M.; BAZAN, R.; DE OLIVEIRA BAGGIO, J. A.; DE SOUZA, L. A. P. S.; LUVIZUTTO, G. J. Analysis of Verticality Perception in Older Adults With and Without Acute Stroke in Half-Lying Versus Sitting Positions. Percept Mot Skills, 2022. DOI: 10.1177/00315125221091344.
- 18
FERREIRA LR, FERREIRA FJPA, CAMPOS FA, LUVIZUTTO GJ, SOUZA LAPS. Evaluation of subjective vertical perception among stroke patients: a systematic review. Arq Neuropsiquiatr. 2021 Nov;79(11):1026-1034. doi: 10.1590/0004-282X-ANP-2020-0584. PMID: 34816993.
- 19
FAVARO, Isabela Forcin; MARTINS, Jaqueline; ROSSI, Denise Martineli; BOARATI, Eduardo de Lima; MORAIS, Mayra Felippe de; OLIVEIRA, Anamaria Siriani. Laser-Pointer assisted angle reproduction test (LP-ART): reliability, performance, and correlation with shoulder pain and disability in patients with subacromial pain syndrome. Physiotherapy Theory and Practice, v. 39, n. 6, p. 1287-1296, 2023. DOI: 10.1080/09593985.2022.2035031
- 20
PISCICELLI, C.; PÉRENNOU, D. Visual verticality perception after stroke: a systematic review of methodological approaches and suggestions for standardization. Annals of Physical and Rehabilitation Medicine, v. 60, p. 208-216, 2017.
- 21
PARANHOS, R.; FIGUEIREDO FILHO, D. B.; ROCHA, E. C. da; SILVA JÚNIOR, J. A. da; NEVES, J. A. B.; SANTOS, M. L. W. D. Desvendando os Mistérios do Coeficiente de Correlação de Pearson: o Retorno. Leviathan (São Paulo), v. 8, p. 66-95, 2014.
- 22
FALLA, D.; JULL, G.; HODGES, P. et al. An endurance-strength training regime is effective in reducing myoelectric manifestations of cervical flexor muscle fatigue in females with chronic neck pain. Clinical Neurophysiology, v. 117, n. 4, p. 828-837, 2006.
- 23
DE ZOETE, R. M. J.; OSMOTHERLY, P. G.; RIVETT, D. A.; FARRELL, S. F.; SNODGRASS, S. J. Sensorimotor control in individuals with idiopathic neck pain and healthy individuals: A systematic review and meta-analysis. Archives of Physical Medicine and Rehabilitation, v. 98, n. 6, p. 1257–1271, 2017.
- 24
BAKHTADZE, M. A.; VERNON, H.; KARALKIN, A. V.; PASHA, S. P.; TOMASHEVSKIY, I. O.; SOAVE, D. Cerebral perfusion in patients with chronic neck and upper back pain: Preliminary observations. Journal of Manipulative and Physiological Therapeutics, v. 35, p. 76-85, 2012.
- 25
ALDAHAS, A.; DEVECCHI, V.; DEANE, J. A.; FALLA, D. Measurement properties of cervical joint position error in people with and without chronic neck pain. PLoS One, v. 18, n. 10, p. e0292798, 2023. DOI: 10.1371/journal.pone.0292798.