Brown Spiders’ Venom Ulcer Necrosis Local Insulin Micro Doses Therapeutic Essay. Literature Review
Gaspar NK ✉
Gaspar NKCorresponding author More articles by this author →Nunes-Nogueira M ✉
Nunes-Nogueira MCorresponding author More articles by this author →Nogueira-Ramos IFN
Nogueira-Ramos IFN More articles by this author →
Published
Abstract
BackgroundBrown spiders’ bites ulcers heal in about 3 months. Intralesional insulin micro multiples doses injections accelerate healing ulcers. In 3,5% of brown spiders’ accidents occur hemolysis, intravascular coagulation, renal failure and, in 3%, death. Loxosceles venom transforms sphingomyelin into ceramides. Insulin inhibition by ceramides, may be responsible by necrosis, hemolysis, intravascular coagulation, and thrombosis. Relationship between insulin inhibition and lesion development isn’t appreciated in literature about loxoscelism.
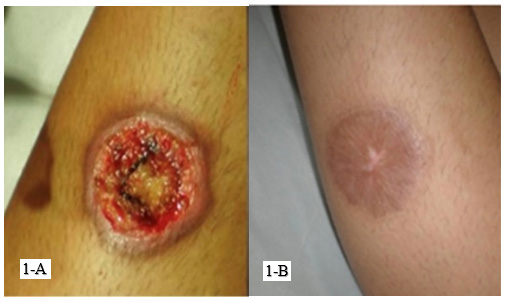
Objectives2-Evaluate healing acceleration by intralesional insulin in cutaneous ulcers by brown spiders´ bites in 13 patients, (between 2015-2023) and it’s efficacy preventing serious sequelae. Review diagnosis, physiopathology and therapeutic. Discuss ceramides’ relationships with insulin resistance and hemolysis. Demonstrate intralesional insulin multiple micro-dosis injections efficacy as efficient treatment. Exhibit lesions photographic aspects, helping earlier diagnosis and treatment, preventing serious sequelae and death, especially, at distant places from serum therapy hospitals.
Methods3-Intralesional and perilesional applications sections of multiples 0,01ml of insulin NPH solution with 3/5 UI in 1ml of anesthetic or saline, with variable frequency (Gaspar N.K. 2020) and doxycycline. Photographic control.
ResultsHealing tendency was observed since first applications. All ulcers healed in less than 36days. Authors refer ulcers healing take more than 90days. No patient required reconstructive surgery. No patient developed hypoglycemia symptoms during treatment. Study Limitations: Small sampling; control group absence; different evolutionary stages injuries treatment; insulin data related in patient’s absence.
ConclusionsThis method proved to accelerate ulcers healing. It´s necessary to clarify insulin resistance aspects in loxoscelism. Healing necessary sections were wound size related.
1 Introduction#
Found globally Loxosceles genus, includes small araneus, with 1-5cm body length, fine long legs, surviving 1-2 years in 8-430 t C, with nocturnal habits, laying about 50 eggs1-2 .
Living in dry, dark, quiet places, caves, under rocks, in temperate and tropical regions. At home, they choose attics, basements, cupboards, drawers, boxes, sheets, furniture, shoes, under papers, dry leaves etc.2-3 . They survive 50 days with no food or water2. Accidents happened 86% at home4 .
In Brazil, there are 50 species5 . L. Gaucho, L. intermedia and L. laeta are blamed for most accidents 1;2;6;7 . They were 39.409 between 2017 and 2021 in Brazil, most in south region(53%), mainly in Paraná state8 . Cutaneous-systemic loxoscelism occurred in Chile, in around 5,5% of 200 accidents9 .
Severity is influenced by geographic region10 , injected venom amount and composition11-14 .
There is no laboratory method capable of diagnosing cutaneous or systemic loxoscelism. Most patients never see the spider. An isothermal amplification of DNA samples obtained from experimentally envenomed rabbit, through colorimetric lamp was related as diagnosis alternative15 .
1.1 Cutaneous Loxoscelism#
Bite is painless. After hours or days, the local becomes pale. May appear itching, pain, and bullae11;16 . Over days, occurs induration, erythema, edema17 . Central ulcer comes up that can spread gravitationally18 . Usually single, smaller than 10cm.19 , evolves with a dark sunken necrotic center, with well-defined raised edges, intense inflammatory reaction, without typical purulent secretion but with mummified crust and hardened peripheral area17 . This aspect aids diagnosis11 .
Healing usually takes three months20-21;17;19;22-23 leaving deep scar that can require excision and grafting24;16;22 .
Mixed inflammatory cell infiltrate, tissue aseptic coagulative necrosis and vasculitis occur after venom injection25 .
1.2 Systemic Loxoscelism#
Suspicion should be high, especially in children with cutaneous ulcer, hemolysis, or coagulopathy. Lesion is frequently misdiagnosed as “cellulitis”. May occur pruritus, rash, headache, vomiting, fever, arthralgia26 and coagulopathy4;27;22;26 . Hemoglobinuria, acute renal failure, rhabdomyolysis, thrombocytopenia, and jaundice may develop within 1-10 days26 . Bilirubin (BT) and LDH levels27;24 had 91% specificity and 94% sensibility in a 275 patient series28 . In 53.5% of patients, D-dimer levels were increased after 1 week and in 25%, after 2 weeks10. Acute kidney injury 29-31;24;13;32;10 , occurred with massive hemolysis noticed in 2 of 81 patients27 .
High serum D-dimer level, by endothelial cell activation and intravascular coagulation, total bilirubin (TB), and LDH levels and leukocytosis with neutrophilia indicate necrosis, systemic involvement27;24;28;33;10 and patient condition. Coombs' test may be positive33 . Mortality was 3.5% (2/57 individuals)33
1.3 The Venom#
Spider evolution had natural selection and increase in noxiousness34-36 . L. laeta venom revealing superior activity in Brazil14 .
In 1978, Forrester D. et al 37 , demonstrated direct lytic action of phospholipase D (referred to as sphingomyelinase D). Phospholipase D metabolizes sphingomyelin into ceramide and phosphocholine39-40;36 . Ceramides alter immune functions of NK cells, T CD8+ T cells, activating complement and recruiting polymorphonuclear infiltrate7;13;36 .
Venom is a complex of biological toxins especially phospholipase D, metalloproteases, serineproteases, hialuronidase and Inhibitor Cystine Knot (ICK) peptides31-32 , induces rapid coagulation, capillaries occlusion and necrosis17. Proteomic analysis of Loxosceles gaucho venom showed 12 different phospholipases, Astacin-Metalloprotease(ASM) and insecticidal toxin Sicaritoxin-Lia38 .
1.4 Ceramides and Insulin Resistance#
Ceramides are crucial actors in the development of insulin resistance and type 2 diabetes, and negatively affect mitochondrial respiratory chain, hallmark of type 2 diabetes (T2-D)56 .
The insulin inhibition by ceramides, through the protein kinase mTOR (target of rapamycin) has been evaluated by different authors45-48;39-40;49-54;36 . In addition, insulin production is impaired by potent proinflammatory lactate hydrogenase overexpression55;36 .
Sphingomyelin and phosphatidylcholines constitute more than 50% of membranous phospholipids, exerting important impact on cell signaling, through their catabolic products, ceramides and glucoceramides41 , controlling growth, differentiation, apoptosis42-43;31 , and immuno-inflammatory events17;44;10 .
Insulin has pivotal role in maintaining mitochondrial proteome abundance and quality by enhancing your biogenesis and preventing proteome degradation. Insulin resistance is characterized by inefficient mitochondrial coupling and excessive production of reactive oxygen species57-58 . Hypoglycemia impairs fibrinolytic balance, increases pro-inflammatory responses, platelet activation, coagulation biomarkers, and reduces function endothelial mediated by nitric oxide59 .
The venom depletes serum hemolytic complement, clotting factors VIII, IX, XI, and XII, prolongs the activated partial thromboplastin time, induces rapid coagulation, occlusion of capillaries, necrosis17;60;13 .
1.5 Therapy#
The specific treatment is serum therapy, (produced through L intermedia venom) applied until for up to 12h after bite. Pauli I. demonstrated beneficial results reducing the size of necrotic area until 48hs61 . Adverse reactions are described62 .
Systemic treatment involves aggressive supportive care, wound management, blood transfusions, intravenous fluid replacement and antibiotics.
In a mouse model of systemic loxoscelism, venom-induced kidney failure was abrogated by administration of tetracycline, that reduces kidney damage induced by venom63 , the progression of dermonecrotic lesion, the expression of MMP-2 and the induction of MMP-967 . Tetracyclines action on MMPs is thought to be mediated by chelation of structural metals within the enzyme64 . The strength of tetracycline-metal interaction is dependent on metal ion present. Tetracycline’s affinity for different divalent zinc differs and is highly dependent on pH and the presence of other metal ions. Doxycycline action, a zinc dependent enzyme, has a relative superiority over tetracycline and minocycline due to its increased affinity for Zn2+ compared with tetracycline or minocycline65-66 .
Animals, inoculated with venom, treated twice a day for 48 hours with cream containing tetracycline or doxycycline (50 μg/ml) had significant reduction in lesions evolution. Similarly, topical, or oral tetracycline or doxycycline, could control progression of the dermonecrotic lesion in animals injected with venom67 .
The recombinant protein containing β-cell epitopes of different Loxosceles toxins, that generated neutralizing antibodies in immunized rabbits can be candidate for antivenom production68 .
Monoclonal antibodies targeting acid SMase inhibitors can be used as therapeutic tools69 .
Imipramine and zoledronic acid capable of reducing acid SMase activity in animals, may be useful in reducing ceramides70 .
Glucocorticoids and immunoglobulins may have benefits treating severe loxoscelism24 and may trigger rapid recovery of platelets24;10 .
Dapsone was used by its activity to reduce polymorphonuclear leukocyte function11;17 but, should be avoided because it can trigger serious adverse reactions72-73 .
The magnitude of hyperbaric therapy results in necrosis reduction was insignificant74 .
In vitro topic diethilazelat, a plasma membrane fluidizer, with a broad range of immune modulatory activities, inhibit hemolysis cause by the venom and suppressed phospholipase A2 activity in a dose dependent manner75 .
Marbled necrotic skin lesions require surgical removal of the necrotic area21;11;76;24 .
Complications as hyperkalemia (NR≥2.0), metabolic acidosis requiring bicarbonate. Hypotension requiring vasopressors, and hypoxia requiring intubation, occurred only in patients with profound hemolytic anemia22;26 .
2 Intralesional Insulin Therapeutic Essay#
2.1 Background#
Insulin has metabolic and growth-stimulating actions, both through its own receptors and of its homologous factors (IGFs)77-80 , having pivotal role in mitochondrial proteome preservation58 . Insulin has been used in humans to recover cutaneous and subcutaneous atrophies81 and was effective to accelerate healing experimental wounds in Wistar rats. Fibroblasts trans-differentiation in myofibroblasts occurred precociously82 . Healing acceleration was obtained in difficult healing cutaneous wounds by multiple, simultaneous, intralesional and perilesional injections, of 0.04-0.05UI NPH* mono component insulin, without adverse effects83 .
2.2 Method#
a- Multiples micro doses of intralesional and perilesional applications, of 4-5UI of NPH *Novolin Nordisk mono component Insulin NPH 100 UI, diluted in 1ml of lidocaine in multiple simultaneous injections of 0.01 ml (0.04-0.05UI), in various lesions planes and points, repeated at variable time intervals. Debridement of necrotic tissues on the first day treatment.
b- Doxycycline 100mg administration every 12hours in recent cases.
2.3 Patients#
| Pat. | Sex- Age | Days Evolution | Clinical aspects | Insulin sections | Doxicycline | Debridment | Healing/days |
|---|---|---|---|---|---|---|---|
| 1 | M-21 | 136 | 6 cm necrotic dark crust leg ulcer, reaching adipose tissue.(fig1) | 5 | No | Yes | 36 |
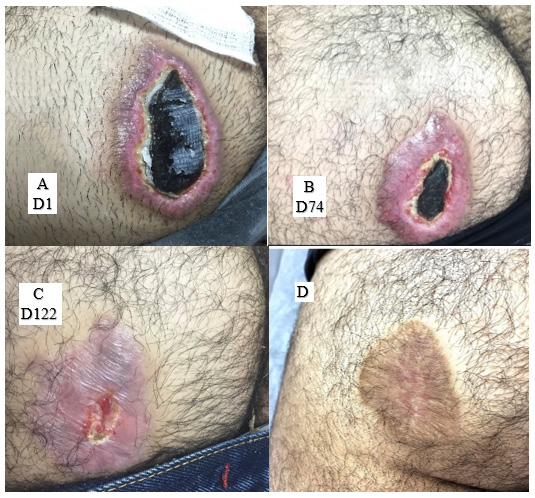
| 2 | M-23 | 57 | 2 days after bite, bullae that evolved to 6x8cm. gluteal ulcer with black mummified crust.(fig.2) | 16 | No | No | 40 |
| 3 | M-22 | 126 | 3/4cm left thigh, elevated cyanotic edges ulcer with marble consistence margins. | 4 | No | Yes | 35 |
| 4 | F-52 | 14 | Necrotic, 1,5cm., dry ulcer with raised marble consistence edges, on right breast. | 5 | Yes | ||
| Yes | 16 | ||||||
| 5 | F-40 | 6 | Well-defined edges right leg ulceration. (1o episode) | 6 | Yes | Yes | 22 |
| 6 | F-40 | 6 | Right leg ulcer. (2o episode) | 7 | Yes | Yes | 18 |
| 7 | F-40 | 40 | Dry raised indurated edges, 3/5cm., leg ulcer. | 6 | Yes | No | 30 |
| 8 | M-79 | 7 | Erythematous elevated borders, 2/3cm., leg ulcer. | 6 | Yes | Yes | 29 |
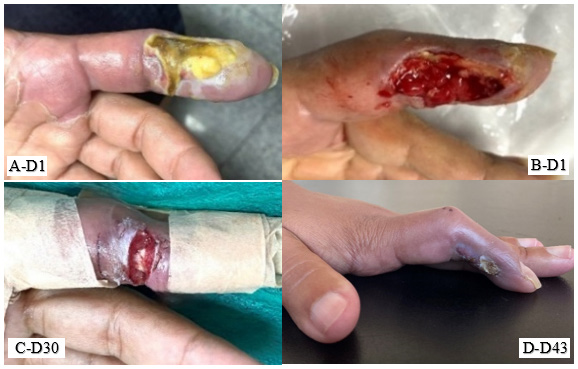
| 9 | F-42 | 30 | Necrotic marble consistence, 3x2,5cm., dry crust, raised, irregular edges, ulcer on 2nd finger.(fig-3) | 18 (pos split use) | Yes | Yes | 27 (ankylosis) |
| 10 | M-67 | 1 | 2mm clear lesion on 12cm. indurated erythematous plaque, that evolved to dark, crust, 1,5cm leg ulcer. | 7 | Yes | Yes | 29 |
| 11 | F-50 | 4 | Erythematous-violaceous plaque, necrosis(4cm.) with raised edges, in right instep. | 9 | Yes | Yes | 23 |
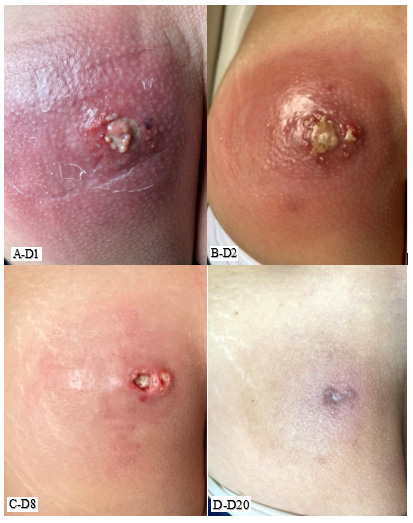
| 12** | F-58 | 13 | 1-day after bite pain, bullae, great induration. After 10days 1.5cm., elevated edges gluteal ulcer and left leg edema (fig.4). | 11 | Yes | Yes | 20 |
| 13 | F-31 | 4 | Pain 4hs after. After 4 days painful erythematous-edematous, 10cm. right tight plaque, with central, 1,7cm., hemorrhagic crust ulcer. | 4 | Yes | No | 8 |
| 14 | F-35 | 8 | A 5cm. gluteal ulceration with erythematous induration. | 7 | Yes | Yes | 30 |
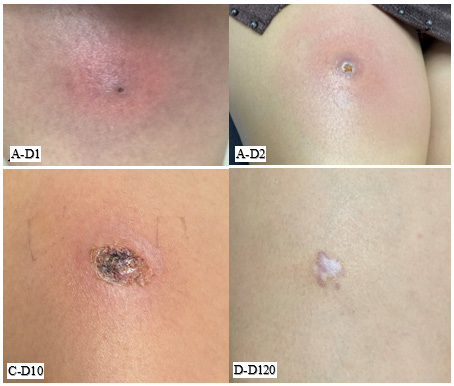
4 Conclusion#
1-Healing ulcers by Loxoscelles venom takes 3 months. With insulin in intralesional micro multiple doses, healing occurs in about 1 month.
2-Healing response onset begins in 24-48 hours, with final resolution in less than 1 month in our patients, indicating that this therapy may help.
3-Different intervals between applications did not change the results.
4-The method proved to be effective and without adverse effects.
5-Regenerative activity onset in all lesions was observed between 1 or 2 days after first application, and can be attributed to its stimulating healing activity, as demonstrated by Gaspar and Gaspar, and the insulin’s reduction of ceramides’ resistance.
6-Advantages obtained indicate that the process can be successfully used to accelerate healing of brown spider’s bites ulcers.
7-According to previous experience (Gaspar 2020)83, applications performed using this method don’t determine glycemic changes in adult patients.
8-Raw (or open) wounds can heal with undiluted insulin in topical applications83.
9-Despite a significant correlation between sphingolipids, mitochondrial dysfunction, insulin resistance and T2 D, this subject hasn’t received much attention compared to direct sphingolipids effect on insulin signaling pathway84.
10-Insulin’s availability and safety use, indicates the method as an effective therapeutic option for difficult-to-heal wounds, without adverse effects.
Declarations
✎Author contributions
◎Competing interests
Article information
- Published
Copyright © 2026 Neide Kalil Gaspar. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 84#
- 1
Gonçalves de Andrade RM, Galati EA, Tambourgi DV. Presença de Loxosceles similis Moenkhaus, 1898 (Araneae, Sicariidae) na Serra da Bodoquena, Estado de Mato Grosso do Sul, Brasil [PresenceofLoxosceles similis Moenkhaus, 1898 (Araneae, Sicariidae) in Serra da Bodoquena, State of Mato Grosso do Sul, Brazil]. Ver Soc Bras Med Trop. 2001 May-Jun;34(3):275-7. Portuguese
- 2
Gonçalves-de-Andrade RM, Tambourgi DV. First record on Loxosceles laeta (Nicolet, 1849) (Araneae, Sicariidae) in the West Zone of São Paulo City, São Paulo, Brazil, and considerations regarding its geographic distribution. Rev Soc Bras Med Trop. 2003 May-Jun;36(3):425-6.
- 3
Fischer ML, Vasconcellos-Neto J. Microhabitats occupied by Loxosceles intermedia and Loxosceles laeta (Araneae: Sicariidae) in Curitiba, Paraná, Brazil. J Med Entomol. 2005 Sep;42(5):756-65
- 4
Schenone H, Saavedra T, Rojas A, Villarroel F. [Loxoscelism in Chile. Epidemiologic, clinical and experimental studies]. Revista do Instituto de Medicina Tropical de Sao Paulo. 1989;31(6):403–15.
- 5
Araujo D, Schneider MC, Zacaro AA, de Oliveira EG, Martins R, Brescovit AD, Knysak I, Cella DM. Venomous Loxosceles Species (Araneae, Haplogynae, Sicariidae) from Brazil: 2n♂ = 23 and X1X2Y Sex Chromosome System as Shared Characteristics. ZoologSci. 2020 Apr;37(2):128-139.
- 6
de Oliveira KC, Goncalves de Andrade RM, Piazza RM, Ferreira JM Jr., van den Berg CW, Tambourgi DV. Variations in Loxosceles spider venom composition and toxicity contribute to the severity of envenomation. Toxicon. 2005;45(4):421–9.
- 7
Tambourgi DV, Paixão-Cavalcante D, Gonçalves de Andrade RM, Fernandes-Pedrosa Mde F, Magnoli FC, Paul Morgan B, van den Berg CW. Loxosceles sphingomyelinase induces complement-dependent dermonecrosis, neutrophil infiltration, and endogenous gelatinase expression. J Invest Dermatol. 2005 Apr;124(4):725-31.
- 8
SINAM-Boletim epidemiol. | Secretaria de Vigilância em Saúde | Ministério da Saúde, vol. 53 | no. 31, ago. 2022.
- 9
Droppelmann K, Majluf-Cáceres P, Sabatini-Ugarte N, Valle E, Herrera H, Acuña D. Caracterización clínica y epidemiológica de 200 pacientes com loxoscelismo cutáneo y cutáneo visceral [Loxoscelism. Experience in 200 patients]. Rev Med Chil. 2021 May;149(5):682-688. Spanish
- 10
Gremski LH, da Justa HC, Polli NLC, Schluga PHC, Theodoro JL, Wille ACM, Senff-Ribeiro A, Veiga SS. Systemic Loxoscelism, Less Frequent but More Deadly: TheInvolvement of Phospholipases D in the Pathophysiology of Envenomation. Toxins (Basel). 2022 Dec 27;15(1):17.
- 11
Futrell JM. Loxoscelism. Am J Med Sci. 1992;304(4):261–7.
- 12
Barbaro KC, Ferreira ML, Cardoso DF, Eickstedt VR, Mota I. Identification and neutralization of biological activities in the venoms of Loxosceles spiders. Braz J Med Biol Res. 1996 Nov;29(11):1491-7.
- 13
Lopes PH, Murakami MT, Portaro FCV, Mesquita Pasqualoto KF, van den Berg C, Tambourgi DV. Targeting Loxosceles spider Sphingomyelinase D with small-molecule inhibitors as a potential therapeutic approach for loxoscelism. J EnzymeInhib Med Chem. 2019 Dec;34(1):310-321.
- 14
Medina-Santos R, Fernandes Costa TG, Silva de Assis TC, Kalapothakis Y, de Almeida Lima S, do Carmo AO, Gonzalez-Kozlova EE, Kalapothakis E, Chávez-Olórtegui C, Guerra Duarte C. Analysis of NGS data from Peruvian Loxosceles laeta spider venom gland reveals toxin diversity. Comp BiochemPhysiol Part D Genomics Proteomics. 2022 Sep;43:101017.
- 15
Fernandes LP, Rocha MN, Duarte CG, Minozzo JC, do Monte-Neto RL, Felicori LF. Validation of a colorimetric LAMP to detect Loxosceles experimental envenomation. Toxicon. 2022 Sep;216:50-56.
- 16
Sams HH, Dunnick CA, Smith ML, King LE Jr. Necrotic arachnidism. J Am Acad Dermatol. 2001 Apr;44(4):561-73; quiz 573-6
- 17
Peterson ME. Brown spider envenomation. Clin Tech Small Anim Pract. 2006 Nov;21(4):191-3.
- 18
da Silveira RB, dos Santos Filho JF, Mangili OC, Veiga SS, Gremski W, Nader HB, von Dietrich CP. Identification of proteases in the extract of venom glands from brown spiders. Toxicon. 2002 Jun;40(6):815-22.
- 19
Stoecker WV, Vetter RS, Dyer JA. NOT RECLUSE-A Mnemonic Device to Avoid False Diagnoses of Brown Recluse Spider Bites. JAMA Dermatol. 2017 May 1;153(5):377-378.
- 20
Wasserman GS, Anderson PC. Loxoscelism and necrotic arachnidism. J Toxicol Clin Toxicol. 1983-1984;21(4-5):451-72.
- 21
Gutowicz M, Fritz RA, Sonoga AL. Brown recluse spider bite. A literature review and case report. J Am Podiatr Med Assoc. 1989 Mar;79(3):142-6
- 22
Lopes PH, Squaiella-Baptistão CC, Marques MOT, Tambourgi DV. Clinical aspects, diagnosis, and management of Loxosceles spider envenomation: literature and case review. Arch Toxicol. 2020 May;94(5):1461-1477.
- 23
Borrasca-Fernandes CF, Prado CC, Capitani EM, Hyslop S, Bucaretchi F. Temporal Evolution of dermonecrosis in loxoscelism assessed by photodocumentation. Rev Soc Bras Med Trop. 2022 Feb 25;55:e0502.
- 24
Nguyen N, Pandey M.Loxoscelism: Cutaneous and Hematologic Manifestations. Adv Hematol. 2019 Mar 20;2019:4091278.
- 25
Elston DM, Eggers JS, Schmidt WE, Storrow AB, Doe RH, McGlasson D, Fischer JR. Histological findings after brown recluse spider envenomation. Am J Dermatopathol. 2000 Jun;22(3):242-6.
- 26
Loden JK, Seger DL, Spiller HA, Wang L, Byrne DW. Cutaneous-hemolytic loxoscelism following brown recluse spider envenomation: new understandings. Clin Toxicol (Phila). 2020 Dec;58(12):1297-1305.
- 27
Malaque CM, Santoro ML, Cardoso JL, Conde MR, Novaes CT, Risk JY, França FO, de Medeiros CR, Fan HW. Clinical picture and laboratorial evaluation in human loxoscelism. Toxicon. 2011 Dec 1;58(8):664-71.
- 28
Jacobs JW, Bastarache L, Thompson MA. Laboratory Predictors of Hemolytic Anemia in Patients with Systemic Loxoscelism. Am J Clin Pathol. 2022 Apr 1;157(4):566-572.
- 29
Da Silva PH, da Silveira RB, Appel MH, Mangili OC, Gremski W, Veiga SS. Brown spiders and loxoscelism. Toxicon. 2004 Dec 1;44(7):693-709.
- 30
Tambourgi DV, Gonçalves-de-Andrade RM, van den Berg CW. Loxoscelism: From basic research to the proposal of new therapies. Toxicon. 2010 Dec 15;56(7):1113-9.
- 31
Gremski LH, Trevisan-Silva D, Ferrer VP, Matsubara FH, Meissner GO, Wille AC, Vuitika L, Dias-Lopes C, Ullah A, de Moraes FR, Chávez-Olórtegui C, Barbaro KC, Murakami MT, Arni RK, Senff-Ribeiro A, Chaim OM, Veiga SS. Recent advances in the understanding of brown spider venoms: From the biology of spiders to the molecular mechanisms of toxins. Toxicon. 2014 Jun;83:91-120.
- 32
Gremski LH, da Justa HC, da Silva TP, Polli NLC, Antunes BC, Minozzo JC, Wille ACM, Senff-Ribeiro A, Arni RK, Veiga SS. Forty Years of the Description of Brown Spider Venom Phospholipases-D. Toxins (Basel). 2020 Mar 6;12(3):164.
- 33
Robinson JR, Kennedy VE, Doss Y, Bastarache L, Denny J, Warner JL. Defining the complex phenotype of severe systemic loxoscelism using a large electronic health record cohort. PLoS One. 2017 Apr 19;12(4):e0174941.
- 34
Pedroso A, Matioli SR, Murakami MT, Pidde-Queiroz G, Tambourgi DV. Adaptive evolution in the toxicity of a spider's venom enzymes. BMC Evol Biol. 2015 Dec 21;15:290.
- 35
Mandal M et al 2019 Sanchez V, Galor A, Jensen K, Mondal K, Mandal N. Relationships between ocular surface sphingomyelinases, Meibum and Tear Sphingolipids, and clinical parameters of meibomian gland dysfunction. Ocul Surf. 2022 Jul;25:101-107.
- 36
Tan-Chen S, Bourron O, Hajduch É. Céramides, acteurs cruciaux dans le développement de l’insulino-résistance et du diabète de type 2 [Ceramides, crucial actors in the development of insulin resistance and type 2 diabetes]. Med Sci (Paris). 2020 May;36(5):497-503. French.
- 37
Forrester LJ, Barrett JT, Campbell BJ. Red blood cell lysis induced by the venom of the brown recluse spider: the role of sphingomyelinase D. Arch BiochemBiophys. 1978 Apr 30;187(2):355-65.
- 38
Valladão R, da Silva DL, Beraldo Neto E, Pimenta DC, Chiariello TM, Auada AVV, Wen FH, Lopes AR. Loxosceles gaucho venom gland proteome: A new perspective on Loxosceles venom biochemical composition. Toxicon. 2020; 20;177 Suppl 1:S34
- 39
Chavez JA, Holland WL, Bär J, Sandhoff K, Summers SA. Acid ceramidase overexpression prevents the inhibitory effects of saturated fatty acids on insulin signaling. J Biol Chem. 2005 May 20;280(20):20148-53.
- 40
Stock RP, Brewer J, Wagner K, Ramos-Cerrillo B, Duelund L, Jernshøj KD, Olsen, Balfgatolli LA. Sphingomyelinase D Activity in Model Membranes: Structural Effects of in situ Generation of Ceramide-1-Phosphate. PLoS One. 2012; 7(4): e36003
- 41
Barenholtz Y, Thompson TE. Sphingomyelin: biophysical aspects. Chem Phys Lipids. 1999 Nov;102(1-2):29-34.
- 42
Hannun YA, Obeid LM. Principles of bioactive lipid signalling: lessons from sphingolipids. Nat Rev Mol Cell Biol. 2008 Feb;9(2):139-50.
- 43
Slotte JP. Biological functions of sphingomyelins. Prog Lipid Res. 2013 Oct;52(4):424-37.
- 44
Albeituni S, Stiban J. Roles of Ceramides and Other Sphingolipids in Immune Cell Function and Inflammation. Adv Exp Med Biol. 2019;1161:169-191
- 45
Kanety H, Hemi R, Papa MZ, Karasik A. Sphingomyelinase and ceramide suppress insulin-induced tyrosine phosphorylation of the insulin receptor substrate-1. J Biol Chem. 1996 Apr 26;271(17):9895-7.
- 46
Schmitz-Peiffer C, Craig DL, Biden TJ. Ceramide generation is sufficient to account for the inhibition of the insulin-stimulated PKB pathway in C2C12 skeletal muscle cells pretreated with palmitate. J Biol Chem. 1999 Aug 20;274(34):24202-10.
- 47
Chavez JA, Knotts TA, Wang L-P, Guibin Li, Dobrowsky RT, Florant GL, Summers SA. A role for ceramide, but not diacylglycerol, in the antagonism of insulin signal transduction by saturated fatty acids. Biol Chem. 2003; 278(12):10297-303.
- 48
Stratford S, Hoehn KL, Liu F, Summers SA. Regulation of insulin action by ceramide: dual mechanisms linking ceramide accumulation to the inhibition of Akt/protein kinase B. J Biol Chem. 2004 Aug 27;279(35):36608-15.
- 49
Babenko NA, Kharchenko VS. Ceramides inhibit phospholipase D-dependent insulin signaling in liver cells of old rats. Biochemistry (Mosc)31 2012;77(2):180-6.
- 50
Babenko NA and Kharchenko VS. Modulation of Insulin Sensitivity of Hepatocytes by the Pharmacological Downregulation of Phospholipase D. Int J Endocrinol. 2015; 2015: 794838
- 51
Gorelik A, Illes K, Superti-Furga G, Nagar B. Structural Basis for Nucleotide Hydrolysis by the Acid Sphingomyelinase-like phosphodiesterase SMPDL3A. J Biol Chem. 2016. 291(12):6376-85.
- 52
Yoon MS, Choi CS. The role of amino acid-induced mamalian target of rapamycin complex 1(mTORC1) signaling in insulin resistance. Exp Mol Med. 2016 Jan 8;48(1):e201.
- 53
Kuefner MS, Pham K, Redd JR, Stephenson, Deng X, Bridges D, Boilard E, Elam MB, Park EA. Secretory phospholipase A 2 group IIA modulates insulin sensitivity and metabolism. Lipid Res. 2017 Sep;58(9):1822-1833.
- 54
Kim MH, Park JW, Lee EJ, Kim S, Shin SH, Ahn JH, Jung Y, Park I, Park WJ.C16 ceramide and sphingosine 1 phosphate/S1PR2 have opposite effects on cell growth through mTOR signaling pathway regulation. Oncol. Rep. 2018 Nov;40(5):2977-2987.
- 55
Ainscow EK, Zhao C, Rutter GA. Acute overexpression of lactate dehydrogenase-A perturbs (beta-cell mitochondrial metabolism and insulin secretion. Diabetes. 2000 Jul;49(7):1149-55
- 56
Roszczyc-Owsiejczuk K, Zabielski P. Sphingolipids as a Culprit of Mitochondrial Dysfunction in Insulin Resistance and Type 2 Diabetes. Front Endocrinol (Lausanne). 2021 Mar 18;12:635175.
- 57
Liesa M, Palacín M, Zorzano A. Mitochondrial dynamics in mammalian health and disease. Physiol Rev. 2009;89(3):799–845.
- 58
Ruegsegger GN, Creo AL, Cortes TM, Dasari S, Nair KS. Altered mitochondrial function in insulin-deficient and insulin-resistant states. Altered mitochondrial function in insulin-deficient and insulin-resistant states. J Clin Invest. 2018 ;128(9):3671-3681.
- 59
Joy NG, Tate DB, Davis SN. Counter regulatory responses to hypoglycemia differ between glimepiride and glyburide in non-diabetic individuals. Metabolism. 2015 Jun;64(6):729-37
- 60
Rozenova KA, Deevska GM, Karakashian AA, Nikolova-Karakashian MN. Studies on the role of acid sphingomyelinase and ceramide in the regulation of tumor necrosis factor alpha (TNFalpha)-converting enzyme activity and TNFalpha secretion in macrophages. J Biol Chem. 2010 Jul 2;285(27):21103-13
- 61
Pauli I, Minozzo JC, da Silva PH, Chaim OM, Veiga SS. Analysis of therapeutic benefits of antivenin at different time intervals after experimental envenomation in rabbits by venom of the brown spider (Loxosceles intermedia). Toxicon. 2009;53(6):660-71.
- 62
Malaque CMS, Novaes CTG, Piorelli RO, Risk JY, Murad JC, Lara AN, Virgulino CC, Miyaji KT, Santoro ML. Impact of antivenom administration on the evolution of cutaneous lesions in loxoscelism: A prospective observational study. PLoS Negl Trop Dis. 2022 Oct 14;16(10):e0010842.
- 63
Okamoto C.K., van den Berg C.W., Masashi M., Gonçalves-de-Andrade R.M., Tambourgi D.V. Tetracycline reduces kidney damage induced by loxosceles spider venom. Toxins. 2017;9:90.
- 64
Golub LM, McNamara TF, D'Angelo G, Greenwald RA, Ramamurthy NS. A non-antibacterial chemically-modified tetracycline inhibits mammalian collagenase activity. J Dent Res. 1987 Aug; 66(8):1310-4.
- 65
Schissel SL, Keesler GA, Schuchman EH, Williams KJ, Tabas I. The cellular trafficking and zinc dependence of secretory and lysosomal sphingomyelinase, two products of the acid sphingomyelinase gene. J Biol Chem. 1998 Jul 17;273(29):18250-9.
- 66
Deniz Ogut, Buket Reel 1, CerenGonen Korkmaz, Mehmet Zuhuri Arun, SerapCilakerMicili, Bekir Ugur Ergur. Doxycycline down-regulates matrix metalloproteinase expression and inhibits NF-κB signaling in LPS-induced PC3 cells. Folia HistochemCytobiol. 2016;54(4):171-180.
- 67
Paixão-Cavalcante D., Van Den Berg C.W., Gonçalves-De-Andrade R.M., Fernandes-Pedrosa M.D.F., Okamoto C.K., Tambourgi D.V. Tetracycline protects against dermonecrosis induced by Loxosceles spider venom. J. Investig. Dermatol. 2007;127:1410–1418.
- 68
Lima SA, Guerra-Duarte C, Costal-Oliveira F, Mendes TM, Figueiredo LFM, Oliveira D, Machado de Avila RA, Ferrer VP, Trevisan-Silva D, Veiga SS, Minozzo JC, Kalapothakis E, Chávez-Olórtegui C. Recombinant Protein Containing B-Cel lEpitopesof Different Loxosceles Spider Toxins Generates Neutralizing Antibodies in Immunized Rabbits. Front Immunol. 2018 Apr 3;9:653.
- 69
Karim-Silva S, Becker-Finco A,Gizzi I J, Boursin F, Leroy A,Noiray M et al. Loxoscelism: Advances and Challenges in the Design of Antibody Fragments with Therapeutic Potential. Toxins (Basel). 2020; 12(4): 256.
- 70
Hassouneh LK, Timofiychuk OA, Babenko NA. Acid sphingomyelinase inhibitors, imipramine and zoledronic acid, increase skeletal muscle tissue sensitivity to insulin action at old age. Gen PhysiolBiophys. 2018 Mar;37(2):163-174.
- 71
Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs. 1976;11(1):45-54.
- 72
Hama N, Abe R, Gibson A, Phillips EJ. Drug-Induced Hypersensitivity Syndrome (DIHS)/Drug Reaction With Eosinophilia and Systemic Symptoms (DRESS): Clinical Features and Pathogenesis. J Allergy Clin Immunol Pract. 2022 May;10(5):1155-1167.e5.
- 73
Zhao Q, Sun L, Sun Y, Naisbitt D, Liu H, Zhang F. Dapsone hypersensitivity syndrome. Chin Med J (Engl). 2023 Jul 5;136(13):1560-1562.
- 74
Hobbs GD, Anderson AR, Greene TJ, Yealy DM. Comparison of hyperbaric oxygen and dapsone therapy for loxosceles envenomation. Acad Emerg Med. 1996 Aug;3(8):758-61.
- 75
Streeper RT, Izbicka E. Diethyl Azelate for the Treatment of Brown Recluse Spider Bite, a Neglected Orphan Indication. In Vivo. 2022 Jan-Feb;36(1):86-93.
- 76
Boissiere F, Masson R, Fluieraru S, Vitse J, Dessena L, Lefevre M, Bekara F, Herlin C. Le loxoscelismecutané, à proposd’une observation exceptionnelle de 9 casconsécutifs [Cutaneous loxoscelism, about an exceptional observation of 9 consecutive cases]. Ann ChirPlastEsthet. 2016 Dec;61(6):811-819. French
- 77
Czeck MP, Oppenheimer CL, Massagué J. Interrelationhip among receptor structures for insulin and peptide growth factors. Fed Proc. 1983;42:2598-602.
- 78
Ish-Shalon D, Christoffersen CT, Vorwek P, Sacerdoti-Sierra N, Naor D, De Metys P. Mitogenic properties of insulin and insulin analogues mediated by the insulin receptor. Diabetologia. 1997;40:S25-S31.
- 79
Pandini G, Frasca F, Mineo R, Sciacca L, Vigneri R, Belfiore A. Insulin/insulin-like growth factor I hybrid receptors have different biological characteristics depending on the insulin receptor isoform involved. J. Biol. Chem. 2002; 277:39684-39695.
- 80
Slaaby R, Schäffer L, Lautrup-Larsen I, Andersen AS, Shaw AC, Mathiasen IS et al. Hybrid receptors formed by insulin receptor (IR) and insulin-like growth factor I receptor (IGF-IR) have low insulin and high IGF-1 affinity irrespective of the IR splice variant. J Biol Chem. 2006 Sep 8;281(36):25869-74.
- 81
Gaspar NK, Gaspar APA, Bruno AFM, Travassos Neto P. Tratamento das lipoatrofias localizadas com insulina monocomponente. An B Dermatol. 1984;59:135-136.
- 82
Gaspar NK Tese: A importância da insulina nos processos regenerativos cutâneos e subcutâneos. Universidade Federal Fluminense 1995.
- 83
Gaspar NK, APA, Difficult to Heal Wounds Intralesional Insulin Therapy Trial. Journal of Surgery. 2020;8(6):184-189
- 84
Petersen MC, Shulman GI. Mechanisms of Insulin Action and Insulin Resistance. Physiol Rev. 2018 Oct 1;98(4):2133-2223.
3 Comments#
1- Systemic suspicious loxoscelism should be high, especially in children and younger adults, who presents cutaneous ulcer, hemolysis and coagulopathy.
2- The edges sharply defined and elevated, without purulent secretion aid diagnosis.
3- Debridement of necrotic lesions can accelerate healing.
4- Tetracyclines, especially doxycycline, given early, can limit the aggressive proteases. Topical applications may offer advantages, especially in infants67.
5- The only case taking more than 30days to heal, was n.2, who presented enormous crust that wasn’t debrided. In all our cases, cosmetics’ cicatricial aspects were good.
6- In case n.9, after occurs cicatricial ankylosis, was proceeded a surgical incision on the 2nd finger and immobilization with a splint, on extension, during insulin treatment, permitting anatomic position healing, in order to reduce the ankyloses with minimal defect and perfect function.
7- Healing time and applications number were related to lesions size and severity. Patients 1 and 3 with long intervals between applications, could have achieved faster healing.
9- The speed and time of wound resolution was dependent on the frequency and number of sessions.