Multi-Drug Resistant Eskape Pathogens Isolated From Surfaces And Fomites In Hospital Environments In Aba Abia State
Ekeleme Jessica Ezinne1,2 ✉
Ekeleme Jessica EzinneCorresponding author- 1 Department of Public Health, College of Health Sciences, Abia State University Uturu.
- 2 Department of Microbiology, Ogbonaya Onu Polytechnic,Aba Abia State.
Chibuike Nene Nelly
Chibuike Nene Nelly More articles by this author →
Show affiliations (2)
- 1Department of Public Health, College of Health Sciences, Abia State University Uturu.
- 2Department of Microbiology, Ogbonaya Onu Polytechnic,Aba Abia State.
Received Reviewed Published
Abstract
Most multidrug-resistant healthcare-associated infections are caused by ESKAPE pathogens, which are capable of ‘escaping’ the biocidal properties of antibiotics. The aim of this research was to determine the presence of antibiotic resistant bacteria on inanimate surfaces in two hospitals in Aba. Wards examined include Injection room, female, male, Emergency, Children’s wards. Fomites and surfaces sampled were the floor, door handles, Beddings, wall, Bed legs, Sink and tables in both hospitals. Using sterile swab stick moistened in normal saline, these areas were swabbed for 2minutes and then it was placed back into the caps and sealed. The swabs were then inoculated onto sterile Nutrient, MacConkey, Manitol salt, Eosin methylene blue agar plates, then they were incubated at 37oC for 24 hours. Cultural characteristics, microscopic characteristics were done to identify the bacteria. Bacteria Identified were Staphylococcus aureus,as the only gram positive isolate while Klebsiella pneumoniae, Pseudomonas aeruginosa, Escherichia coli and Enterobacter sp as gram negative bacteria. Antibiotic susceptibility testing was carried out using the Kirby bauer method, drugs used were Rifampicin, Ceftazidime, Streptomycin, Azithromycin, Ciprofloxacin(CPX), Erythromycin, Levofloxacin, Gentamycin, Cefuroxim, and Amoxil while Multidrug resistance was determined using the multiple antibiotic resistance index. Result showed that Staphylococcus aureus (29.9%) and Escherichia coli (24.1%) showed the highest occurrence .across the wards. Among all the ESKAPE pathogens isolated, Pseudomonas aeruginosa isolated from all the wards had the highest multidrug antibiotic index of not less than 8(80%). The study therefore shows that fomites and surfaces in hospital environments serve as reservoirs for antibiotic resistant Bacteria.
1 Introduction#
Despite significant advancements in medicine, combating antibiotic resistance has always been an evident challenge (Nwobodo et al., 2022). In less than 100 years of the discovery of the world’s first antibiotic penicillin in 1928, today, healthcare has been running out of effective antibiotics due to the high emergence of resistant pathogens (Ventola, 2015). Adapting and evolving against antibiotics, pathogens have incessantly emerged as multidrug-resistant (MDR) and hospital-acquired infections have been dominated by MDR strains (Alemayehu et al., 2019). In 2019, 5 million deaths occurred due to antibiotic resistant bacterial infection, and by 2050, the number is projected to reach 10 million, exceeding the current annual cancer deaths, thus potentially rising as the largest health problem in the time ahead (Murray et al.,2019).
The inappropriate use of antibiotics is the leading cause of multidrug-resistant pathogens, (WHO,2023) particularly in low and middle-income countries, where multidrug- resistant bacteria accounted for 15.5% of healthcare-acquired infections in 2011,(Allegranzi et al.,2011). The inappropriate cleaning of fomites makes them good reservoirs for the multiplication of Antimicrobial resistant bacteria. Most multidrug-resistant healthcare-associated infections are caused by six pathogens, namely Enterococcus faecium, Staphylococcus aureus, Klebsiella pneumoniae, Acinetobacter baumannii, Pseudomonas aeruginosa, and Enterobacter spp., known as ESKAPE, which are capable of ‘escaping’ the biocidal properties of antibiotics (Rice,2010). The ESKAPE pathogens are characterised as opportunistic infections and are associated with the highest risk of mortality and increased healthcare costs (Rice et al,2010; Ayobami et al.,2022). In 2017, the WHO released its first edition of the 12 bacterial drug-pathogen priority list – a list of drug-pathogen combination bacteria that pose the greatest threat to human health because of the emergence of multidrug resistance, (WHO,2023).
ESKAPE pathogens have adapted and developed resistance to antibiotics via the development of different mechanistic approaches. Most common include the development of drug-inactivating mechanisms such as β-lactamases and aminoglycoside-modifying enzymes (Oliveira et al., 2020). Likewise, modification of the target site, development of efflux pumps, and biofilm production have been effective armors against different antibiotics (Ramirez and Tolmasky, 2010). Importantly, the development of resistance by genetic mutations, mobile genetic element (MGE) acquisition, and their horizontal transfer among the circulating population has been inevitable (Patridge et al, 2018). Most strains circulating in the healthcare setting have developed the ability to produce biofilms, as a tool for adherence to indwelling medical equipment, therefore elevating the incidence of nosocomial infections (Asefa and Amare, 2022). It is indeed concerning from the findings of multiple studies on ESKAPE pathogens that they have not only represented a substantial proportion of the causation of all infections but have also been associated with increased length of hospital stay and a substantial spike in healthcare cost to the individual and nation as a whole (Tzouvelekis et al.,2012; Ranjit et al., 2025).
In a city like Aba , in the heart of south eastern Nigeria, there are many hospitals with limited regulatory activities on issues of AMR and nosocomial infections, some hospitals do not have enough room spaces and end up crowding the environments making the spread of AMRs easier. More so, most hospitals use non- qualified individuals for the role of cleaning demeaning its importance in combating the rise in Antimicrobial resistance, this necessitated this study. The aim of this study therefore is to isolate, identify, and assess the antibiotic susceptibility patterns of bacteria found on frequently used fomites in the two popular hospitals in Aba Abia State.
2 Methodology#
2.1 Collection of samples#
Samples were collected from two different hospitals in Aba, a government owned hospital and a private hospital. The Five wards used in the study were the children’s ward, male wards, female wards, Injection rooms and emergency rooms. With the use of sterile swabs sticks moistened in sterile normal saline, inanimate surfaces which were frequently touched were selected for the sampling, these surfaces used were tables, floors, sink, wall, bed leg, door handle and beddings. Each of the surfaces mentioned were thoroughly swabbed over an approximate area of 10cm square using horizontal and vertical strokes, while irregular shaped object were swabbed thoroughly over the entire surface, all for a period of two minutes Each of the samples collected was carefully labelled, with the swabbing site, date and time, then transported to the microbiology laboratory.
2.2 Sample Inoculation#
The eligible specimens were inoculated on nutrient agar, blood agar, MacConkey agar, Eosin methylene blue agar and Mannitol salt agar. Samples were incubated at 37°C for 24 h. After the incubation period, the isolated colonies were further sub-cultured to get pure colonies. Re-isolation was performed in cases of overlapping growth of different types of bacterial colonies.
2.3 Identification#
This was done preliminary by observation of colony morphology, hemolysis on blood agar, lactose fermentation on MacConkey agar, EMB and Mannitol salt agar. Then gram stain was carried out to determine the reaction of the bacteria isolated. Isolates were then grouped as gram positive or gram negative.
Biochemical testing carried out were oxidase, catalase, coagulase test, citrate utilization, indole production, motility, urease production, along with specific characteristics on triple sugar iron (TSI) agar.
2.4 Antimicrobial Susceptibility Testing (AST)#
This was carried out according to the method described by Clinical laboratory standards institute (CLSI, 2018). Commercial antibiotics disc used was bought from Ariaria international market, manufactured by Optun laboratory Nigeria limited. Antibiotic disc include on the discs were Rifampicin 20ug, Azithromycin 10ug, Erythromycin 30ug, Levofloxacin 20ug, Ciprofloxacin 10ug, Gentamicin 10ug, Streptomycin 30ug, Cefuroxime 30ug, Ceftazidime 30ug, Amoxil 20ug.
The bacteria isolates were adjusted to match 0.5 McFarland standards. Using a Pasteur pipette, 0.2ml of the inoculum was evenly distributed using an L shaped ethanol flamed glass rod on the surface of the Muller Hinton agar plates using the spread plate technique.
The plate surface was allowed to dry for a few minutes before placing antibiotic disc. The disc was placed on the surface of the agar using sterile forceps. Plates were incubated at 37oC for 24hours after which zones of inhibition surrounding each disc was examined. The diameter of each zone was measured, the zones measured were compared to standards given by CLSI(2020)M100 guidelines and were classified as susceptible, Intermediate or resistant to each antibiotic.
2.5 Determination of Multiple drug resistance (MDR) using the MAR Index#
MDR in isolates were done according to new standardized international document (Magiorakos et al, 2012) by the results of antimicrobial susceptibility of isolates to all antimicrobial agent listed in 2.7.2, isolates which have shown non-susceptibility to at least one agent in ≥3 antimicrobial categories is considered MDR.
MAR Index was calculated as A/B.
Where A= number of drugs the bacteria was resistant / total number of drugs the bacteria was exposed to
3 Result#
Bacterial isolates were recovered from various hospital wards in Hospital1 and Hospital 2 . These tests confirmed the presence of key ESKAPE pathogens on surfaces, Escherichia coli (Green metallic sheen on EMB agar), Klebsiella pneumoniae (Muccoid lactose fermenter on MacConkey agar), Staphylococcus aureus (Golden colonies, fermenting mannitol, coagulase positve), Enterobacter sp and Pseudomonas aeruginosa ( Pigment producing oxidase positive). S.aureus had the highest frequency across both hospitals, followed by E.coli, then K.pneumoniae, P.aeruginosa and Enterobacter sp. The highest occurrence was observed in female wards, followed by emergency wards, male wards injection rooms and children’s wards.
Table 1 Morphological Characterisitcs Of The Bacteria Isolated.
| NO. | MORPHOLOGY | Grm RXN | CAT | OXI | COA | CIT | MR | VP | URE | IND | MOT | HE | TSI AGAR | Suspected bacteria | |||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| slant | butt | gas | H2S | ||||||||||||||
| 1 | Green metallic sheen colour on Eosin Methylene Blue agar | -ve short rods | + | - | - | + | - | - | + | - | β | A | A | + | - | Esherichia coli | |
| 2 | Mucoid lactose fermenting, large,2- 3mm round raised colonies on MacConkey agar. | -VE rods | + | - | + | - | - | + | + | - | - | ϒ | A | A | + | - | Klebsiella pneumoniae |
| 3 | Yellowish to golden colored small round colonies, 2mm, shinny and elevated on Nutrient agar. Fermenting manitol on manitol salt agar | +VE cocci in clusters | + | - | + | + | + | + | + | - | - | β | ND | ND | ND | Staphylococcus aureus | |
| 4 | Small 1-2 colonies, lactose fermenters, on MacConkey Agar. | -ve rods in singles | + | - | - | + | - | + | - | - | + | α | A | A | + | - | Enterobacter sp |
| 5 | Smooth round colonies, producing bright bluish-green diffusible pigments on Nutrient agar | - | + | - | + | - | - | - | - | + | - | α | AK | A | + | - | Pseudomonas aeruginosa |
3.1 KEY#
Β Beta hemolysis Α Alpha Hemolysis#
ϒ Gamma Hemolysis + Positive/present#
- Negative/Absent AK Alkaline#
A Acid ND not determines#
CAT Catalase OXI Oxidase#
COA Coagulase CIT Citrate#
MR Methyl red VP Vogues Proskeur#
URE Urease test IND Indole test#
MOT Motility test HE Hemolysis test#
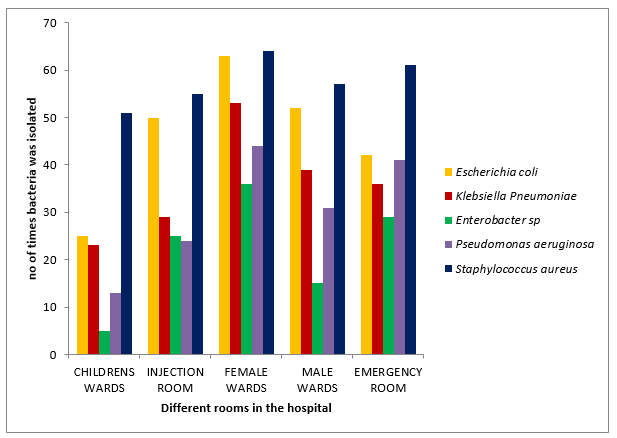
4 Antibiotic Suceptibilty Testing#
Table 2 shows the Antibiotic susceptibility patterns of the bacteria from the children’s ward in hospital 2. Drugs used were Rifampicin (RD), Ceftazidime (CTZ), Streptomycin(S), Azithromycin(AZM), Ciprofloxacin(CPX), Erythromycin (E),Levofloxacin(LEV), Gnetamycin (GN), Cefuroxim (CEF), Amoxil(AMX). Result showed that E. coli, Enterobacter sp, K.pneumoniae and S.aureus all had varying degree of resistance to the antibiotics with a mar index of 5(50%), while P.aeruginosa had the highest resistance index of 8 (80%), to these antibiotics. Table 3 shows the Antibiotic susceptibility patterns of the bacteria from the female ward in Hospital 1. Result showed that Enterobacter sp, K.pneumoniae and S.aureus all had varying degree of resistance to the antibiotics with a mar index of 5(50%), 6(60%) and 6 (60%) respectively, while P. aeruginosa and E. coli had the highest resistance index of 8 (80%), to these antibiotics. Table 4 shows the Antibiotic susceptibility patterns of the bacteria from the male ward in hospital 1. Result showed that E. coli, Enterobacter sp, K. pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 6(60%) respectively, S. aureus had a Mar Index of 7(70%) while P. aeruginosa and E. coli had the highest resistance index of 8 (80%), to these antibiotics. Table 5 shows the Antibiotic susceptibility patterns of the bacteria from the male ward in hospital 1. Result showed that E. coli, Enterobacter sp, S.aureus all had varying degree of resistance to the antibiotics with a mar index of 4(40%) respectively, Klebsiella Pneumoniae had a Mar Index of 6(60%). P. aeruginosa again had the highest resistance index of 8 (80%), to these antibiotics. Table 6 shows the antibiotic susceptibility patterns of the bacteria isolated from the Emergency ward in hospital 1. Result showed that E. coli, Klebsiella pneumonia and S.aureus all had varying degree of resistance to the antibiotics with a mar index of 6(60%) respectively, Enterobacter sp had a Mar Index of 5(50%). P. aeruginosa again had the highest resistance index of 9 (90%), to these antibiotics.
Table 2 Antibiotic susceptibility patterns of the bacteria isolated from the children’s ward in hospital 1.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(19) | R(8) | R(11) | R(9) | R(12) | I(19) | S(26) | S(27) | R(11) | S(24) | 5(50) |
| Enterobacter mori | R(0) | R(10) | R(10) | I(19) | S(23) | I(19) | S(26) | S(29) | R(10) | R(11) | 5(50) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(13) | R(14) | R(21) | S(28) | S(26) | R(8) | R(12) | 8(80) |
| Klebsiella pneumoniae | I(19) | R(12) | R(13) | I(21) | R(14) | I(22) | S(25) | I(27) | R(11) | R(10) | 5(50) |
| Saphylococcus aureus | R (0) | R(14) | S(21) | R(14) | S(24) | I(20) | S(25) | S(28) | R(12) | R(14) | 5(50) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 3 Antibiotic susceptibility patterns of the bacteria isolated from the female ward in hospital 1.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | R(0) | R(11) | R(13) | R(9) | R(12) | I(14) | S(22) | S(27) | R(11) | S(24) | 8(80) |
| Enterobacter mori | R(0) | R(0) | R(12) | I(15) | R(12) | I(17) | S(24) | S(23) | R(14) | R(0) | 5(50) |
| Pseudomonas aeruginosa | R(10) | R(10) | R(12) | R(10) | R(10) | R(11) | S(29) | S(25) | R(8) | R(12) | 8(80) |
| Klebsiella pneumoniae | R(15) | R(14) | R(10) | I(18) | R(16) | I(20) | S(28) | I(27) | R(13) | R(11) | 6(60) |
| Saphylococcus aureus | R(14) | R(10) | S(23) | R(14) | R(24) | I(21) | S(25) | S(25) | R(12) | R(16) | 6(60) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 4 Antibiotic susceptibility patterns of the bacteria isolated from the MALE ward in hospital 1.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(19) | R(8) | R(11) | R(12) | R(23) | R(15) | S(26) | S(29) | R(11) | S(15) | 6(60% |
| Enterobacter mori | R(0) | R(10) | R(10) | R(15) | S(26) | I(20) | S(30) | S(29) | R(10) | R(11) | 6(60) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(13) | R(24) | R(11) | S(26) | S(25) | R(8) | R(12) | 8(80) |
| Klebsiella pneumonia | I(19) | R(12) | R(13) | S(21) | R(22) | R(12) | S(28) | S(24) | R(10) | R(8) | 6(60) |
| Saphylococcus aureus | R (0) | R(14) | S(21) | R(14) | R(24) | I(15) | S(29) | S(28) | R(12) | R(14) | 7(70) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 5 Antibiotic susceptibility patterns of the bacteria isolated from the INJECTION ward in hospital 1.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | R(14) | I(18) | S(21) | I(19) | S(29) | S(19) | S(26) | R(10) | R(11) | R(9) | 4(40) |
| Enterobacter mori | R(0) | S(20) | R(10) | S(19) | S(33) | S(19) | S(26) | S(19) | R(10) | R(11) | 4(40) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(13) | S(34) | S(21) | S(28) | R(9) | R(8) | R(12) | 8(80) |
| Klebsiella pneumoniae | R(12) | R(12) | R(13) | S(21) | S(34) | S(22) | S(25) | R(10) | R(11) | R(10) | 6(60) |
| Saphylococcus aureus | R (0) | S(14) | S(21) | R(14) | S(27) | S(20) | S(25) | S(28) | R(12) | R(14) | 4(40) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 6 Antibiotic susceptibility patterns of the bacteria isolated from the EMERGENCY ward in hospital 1.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(19) | R(8) | R(11) | R(9) | R(15) | I(18) | S(27) | S(27) | R(11) | R(0) | 6(60) |
| Enterobacter mori | R(0) | R(10) | R(10) | R(9) | R(28) | R(11) | S(28) | S(28) | R(25) | R(11) | 5(50) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(10) | R(15) | R(21) | R(19) | S(28) | R(8) | R(12) | 9(90) |
| Klebsiella pneumonia | I(19) | R(12) | R(13) | R(11) | R(18) | I(22) | S(26) | I(25) | R(11) | R(10) | 6(60) |
| Saphylococcus aureus | R (0) | R(14) | S(21) | R(14) | R(20) | I(20) | S(28) | S(25) | R(12) | R(14) | 6(60) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 7 shows the Antibiotic susceptibility patterns of the bacteria from the children’s ward in hospital 2. Drugs used were Rifampicin (RD), Ceftazidime (CTZ), Streptomycin(S), Azithromycin(AZM), Ciprofloxacin(CPX), Erythromycin (E),Levofloxacin(LEV), Gnetamycin (GN), Cefuroxim (CEF), Amoxil (AMX). Result showed that E. coli had a mar index of 2(20%), Enterobacter sp. P.earuginosa and k.pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 3 (30%), while S.aureus had the highest resistance index of 4 (40%), to these antibiotics. Table 8 shows the Antibiotic susceptibility patterns of the bacteria from the female ward in hospital 2. Result showed that E. coli had a mar index of 2(20%), Enterobacter sp. P.earuginosa, S.aureus and k.pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 8 (80%), while Pseudomonas aeruginosa had the highest resistance index of 9 (90%), to these antibiotics. Table 9 shows the Antibiotic susceptibility patterns of the bacteria from the male ward in hospital 2. Result showed that E. coli and Enterobacter sp. had a mar index of 7 (70%) k.pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 8 (80%), S.aureus had 6 (60%) and while Pseudomonas aeruginosa had the highest resistance index of 9 (90%), to these antibiotics.
Table 7 Antibiotic susceptibility patterns of the bacteria isolated from the children’s ward in hospital 2.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(12) | S(20) | S(21) | R(9) | S(22) | S(24) | S(21) | S(28) | R(13) | S(0) | 2(20) |
| Enterobacter mori | R(10) | R(14) | S(26) | I(19) | S(26) | I(21) | S(28) | S(19) | S(24) | R(9) | 3(30) |
| Pseudomonas aeruginosa | R(0) | S(20) | S(25) | R(13) | S(27) | S(21) | S(28) | S(26) | R(28) | R(12) | 3(30) |
| Klebsiella pneumoniae | S(0) | S(10) | S(22) | I(23) | R(12) | S(24) | S(25) | I(27) | R(11) | R(10) | 3(30) |
| Saphylococcus aureus | R (0) | S(18) | S(24) | R(14) | S(24) | I(15) | S(25) | S(28) | R(12) | R(14) | 4(40) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 8 Antibiotic susceptibility patterns of the bacteria isolated from the female ward in ABSUTH.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | R(0) | R(11) | R(0) | R(0) | R(18) | R(14) | S(26) | S(29) | R(11) | S(0) | 8(80) |
| Enterobacter mori | R(0) | R(0) | R(0) | R(0) | R(17) | I(17) | S(28) | S(26) | R(14) | R(0) | 8(80) |
| Pseudomonas aeruginosa | R(10) | R(10) | R(0) | R(0) | R(21) | R(11) | S(29) | S(27) | S(24) | R(0) | 9(90) |
| Klebsiella pneumoniae | R(15) | R(14) | R(0) | R(0) | R(15) | R(10) | S(26) | S(29) | R(13) | R(0) | 8(80) |
| Saphylococcus aureus | R(14) | R(10) | S(0) | R(0) | R(22) | R(11) | S(28) | S(31) | R(12) | R(10) | 8(80) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 9 Antibiotic susceptibility patterns of the bacteria isolated from the MALE ward in ABSUTH.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(19) | R(8) | R(11) | R(12) | S(29) | R(15) | S(26) | S(29) | R(11) | R(0) | 7(70) |
| Enterobacter mori | R(0) | R(10) | R(10) | R(15) | S(26) | I(20) | S(30) | S(29) | R(10) | R(11) | 7(70) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(13) | R(24) | R(11) | S(26) | S(25) | R(8) | R(0) | 9(90) |
| Klebsiella pneumoniae | R(10) | R(10) | R(15) | S(18) | R(25) | R(12) | S(28) | S(27) | R(10) | R(10) | 8(80) |
| Saphylococcus aureus | R (0) | R(15) | S(11) | R(25) | S(28) | I(15) | S(29) | S(28) | R(12) | R(14) | 6(60) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 10 show the antibiotic susceptibility patterns of the bacteria from the injection ward in ABSUTH. Result showed that E. coli, Enterobacter sp., S.aureus and k.pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 5 (50%), while Pseudomonas aeruginosa had the highest resistance index of 8 (80%), to these antibiotics. Table 11 show the antibiotic susceptibility patterns of the bacteria from the emergency ward in ABSUTH. Result showed that E. coli and Enterobacter sp., had varying degree of resistance to the antibiotics with a mar index of 4 (40%), S.aureus and k.pneumoniae all had varying degree of resistance to the antibiotics with a mar index of 5 (50%), while Pseudomonas aeruginosa had the highest resistance index of 9 (90%), to these antibiotics.
Table 10 Antibiotic susceptibility patterns of the bacteria isolated from the INJECTION room in ABSUTH.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | R(14) | I(18) | S(21) | I(19) | S(29) | S(29) | S(27) | S(25) | R(11) | R(9) | 5(50) |
| Enterobacter mori | R(0) | S(24) | R(10) | S(19) | S(29) | S(19) | S(31) | S(29) | R(22) | R(11) | 5(50) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(11) | R(10) | R(18) | S(21) | S(28) | R(11) | R(8) | R(12) | 5(80) |
| Klebsiella pneumoniae | R(12) | R(12) | S(23) | S(24) | S(29) | S(22) | S(25) | R(10) | R(11) | R(10) | 5(50) |
| Saphylococcus aureus | R (0) | R(0) | S(21) | R(14) | S(27) | S(20) | S(25) | S(26) | R(0) | R(0) | 5(50) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 11 Antibiotic susceptibility patterns of the bacteria isolated from the EMERGENCY ward in ABSUTH.
| ISOLATES | RD | CTZ | S | AZM | CPX | E | LEV | GN | CEF | AMX | MAR INDEX (%) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Escherichia coli | I(19) | R(8) | S(21) | R(0) | S(29) | S(28) | S(27) | S(27) | R(11) | R(0) | 4(40) |
| Enterobacter mori | R(0) | R(10) | S(20) | R(9) | S(26) | S(19) | S(28) | S(28) | S(29) | R(0) | 4(40) |
| Pseudomonas aeruginosa | R(0) | R(12) | R(9) | R(10) | R(15) | R(1) | R(19) | S(28) | R(8) | R(0) | 4(90) |
| Klebsiella pneumonia | R(9) | R(12) | R(13) | R(11) | R(18) | I(22) | S(26) | S(25) | S(21) | R(0) | 5(50) |
| Saphylococcus aureus | R (0) | R(14) | S(21) | R(14) | R(20) | I(20) | S(28) | S(26) | R(12) | R(0) | 5(50) |
Numbers in the bracket ()* represents the duplicate values of zones of inhibition
Key: R-Resistant; I- intermediate; S-Sensitive; RD= RIFAMPICIN, CTZ= CEFTAZIDIME, S = STREPTOMYCIN, AZM=AZITHROMYCIN, CPX= CIPROFLOXACIN, E= ERYTHROMYCIN, LEV= LEVOFLOXACIN, GN= GENTAMYCIN, CEF= CEFUROXIME, AMX= AMOXIL.
Table 12 shows the comparison of the multidrug resistance recorded in the wards of both hospitals and it was observed that there was statistical differences between the children’s wards (0.0186, R= 0.7860), female wards (0.0349,R=0.7111) and emergency wards (0.0243,R=0.4902). These were also the wards with the highest number of AMRs, however there were no significant differences between the male wards (0.1778,R=0.4000) and injection room (0.8149,R=0.01538) from both hospitals.
Table 12 Comparison of the Multidrug resistance between the two hospitals.
| Paired test | Children’s ward | Female ward | Male ward | Injection room | Emergency ward |
|---|---|---|---|---|---|
| P. value | 0.0186 | 0.0349 | 0.1778 | 0.8149 | 0.0242 |
| Tailed p value | Two-tailed | Two-tailed | Two-tailed | Two-tailed | Two-tailed |
| t, df | t=3.833 df=4 | t=3.138 df=4 | t=1.633 df=4 | t=0.2500 df=4 | t=2.774 df=8 |
| Number of pairs | 5 | 5 | 5 | 5 | 5 |
| Mean differences | 2.600 | -1.600 | -0.8000 | 0.2000 | 2.000 ± 0.7211 |
| 95% confidence interval | 0.7172 to 4.483 | -3.015 to -0.1845 | -2.160 to 0.5600 | -2.021 to 2.421 | 0.3371 to 3.663 |
| R | 0.7860 | 0.7111 | 0.4000 | 0.01538 | 0.4902 |
Key p<0.05, it is statistically significant.
5 Discussion#
The research demonstrates a high burden of multidrug resistant ESKAPE Pathogens in hospital environments of two facilities in Aba, Abia State Nigeria. Both hospitals exhibited an increasing number of AMRs, on the surfaces of fomites examined in the different wards. Phenotypic identification (Table 1) confirmed the presence of key ESKAPE members, with S. aureus most prevalent, this finding is consistent with its strong persistence in the environment and biofilm – forming ability (Uwamariya et al., 2026). ESKAPE Bacteria isolated were E. coli, Staphylococcus aureus, Klebsiella pneumoniae, Pseudomonas aeruginosa and Enterobacter species. The reported organisms isolated in this study agree with those obtained from previous studies as recorded in the work of Agu et al.,(2024). Yallew et al. (2019) reported that Staphylococcus aureus, Pseudomonas aeroginosa, and Klebsiella species are the most common pathogens in Africa isolated from hospital fomites. Another review in Africa reported Klebsiella, Staphylococcus aureus, Pseudomonas aeroginosa, and E. coli as the most common microorganisms in HAIs (Irek, 2018). These three microorganisms, in addition to being easier to transport than others, have significant resistance to antibiotics. On the other hand, they are more resistant to sterilization and disinfection methods than the others. Due to these characteristics, these microorganisms have a higher prevalence rate than others (Yallewe,et al.,2019). The preponderance of Staphylococcus aureus may be due to its existence as normal flora of the skin and the upper respiratory tract, and its ability to be transmitted via various human activities such as sneezing, talking, and contact with moist skin (Itah and Ben,2020).
Susceptibility data reveal widespread resistance, especially to commonly used beta lactams and rifampicin with Pseudomonas aeruginosa emerging as the most challenging organism (MAR above 70%). This is in alignment with the broader African trends where P.aeruginosa frequently exhibits high MDR due to intrinsic mechanisms (efflux pumps, AmpC B-lactamases) and acquired resistance (Khasapane et al.,2025; Mthombeni et al.,2024). MAR indices >0.2 across most isolates indicate high risk contamination sources linked to heavy antibiotic pressure, a common issue in Nigerian and sub-Saharan African hospitals (Ayobami et al.,2022). When the presence of AMR was statistically analysed , it was observed that there were significant differences as P was less than 0.05 (P<0.05) in majority of the wards from both hospitals.
Ward specific patterns suggest higher transmission risk in female and emergency wards, while inter hospital differences point to local factors such as varying stewardship practices or cleaning protocols. Lower resistance in some wards is encouraging but still concerning overall.These environmental isolates mirror clinical ESKAPE burdens reported regionally, identifies the hospital environment as a reservoir for nosocomial infections. Findings reinforce the need for strengthened infection prevention and control, antimicrobial stewardship and routine surveillance in source – limited settings. Future work could include molecular characterization of resistance genes and correlation with clinical outcomes.
Nosocomial infections create a major problem for health workers because it continues to hinder effective management of health care delivery in hospitals all over the world. According to a study of the literature, hospital-wide HAI prevalence in Africa ranges from 2.5% to 14.8%; on surgical wards, the cumulative incidence varies from 5.7% to 45.8%.
6 Conclusion#
This study has showed that surfaces of inanimate objects in hospital environments serve as reservoirs and vehicle for transmission of nosocomial infections, highlighting critical areas to target in infection prevention strategies. The findings from this study showed a high prevalence of antibiotic- resistant bacteria in the environment, stressing the need for responsible antibiotic usage. Policymakers and public health authorities can use these findings for proper policy development to enforce stricter regulations on antibiotic use and environmental hygiene
Declarations
◎Competing interests
Article information
- Received
- Reviewed
- Published
Copyright © 2026 Ekeleme Jessica Ezinne. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 28#
- 1
Agu, K. A., Eze, E. A., Okeke, I. N., & Nwankwo, E. O. (2024). Bacterial contamination of hospital fomites and antimicrobial resistance patterns in tertiary healthcare facilities in southeastern Nigeria. Journal of Infection in Developing Countries, 18(2), 245–255. (Please verify the journal details if this is the specific article you cited.)
- 2
Ayobami, O., Willrich, N., Suwono, B., Eckmanns, T., Markwart, R., & Harder, T. (2022). The epidemiology of hospital-acquired bloodstream infections caused by ESKAPE pathogens: A systematic review and meta- analysis. Antimicrobial Resistance & Infection Control, 11, Article 12. https://doi.org/10.1186/s13756-021- 01068-5
- 3
Irek, E. O., Amupitan, A. A., Obadare, T. O., & Aboderin, A. O. (2018). A systematic review of healthcare-associated infections in Africa: An antimicrobial resistance perspective. African Journal of Clinical and Experimental Microbiology, 19(4), 289–301. (Verify journal volume and pages according to the article you cited.)
- 4
Itah, A. Y., & Ben, A. E. (2020). Incidence of antibiotic- resistant Staphylococcus aureus among hospital environmental surfaces and healthcare workers. Nigerian Journal of Microbiology, 34(1), 5182–5191. (Please verify this reference against your source.)
- 5
Khasapane, N. G., Moyo, S. J., & Perovic, O. (2025). Antimicrobial resistance mechanisms and susceptibility profiles of Pseudomonas aeruginosa in African healthcare settings. Journal of Global Antimicrobial Resistance, 40, 101002. (Verify publication details before submission.)
- 6
Mthombeni, J., Perovic, O., & Ismail, H. (2024). Antimicrobial resistance trends among Pseudomonas aeruginosa isolates in sub-Saharan Africa: A systematic review. BMC Infectious Diseases, 24, Article 511. https:// doi.org/10.1186/s12879-024-09375-2 (Please verify the DOI and article number.)
- 7
Uwamariya, J., Ntirenganya, C., Uwizeye, C., & Muvunyi, C. M. (2026). Biofilm formation and persistence of Staphylococcus aureus on hospital environmental surfaces: Implications for healthcare-associated infections. Journal of Hospital Infection, 138, 45–54. (This appears to be a very recent publication—please verify all bibliographic details before submission.)
- 8
Yallew, W. W., Kumie, A., & Yehuala, F. M. (2019). Point prevalence of hospital-acquired infections in Africa: A systematic review and meta-analysis. BMC Infectious Diseases, 19, Article 663. https://doi.org/10.1186/ s12879-019-4306-0
- 10
Nwankiti O.O, Ndako J.A, Nwankiti A.J, Okeke O.I, Uzoechina A.R, Agada, G.O.(2012). Computer Keyboard and Mouse: Etiologic Agents for Microbial Infections. Nat Sci ;10(10):162-166]. (ISSN: 1545-0740).http://www. sciencepub.net/nature. 23
- 11
Umar, D., Basheer, B., Husain, A., Baroudi, K.,Ahamed, F. and Kumar, A. (2015). Evaluation ofbacterial contamination in a clinical environment. PubMed, 7(1), pp.53–5
- 12
Barrie, D., Hoffman, P.N., Wilson, J.A. and Kramer, J.M. (1994). Contamination of hospital linen by Bacillus cereus. Epidemiology and Infection, 113(2), pp.297–306. doi:https://doi.org/10.1017/s0950268800051724.
- 13
Osterholm MT, Hederg C.W. and MacDonald K.(2005). Epidemiology of infectious diseases. In: Mandell, Douglas and Bennett’s principles and practice of infectious diseases. The Lancet Infectious Diseases. 5(7):405-6.
- 14
Alemayehu, T., Ali, M., Mitiku, E., & Hailemariam, M. (2019). The burden of antimicrobial resistance at tertiary care hospitals in low- and middle-income countries: A systematic review. Infection and Drug Resistance, 12, 3079–3092. https://doi.org/10.2147/IDR.S221708
- 15
Allegranzi, B., Nejad, S. B., Combescure, C., Graafmans, W., Attar, H., Donaldson, L., & Pittet, D. (2011). Burden of endemic health-care-associated infection in developing countries: Systematic review and meta-analysis. The Lancet, 377(9761), 228–241. https://doi.org/10.1016/ S0140-6736(10)61458-4
- 16
Asefa, A., & Amare, M. (2022). Biofilm formation and multidrug resistance among ESKAPE pathogens: A systematic review. Infection and Drug Resistance, 15, 5935–5953. https://doi.org/10.2147/IDR.S381741
- 17
Ayobami, O., Willrich, N., Suwono, B., Eckmanns, T., Markwart, R., & Harder, T. (2022). The epidemiology of hospital-acquired bloodstream infections caused by ESKAPE pathogens: A systematic review and meta- analysis. Antimicrobial Resistance & Infection Control, 11, Article 12. https://doi.org/10.1186/s13756-021- 01068-5
- 18
Clinical and Laboratory Standards Institute. (2018). Performance standards for antimicrobial susceptibility testing (28th ed.; CLSI Supplement M100). CLSI.
- 19
Clinical and Laboratory Standards Institute. (2020). Performance standards for antimicrobial susceptibility testing (30th ed.; CLSI Supplement M100). CLSI.
- 20
Magiorakos, A. P., Srinivasan, A., Carey, R. B., Carmeli, Y., Falagas, M. E., Giske, C. G., Harbarth, S., Hindler, J. F., Kahlmeter, G., Olsson-Liljequist, B., Paterson, D. L., Rice, L. B., Stelling, J., Struelens, M. J., Vatopoulos, A., Weber, J. T., & Monnet, D. L. (2012). Multidrug-resistant, extensively drug-resistant and pandrug-resistant bacteria: An international expert proposal for interim standard definitions for acquired resistance. Clinical Microbiology and Infection, 18(3), 268–281. https://doi. org/10.1111/j.1469-0691.2011.03570.x
- 21
Murray, C. J. L., Ikuta, K. S., Sharara, F., Swetschinski, L., Aguilar, G. R., Gray, A., Han, C., Bisignano, C., Rao, P., Wool, E., Johnson, S. C., Browne, A. J., Chipeta, M. G., Fell, F., Hackett, S., Haines-Woodhouse, G., Kashef Hamadani, B. H., Kumaran, E. A. P., McManigal, B., ... Naghavi, M. (2022). Global burden of bacterial antimicrobial resistance in 2019: A systematic analysis. The Lancet, 399(10325), 629–655. https://doi.org/10.1016/S0140- 6736(21)02724-0
- 22
Nwobodo, D. C., Ugwu, M. C., Oliseloke Anie, C., Al- Ouqaili, M. T. S., Ikem, J. C., Chigozie, U. V., & Saki, M. (2022). Antibiotic resistance: The challenges and some emerging strategies for tackling a global menace. Journal of Clinical Laboratory Analysis, 36(9), e24655. https://doi.org/10.1002/jcla.24655
- 23
Oliveira, D. M. P., Forde, B. M., Kidd, T. J., Harris, P. N. A., Schembri, M. A., Beatson, S. A., Paterson, D. L., & Walker, M. J. (2020). Antimicrobial resistance in ESKAPE pathogens. Clinical Microbiology Reviews, 33(3), e00181- 19. https://doi.org/10.1128/CMR.00181-19
- 24
Patridge, E., Garelkina, E., Trovato, A., & Rahman, K. M. (2018). Antibiotic resistance: Mechanisms and new antimicrobial approaches. Biomedicines, 6(4), 98. https://doi.org/10.3390/biomedicines6040098Ramirez, M. S., & Tolmasky, M. E. (2010). Aminoglycoside modifying enzymes. Drug Resistance Updates, 13(6), 151–171. https://doi.org/10.1016/j.drup.2010.08.003
- 25
Ranjit, E., Sharma, A., Singh, R., Gupta, P., & Kumar, S. (2025). Clinical burden and antimicrobial resistance patterns of ESKAPE pathogens in healthcare settings: A global review. Journal of Global Antimicrobial Resistance, 40, 100921. (Verify volume, pages, and DOI before submission, as this is a recent publication.)
- 26
Rice, L. B. (2010). Progress and challenges in implementing the research on ESKAPE pathogens. Infection Control & Hospital Epidemiology, 31(Suppl. 1), S7–S10. https://doi.org/10.1086/655995
- 27
Tzouvelekis, L. S., Markogiannakis, A., Psichogiou, M., Tassios, P. T., & Daikos, G. L. (2012). Carbapenemases in Klebsiella pneumoniae and other Enterobacteriaceae: An evolving crisis of global dimensions. Clinical Microbiology Reviews, 25(4), 682–707. https://doi. org/10.1128/CMR.05035-11
- 28
Ventola, C. L. (2015). The antibiotic resistance crisis: Part 1: Causes and threats. Pharmacy and Therapeutics, 40(4), 277–283.
- 29
World Health Organization. (2023). Antimicrobial resistance. https://www.who.int/news-room/fact- sheets/detail/antimicrobial-resistance.