Cholangitis due to Cholecysto-Hydatid Cyst Fistula
Nizar Khedhiri
Nizar Khedhiri More articles by this author →Haithem Zaafouri ✉
Haithem ZaafouriCorresponding author More articles by this author →Meryam Mesbahi
Meryam Mesbahi More articles by this author →Anis Ben Maamer
Anis Ben Maamer More articles by this author →
Published
A 36-year-old female patient was referred to our department with the complaint of acute abdominal pain in the right hypochondrium, fever, and jaundice. Laboratory findings were suggestive of obstructive jaundice and an increase in infectious parameters.
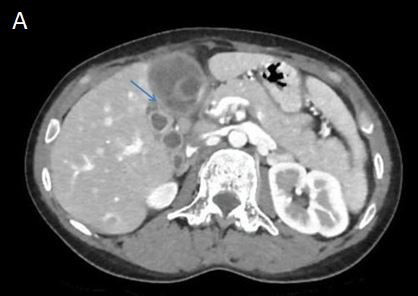
Ultrasound and abdominal CT scan showed a 43*41*56 mm cystic formation of segment IVb of the liver communicating with the gallbladder via a fistula, as well as a discrete dilatation of the main bile duct (Figure 1).
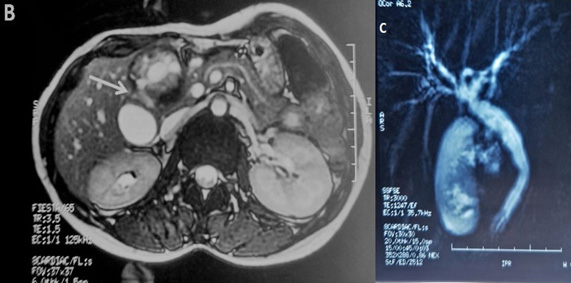
MRCP revealed 4.5 cm liver cyst in segment IVb with internal echoes and irregular hyperintensities inside seen in direct communication with gallbladder and a heterogeneous T2 content of the vesicular fundus with no detectable lithiasis (Figure 2, Panel B and C). Common bile duct (CBD) was dilated with internal debris seen inside.
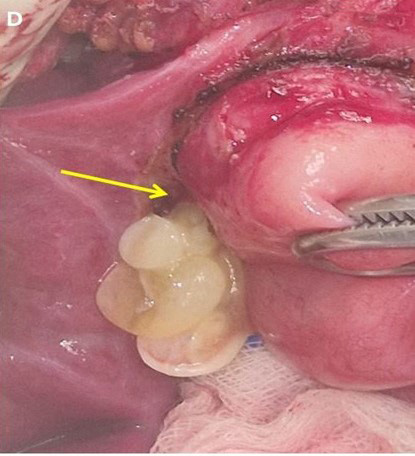
A diagnosis of rupture of a hydatid cyst into the gallbladder with a fistulous communication was made. The patient underwent a laparotomy, which confirmed the imaging findings of the fistula (Figure 3). The patient was treated: cholecystectomy fistulization was detected between the gallbladder and hydatid cyst. Pericystectomy was performed along with cholecystectomy following sterilization maneuvers for cyst hydatids, CBD exploration and T tube. The postoperative period was uneventful.
Article information
- Published
Copyright © 2025 Dr. Haithem Zaafouri. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy