Successful Surgical Management of Trans-catheter Mitral Clip PASCAL Embolization into Right Coronary Artery
Published in Journal of Cardiovascular Diseases
Salvatore Poddi1 ✉
Salvatore PoddiCorresponding author- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Livio San Biagio1
Livio San Biagio- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Irene Maffei1
Irene Maffei- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Gina Mazzeo1
Gina Mazzeo- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Bruno Dal Corso1
Bruno Dal Corso- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Alessandra Francica1
Alessandra Francica- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Valeria Gasparetto2
Valeria Gasparetto- 2 Division of Cardiovascular Diseases, Pederzoli Hospital, Peschiera del Garda, Italy
Diego Maffeo3
Diego Maffeo- 3 Division of Cardiovascular Diseases, Poliambulanza Hospital Istitute, Brescia, Italy
Giovanni Battista Luciani1
Giovanni Battista Luciani- 1 Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
Show affiliations (3)
- 1Division of Cardiac Surgery, University of Verona Medical Center, Verona, Italy
- 2Division of Cardiovascular Diseases, Pederzoli Hospital, Peschiera del Garda, Italy
- 3Division of Cardiovascular Diseases, Poliambulanza Hospital Istitute, Brescia, Italy
Published
Abstract
Transcatheter edge-to-edge repair using a PASCAL device is safe and effective. Post-procedure embolization is a rare phenomenon. The present case report is to describe the very first case of PASCAL device embolization into the right coronary artery, which was successfully removed through emergency surgery.
1 Background#
Percutaneous, trans-catheter edge-to-edge mitral valve repair (TMVR) using the PASCAL device (Edwards Lifesciences, Irvine, CA, USA) demonstrated to be a safe and effective procedure1. Embolization into the right coronary artery (RCA) is a rare complication of TMVR2-5. We report the very first case of an embolized PASCAL clip into the RCA ostium, successfully removed through surgical approach.
2 Case Presentation#
Patient signed a written informed consent for potential publication of data; institutional review board (IRB) approval was not required.
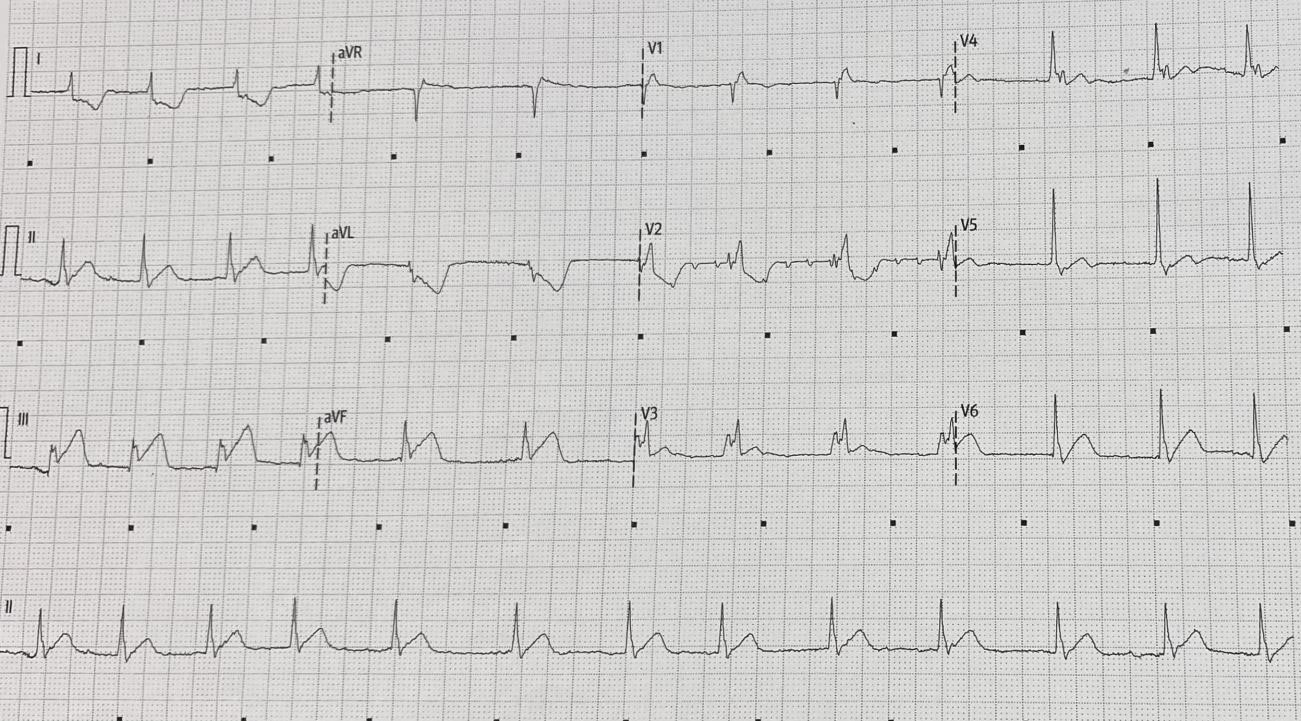
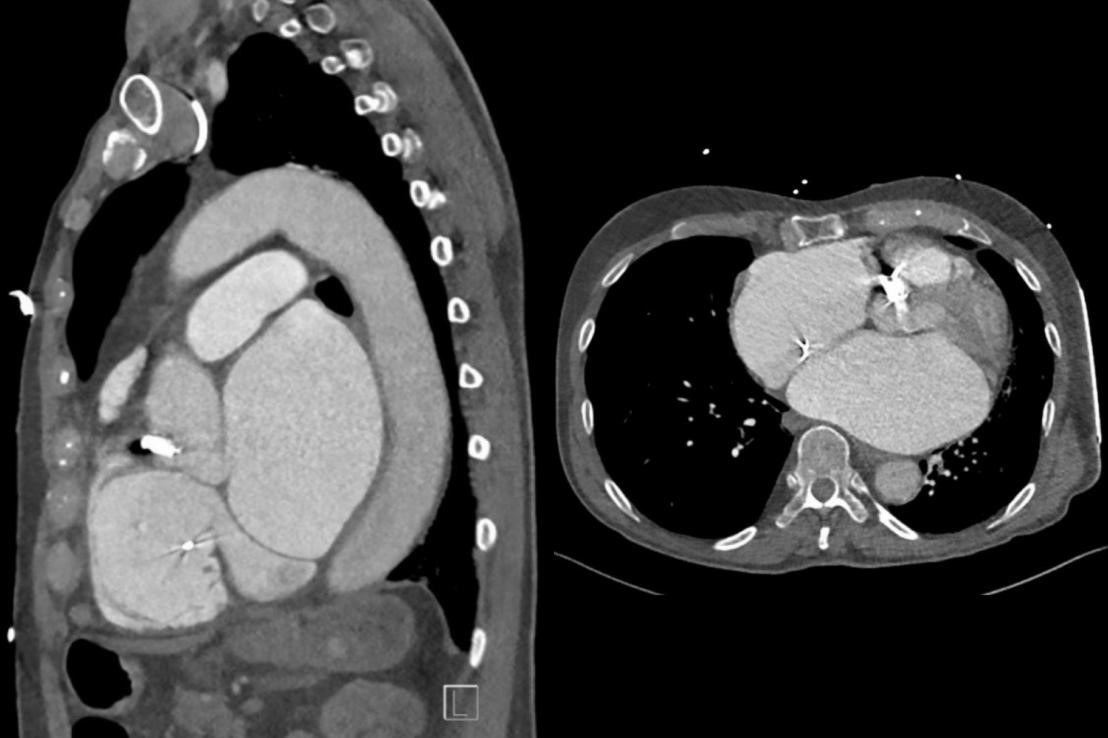
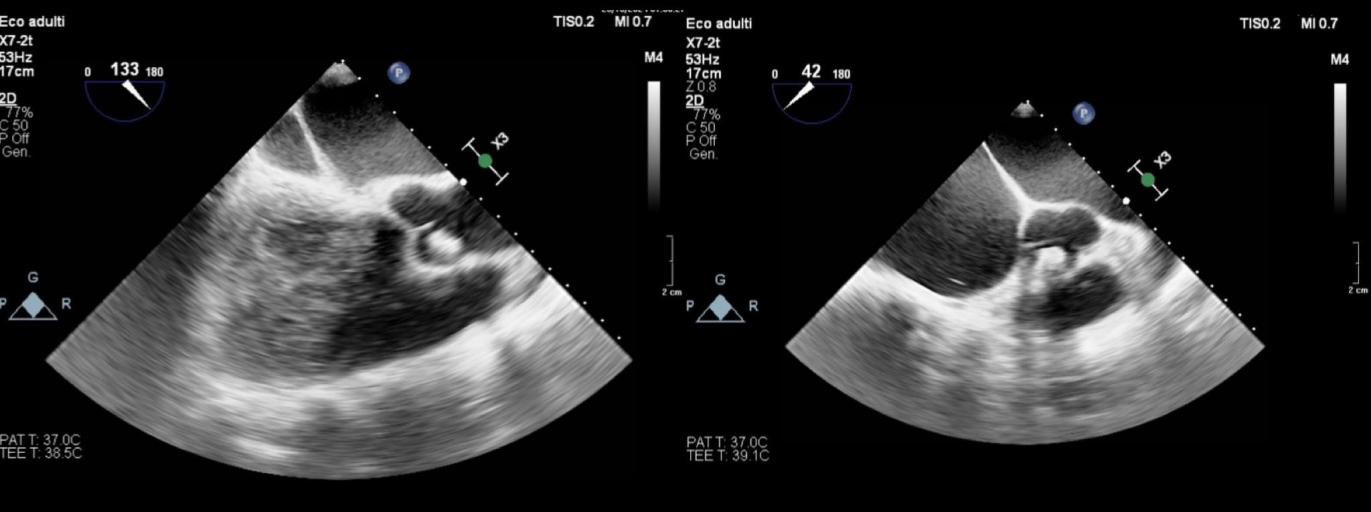
An 82-year-old male presented to a nearby Emergency Department for ongoing chest pain started about six hours earlier, ten days after patient undergoing PASCAL procedure for severe secondary mitral regurgitation (MR). Past medical history included systemic hypertension, permanent atrial fibrillation, Pace-maker implantation. Electrocardiogram (EKG) showed signs of inferior STEMI (Figure 1). Trans-thoracic echocardiogram showed mild left ventricular (LV) dysfunction with inferior akinesia, severe MR, severe right ventricular (RV) dysfunction, moderate tricuspid regurgitation, severe left atrium enlargement. Chest CT scan was done to rule out acute type A dissection; it incidentally found signs of an occluding foreign body in the RCA ostium (Figure 2). At this time, suspicion for clip embolization was raised and the patient was transferred immediately to our institution for emergent cardiac surgery. Intra-operative pre-cardiopulmonary bypass trans-esophageal echocardiogram (TEE) confirmed suspicion of clip embolization (Figure 3).
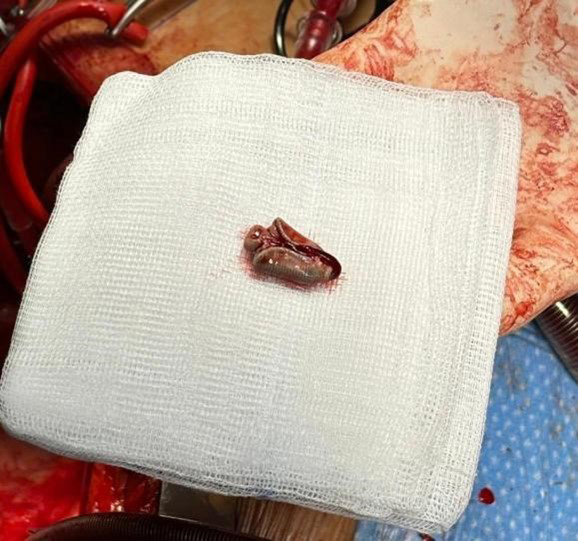
Via median sternotomy, using normothermic cardiopulmonary bypass, the aorta was clamped and retrograde cardioplegia was delivered. The aortic root was incised, and a clip was easily identified into the RCA ostium. The clip was gently removed (Figure 4). After clip removal, accurate inspection of RCA ostium was done; selective RCA cardioplegia was then carefully delivered to both protect RV and check for indirect signs of RCA thrombosis and/or dissection (high resistance to cardioplegia flow). Since the RCA seemed to be clear from sequelae, no coronary artery bypass graft (CABG) was performed. Via left atrial approach, mitral valve replacement (MVR) was done using a 33-mm bio-prosthesis. After clamp removal, TEE showed severe biventricular dysfunction despite high-dose inotropes, therefore intra-aortic balloon pump (IABP) was placed to aide CPB weaning. Patient was then transferred to the ICU. First post-operative ECG showed signs of inferior ischemia, Troponine T was 14200 ng/L. On post-operative day (POD) 3 EKG improved, and Troponine T was 5290 ng/L; patient hemodynamics also improved and IABP was removed.
3 Discussion#
PASCAL TMVR is generally reported to be a safe and effective procedure1. Among TMVR devices, few cases of RCA embolization are described: three patients underwent a percutaneous extraction, two of them dying shortly thereafter2-4. Surgical removal has previously been described, combined with RCA CABG and MVR5. To the best of our knowledge, no PASCAL device coronary embolization has been reported to date. We described the very first PASCAL clip embolization into the RCA ostium and its successful surgical removal. Despite percutaneous snaring is less invasive, it could not allow an accurate RCA assessment; also, distal embolization during snaring may happen4. In our opinion, surgical removal should be always discussed as it provides some advantages: first, an easier clip removal. Then, ostium and proximal RCA can be accurately assessed both visually and through selective cardioplegia, as a high resistance to flow would be an indirect sign of thrombosis and/or dissection. In the latter case, surgical approach allows to proceed directly with CABG. Finally, mitral valve surgery to treat native disease can also be associated. Curiously, all the coronary embolization cases reported the RCA ostium involvement; we may speculate that could be linked to the aortic root hemodynamics. Another reason could be that left coronary embolization would lead to ventricular fibrillation and sudden cardiac death, with no possibility to rescue the patient and report the case.
4 Conclusions#
We reported the very first case of a PASCAL device embolization into the RCA ostium, successfully managed through surgical approach. Surgery should always be discussed in cases of coronary embolization.
Declarations
✓Patient consent
€Funding
✎Author contributions
◎Competing interests
Article information
- Published
Copyright © 2025 Salvatore Poddi MD. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 5#
- 1
Srinivasan A, Brown J, Ahmed H, Daniel M. PASCAL repair system for patients with mitral regurgitation: A systematic review. Int J Cardiol. 2023 Apr 1;376:108-114.
- 2
Zhou L, Lin C, Torosyan N, Rao S, Mehra A, Bender A. Percutaneous Retrieval of an Embolized Transcatheter Mitral Valve Repair Clip Causing ST-Segment Elevation Myocardial Infarction. JACC Case Rep. 2023 Jan 27;9:101745.
- 3
Chitsaz S, Jumean M, Dayah T, Rajagopal K, Kar B. Late MitraClip Embolization: A New Cause of ST-Segment-Elevation Myocardial Infarction. Circ Cardiovasc Interv. 2016 Nov;9(11):e004271.
- 4
Schueler R, Jensen C, Wolf A, Schmitz T. Acute occlusion of the right coronary artery: an unusual case. Eur Heart J. 2018 Dec 7;39(46):4126.
- 5
Nitz J, Karamchandani M, Phan T, Carpino P, Couper G. Transcatheter mitral valve repair clip embolization to the right coronary artery. JTCVS Tech. 2023 Sep 19;22:118-119.