Prevalence Of Headache Among Medical Student
Published in The American Journal of Public Health
Lamya A Darwish ✉
Lamya A DarwishCorresponding author More articles by this author →Associate Professor College
Associate Professor College More articles by this author →
Published
Abstract
BackgroundHeadache is one of the most common complaints during the medical curriculum and occurs due to numerous psychological and physical stressors, which are more prevalent among medical students than in the general population. This study aimed to evaluate the frequency, characteristics, and types of headaches, as well as their precipitating and associated variables among medical students.
AimHeadache is among the commonest complaints in medical students it could be due to many physical or psychological stressors The aim of this study is to assess the prevalence of headache among male and female medical students Methods: This cross-sectional study was conducted at Al-Ameed University Faculty of Medicine and Kerbala University Faculty of Medicine from October 2023 to February 2025. First- to sixth-year medical students who had experienced some form of headache in their lifetime and had headache attacks during the past 6 months were included. All participants completed a structured checklist covering demographic data, associated factors, and headache characteristics. Medical stages were classified into three groups: Group 1 (first and second years), Group 2 (third and fourth years), and Group 3 (fifth and sixth years) to assess significant differences in headache characteristics among them.
ResultsA total of 624 students from two medical colleges in Kerbala province, Iraq, were included: 298 males (47.8%) and 326 females (52.2%). Overall, 47.5% of students reported headaches starting after an accident, illness, or infection, suggesting potential external triggers (26% males, 39.5% females). The majority of headaches were subacute (44.2%), lasting 4–8 weeks, while 42.6% were acute (<4 weeks). Chronic headaches (>3 months) were less common (13.2%). The most common precipitating factor was stress and anxiety (55.9%), followed by fatigue (55.1%) and loud noises (47.4%). No significant relationship was found between headache and foods or medications. Headache was most frequently described as tightness (49%) or throbbing (30.9%). Notably, neuroimaging was performed in 37.1% of patients without clear indications. Several headache characteristics were significantly associated with all stages of study, while others were significantly associated with gender.
ConclusionHeadache is very common among medical students, with a prevalence exceeding 50%. Most headaches fall into the subacute category and do not require neuroimaging or extensive investigations. The most striking findings were stress, anxiety, and fatigue as precipitating factors. Furthermore, certain headache characteristics are significantly associated with the level of stress across all study stages. Females were more susceptible to headache, with significant associations between many headache characteristics and gender across different stages of study. We recommend providing mentor educators for all students and establishing a center to address mental, social, and medical issues for all students in medical colleges, given the high burden of stress and long study hours that accompany this burden.
1 Introduction#
Headache is a subjective sensation of pain or discomfort of the head or face, often triggered by stress, dehydration, sleep deprivation, or underlying medical conditions[1]. Headache disorders are among the most prevalent neurological conditions; 50% of adults experience at least one headache per year, with higher occurrence in women[1]. Primary headaches (migraine, tension-type headache, cluster headache) account for nearly 98% of cases, while secondary headaches may indicate serious pathology[1]. The International Classification of Headache Disorders, 3rd edition (ICHD-3) provides standardized diagnostic criteria[2]. Key red flags for secondary headache are summarized by the mnemonic SNOOPP (Systemic symptoms, Neurologic deficits, Sudden onset, older age, Progressive course, Positional change/ Precipitators/Papilledema)[3–5]. Management includes trigger avoidance, acute analgesia (paracetamol, NSAIDs), and prophylaxis for frequent attacks (≥2/month) with beta-blockers, amitriptyline, or topiramate[1].
Headache is a common complaint among medical students due to physical and psychological stressors[6]. This study aims to assess the prevalence of headache among male and female medical students.
1.1 Aim of the study#
Headache is among the commonest complaints in medical students it could be due to many physical or psychological stressors The aim of this study is to assess the prevalence of headache among male and female medical students.
2 Methodology#
2.1 Study design and setting#
A cross-sectional study was conducted from October 2023 to February 2025 among undergraduate medical students at two colleges in Kerbala province, Iraq: University of Al-Ameed Faculty of Medicine (minimum 50 students per stage, years 2–6) and University of Kerbala Faculty of Medicine (minimum 20 students per stage, years 1–6), representing diverse socioeconomic backgrounds. The cross-sectional design is appropriate for assessing the prevalence of conditions such as headache in a defined population at a single time point[7,8].
2.2 Sampling#
A stratified random sampling technique was employed using academic year as the stratum. Stratified random sampling ensures representation from each subgroup (academic year) and improves the precision of prevalence estimates compared to simple random sampling[9,10]. The total sample size was proportionally allocated to each year (first to sixth), followed by simple random sampling using random number generator software. The response rate was 100%.
2.3 Stress classification#
Medical stages were categorized by stress level: mild (years 1–2), moderate (years 3–4), and severe (years 5–6). Previous studies have demonstrated that psychological stress levels vary significantly across different phases of medical education, with earlier and later years often showing higher distress[11, 12].
2.4 Statistical analysis#
Data were entered into a spreadsheet and analyzed using SPSS version 28.0 (IBM, Chicago, Illinois, USA)[13,14] and Real Statistics Resource Pack for Excel 2016. Descriptive statistics were presented as n (%) for categorical variables and mean ± standard deviation (SD) for continuous variables[15]. Normality was assessed using the Shapiro-Wilk test[16]. Homogeneity of variances was assessed by Levene's test (p < 0.05). Fisher's LSD method was used for confidence intervals. A p-value < 0.05 (two-sided) was considered statistically significant.
3 Results#
3.1 Demographic and clinical characteristics#
This study investigated the characteristics of headaches among medical students. Nearly half (47.5%) of students reported headaches starting after a participating factor (smoking, sleeping prevention, fatigue). Most headaches were described as episodic (72.6%) rather than constant (27.4%). Weekly headaches were the most frequent (45.0%), followed by monthly (31.8%) and daily (23.1%). And the rest of result shown in the table below. The perveance of headache is (53%)
Table 1 Characteristic of headache among medical students(N=624).
| Variable | G | Frequency | Percentage |
|---|---|---|---|
| Did the headaches start after participating factors (smoking, sleeping prevention, fatigue) | Yes | 296 | 47.5 |
| No | 328 | 52.6 | |
| The headaches | Are constant | 171 | 27.4 |
| Come and go | 453 | 72.6 | |
| How often do the headaches occur? | Daily | 144 | 23.1 |
| Weekly | 281 | 45.0 | |
| Monthly | 199 | 31.8 | |
| How many hours do the headaches last? | 1-6 | 373 | 59.8 |
| 6-12 | 170 | 27.2 | |
| 12-24 | 65 | 10.4 | |
| 12-48 | 11 | 1.8 | |
| 48-72 | 3 | .5 | |
| More than 72 | 2 | .3 | |
| Do the headaches occur at a certain time of day? | Morning | 155 | 24.8 |
| Afternoon | 294 | 47.1 | |
| Night | 175 | 28.1 | |
| Are the headaches becoming: | Stronger | 156 | 25.0 |
| Lasting longer | 151 | 24.2 | |
| Occurring more frequently | 140 | 22.4 | |
| None | 177 | 28.4 | |
| Do the headaches ever wake the patient up when they are asleep? | Yes | 189 | 30.3 |
| No | 435 | 69.8 | |
| Does rest or sleep relieve the headache? | Yes | 397 | 63.6 |
| No | 227 | 36.4 | |
| Do the headaches stop the patient from doing regular daily activities? | Yes | 299 | 47.9 |
| No | 325 | 52.1 | |
| Has the patient ever missed work/school because of a headache? | Yes | 247 | 39.6 |
| No | 377 | 60.4 |
Table (2) demonstrated that the most concerning finding is that anxiety or stress was the overwhelming leader, with over (55.9%) of students followed by fatigue (55.1%) and loud noises (47.4%) the rest of result shown in the table below.
Table 2 Frequency of the most common participating factors of headache among medical students(N=624).
| Variable | Frequency | Percentage |
|---|---|---|
| Anxiety or stress | 349 | 55.9 |
| Fatigue | 344 | 55.1 |
| Loud Noises | 296 | 47.4 |
| School | 278 | 44.6 |
| Family problems | 262 | 42.0 |
| Hunger (missing meals | 253 | 40.5 |
| Too little sleep (staying up late) | 241 | 38.6 |
| Too much sleep (sleeping in) | 224 | 35.9 |
| Bright lights | 209 | 33.5 |
| Sunshine | 206 | 33.0 |
| Odors (Perfume, cigarettes) No. | 201 | 32.2 |
| Hot weather | 200 | 32.1 |
| Ice cream | 186 | 29.8 |
| Menstrual cycle | 183 | 29.3 |
| Riding in a car | 166 | 26.6 |
| Exercise or playing | 157 | 25.2 |
| Birth control pills | 135 | 21.6 |
| Alcohol | 96 | 15.4 |
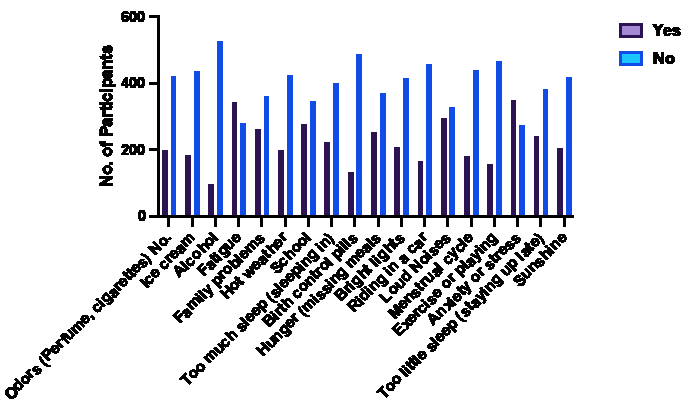
Table (3) shows the frequency of various factors that may contribute to headaches among medical students.
Table 3 Association of medications, foods and headache frequency(N=624).
| Variable | Groups | Frequency | Percentage | Pvalue |
|---|---|---|---|---|
| Medication | Yes | 131 | 21 | |
| No | 493 | 79.0 | ||
| Certain foods | Yes | 90 | 14.4 | |
| No | 534 | 85.6 |
Table (4) illustrated the frequency of various warning signs reported by medical students before experiencing headache, it was reported that Tiredness, sleepiness, or yawning were the most common warning sign (50.5%). (43.4%) of students reported experiencing dizziness before headaches. Eye problems, Over (42.5%) of the students reported eye problems as a warning sign. Other warning signs like paleness, mood swings, increased appetite, and cravings were reported by less than half of the students and the rest of result shown in the table below.
Table 4 Frequency of the warning signs BEFORE the headache begins among medical students(N=624).
| Variable | Frequency | Percentage |
|---|---|---|
| Tired, sleepy or yawning | 315 | 50.5 |
| Dizziness | 271 | 43.4 |
| Eye problems | 265 | 42.5 |
| Mood swings (either high or low) | 247 | 39.6 |
| Irritability | 210 | 33.7 |
| Rings around the eyes | 182 | 29.2 |
| Craving sweets | 147 | 23.6 |
| Increased appetite | 144 | 23.1 |
| Paleness | 140 | 22.4 |
| Hyperactivity | 136 | 21.8 |
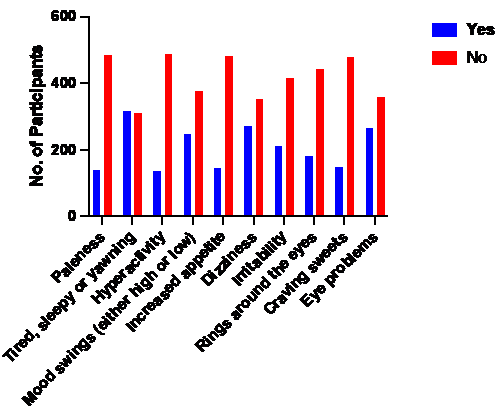
Table (5) below shows the frequency of headaches in various locations among medical students. Forehead headaches are the most common (43.9%) followed by all around the head (38%) and left-sided headaches (28.5%) . Neck, right-sided, top of head, temple, and back of head headaches are all less frequent and the rest of result shown in the table below.
Table 5 Frequency of the headache locations among medical students(N=264).
| Variable | Frequency | Percentage |
|---|---|---|
| Forehead | 274 | 43.9 |
| All around the head | 237 | 38.0 |
| Left side | 178 | 28.5 |
| Back of the head | 170 | 27.2 |
| Neck | 160 | 25.6 |
| Right side | 143 | 22.9 |
| Top of the head | 143 | 22.9 |
| Temples | 141 | 22.6 |
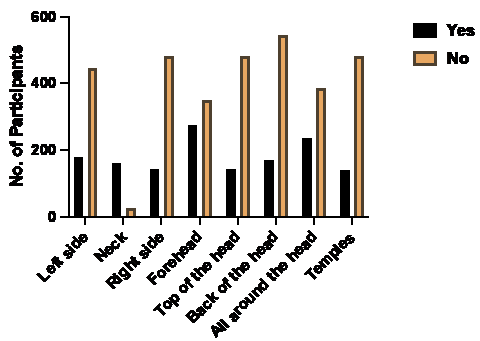
Table (6) shows the frequency of different types of feelings reported by medical students. Results demonstrated that various sensations experience, including pressure, sharpness, tightness, throbbing/pounding, aching, and dullness. Tightness (like a rubber band wrapped around the head) was the most common feeling (49%). Throbbing pain, a hallmark of migraine headaches, were also common (30.93%). aching pain and dull pain were all less frequent. The rest of result shown in the table below.
Table 6 characteristic of headache among medical students(N=624).
| Variable | Frequency | Percentage |
|---|---|---|
| Ice back pain | 160 | 25.6% |
| Throbbing/pounding (like a hammer) | 193 | 30.9% |
| Tightness (like a rubber band wrapped around the head) | 306 | 49% |
| Dull | 148 | 23.7% |
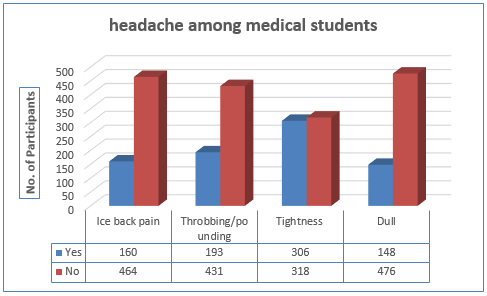
Table (7) Presented the frequency of various symptoms experienced by medical students during headaches. Nausea is the most common symptom (39.7%), followed by confusion (33%). Vomiting was less frequent than others (26.1%). The rest of result shown in the table below.
Table 7 Frequency of the symptoms when the patient has a headache among medical students(N=624).
| Variable | Frequency | Percentage |
|---|---|---|
| Nausea | 248 | 39.7 |
| Dizziness and light headedness | 206 | 33.0 |
| Fatigue in the arms or legs | 164 | 26.3 |
| Vomiting | 163 | 26.1 |
| Stomach pains | 142 | 22.8 |
| Numbness to the arms and face | 118 | 18.9 |
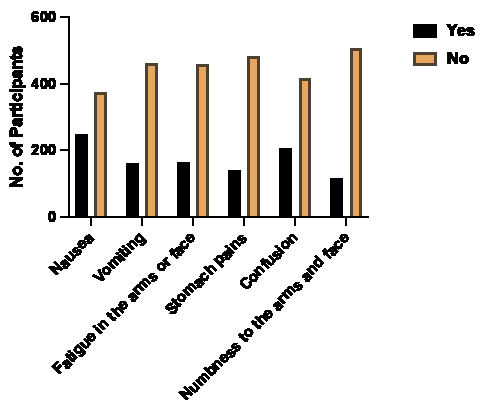
Table (8) shown the frequency of various tests performed during headache treatment among medical students. Blood tests (44.23%) were the most commonly performed test, followed by eye exams (35.89%), followed by dental exam (20.8%) the rest was less common and as it shown in the table below.
Table 8 Frequency of the test performed during that headache treatment period among medical students(N=624).
| Variable | Frequency | Percentage |
|---|---|---|
| Blood tests | 276 | 44.2 |
| Eye exam | 225 | 36.1 |
| Dental exam | 130 | 20.8 |
| Sinus X-rays | 130 | 20.8 |
| Allergy tests | 121 | 19.4 |
| CT Scan | 117 | 18.8 |
| MRI | 114 | 18.3 |
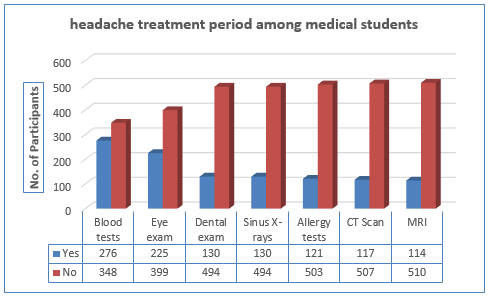
Table (9) shown the Association between characteristic of headache and medical stage and show that the frequency of headache was common weekly in moderate stress stages (18%) followed by severe stress stages (17.7%) and mild stress stages were less common. The duration most common between 1-6 hours in severe stress stages (26.6%) followed by moderate stages (21.96%) and less common in mild stress stages. The rest of the result shown in the table below.
Table 9 Association between characteristic of headache and medical stage (N=624).
| Variables Groups | Stress stages | P value | |||
|---|---|---|---|---|---|
| Mild | Moderate | Severe | |||
| University | University of Al-Ameed | 100 | 200 | 150 | 0.001[S] |
| 21 | 53 | 100 | |||
| The headaches | constant | 44 | 75 | 50 | 0.003[S] |
| episodic | 77 | 178 | 200 | ||
| Frequency of the headache | Daily | 44 | 52 | 48 | 0.001[S] |
| Weekly | 51 | 116 | 114 | ||
| Monthly | 26 | 85 | 88 | ||
| How many hours do the headaches attack last? | 1-6 | 61 | 141 | 171 | <0.001[S] |
| 6-12 | 37 | 82 | 51 | ||
| 12-24 | 22 | 21 | 22 | ||
| 12-48 | 1 | 7 | 3 | ||
| 48-72 | 0 | 1 | 2 | ||
| More than 72 | 0 | 1 | 1 | ||
| Stronger | 48 | 52 | 56 | ||
| The headache pattern | Lasting longer | 44 | 62 | 45 | 0.04[S] |
| Occurring more frequently | 14 | 59 | 67 | ||
| None | 15 | 80 | 82 | ||
| headaches ever wake the patient up when asleep? | Yes | 50 | 86 | 53 | 0.001[S] |
| No | 71 | 167 | 197 | ||
| Does rest or sleep relieve the headache | Yes | 69 | 139 | 189 | 0.003[S] |
| No | 52 | 114 | 61 | ||
| Headaches stop the patient from doing regular daily activities | Yes | 61 | 112 | 126 | 0.002[S] |
| No | 60 | 141 | 124 | ||
| Patient ever missed work because of a headache | Yes | 59 | 102 | 86 | 0.021[S] |
| No | 62 | 151 | 164 | ||
| Starts out small & builds up | 67 | 154 | 161 | ||
| Chi-Square Results are presented as N(%), p<0.05 considered significantly different, [S]= Significant, [NS]= Non-significant | |||||
Table (10) shown Association between characteristic of headache and Sex. It shows that the headache was most common in male who experienced headaches without participating factors (28.19%) and more frequent in females that triggered by participating factors (27.7%).The headaches tend to be more subacute (24.29%) than acute (22.1%) in females while it was acute (19.3%) than subacute (18.69%) in males. The rest of the result shown in the table below.
Table 10 Association between characteristic of headache and Sex(N=624).
| Variables Groups | Sex | P value | ||
|---|---|---|---|---|
| Male | Female | |||
| University | University of Al-Ameed | 224 | 226 | 0.432 [NS] |
| University of Kerbala | 74 | 100 | ||
| Did the headaches start after participating factors (smoking, sleeping prevention, fatigue) | Yes | 117 | 178 | 0.002 [S] |
| No | 181 | 148 | ||
| How long has the patient had these headaches | Acute | 124 | 142 | 0.004 [S] |
| Sub-Acute | 120 | 156 | ||
| Chronic | 54 | 28 | ||
| The headaches | constant | 55 | 114 | 0.021 [S] |
| Come & go | 243 | 212 | ||
| How often do the headaches occur | Daily | 53 | 91 | 0.001 [S] |
| Weekly | 139 | 142 | ||
| Monthly | 106 | 93 | ||
| How many hours do the headaches last? | 1-6 | 197 | 176 | <0.001 [S] |
| 6-12 | 60 | 110 | ||
| 12-24 | 35 | 30 | ||
| 12-48 | 2 | 9 | ||
| 48-72 | 2 | 1 | ||
| More than 72 | 2 | 0 | ||
| Do the headaches occur at a certain time of day | day | 62 | 93 | <0.001 [S] |
| Morning | 134 | 160 | ||
| Afternoon | 80 | 62 | ||
| Night | 22 | 11 | ||
| Are the headaches becoming | Stronger | 67 | 89 | <0.001 [S] |
| Lasting longer | 55 | 96 | ||
| Occurring more frequently | 83 | 57 | ||
| None | 93 | 84 | ||
| Do the headaches ever wake the patient up when they are asleep? | Yes | 75 | 114 | 0.003 [S] |
| No | 223 | 212 | ||
| Does rest or sleep relieve the headache | Yes | 200 | 197 | 0.543 [NS] |
| No | 98 | 129 | ||
| Do the headaches stop the patient from doing regular daily activities | Yes | 147 | 152 | 0.054 [NS] |
| No | 151 | 174 | ||
| Has the patient ever missed work/school because of a headache | Yes | 116 | 131 | 0.322 [NS] |
| No | 182 | 195 | ||
| Is the headache pain | Intense when it starts | 112 | 124 | 0.521 [NS] |
| Starts out small and builds up | 186 | 202 | ||
| Chi-Square Results are presented as N(%), p<0.05 considered significantly different, [S]= Significant, [NS]= Non significant | ||||
Table (11) shown Association between characteristic of headache between medical stage and sex it shows that the duration of headache mostly acute in moderate stress stages in males (18.79%) and was mostly subacute in moderate stress stages in female (22.08%) and the rest of result shown in the table below.
Table 11 Association between characteristic of headache between medical stage and sex (N=624)
| Variable | Groups | Male N=298 | P value | Female N=326 | P value | ||||
|---|---|---|---|---|---|---|---|---|---|
| Mild stress | Moderate stress | Severe stress | Mild stress | Moderate stress | Severe stress | ||||
| How long has the patient had these headaches | Acute | 14 | 56 | 54 | 0.001 [S] | 0.002 [S] | |||
| 29 | 55 | 58 | 0.002 | ||||||
| Sub Acute | 25 | 40 | 55 | 29 | 72 | 55 | |||
| Chronic | 18 | 20 | 16 | 6 | 10 | 12 | |||
| How many hours do the headaches last? | 1-6 | 29 | 88 | 80 | 0.067 [NS] | 0.05 [S] | |||
| 41 | 55 | 80 | 0.05 | ||||||
| 6-12 | 20 | 18 | 22 | 20 | 45 | 45 | |||
| 12-24 | 5 | 21 | 9 | 6 | 13 | 11 | |||
| 12-48 | 0 | 2 | 0 | 0 | 9 | ||||
| 48-72 | 0 | 0 | 2 | 0 | 1 | 0 | |||
| More than 72 | 0 | 1 | 1 | 0 | 0 | 0 | |||
| Dose the headache awakes the patient from sleep | Yes | 23 | 22 | 30 | 0.001 [S] | 32 | 34 | 48 | 0.002 [S] |
| No | 38 | 89 | 96 | 28 | 108 | 76 | |||
| Does rest or sleep relieve the headache | Yes | 32 | 76 | 92 | 0.001 [S] | 32 | 90 | 75 | 0.003 [S] |
| No | 20 | 38 | 40 | 37 | 49 | 43 | |||
4 Discussion#
The present study demonstrates that headache is a highly prevalent condition among medical students, with an overall prevalence of 53%. This finding is consistent with previous studies reporting prevalence rates ranging from approximately 50% to over 70% among medical students, reflecting the significant burden of headache disorders in this population[17,18]. For instance, a study conducted among medical students reported a headache prevalence of 68%, highlighting the widespread nature of this condition[19].
A considerable proportion of participants (47.5%) reported that their headaches were triggered by identifiable factors such as smoking, sleep deprivation, and fatigue. These findings are in agreement with previous research indicating that lifestyle-related factors, particularly poor sleep hygiene and stress, play a major role in headache occurrence[20,21]. Moreover, the predominance of episodic headaches (72.6%) suggests that most cases are likely primary headaches, particularly tension-type headaches (TTH) and migraines, which are the most common subtypes reported in similar populations[22,23].
Regarding headache frequency, weekly episodes (45%) were the most commonly reported pattern. Comparable findings have been reported in earlier studies, where recurrent headaches were attributed to ongoing academic stress and irregular daily routines among medical students[24, 25]. The majority of headaches in this study lasted 1–6 hours (59.8%), which is consistent with the typical duration of primary headaches, particularly migraines and TTH, as defined by international classification criteria[26].
The temporal distribution showed that headaches occurred most frequently in the afternoon (47.1%), likely reflecting cumulative fatigue and prolonged cognitive effort throughout the day. This observation is supported by evidence linking prolonged mental activity and inadequate rest to increased headache risk[27,28]. Furthermore, the fact that 63.6% of participants reported relief with rest or sleep reinforces the role of fatigue and sleep disturbances in headache pathogenesis[29].
The functional burden of headaches was considerable, with 47.9% of students reporting interference with daily activities and 39.6% missing academic activities. These findings are consistent with previous studies demonstrating that headaches significantly impair academic performance and quality of life, with many students reporting reduced productivity and absenteeism[30,31].
Among the triggering factors, stress and anxiety (55.9%) were the most prominent, followed by fatigue and environmental stimuli such as loud noise. This aligns with a large body of literature identifying stress as a key precipitating factor for both migraine and tension-type headaches in student populations[32,33]. Academic-related stressors, particularly examinations, have been shown to significantly increase headache frequency and severity[34].
Prodromal symptoms were commonly reported, with tiredness, sleepiness, or yawning (50.5%) being the most frequent. Such symptoms are well-documented in migraine patients and are considered early indicators of impending headache attacks[35,36]. Additional symptoms such as dizziness and visual disturbances further support the presence of migraine features among a substantial proportion of participants.
In terms of headache characteristics, the forehead (43.9%) was the most common location, while tightness (49%) was the most frequently described sensation, consistent with tension-type headaches. However, the presence of throbbing pain (30.9%) and associated symptoms such as nausea (39.7%) suggests a significant overlap with migraine-type headaches. Previous studies have similarly reported coexistence of tension-type and migraine headaches among medical students[37,38].
Regarding diagnostic evaluation, blood tests (44.2%) and eye examinations (36.1%) were the most commonly performed investigations, while advanced imaging modalities such as CT and MRI were less frequently utilized. This is consistent with clinical practice, where imaging is generally reserved for cases with suspected secondary causes rather than routine evaluation of primary headaches[39,40].
Statistically significant associations were observed between headache characteristics and stress levels, with increased stress correlating with higher frequency and longer duration of headaches. This finding is supported by previous studies demonstrating a strong relationship between psychological stress and headache severity in students[41,42]. Additionally, gender differences were observed, with females more likely to experience headaches triggered by external factors and of longer duration. This is consistent with prior research showing a higher prevalence of migraine among females, potentially due to hormonal and psychosocial influences[43,44].
In conclusion, the findings of this study indicate that headaches among medical students are highly prevalent and multifactorial, with significant contributions from stress, lifestyle factors, and environmental triggers. The substantial impact on academic performance and daily functioning highlights the need for targeted interventions, including stress management programs, improved sleep hygiene, and increased awareness of headache triggers. Future studies should focus on longitudinal designs and intervention-based strategies to reduce the burden of headaches in this vulnerable population[45,46].
5 Conclusion#
Headache is highly prevalent among medical students, affecting over half of the study population. Most headaches were episodic, commonly occurring on a weekly basis, and typically lasted 1–6 hours. Stress, fatigue, and sleep disturbances were the main contributing factors, with stress being the most significant trigger.
The clinical profile suggests a predominance of tension-type headaches, although migraine features were also observed. Headaches had a notable impact on daily activities and academic performance. Significant associations with stress levels and gender differences highlight the multifactorial nature of headache in this population.
5.1 Recommendations#
Implementation of stress management programs and promotion of healthy sleep habits are strongly recommended. Universities should encourage lifestyle modifications, including regular physical activity and balanced nutrition, while improving access to medical care for early diagnosis and management.
Additionally, optimizing academic workload and increasing awareness about headache triggers and self-management strategies may help reduce the burden. Further longitudinal and interventional studies are recommended to better understand and address this issue.
Declarations
€Funding
✎Author contributions
◎Competing interests
♥Acknowledgements
Article information
- Published
Copyright © 2026 Dr. Lamya A Darwish. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 46#
- 1
Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38(1):1–211.
- 2
Stovner LJ, Hagen K, Jensen R, Katsarava Z, Lipton R, Scher A, et al. The global burden of headache: a documentation of headache prevalence and disability worldwide. Cephalalgia. 2007;27(3):193–210.
- 3
Dodick DW. Clinical review: Thunderclap headache. BMJ. 2014;348:g2900.
- 4
Do TP, Remmers A, Schytz HW, Schankin C, Nelson SE, Obermann M, et al. Red and orange flags for secondary headaches in clinical practice: SNNOOP10 list. Neurology. 2019;92(3):134–44.
- 5
Godwin SA, Cherkas DS, Panagos PD. Headache in the emergency department. Emerg Med Clin North Am. 2021;39(1):1–18.
- 6
Al-Hashel JY, Ahmed SF, Alroughani R. Prevalence and burden of primary headache disorders in Kuwaiti children and adolescents: a school-based study. Front Neurol. 2020; 11:553.
- 7
Setia MS. Methodology series module 3: Cross-sectional studies. Indian J Dermatol. 2016;61(3):261-4.
- 8
Levin KA. Study design III: Cross-sectional studies. Evid Based Dent. 2006;7(1):24-5.
- 9
Samaranayaka A, Turner RM, Cameron C. Health related surveys: Sampling weights. N Z Med Stud J. 2025;(38):39-41.
- 10
Elfil M, Negida A. Sampling methods in clinical research: An educational review. Emerg (Tehran). 2017;5(1):e52.
- 11
Makki NM, Alharbi AK, Aloufi AA, et al. Depression, anxiety, and stress among different phases of medical students in Taibah University: a comparative study. Int J Med Dev Ctries. 2022;6(1):71-9.
- 12
Abdulghani HM, AlKanhal AA, Mahmoud ES, et al. Stress and its effects on medical students: a cross-sectional study at a college of medicine in Saudi Arabia. J Health Popul Nutr. 2011;29(5):516-22.
- 13
Shahrul AI, et al. A comparative evaluation of Statistical Product and Service Solutions (SPSS) and ChatGPT-4 in statistical analyses. Cureus. 2024;16(10):e72581.
- 14
George D, Mallery P. IBM SPSS Statistics 25 step by step: A simple guide and reference. 15th ed. New York: Routledge; 2018.
- 15
Mishra P, Pandey CM, Singh U, et al. Descriptive statistics and normality tests for statistical data. Ann Card Anaesth. 2019;22(1):67-72.
- 16
Ghasemi A, Zahediasl S. Normality tests for statistical analysis: a guide for non-statisticians. Int J Endocrinol Metab. 2012;10(2):486-9.
- 17
Stovner LJ, Hagen K, Jensen R, Katsarava Z, Lipton R, Scher A, et al. The global burden of headache: a documentation of headache prevalence and disability worldwide. Cephalalgia. 2007;27(3):193-210.
- 18
Okyay RA, Celen Y, Keten HS, Tasyurek E. Prevalence of headache and its associated factors among medical students. J Neurol Sci. 2016;33(2):273-82.
- 19
Al-Hashel JY, Ahmed SF, Alroughani R. Prevalence and burden of primary headache disorders in Kuwaiti children and adolescents: a school-based study. Front Neurol. 2020;11:553.
- 20
Rains JC, Poceta JS. Sleep and headache. Curr Treat Options Neurol. 2010;12(1):1-15.
- 21
Boardman HF, Thomas E, Millson DS, Croft PR. Psychological, sleep, lifestyle and demographic associations with headache in young adults. Cephalalgia. 2005;25(6):472-80.
- 22
Rasmussen BK, Jensen R, Schroll M, Olesen J. Epidemiology of headache in a general population: a prevalence study. J Clin Epidemiol. 1991;44(11):1147-57.
- 23
Schramm SH, Moebus S, Lehmann N, Galli U, Obermann M, Bock E, et al. The association between stress and headache: A longitudinal population-based study. Cephalalgia. 2015;35(10):853-63.
- 24
Ferrara M, Langiano E, Di Brango T, De Vito E, Di Cioccio L, Bauco C. Prevalence of stress, anxiety and depression in medical students. Ann Ig. 2021;33(4):361-72.
- 25
Fares J, Al Tabosh H, Saadeddin Z, El Mouhayyar C, Aridi H. Stress, burnout and coping strategies in medical students. BMC Med Educ. 2016;16(1):115.
- 26
Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38(1):1-211.
- 27
Houle TT, Butschek RA, Turner DP, Smitherman TA, Rains JC, Penzien DB. Stress and sleep duration predict headache severity in chronic headache sufferers. Pain. 2012;153(12):2432-40.
- 28
Kelman L. The triggers or precipitants of the acute migraine attack. Cephalalgia. 2007;27(5):394-402.
- 29
Spierings EL, Ranke AH, Honkoop PC. Precipitating and aggravating factors of migraine vs tension-type headache. Headache. 2001;41(6):554-8.
- 30
Jensen R, Stovner LJ. Epidemiology and comorbidity of headache. Lancet Neurol. 2008;7(4):354-61.
- 31
Leonardi M, Raggi A. A narrative review on the burden of migraine: when the burden is the impact on people's life. J Headache Pain. 2019;20(1):41.
- 32
Wacogne C, Lacoste JP, Guillibert E, Hugues FC, Le Jeunne C. Stress, anxiety, depression and migraine. Cephalalgia. 2003;23(6):451-5.
- 33
Nash JM, Thebarge RW. Understanding psychological stress, its biological processes, and impact on primary headache. Headache. 2006;46(9):1377-86.
- 34
Al-Hashel JY, Ahmed SF, Alroughani R. The impact of academic stress on headache prevalence and severity among medical students. J Headache Pain. 2018;19(1):78.
- 35
Giffin NJ, Ruggiero L, Lipton RB, Silberstein SD, Tvedskov JF, Olesen J, et al. Premonitory symptoms in migraine: an electronic diary study. Neurology. 2003;60(6):935-40.
- 36
Laurell K, Artto V, Bendtsen L, Hagen K, Häggström J, Linde M, et al. Premonitory symptoms in migraine: A cross-sectional study in 2714 persons. Cephalalgia. 2016;36(10):951-9.
- 37
Kaniecki RG. Migraine and tension-type headache: an assessment of challenges in diagnosis. Neurology. 2002;58(9 Suppl 6):S15-20.
- 38
Spierings EL, Donoghue S. Overlap between migraine and tension-type headache. Headache. 2006;46(8):1311-2.
- 39
Evans RW. Diagnostic testing for headache. Med Clin North Am. 2001;85(4):865-85.
- 40
Sandrini G, Friberg L, Coppola G, Jänig W, Jensen R, Tassorelli C, et al. Neurophysiological tests and neuroimaging procedures in non-acute headache: guidelines and recommendations. Eur J Neurol. 2004;11(4):217-24.
- 41
Borsook D, Maleki N, Becerra L, McEwen B. Understanding migraine through the lens of maladaptive stress responses: a model disease of allostatic load. Neuron. 2012;73(2):219-34.
- 42
Sauro KM, Becker WJ. The stress and migraine interaction. Headache. 2009;49(9):1378-86.
- 43
Vetvik KG, MacGregor EA. Sex differences in the epidemiology, clinical features, and pathophysiology of migraine. Lancet Neurol. 2017;16(1):76-87.
- 44
Steiner TJ, Stovner LJ, Jensen R, Uluduz D, Katsarava Z. Migraine remains second among the world's causes of disability, and first among young women: findings from GBD2019. J Headache Pain. 2020;21(1):137.
- 45
Smitherman TA, Burch R, Sheikh H, Loder E. The prevalence, impact, and treatment of migraine and severe headache in the United States: a review of statistics from national surveillance studies. Headache. 2013;53(3):427-36.
- 46
Probyn K, Bowers H, Mistry D, Caldwell F, Underwood M, Patel S, et al. Non-pharmacological self-management for people living with migraine: a systematic review. J Headache Pain. 2017;18(1)