Mast Cell Density In The Heart Of Eosinophilic Coronary Periarteritis (ECPA): A Histochemical Study
Hiroki Kajihara1 ✉
Hiroki KajiharaCorresponding author- 1 Emeritus Professor of Hiroshima Univ, Hiroshima, Japan
Kazuhiro Sentani2
Kazuhiro Sentani- 2 Department of Molecular Pathology, Graduate School of Biomedical and Health Sciences, Hiroshima University
Show affiliations (2)
- 1Emeritus Professor of Hiroshima Univ, Hiroshima, Japan
- 2Department of Molecular Pathology, Graduate School of Biomedical and Health Sciences, Hiroshima University
Published
Abstract
The mast cell counts in the adventitia of large subepicardial coronary arteries and in the myocardium of both the right and left ventricles were determined in a patient (age 40 years, male) with eosinophilic coronary periarteritis (ECPA) and a patient (age 66 years, male) without cardiac inflammation. A large number of mast cells (96.0/mm 2 ) were found with numerous eosinophils in the adventitia of the inflamed subepicardial coronary artery of patients with ECPA. On the other hand, in a patient (age 66 years, male) without coronary inflammation, the average mast cell count was normal (7.0±0.8 mast cell /mm 2 ). The mast cell counts of the right and left myocardia of patients with ECPA were 13.6±4.2 mast cell / mm 2 and 13.8±2.0 mast cell /mm 2 , respectively, and those of patients without coronary inflammation were 10.2±1.6 mast cell /mm 2 and 8.2±1.7 mast cell /mm 2 , respectively. The mast cell counts in the myocardium of patients with ECPA was slightly greater than that in patients without coronary inflammation. These differences in numbers of mast cells between patients with ECPA and patients without inflammation were considered to be influenced by coronary artery inflammation. The mast cell counts in the coronary adventitia of patients with ECPA was approximately 14 times greater than that in patients without coronary artery infection. These findings indicate that the adventitial resident mast cells of the coronary arteries in patients with ECPA might transform into a new phenotype with the ability to recruit eosinophils from the blood. Coronary spasm in patients with ECPA could be induced by mediators released from transformed mast cells and recruited eosinophils. However, the precise mechanism of mast cell transformation remains to be elucidated.
1 Introduction#
Eosinophilic coronary periarteritis (ECPA) is a rare disease leading to vasospastic angina (i.e., Prinzmetal’s variant angina[1]) and sudden cardiac death (SCD)[2,3]. The characteristic clinical findings of this disease include: a) vasospastic angina normally occurring within 30 minutes, usually from the evening to the early morning; b) anginal attack usually occurring with circadian or circannual rhythm; c) electrocardiogram (ECG) findings showing ST segment elevation during an anginal attack; d) almost all patients experience SCD early in the morning; e) allergies or a history of allergies are difficult to identify in patients with this disease.
At autopsy, macroscopic findings of the heart include a) subepicardial large coronary arteries that are grayish-white in color, b) left ventricular hypertrophy, and c) small scar formation scattered in the left ventricular wall.
The histological findings include a) infiltration of numerous eosinophils with other inflammatory cells in the adventitia of large coronary arteries in the subepicardial artery; b) all 3 main coronary artery branches are affected, with the left anterior descending artery most frequently affected; c) the medial smooth muscle cells and both the internal and external elastic laminae of the affected coronary artery are well preserved; and d) fibrinoid necrosis or granulomas, as observed in poly arteritis nodosa (PN) or allergic granulomatous angiitis (AGA), are not identified.
On the other hand, in 1982, Robinowitz et al.[4] reported 8 autopsy cases of spontaneous coronary artery dissection (SCAD) and summarized the characteristic findings of these 8 cases with a review of 46 cases in the literature. Two years later, Virmani et al.[5] added 3 more autopsy cases to the 8 cases reported by Robinowitz et al.[4]. The 11 autopsy cases of SCAD reported by Virmani et al. were all female and ranged in age from 26 to 47 years. Three of them presented in the postpartum period, and 9 died suddenly. The most common artery of dissection was the left coronary anterior descending artery (LAD). In the 11 patients, the dissection usually occurred in the outer third of the media. The characteristic histological finding was infiltration of the most prominent eosinophils limited to the adventitia of the dissected portion of the coronary arteries. This adventitial eosinophilic inflammation of the epicardial coronary arteries in SCAD patients is considered to be the same finding as that in ECPA patients.
In 2015, Mandal et al.[6] reported two autopsy cases of SCAD that histologically presented a dense band of inflammatory cells, including copious eosinophils within the adventitial and periadventitial tissues of the dissected coronary arteries, similar to the findings of the ECPA. They proposed the “mast cell hypothesis” on the etiology and pathogenesis of ECPA.
It is now generally accepted that mast cells have a functionally intimate relationship with eosinophils and that they cross-talk with each other in allergic reactions[7–12].
We investigated the distribution or density of mast cells in the heart of a patient with ECPA and, as a control, a patient (age, 66 years, male) without coronary inflammation. The mast cells in the adventitia of the subepicardial right and left coronary arteries and in the right and left ventricular myocardium were measured via immunohistochemistry for tryptase, which is known as a mediator contained in the secretory granules of mast cells.
2 Materials and Methods#
The materials used in this study were the right coronary artery of the heart obtained from an autopsy case reported as a typical case of ECPA (the 1st case of EPCA reported in 1989), and the left coronary artery of the heart obtained from a 66-year-old man who died of mesothelioma without cardiac problems.
The tissues obtained from both patients were embedded in paraffin, and the paraffin sections were used for immunohistochemical staining of tryptase. Positive and negative controls were utilized. The antibody source was tryptase (mouse monoclonal, Cell Marque, Rocklin, CA).
3 Results#
The mast cell counts in the hearts of patients with ECPA and patients without cardiac problems were measured in the adventitia of the subepicardial large coronary arteries and in both ventricular myocardia.
A.Mast cell count in the heart of a patient (40-year-old, male) with eosinophilic coronary periarteritis (ECPA)
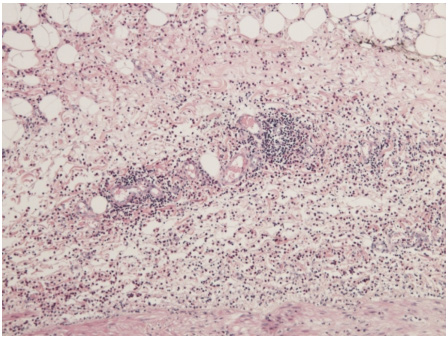
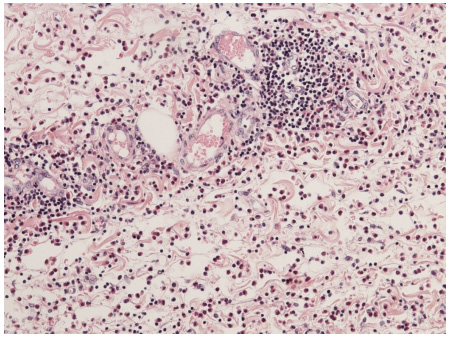
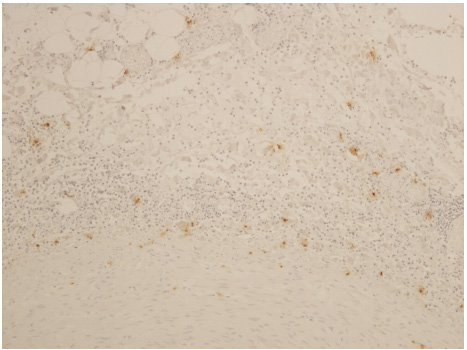
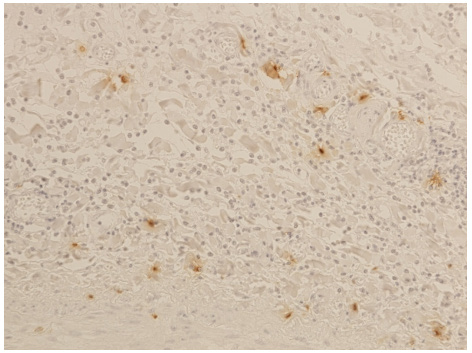
1)Mast cell count in the adventitia of the inflamed subepicardial right coronary artery: 96.0±27.2 mast cell /mm2 (range 68 to 132 mast cell /mm2 =96,0±27,2 mast cell /mm2 )
3.1 (Fig 1-a, -b HE and Fig 1-c, -d Tryptase)#
A. 1) H-E and tryptase stain of the coronary artery and ventricular myocardium in a patient (age 40 years, male) with ECPA
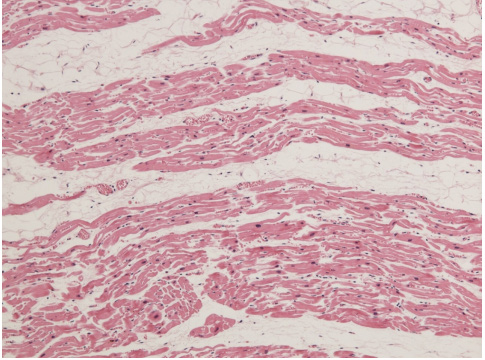
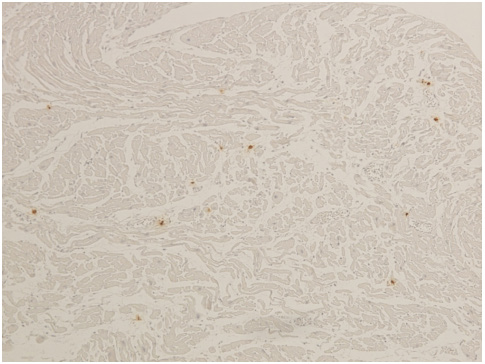
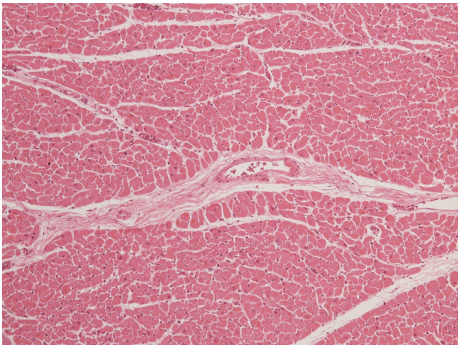
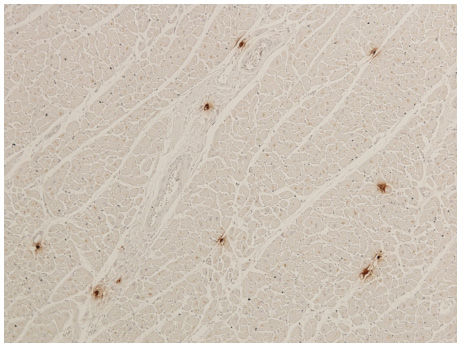
2) HE and Mast cell count in the right ventricular myocardium: 13,6±4.2 mast cell/mm2 (range 8 to 20 mast cell /mm2 = 13.6±4.2 mast cell/ mm2 ), (Fig 2-a HE, -b Tryptase)
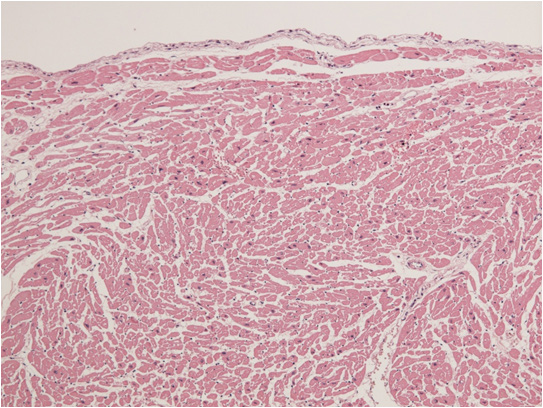
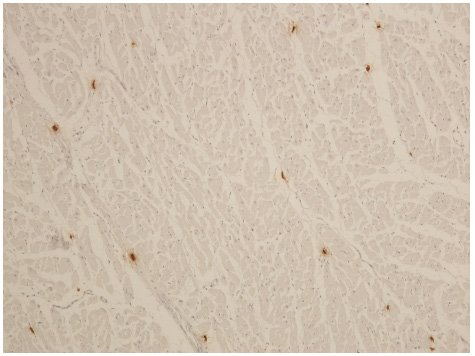
3) HE and Mast cell count in the left ventricular myocardium: 13.8±2.0 mast cell /mm2 (range 11 to 17 mast cell /mm2 = 13.8±2.0 mast cell /mm2 ), (Fig 3-a HE, -b Tryptase)
B. H-E and Mast cell count in the heart of a patient (66-year-old, male) without cardiac problems
1)Mast cell count in the adventitia of the subepicardial left coronary Artery: 7.0±0.8 mast cell /mm2 (range 6 to 8/mm2 = 7.0±0.8 mast cell /mm2 ) (Fig 4-a HE, -b Tryptase)
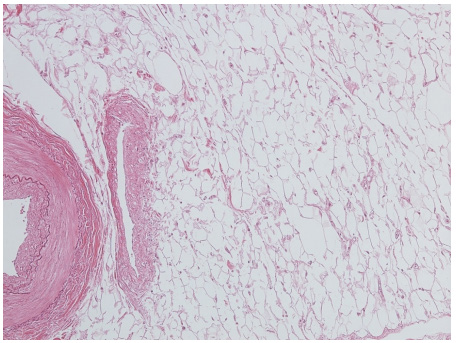
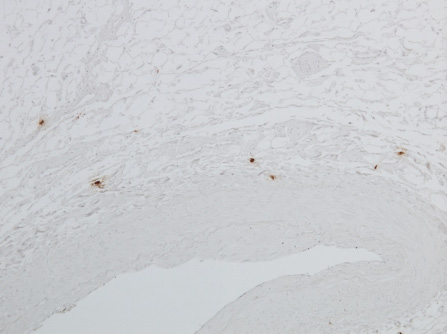
(0.10 mm2 ). Small number of tryptase positive cells are seen in the peri-arterial and adventitial tissue.
2) Mast cell count in the right ventricular myocardium: 10.2±1.6 mast cell /mm2 (range 8 to 12 mast cell /mm2 = 10.2±1.6 mast cell /mm2 ) (Fig 5-a HE, -b Tryptase).
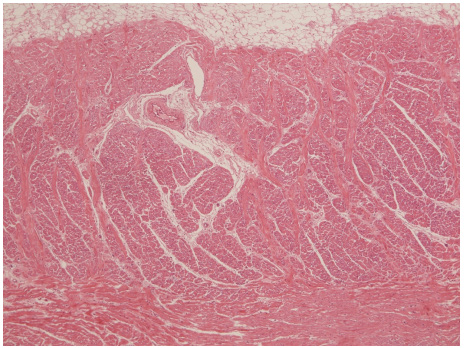
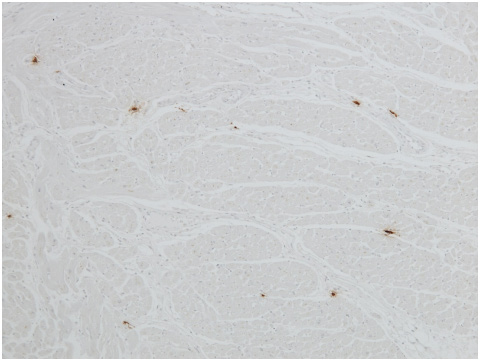
3) Mast cell count in the left ventricular myocardium: 8.2±1.7/mm2 (range 5 to 10 mast cell /mm2 = 8.2±1.7 mast cell /mm2 )
3.2 (Fig 6-a HE, -b Tryptase)#
As shown in Fig. 1-a and 1-b, a large number of eosinophils infiltrated with many lymphocytes and other leukocytes in the adventitia of the right subepicardial large coronary artery of patients with ECPA. The mast cells were identified via immunohistochemical staining of tryptase and are shown in Fig. 1-c and -d. The mast cell count in the adventitia of the inflamed coronary artery was markedly greater (96.0±27.2 mast cell /mm2 ) than that in the noninflamed coronary adventitia (7.0/±0.8 mast cell/mm2 ) (Fig. 4-b) of patients without coronary inflammation.
The right and left ventricular myocardia of patients with ECPA and patients without coronary infection were free from inflammatory cell infiltration (Figs 2a, 3a, 5a and 6a). The mast cell counts of both ventricles in patients with ECPA and without inflammation were not high, while a few mast cells were usually situated in perivascular connective tissue and between myocardial cells. In patients with ECPA, the mast cell count in the myocardia was slightly greater than that in patients without inflammation.
4 Discussion#
Mast cells are important cells of the immune system and arise from bone marrow-derived pluripotent progenitor cells that circulate in the blood and finally reside in connective tissues or mucosal tissues[9–12]. The mast cell phenotype in a tissue is controlled by its location and differentiation under the influence of various tissue microenvironmental conditions, which include mainly stem cell factor (SCF) and other cytokines[13, 14]. Historically, mast cells (MCs) were classified into 2 subtypes according to tryptic enzyme expression levels. MCs that produce the enzymes tryptase and chymase (MCTC) and that contain tryptase but not chymase (MCT). MCTC are prominent in connective tissue, whereas MCT are found in the mucosa[15–18].
In 1995, Patella et al.[19] isolated and purified human heart mast cells (HHMCs), human lung mast cells (HLMCs), and human skin mast cells (HSMCs) and reported that the phenotype of HHMCs was different from that of HLMCs and HSMCs.
Recently, Frossi et al.[20] reported that the mast cell phenotype was more variable and was dependent on the tissue residing in organs, such as the skin, lung, intestine, pancreas and kidney. Many investigators have reported that mast cells reside in the human heart, coronary arteries, and myocardium in relation to myocardial infarction or atherosclerosis and that the number of resident mast cells increases with several cardiac injuries.
In 1990, Stary[21] reported normal and atherosclerotic lesions in the coronary arteries of 691 subjects of <40 years of age and reported that mast cells in the normal coronary artery intima were rare, but mast cells in the intima were accompanied by the development of atherosclerosis. The number of adventitial mast cells in the intima was at least 10.
In 1995, Laine et al.[22] reported an article about the association between myocardial infarction and mast cells in the adventitia of the infarct-related coronary artery and noted that a significantly greater number of mast cells were present in the adventitia backing ruptured plaques (98±40 mast cells/mm2 , mean±SD) than in the adventitia backing nonruptured plaques (41±12 mast cells/mm2 ; p<0.001) or backing the normal intima (19±8 mast cells/mm2 ; p<0.001). Even in the normal segments of the infarct-related coronary artery, the mast cell density was greater (2-fold) than that in the corresponding segments of the control arteries. Based on these findings, they concluded that the entire adventitial layer of the infarct-related coronary artery was affected by an inflammatory process.
In our study of patients with ECPA, the adventitial mast cell count of the subepicardial large coronary artery was 96.0±27.2 mast cell /mm2 , and the right and left ventricular must cell counts were 13.6±4.2 mast cell / mm2 and 13.8±2.0 mast cell /mm2 , respectively. As a control heart of a patient without coronary inflammation (age 66 years, male), the adventitial mast cell count of the subepicardial large coronary artery was 7.0±0.8 mast cell /mm2 , and the right and left ventricular mast cell counts were 10.2±1.6 mast cell /mm2 and 8.2±1.7 mast cell /mm2 , respectively.
The increased number of mast cells in the adventitia of the coronary arteries of patients with ECPA was almost the same as that in the infarct-related coronary artery of Laine’s case (myocardial infarction), whereas the infiltration of eosinophils was not described in Laine’s report.
ECPA is a type I hypersensitivity (allergic) disease (i.e., immunoglobulin E [IgE]-mediated disease), characterized by mast cell activation and the infiltration of eosinophils with other inflammatory cells. In our previous study, adventitial eosinophilic inflammation appeared not only in a single coronary artery (mostly the LAD) but also in two coronary arteries (LAD, RC) or all three coronary arteries (LAD, RC and LCX). These findings suggest that the activation or transition to a new phenotype of resident mast cells in the adventitia of coronary arteries might not be uniform but rather be localized or segmental.
There are some reports concerning the immunological mechanism by which mast cells and eosinophils cross-talk with soluble mediators released by both cell types and affect each other[7–14]. These findings suggest that resident mast cells in the adventitia of coronary arteries are activated, assume a new phenotype to recruit eosinophils from the bloodstream, and ultimately result in the onset of an allergic reaction, such as IgE-mediated (type I hypersensitivity) disease.
Wong et al.[8] reported that the mast cell-specific protease chymase can induce eosinophil infiltration into the inflammatory site, and some investigators suggest that genetic, environmental, and immunological aspects are likely involved.
In recent years, considerable information has been obtained from the study of high-affinity receptor for IgE (FcεRI) and the dysregulation of mast cell function in the context of physiological consequences[23]. However, the exact etiology and pathogenesis of ECPA are not yet understood.
In 1964, Fernex and Sternby[24] studied mast cell counts of the human myocardium via a large number of autopsy series and reported that the mast cell count in the left ventricular myocardium ranged between 0.1 and 11.5 per mm2 . The cases with <1 mast cell per mm2 were said to have “few mast cells”, cases with 1–3 mast cells per mm2 were said to have “normal mast cell counts”, and cases with more than 3 mast cells per mm2 were said to have a “large number of mast cells” in their myocardium.
In our study, there were more than 3 mast cells in the right and left myocardia of the heart with ECPA and without cardiac inflammation per mm2 , which is considered to be a “large number of mast cells”, as proposed by Fernex and Sternby. The mast cell counts in both the right and left myocardia of patients with ECPA were slightly greater (13.6±4.2 mast cell / mm2 and 13.8±2.0 mast cell /mm2 , respectively) than those (10.2±1.6 mast cell /mm2 and 8.2±1.7 mast cell /mm2 , respectively) in the myocardium of patients without coronary infection. These differences in myocardial mast cell density (number) between patients with ECPA and without cardiac problems were considered to result from the influence of coronary artery inflammation.
With respect to the role of resident mast cells in the myocardium, it is now generally accepted that mast cells store and release several cytokines, some of which have been implicated in the activation of matrix metalloproteinases and in the fibrotic process[25–31]. Increased numbers of mast cells have been reported in explanted human hearts with dilated cardiomyopathy and in animal models of experimentally induced hypertension, myocardial infarction and chronic cardiac volume overload, and play a major role in the adverse remodeling underlying these cardiovascular disorders.
Article information
- Published
Copyright © 2026 Hiroki Kajihara. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 31#
- 1
Prinzmetal M, Kennamer R, Merliss R, Wada T, Bor N (1959) Angina pectoris. I. A variant form of angina pectoris; preliminary report. Am J Med 27:375-388. doi: 10.1016/0002-9343(59)90003-8
- 2
Kajihara H, Kato Y, Takanashi A, Nakagawa H, Tahara E, Otsuki T, Tsuchioka Y, Amioka H, Okamoto M, Matsuura H, Kajiyama G (1989) Periarteritis of coronary arteries with severe eosinophilic infiltration. A new pathologic entity (eosinophilic periarteritis)? Path Res Pract 184:46-52. doi: 10.1016/S0344-0338(88)80190-0
- 3
Kajihara H, Tachiyama Y, Hirose T, Takada A, Saito K, Murai T, Yasui W (2013) Eosinophilic coronary periarteritis (vasospastic angina and sudden cardiac death), a new type of coronary arteritis: report of seven autopsy cases and a review of the literature. Virchows Arch 462:239-248. doi: 10.1007/s00428-012-1351-7
- 4
Robinowitz M, Virmani R, McAllister HA Jr (1982) Spontaneous coronary artery dissection and eosinophilic inflammation: A cause and effect relationship? Am J Med 72:923-928. doi: 10.1016/0002-9343(82)90853-1
- 5
Virmani R, Forman MB, Robinowitz M, McAllister HA Jr (1984) Coronary artery dissections. Cardiol Clin 2:633-646. doi: 10.1016/S0733-8651(18)30715-X
- 6
Mandal R, Brooks EG, Corliss RF (2015) Eosinophilic coronary periarteritis with arterial dissection: The mast cell hypothesis. J Forensic Sci 60:1088-1092. doi: 10.1111/1556-4029.12752
- 7
Shakoory B, Fitzgerald SM, Lee SA, Chi DS, Krishnaswamy G (2004) The role of human mast cell-derived cytokines in eosinophil biology. J Interferon Cytokine Res 24:271-281. doi: 10.1089/107999004323065057
- 8
Wong CK, Ng SSM, Lun SWM Lun, Cao J, Lam CWK (2008) Signalling mechanism regulating the activation of human eosinophils by mast-cell-derived chymase: implications for mast cell-eosinophil interaction in allergic inflammation. Immunology 126:579-587. doi: 10.1111/j.1365-2567.2008.02916.x
- 9
Minai-Fleminger Y, Levi-Schaffer FL (2009) Mast cell and eosinophils: the two key effector cells in allergic inflammation. Inflamm Res 58:631-638. doi: 10.1007/s00011-009-0042-6
- 10
Abraham SN, St. John AL (2010) Mast cell-orchestrated immunity to pathogens. Nature Reviews, Immunology 10:440-452. doi: 10.1038/nri2782
- 11
Krystel-Wittemore M, Dileepan KN, Wood JG (2016) Mast cell: A multifunctional master cell. Front Immunol 1-12. doi: 10.3389/fimmu.2015.00620
- 12
Robida P, Puzzovio PG, Pahima H, Levi-Schaffer F, Bochner BS (2018) Human eosinophils and master cells: Birds of a feather flock together. Immunol Rev 282:151-167 doi: 10.1111/imr.12638
- 13
Li J, Lu H, Plante E, Melendez GC Levick SP, Janicki JS (2012) Stem cell factor is responsible for the rapid response in mature mast cell density in the acutely stressed heart. J Mol Cell Cardiol 53:469-474. doi: 10.1016/j.yjmcc.2012.07.011
- 14
Gangwar RS, Friedman S, Seaf M, Levi-Schaffer F (2016) Mast cells and eosinophils in allergy: Close friends or just neighbors. Eur J Pharmacol 778:77-83. doi: 10.1016/j.ejphar.2015.10.036
- 15
Irani AMA, Bradford TR, Kepley CI, Schechter NM, Schwartz LB (1989) Detection of MCT and MCTC types of the human mast cells by immune-histochemistry using new monoclonal anti-tryptase and anti-chymas antibodies. J Histochem Cytochem 37:1509-1515. doi: 10.1177/37.10.2674273
- 16
Sperr WR, Bankl HC, Mundigler G, Klappacher G, Grossschmidt K, Agis H, Simon P, Laufer P, Imhof M, Radaszkiewicz Th, Glogar D, Lechner K, Valent P (1994) The human cardiac mast cell: Location, phenotype, and functional characterization. Blood 84:3876-3884. doi: 10.1182/blood.V84.11.3876.bloodjournal84113876
- 17
Jeziorska M, McCollum C, Wolley DE (1997) Mast cell distribution, activation, and phenotype in atherosclerotic lesions of human carotid arteries. J Pathol 182:115-122. doi: 10.1002/(SICI)1096-9896(199705)182:1<115::AID-PATH806>3.0.CO;2-9
- 18
Hermans MAW, van Lennep JER, van Daele PLA, Bot I (2019) Mast cell in cardiovascular disease: From bench to bedside. Int J Mol Sci 20:3395. doi: 10.3390/ijms20143395
- 19
Patella V, de Crescenzo G, Ciccarelli A, Marino I, Adt M, Marone G (1995) Human heart mast cells: A definite case of mast cell heterogeneity. Arch Allergy Immunol 106:386-393. doi: 10.1159/000236871
- 20
Frossi B, Mion F, Sibilano R, Danelli L, Pucillo CEM (2018) Is it time for a new classification of mast cells? What do we know about mast cell heterogeneity? Immunol Rev 282:35-46. doi: 10.1111/imr.12636
- 21
Stary HC (1990): The sequence of cell and matrix changes in atherosclerotic lesions of coronary arteries in the first forty years of life. Eur Heart J 11(Suppl E):3-19. doi: 10.1093/eurheartj/11.suppl_E.3
- 22
Laine P, Kaartinen M, Penttila A, Panula P, Paavonen T, Kovanen P T (1999) Association between myocardial infarction and the mast cells in the adventitia of the infarct-related coronary artery. Circulation 99:361-369. doi: 10.1161/01.CIR.99.3.361
- 23
Rivera J, Gilfillan AM (2006) Molecular regulation of mast cell activation. J Allergy Clin Immunol 117:1214-1225. doi: 10.1016/j.jaci.2006.04.015
- 24
Fernex M, Sternby NH (1964) Mast cells and coronary heart disease, relationship between number of mast cells in myocardium, severity of coronary atherosclerosis and myocardial infarction in an autopsy series of 672 cases. Acta Pathol Microbiol Scand 62:525-538. doi: 10.1111/apm.1964.62.4.525
- 25
Li Q-Y, Raza-Ahmad, MacAulay MA, Lalonde LD, Rowden G, Trethewey F, Dean S (1992) The relationship of mast cells and their secreted products to the volume of fibrosis in posttransplant hearts. Transplantation 53:1047-1051. doi: 10.1097/00007890-199205000-00015
- 26
Patella V, de Crescenzo G, Lamparter-Schummert B, de Rosa G, Adt M, Marone G (1997) Increased cardiac mast cell density and mediator release in patients with dilated cardiomyopathy. Inflamm Res 46 (suppl I), S31-S32. doi: 10.1007/s000110050041
- 27
Shi GP, Bot I, Kovanen PT (2015) Mast cells in human and experimental cardiometabolic diseases. Nat Rev Cardiol 12:643-658. doi: 10.1038/nrcardio.2015.117
- 28
Janicki JS, Brower GL, Levick SP (2015) The emerging prominence of the cardiac mast cell as a potent mediator of adverse myocardial remodeling. Methods Mol Biol 1220:121-139. doi: 10.1007/978-1-4939-1568-2_8
- 29
Levic SP, Widiapradja A (2018) Mast cells: Key contributors to cardiac fibrosis. Int J Mol Sci 19:231-248. doi: 10.3390/ijms19010231
- 30
Jin J, Jiang Y, Chakraberti S, Su (2022) Cardiac mast cells: A two-head regulator in cardiac homeostasis and pathogenesis following injury. Front Immunology 13:963444. doi: 10.3389/fimmu.2022.963444
- 31
Mamazhakypov A, Maripov A, Sarybaev AS, Schermuly RT, Sydykow A (2024) Mast cells in cardiac remodeling: Focus on the right ventricle. J Cardiovasc Dev Dis. 11:54. doi: 10.3390/jcdd11020054