Pancreatic body and tail cancer with multiple liver metastases cured by precision immunochemotherapy: a case report
Taizo Hoshino1 ✉
Kazutoshi Kaketani2
Kazutoshi Kaketani- 2 Hanzoumon Ichou Clinic, Tokyo, Japan
Takao Itoi3
Takao Itoi- 3 Tokyo Medical University Department of Gastroenterology and Hepatology, Tokyo, Japan
Yuichi Nagakawa4
Yuichi Nagakawa- 4 Tokyo Medical University Gastrointestinal and Pediatric Surgery, Tokyo, Japan
Tetsu Fukunaga5
Tetsu Fukunaga- 5 Esophageal & Gastroenterological Surgery, Juntendo University, Tokyo, Japan
Hajime Orita5
Hajime Orita- 5 Esophageal & Gastroenterological Surgery, Juntendo University, Tokyo, Japan
Tadashi Okabe6
Tadashi Okabe- 6 Okabe Clinic, Tokyo, Japan
Show affiliations (6)
- 1Premiere Clinic, Tokyo, Japan
- 2Hanzoumon Ichou Clinic, Tokyo, Japan
- 3Tokyo Medical University Department of Gastroenterology and Hepatology, Tokyo, Japan
- 4Tokyo Medical University Gastrointestinal and Pediatric Surgery, Tokyo, Japan
- 5Esophageal & Gastroenterological Surgery, Juntendo University, Tokyo, Japan
- 6Okabe Clinic, Tokyo, Japan
Published
Abstract
A 63 years-old female patient was found elevated CA19-9 levels during treatment for diabetes mellitus and further examinations led to a diagnosis of pancreatic body and tail cancer with multiple liver metastases. We performed whole-exome sequencing using a biopsy specimen and identified 70 somatic mutations, a part of which indicated generation of possible neoantigens in cancer cells. We then selected seven neoantigens that were predicted to have the high affinity to HLA molecules and administered 18 doses of neoantigen peptide-pulsed dendritic cell vaccine therapy as precision immunotherapy in addition to chemotherapies. CT images taken 3 years and 3 months later revealed the disappearance of both the primary tumor in the pancreas and all the liver metastases. Finally, we performed surgical resection of pancreatic tumor and confirmed the absence of cancer cells in the resected pancreas. Here, we report a case of advanced pancreatic cancer with multiple liver metastases where a combination therapy of precision immunochemotherapy and chemotherapy was effective, resulting in complete pathological remission confirmed in the surgically resected tissue.
1 Introduction#
In recent years, gemcitabine plus nab-paclitaxel (GEM+nab-PTX) and FOLFIRINOX have shown certain tumor suppressive effects against advanced metastatic pancreatic cancer, but it remains challenging to achieve medium- to long-term progression-free survival[1-5]. On the other hand, immunotherapy using genomic information has shown signs of improved response rates[6,7]. Immunochemotherapy is therefore expected as an important modality of a multidisciplinary treatment for refractory cancers[8-11]. Here, we report a case of pancreatic body and tail cancer with multiple liver metastases in which complete disappearance of primary and metastatic lesions was confirmed in the surgical specimen after a combination of precision immunotherapy and chemotherapy.
2 Materials and Methods#
Whole-exome sequencing and neoantigen prediction were performed as previously reported[12]. For the immunotherapies, PBMCs were obtained from the patient using leukapheresis, and then prepared activated T lymphocytes or neoantigen peptide-pulsed DCs were prepared following the protocols[8,9,12]. Genomic and neoantigen analyses, cell processing, and immunotherapy procedures were approved by the ethics committee of our institution. Written informed consent was obtained from the patient for the inclusion of their medical and treatment history as well as clinical images in this case report, in accordance with the Act on Securement of Safety of Regenerative Medicine in Japan.
3 Results and Discussion#
A 63-year-old woman presented to our hospital with a chief complaint of elevated CA19-9 levels that were detected during treatment for diabetes mellitus. She had a history of uterine corpus cancer (hysterectomy) at age 53, but with no recurrence. Nothing particular in her social history and family history. She was diagnosed with pancreatic body and tail cancer with multiple liver metastases (histological type is adenocarcinoma with squamous differentiation) based on computed tomography (CT) scans and histological examination of the biopsy sample (Figure 1A-1D). Blood test results at the time of visit to our clinic were as follows: total bilirubin (T-Bil) 0.4 mg/dL, aspartate transaminase (AST) 17 IU/L, alanine aminotransferase (ALT) 18 IU/L, gamma-glutamyl transpeptidase (γ-GTP) 25 IU/L, alkaline phosphatase (ALP) 361 IU/L, lactate dehydrogenase (LDH) 166 IU/L, creatinine (Cr) 0.49 mg/dL, white blood cells (WBC) 6100/µL, red blood cells (RBC) 430×104/µL, and CA19-9 820 U/mL. On pre-treatment CT, a 4×5-cm mass was found in the pancreatic body and tail as a primary tumor, and 1- to 2-cm metastatic masses were found in segments 4, 5, and 6 of the liver (Figure 1D upper). Since the long-term progression-free survival was generally not expected for stage IV pancreatic cancer (the 5-year survival rate of 1-2 percent) under chemotherapy[1-5], considering that patient’s performance status (PS) was 0, we provided immunotherapy combined with chemotherapy as a multidisciplinary approach for the purpose of improving treatment outcome.
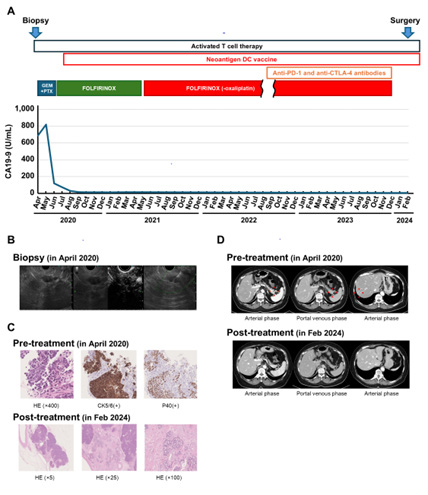
From April 2020, 2 cycles of GEM+nab-PTX were provided, but since tumors showed the progression, we switched to FOLFIRINOX. We removed oxaliplatin from the FOLFIRINOX regimen due to severe bone marrow suppression and peripheral neuritis after 13 cycles. We provided FOLFIRINOX (-oxaliplatin) in the two-week interval at the beginning but sometimes extended to up to the six-week interval when the adverse events became severe. As of the end of December 2023, a total of 37 cycles of chemotherapy were administered.
For personalized neoantigen peptide-pulsed dendritic cell (DC) vaccine, we extracted genomic DNAs from the tumor biopsy and normal control samples, and applied for whole-exome sequencing[12]. We identified 70 somatic mutations including 43 missense/indel mutations that substituted amino acids (Table 1). We also defined her HLA class I genotypes to be A2401/ A3101, B3901/B5502, and C0102/C0702, and used for prediction of possible neoantigens that are likely to bind to each of 6 HLA class I types with the affinity of <500 nM. Among 115 neoantigen peptides predicted, we selected 7 candidate peptides in LTBP2, PLEKHH2, SLC22A15, NISCH, ZNRF3, COL18A1, and FAAH2, which showed the HLA binding affinity of <50 nM (Table 2).
Table 1 Summary of whole-exome sequencing and neoantigen prediction.
| Mutations/neoantigens | N |
|---|---|
| Somatic mutationsa | 70 |
| Somatic mutations with amino acid changes | 43 |
| Predicted neoantigen peptidesb | 115 |
a Number of somatic mutations including insertions, deletions, and nonsense/missense mutations. b Number of neoantigen peptides predicted to bind to HLA class I (HLA-A, -B and -C) with the affinity of <500 nM (including different lengths of peptide sequences derived from the same mutation).
Table 2 List of neoantigen peptides used for the treatment
| No. | Gene | Amino acid change | Neoantigen peptide | Wild-type peptide | HLA alleleb | ||||
|---|---|---|---|---|---|---|---|---|---|
| Peptide length | Position of amino acid changea | Amino acid sequence | Predicted binding affinity to HLA [nM] | Amino acid sequence | Predicted binding affinity to HLA [nM] | ||||
| 1 | LTBP2 | G1673W | 9 | 6 | IYGPDWAPF | 13 | IYGPDGAPF | 61 | A24:02 |
| 2 | PLEKHH2 | S549Y | 11 | 3 | FPYWESRIYAV | 13 | FPSWESRIYAV | 36 | B55:02 |
| 3 | SLC22A15 | L281Q | 11 | 5 | CTFSQTHPANR | 16 | CTFSLTHPANR | 13 | A31:01 |
| 4 | NISCH | I1483L | 8 | 3 | KLLSLLAR | 25 | KLISLLAR | 26 | A31:01 |
| 5 | ZNRF3 | H331Y | 9 | 2 | AYRCGLEHR | 29 | AHRCGLEHR | 1,360 | A31:01 |
| 6 | COL18A1 | H1275Y | 11 | 4 | VQLYDSNPYPR | 42 | VQLHDSNPYPR | 56 | A31:01 |
| 7 | FAAH2 | P234R | 11 | 1 | RAFFNGIFGHK | 46 | PAFFNGIFGHK | 4,155 | A31:01 |
a Position of a mutated amino acid in each neoantigen peptide (N-terminus is 1). b Predicted affinity of neoantigen peptide to each HLA molecule.
While conducting genomic analysis and neoantigen peptide synthesis from early April to the end of June 2020, activated autologous T lymphocytes were infused biweekly (a total of 4 times) as an adjunct to chemotherapy during the chemotherapy intervals (Figure 1A). From early July 2020, neoantigen peptide-pulsed DC vaccine (a total of 12 doses of about 2 months-interval) was administered via subcutaneous and axillary lymph node injections. Additionally, activated autologous T lymphocyte therapy was continued in combination with chemotherapy and neoantigen peptide-pulsed DC vaccine. As an adjuvant[8,9], low-dose anti-PD-1 antibody (12.5 mg) and extremely low-dose anti-CTLA-4 antibody (1 mg) begun to be administered by intravenous infusion in mid-August 2022. Because of the normalization of CA19-9 levels and the imaging results, a combination of anti-PD-1 antibody and anti-CTLA-4 antibody was suspended at early December 2023. After the surgical resection, neoantigen peptide-pulsed DC vaccines was further administered along with activated autologous T lymphocyte therapy (6 times in total).
CA19-9 levels were initially 800 U/mL and rapidly decreased after starting immunochemotherapy, reducing to normal levels within 5 months (Figure 1A). For the past 3 years and 7 months, we have not observed the elevation of CA19-9. CT images in February 2024 also showed the disappearance of the primary tumor as well as the liver metastatic masses (Figure 1D lower). Blood test results at that time were as follows: T-Bil 0.3 mg/dL, aspartate aminotransferase 14 IU/L, alanine transaminase 16 IU/L, γ-glutamyltransferase 35 IU/L, alkaline phosphatase 153 IU/L, acetate dehydrogenase 168 IU/L, creatinine 0.47 mg/dL, white blood cell count 4500/μL, red blood cell count 418×104/μL, and we then performed partial resection of the pancreas and liver, and confirmed complete pathological remission of her tumors (Figure 1C lower). Currently, the patient has been engaging in social activities with good quality of life, and there have been no signs of recurrence.
Although pancreatic cancer has a very poor prognosis, our case of pancreatic cancer with multiple liver metastases remaining disease-free at 3 years and 7 months after the beginning of chemotherapy is extremely rare compared with reported median overall survivals of 6.7-11.1 months under chemotherapy[4,5]. In this case, we provided multidisciplinary immunotherapies, including neoantigen peptide-pulsed DC vaccination, low-dose immune checkpoint inhibitors, and activated autologous T lymphocyte therapy in combination with chemotherapy. Considering the immune cascade following neoantigen administration[6-9], the use of anti-PD-1 and anti-CTLA-4 antibodies was deemed necessary. The decision on how long to continue chemotherapy after tumor disappearance was left to pathological examination through surgery, given that cases of long-term survival and complete cure of pancreatic cancer with multiple liver metastases are rare. Further studies will be needed to determine the duration of neoantigen peptide-pulsed DC vaccine therapy by evaluating the persistence of the efficacy through the immunological peptide activity in peripheral blood.
4 Conclusion#
We found a case of advanced pancreatic cancer who showed the sensitivity to precision immunotherapy combined with chemotherapy resulted in remarkable effectiveness contributing to long-term disease-free survival. In the future, personalized neoantigen vaccines are considered to be promising from the perspective of immunological anti-tumor effects.
Declarations
✎Author contributions
♥Acknowledgements
Article information
- Published
Copyright © 2025 Taizo Hoshino, M.D., Ph.D. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. CC BY 4.0 · Corrections policy
References 12#
- 1
Okusaka T, Furuse J. Recent advances in chemotherapy for pancreatic cancer: evidence from Japan and recommendations in guidelines. J Gastroenterol. 2020;55(4):369–382.
- 2
Di Costanzo F, Di Costanzo F, Antonuzzo L, et al. Optimizing first-line chemotherapy in metastatic pancreatic cancer: efficacy of FOLFIRINOX versus nab-paclitaxel plus gemcitabine. Cancers (Basel). 2023;15(2):416.
- 3
Lee HS, Park SW. Systemic chemotherapy in advanced pancreatic cancer. Gut Liver. 2016;10(3):340–347.
- 4
Conroy T, Desseigne F, Ychou M, et al. FOLFIRINOX versus gemcitabine for metastatic pancreatic cancer. N Engl J Med. 2011;364(19):1817–1825.
- 5
Von Hoff DD, Ervin T, Arena FP, et al. Increased survival in pancreatic cancer with nab-paclitaxel plus gemcitabine. N Engl J Med. 2013;369(18):1691–1703.
- 6
Ott PA, Hu-Lieskovan S, Chmielowski B, et al. A phase Ib trial of personalized neoantigen therapy plus anti-PD-1 in patients with advanced melanoma, non-small cell lung cancer, or bladder cancer. Cell. 2020;183(2):347-- 362.
- 7
Rojas LA, Sethna Z, Soares KC, et al. Personalized RNA neoantigen vaccines stimulate T cells in pancreatic cancer. Nature. 2023;618(7963):144–150.
- 8
Seya T, Takeda Y, Takashima K, et al. Adjuvant immunotherapy for cancer: both dendritic cell-priming and check-point inhibitor blockade are required for immunotherapy. Proc JpnAcad Ser B Phys Biol Sci. 2018;94(3):153–160.
- 9
Sakuma K, Kii T, Takahashi H, et al. An in vivo study of local administration of low-dose anti-PD-1 antibody using an oral cancer cell line. Anticancer Res. 2022;42(9):4293–4303.
- 10
Zhou X, Mo X, Qiu J, et al. Chemotherapy combined with dendritic cell vaccine and cytokine-induced killer cells in the treatment of colorectal carcinoma: a meta-analysis. Cancer Manag Res. 2018;10:5363–5372.
- 11
Kakimoto T, Miura O, Matsuoka K, et al. [A case of postoperative liver metastasis of pancreatic cancer achieved long-term survival through multidisciplinary treatment]. Pancreas. 2019;34:172–180. [Japanese].
- 12
Morisaki T, Hikichi T, Onishi H, et al. Intranodal administration of neoantigen peptide-loaded dendritic cell vaccine elicits epitope-specific T cell responses and clinical effects in a patient with chemorefractory ovarian cancer with malignant ascites. Immunol Invest. 2021;50(5):1–18.